
What Actually Works When You're Coding Orthopedic Procedures
I've spent more years than I care to count trying to get orthopedic surgery codes right. There's no shortcut that makes every case simple. The closest thing to a reliable method is having a solid Orthopedic Surgery Coding Cheat Sheet you can reference quickly during a busy coding session instead of digging through the entire CPT book every time. Most people start by copying whatever they find online and printing it out. That rarely works well in practice because the cheat sheet becomes too broad and you end up flipping through pages looking for something that might not even apply to your case. I learned this the hard way early in my career when I had a 47-page laminated sheet sitting next to my desk and still missed a modifier on a fracture treatment case that led to a denial and a 3-week delay before we figured out what went wrong. The approach that actually saved me time organizes the sheet by surgical scenario rather than by code range. Here's how I structured mine and what ended up sticking:
Core Sections Every Sheet Needs
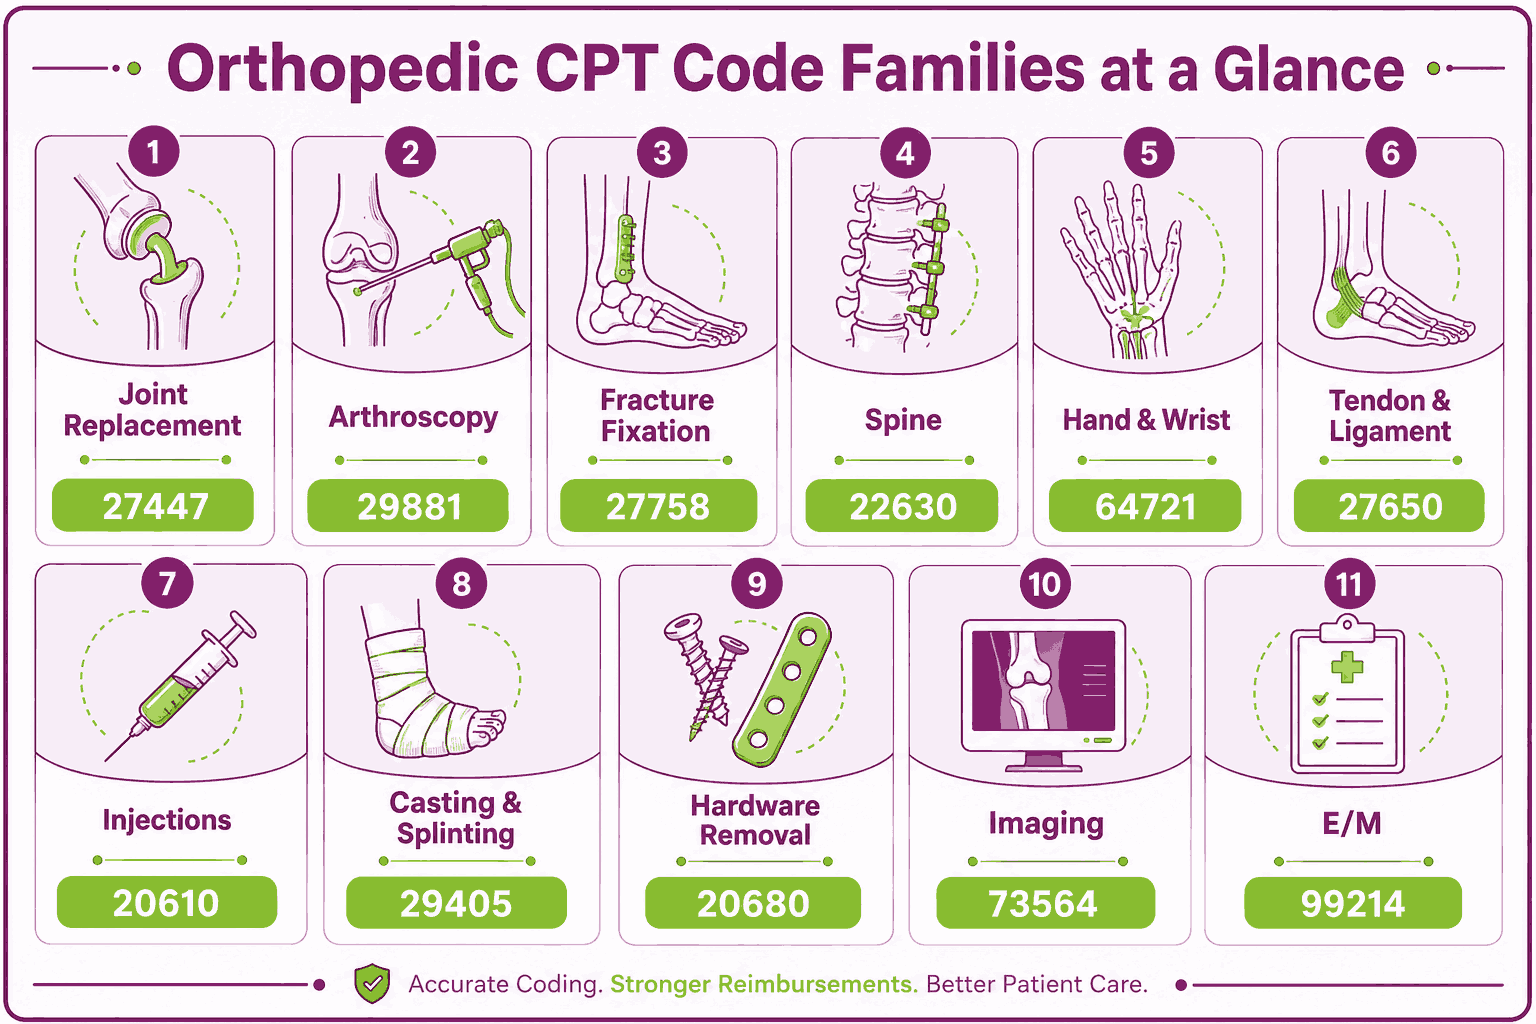
Fracture management—This is where the most denials happen. You need the distinction between closed and open treatment clearly laid out with the associated ICD-10 modifiers. I put the common encounter modifiers (initial, subsequent, sequela) on the front page along with the fracture type codes. The specific codes that trip people up repeatedly are the ones involving manipulation under anesthesia. If the provider performs a separate manipulation, you add 59 or XE modifier depending on payer, but only if documentation explicitly supports it as a distinct procedural service. Arthroscopic procedures—Meniscectomy versus meniscus repair is the classic coding trap. A medial meniscectomy is 29881. A medial meniscus repair is 29883. These look identical in the operative report unless you read the actual procedure description carefully. The surgeon may say "meniscus surgery" in the summary and both are true. You have to look at what was actually done—shaved versus sutured. I keep a quick lookup table showing the arthroscopy codes with their specific indications right on the sheet. Joint replacement—The total joint arthroplasty codes have multiple components that interact with each other. You have the primary procedure, then there's the question of whether it's unilateral or bilateral, and then the global period considerations. The big one people miss is the distinction between primary total hip arthroplasty (27238) and revision total hip arthroplasty (27130). If the operative report mentions removing old hardware or dealing with a previous prosthesis, you need to be using the revision codes. I learned this after a claim got denied for a revision hip that was coded as a primary. The documentation clearly stated prior hardware removal and cement extraction. Should have caught it on first pass.
Soft tissue procedures—Carpal tunnel release codes are straightforward until they aren't. Endoscopic carpal tunnel release (29822) versus open release (25077) requires documentation of the approach method. If the surgeon notes "endoscopic" anywhere in the report, use 29822. If the approach is open regardless of incision size, it's 25077. The reimbursement difference matters, but so does the documentation requirement. Endoscopic codes need explicit documentation that the endoscopic technique was used.
Get the Full Details
Modifier Usage That Actually Matters
The modifiers I reference most frequently on my sheet are 50 (bilateral procedure), 59 (distinct procedural service), XT (separate structure), and 62 (two surgeons). These come up constantly in orthopedic cases. Modifier 59 versus modifier XT is worth special attention. Medicare started requiring XT in addition to 59 for many contexts. Some payers accept one or the other. Your cheat sheet should note which modifier your primary payers accept. I stopped trying to memorize this per payer and just kept a small table showing modifier acceptance by major payer on the back of the sheet.
A Realistic Problem I Faced
There was a case involving a shoulder arthroscopy where the surgeon performed both a rotator cuff repair and a distal clavicle excision. The initial code selection looked correct on the surface. But the bundling rules for these two procedures mean you cannot bill them separately without justification. The CCI edits would typically bundle the distal clavicle excision into the rotator cuff repair. I had to document that the procedures were performed at separate anatomical sites and modify accordingly. This is one of those edge cases where the cheat sheet wasn't enough—I needed to pull the actual CCI edit table and cross-reference the specific codes. The workaround was creating a separate reference section for bundled procedure pairs with the correct unbundling modifier usage. I added about 15 of these high-frequency bundled pairs to my sheet and it cut the review time for shoulder and knee arthroscopy cases from around 20 minutes down to roughly 5 minutes per case. No cheat sheet solves documentation problems. If the operative report is vague—saying things like "debridement performed" without specifying what tissue, how much, or the anatomical location—you will code it wrong regardless of what reference material you have. The single biggest bottleneck I've seen is incomplete operative notes. A good cheat sheet gets you to the right code faster. It cannot compensate for a surgeon who writes "procedure performed satisfactorily" as the entire operative report. There's also the issue of payer-specific rules. Medicare's guidelines differ from commercial payer guidelines on many orthopedic codes. An Orthopedic Surgery Coding Cheat Sheet that works perfectly for one payer environment may produce incorrect codes in another. I maintain two versions—one optimized for Medicare rules and one for the commercial payers we deal with most often. The differences are mostly in the global period handling and modifier requirements, but they add up across volume.
Practical Maintenance Tips
Update the sheet at least quarterly. CPT changes come out annually in October, and ICD-10 updates happen every October as well. Modifier guidance shifts periodically based on payer policy changes. I set a calendar reminder every 90 days to review my sheet against any published updates from CMS and the AAPC. The time investment is usually about 30 minutes, and it prevents the kind of systematic errors that show up in monthly audit reports. Keep the physical sheet at the workstation, not buried in a drawer. The whole point is quick reference during active coding. If you have to search for it, you've already lost the efficiency gain. I keep mine printed on cardstock and laminated. It survives actual daily use for about eight months before the edges start wearing down. That's acceptable.

.webp "Orthopedic CPT Codes: The Complete Cheat Sheet")


