Why People Keep Asking About Orton Gillingham Speech Therapy
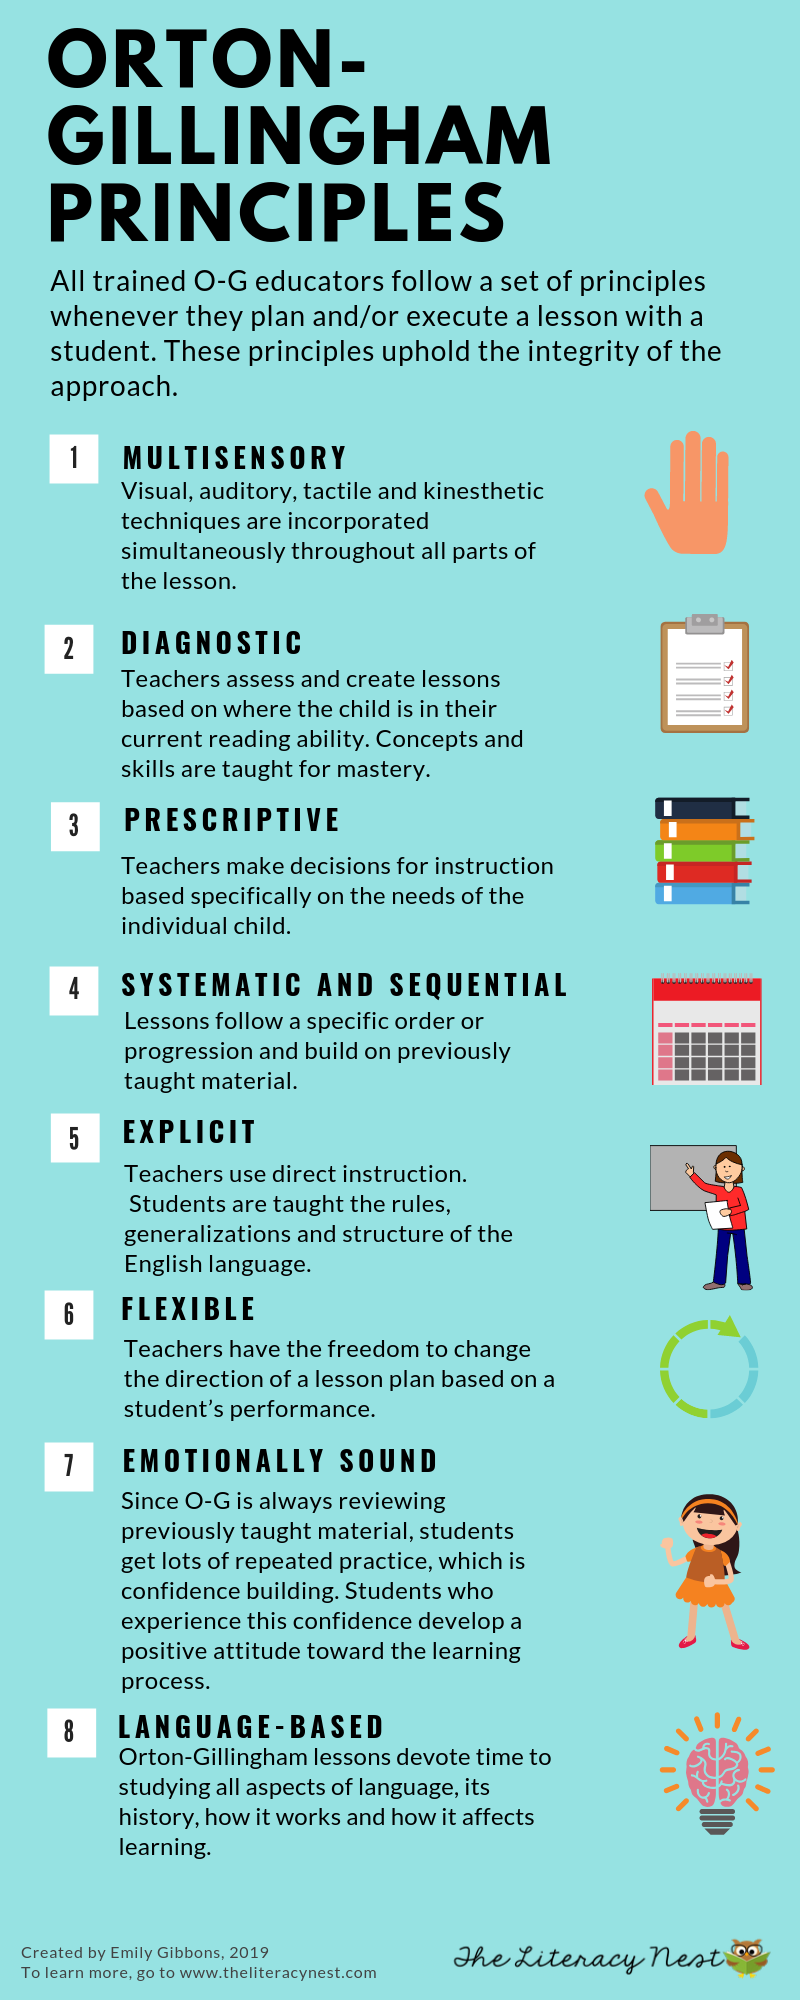
Orton-Gillingham is a structured literacy approach. It was designed for reading and spelling, not speech or language production. When parents and clinicians search for Orton Gillingham Speech Therapy, they are usually looking for something that doesn't quite exist as a standalone thing. What actually happens is that therapists borrow OG principles and apply them alongside speech work. The result can be effective, but only if you understand what OG gives you and what it does not. The core of Orton Gillingham is multi-sensory, systematic, cumulative instruction in phonology, syllable types, morphology, and decoding. A typical session moves from sound manipulation to letter mapping to blending, then to decodable text, and finally to dictated words or sentences. Speech therapy touches this when a client has concurrent phonological processing weakness, dyslexia-related decoding, or language-based learning disabilities that overlap with articulation and language disorder. The therapist integrates the two. That integration is where people get confused. I worked with a nine-year-old who had moderate phonological impairment and a formal dyslexia profile. His auditory discrimination was poor enough that minimal pair work alone stalled for months. I folded in OG-style phoneme segmentation and grapheme mapping before we touched articulation drills. The sound production changed faster once he could actually see and manipulate the phonemic structure rather than trying to copy it by ear. That is not a universal rule. It depends on whether the client's bottleneck is auditory processing, motor planning, or receptive language. Pick the right one and you save weeks. Pick the wrong one and you burn through a child's patience.
What Orton Gillingham Speech Therapy actually looks like
Here is a practical breakdown of how a combined session runs in my experience. Start with phonological awareness at the sound level. This includes isolating, blending, and segmenting phonemes. Move into orthographic mapping by pairing each sound with its letter representation. Then work through syllable patterns. After that, layer in morphological units like prefixes, suffixes, and root words. If speech goals are part of the plan, you embed the target phonemes or sound sequences into the OG routine rather than treating them separately. Dictation ties it together by assessing both decoding and encoding simultaneously. The timeline matters. A typical OG block takes twenty to thirty minutes before fatigue sets in for most school-age clients. Speech motor practice adds cognitive load, so most clinicians cap the combined block at forty-five minutes unless the child has strong stamina and working memory. Anything longer and accuracy drops sharply. I have seen it happen repeatedly. The last ten minutes of a long session are usually noise.
Integrating speech goals into the OG framework
Choose your target sounds strategically. Do not pick sounds that do not appear in the phonograms or syllable types you are covering that day. If your client is working on /r/ and your scope and sequence has no words containing that phoneme, you are adding friction without benefit. Instead, build a custom word list that hits both the OG pattern and the speech target. For example, if you are teaching the closed syllable pattern and the client needs /k/ and /s/, use words like pack, desk, miss, and sock. The client practices the sound in a context that reinforces the literacy skill. Efficiency goes up. Transfer becomes more likely. Morphology changes the equation for older students. A teenager with late-identifying dyslexia often cannot keep up with phoneme-by-phoneme mapping at the speed required. They need structure. Teaching them that un-, re-, and -less are prefixes that attach to base words, and that these units carry meaning, reduces cognitive load dramatically. I had a fourteen-year-old who could decode CVC words but froze on anything longer. Once I introduced Greek and Latin roots alongside the OG scope, her reading speed doubled within three months. It was not magic. It was systematic exposure to recurring patterns.
Get the Full Details

Tools, resources, and where to find them
The OG approach has a large ecosystem of published materials. Core programs include Wilson Reading System, Fundations, and SPIRE. These are structured around the same principles with different pacing and scope. For speech-integrated work, many clinicians build their own supplemental materials. Digital tools like ReadWriteThink, PhonicHero, and online syllable sort generators help with practice, but they do not replace direct instruction. The human element, correcting mapping errors in real time, is non-negotiable. If you are looking for downloadable resources, the International Dyslexia Association and the Council for Exceptional Children have free scope and sequence outlines. Several university programs publish sample lesson templates under open licenses. Search for Orton Gillingham Speech Therapy and you will find scattered blogs, Pinterest boards, and a few commercial vendors repackaging OG worksheets. Most of them are too generic to be useful in a clinical setting. I recommend sticking to established programs or building your own word lists tailored to the client's phonological profile. It takes longer upfront and pays off immediately after.
Pitfalls that wreck OG-based speech integration
The biggest mistake I see is treating OG as a reading program that somehow fixes speech issues without actual integration. You cannot assign a decoding workbook and expect articulation to improve. The two skills must share the same session, the same targets, and the same corrective feedback loop. If the phoneme is incorrect, you correct it during mapping. You do not note the error and come back to it next week. Another common failure point is skipping phonological awareness when the client already has weak phonemic skills. Some clinicians rush straight to letter-sound correspondence because it feels more productive. It is not. Without solid phoneme segmentation, mapping is rote memorization. The client learns the symbol but not the structure. I once had a seventh grader who could spell phonetically in a bizarre way. She mapped sounds but could not segment multisyllabic words. We went back to auditory discrimination and syllable clapping for four weeks. Her decoding improved more in those four weeks than it had in the prior six months of mapping work. Assessment quality also determines success. If you are only using curriculum-based measures from a publisher, you are missing clinical nuances. Dynamic assessment, where you test learning potential during a mini-lesson, gives you far better data. You can see whether the client struggles with retrieval, with mapping, or with motor output. Each problem requires a different adjustment.
When OG integration does not work and what to do instead
There are scenarios where a combined approach fails. Clients with severe apraxia of speech often cannot sustain the phonological manipulation demands that OG requires. Their motor planning deficits are not helped by additional auditory discrimination tasks. In those cases, you separate the programs entirely. Use Motor Learning approaches like PROMPT or DTTC for speech, and run a standalone OG reading program on a different schedule. Mixing them muddies the diagnosis and slows progress on both fronts. Similarly, clients with primary receptive language disorders, not dyslexia, may not benefit from heavy OG integration. Their bottleneck is comprehension and syntax, not phonological processing. Adding decoding drills to speech therapy in these cases is inefficient. Focus on expressive and receptive language goals with explicit vocabulary instruction. Use reading materials at an appropriate level for comprehension practice rather than decoding instruction. Executive function deficits can also derail OG-based sessions. A child who cannot hold multiple phonemes in working memory will struggle with segmenting and blending regardless of how multi-sensory the approach is. In those cases, you reduce the span. Start with two-phoneme segments instead of three. Use visual scaffolding heavily. Accept slower pacing. Pushing through does not help. It just creates frustration and avoidance.

Practical session structure for a combined approach
Here is a template that works reliably for most school-age clients with co-occurring phonological impairment and dyslexia indicators. Open with three minutes of oral phonological warm-up. Blend and segment sounds without letters. Move to five minutes of letter-sound review for previously taught phonograms. Introduce two to three new phonograms with multi-sensory mapping. Spend ten minutes on decodable text that contains the new patterns. Add targeted speech practice using words that include the new phonograms and the client's speech targets. Finish with five minutes of dictation covering both encoding and the speech goal. Close with a quick oral summary. Total time: thirty minutes to forty minutes depending on complexity. Document everything. Not just accuracy rates, but error patterns. Are the errors on retrieval, on mapping, or on motor execution? That distinction determines your next step. If the same phoneme is misspelled and misarticulated consistently, you have found a shared deficit. Work on it together. If the spelling is correct but the speech sound is wrong, you have a motor planning issue that needs separate intervention. Split the focus. Do not confuse the two.