Osmosis isn't some abstract textbook concept. It's the reason your cell culture medium works or fails.
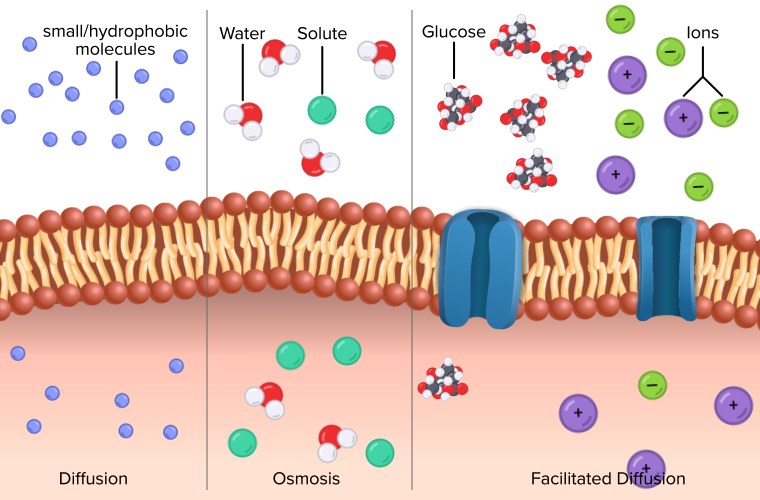
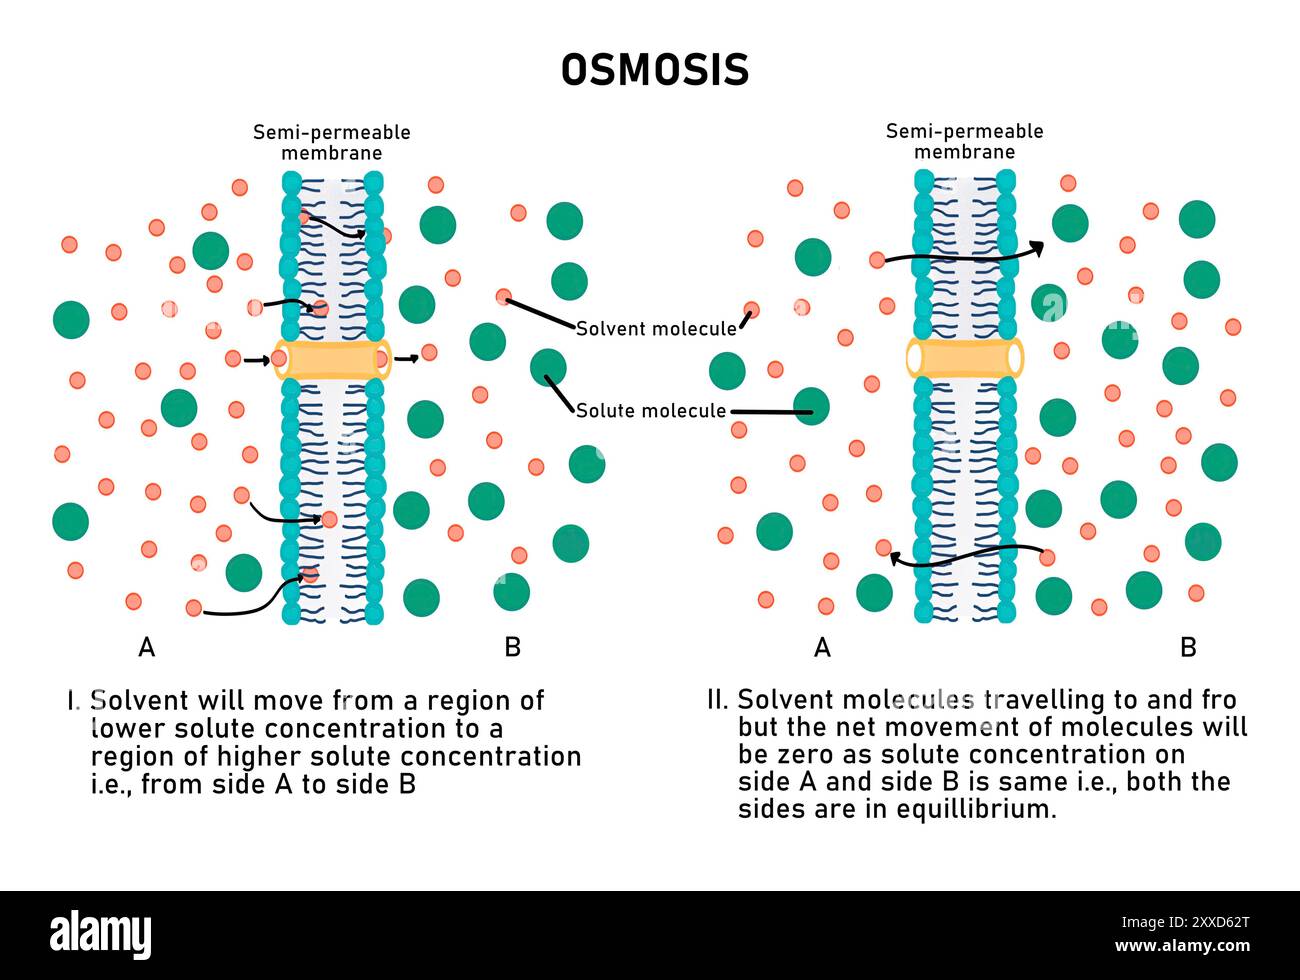
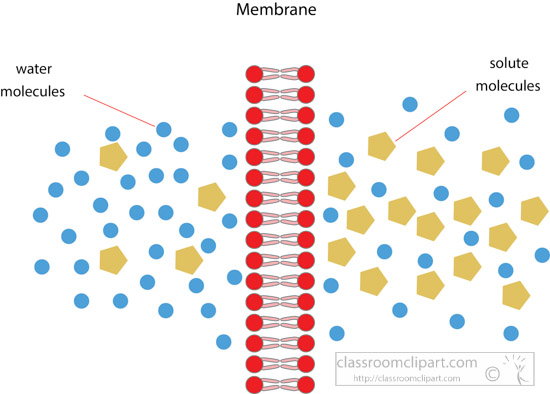
Most people learn osmosis as "water moves from low solute to high solute." That's technically wrong and it will cost you when you're actually working with cells. Water moves to equalize chemical potential, which is not the same thing. Solutes don't act like magnets pulling water—they change the activity of the solvent. The direction of net water flow depends on the water potential gradient across the membrane, and that gradient is shaped by every ion, sugar, and protein in solution. Get that wrong and you wonder why your cells are shriveling or lysing when the numbers on paper looked fine. The cell membrane is selectively permeable. That phrase gets thrown around in every intro biology class, but it's where most people fall apart. Small uncharged molecules like oxygen and CO2 diffuse right through the lipid bilayer. Water gets through because aquaporins are everywhere in most mammalian cell membranes, though they're absent in some specialized tissues. Glucose needs transporters. Ions need channels or pumps. And large molecules like proteins don't cross at all unless you're doing something intentional like electroporation or using fusogenic lipids. The practical consequence is that osmosis in a real cell environment isn't just about one solute. It's about tonicity, which combines the concentration of all impermeant solutes on both sides. If you make a solution isotonic based on total osmolarity but half those solutes can cross the membrane, the cell will still swell and burst. NaCl is impermeant—good for holding tonicity. Urea is permeant—it crosses freely and doesn't contribute to effective osmotic pressure over time. I've seen med students lose points on board questions specifically because they confused osmolarity with tonicity, and I've seen lab techs waste weeks of culture work because they made the same mistake on the bench.
Here's the edge case nobody teaches you. When you prepare a hypertonic solution for an experiment—say, 600 mOsm by adding NaCl—the actual osmotic pressure isn't exactly what the van't Hoff equation predicts. NaCl dissociates into Na+ and Cl-, sure, but the activity coefficient drops as concentration increases. At 150 mOsm (physiologic range), the osmotic coefficient for NaCl is about 0.93. At 600 mOsm it drops to roughly 0.88. That means if you calculate 300 mOsm of NaCl and expect 300 mOsm of osmotic effect, you're off by about 12%. In most routine work that doesn't matter. In membrane biophysics experiments where you're measuring water flux through single aquaporin channels, that 12% difference is the entire experiment. I learned this the hard way when I was running osmotic shock assays on red blood cells and the lysis curves didn't match predicted values. We ended up measuring osmolality with a vapor pressure osmometer instead of calculating it, and everything fell into place. The takeaway: always verify osmolality with a meter, never trust calculated values above 300 mOsm.
How to Think About Water Movement Through Real Membranes
Water flux follows this relationship: Jv = Lp × × . Don't let the symbols scare you. Jv is volumetric water flow per unit area. Lp is the hydraulic conductivity of the membrane—that's how easily water actually passes through, which depends on aquaporin density and lipid composition. is the reflection coefficient, which ranges from 0 to 1 and tells you how "impermeant" a solute is from the water's perspective. is the osmotic pressure difference. If is 1, the solute is completely reflected—water can't carry it across, so full osmotic effect. If is 0, the solute crosses as easily as water—no osmotic effect at all. Urea is the classic example of a low-reflection-coefficient solute. In many cell membranes, for urea is around 0.2 to 0.4. That means a 100 mOsm difference in urea creates only 20 to 40 mOsm worth of effective osmotic driving force. Your cells will behave almost as if there's no gradient at all, at least initially, because urea diffuses in faster than water can follow. But then the urea inside the cell raises the internal osmolarity and water rushes in afterward. The result is a biphasic response: initial slight shrinkage as water leaves to balance the external urea, then swelling as urea enters and reverses the gradient. If you're doing an experiment that assumes urea is a simple osmoticum, this two-phase behavior will wreck your data. Another thing that trips people up: osmolarity and tonicity are not interchangeable. Osmolarity is a measurement of all solute particles per liter. Tonicity describes the effect of a solution on cell volume. A 300 mOsm urea solution is isotonic in osmolarity terms but hypotonic in tonicity terms because urea crosses the membrane and doesn't create lasting osmotic pressure. Normal saline (0.9% NaCl) is both isotonic in osmolarity and in tonicity. Distilled water is neither. D5W (5% dextrose in water) is a common clinical trap—it's isotonic in the bag but becomes hypotonic once the glucose is metabolized by cells, leaving free water behind.
Get the Full Details
Let me be clear about the limitations here. The osmosis model I'm describing works beautifully for simple systems: artificial lipid bilayers, red blood cells in saline, bacteria in growth media. It breaks down in complex tissues where the endothelial glycocalyx creates its own oncotic pressure gradients, where tight junctions make epithelia functionally asymmetric, and where osmolyte transporters actively regulate cell volume. In those cases you need to think in terms of regulatory volume decrease and regulatory volume increase—cellular mechanisms that pump ions and organic osmolytes like betaine and taurine to restore volume after an osmotic challenge. The basic osmosis framework still underlies everything, but cell volume is rarely just about passive water movement anymore.
Practical Steps When Working With Osmotic Gradients
If you're preparing solutions for cell work, start by calculating your target osmolality in mOsm/kg, not mOsm/L. The distinction matters because molality (per kg of solvent) doesn't change with temperature, but molarity does. Your osmometer reads in mOsm/kg anyway, so calculate in the same units you'll measure. Use a calibrated vapor pressure or freezing point osmometer. Don't skip calibration—these instruments drift, and a $5 standard check before each session saves you from making a batch of media that's 40 mOsm off. When you need to create an osmotic gradient for an assay, do it by changing only one variable at a time. If you want to test how cells respond to hypertonic stress, use NaCl to increase osmolality rather than mannitol or sucrose, because NaCl is the most physiologically relevant. Mannitol and sucrose are good as impermeant osmoticums in controlled experiments, but they're not what cells experience in the body, and any conclusions about physiological responses get muddy when your stimulus is non-physiologic. I've reviewed papers where the authors claimed their hypertension model recapitulated in vivo conditions when they'd actually used 200 mM mannitol, which changes cell signaling in ways that have nothing to do with salt loading. For membrane permeability studies, don't assume the cell is a perfect osmometer. Real cells activate volume-sensitive ion channels within seconds of an osmotic shock. NCC and NKCC cotransporters kick in on the minute timescale. AQP expression changes over hours. If you're measuring water flux at t=0, you're seeing something very different from t=10 minutes. Design your time course accordingly. Most published osmotic shock protocols I've seen sample at one or two time points and then draw conclusions that don't hold up. Sample at 0, 30 seconds, 2 minutes, 10 minutes, and 60 minutes minimum if you care about the kinetics.
A note on failure modes. If your cells are dying during osmotic shifts, check three things before blaming the protocol. First, verify the solution pH—osmotic shifts can alter buffer capacity. Second, check for endotoxin contamination in your salts; hypertonic conditions make cells more permeable and more sensitive to LPS. Third, and this one is obscure, consider whether your container material is leaching plasticizers into the solution. Polypropylene tubes can release oligomers that interfere with membrane integrity at high concentrations, and I've had batches of seemingly perfect media kill cells at a rate that had nothing to do with osmolality. Switch to glass and you'll know immediately if that was the issue.
Bottom Line
Osmosis through cell membranes is straightforward when you stay precise about what you're measuring and what you're claiming. The common failure points are confusing osmolarity with tonicity, assuming calculated values are accurate, ignoring the reflection coefficient of your solutes, and treating cells as passive bags of water rather than active volume regulators. Get those right and the whole system makes sense. Get them wrong and you'll spend weeks chasing artifacts that look like biological phenomena but are just bad solution prep.


