Quick Flu A/B Antigen Test — What Actually Happens When You Run It
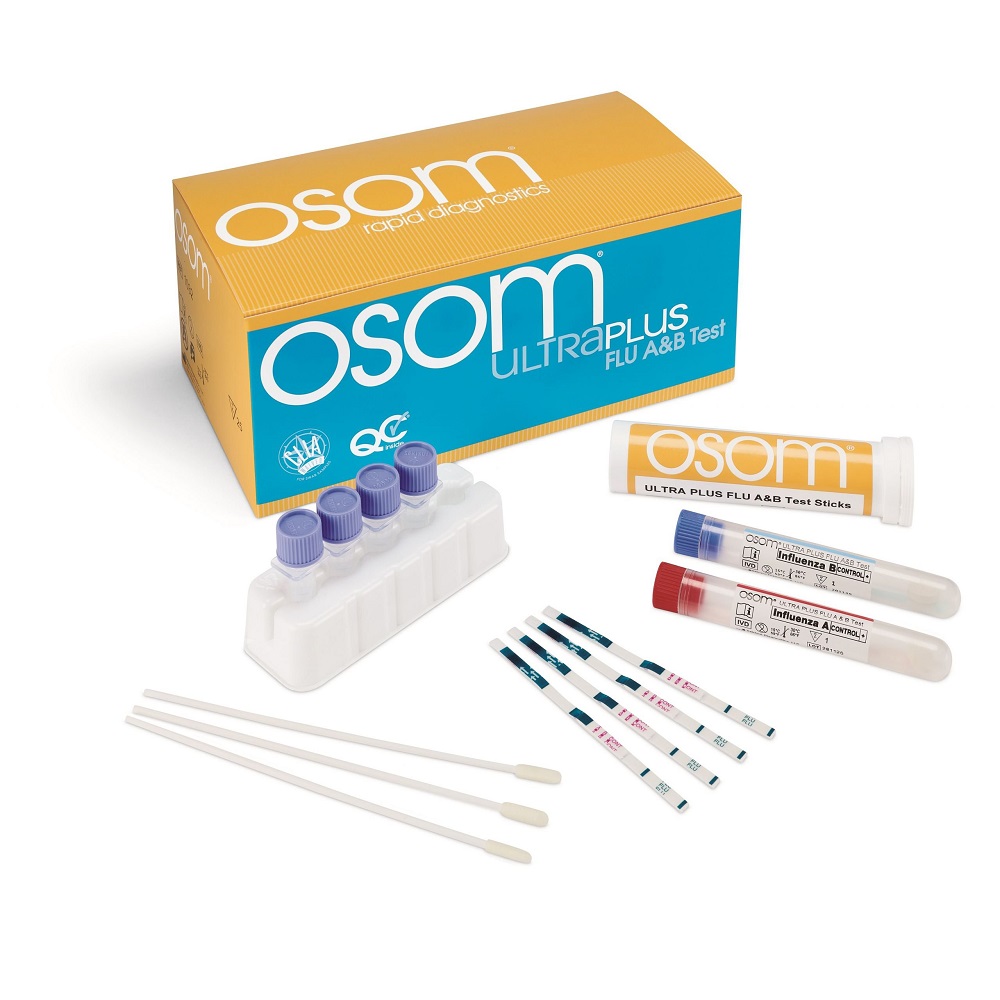
The OSOM Ultra Flu A+B test is an immunochromatographic rapid antigen assay. It detects influenza A and B surface proteins from a single nasal aspirate or swab specimen. You get a result in roughly 15 minutes. That is its entire value proposition. Nothing more, nothing less.Osom Ultra Flu Ab Test Instructions
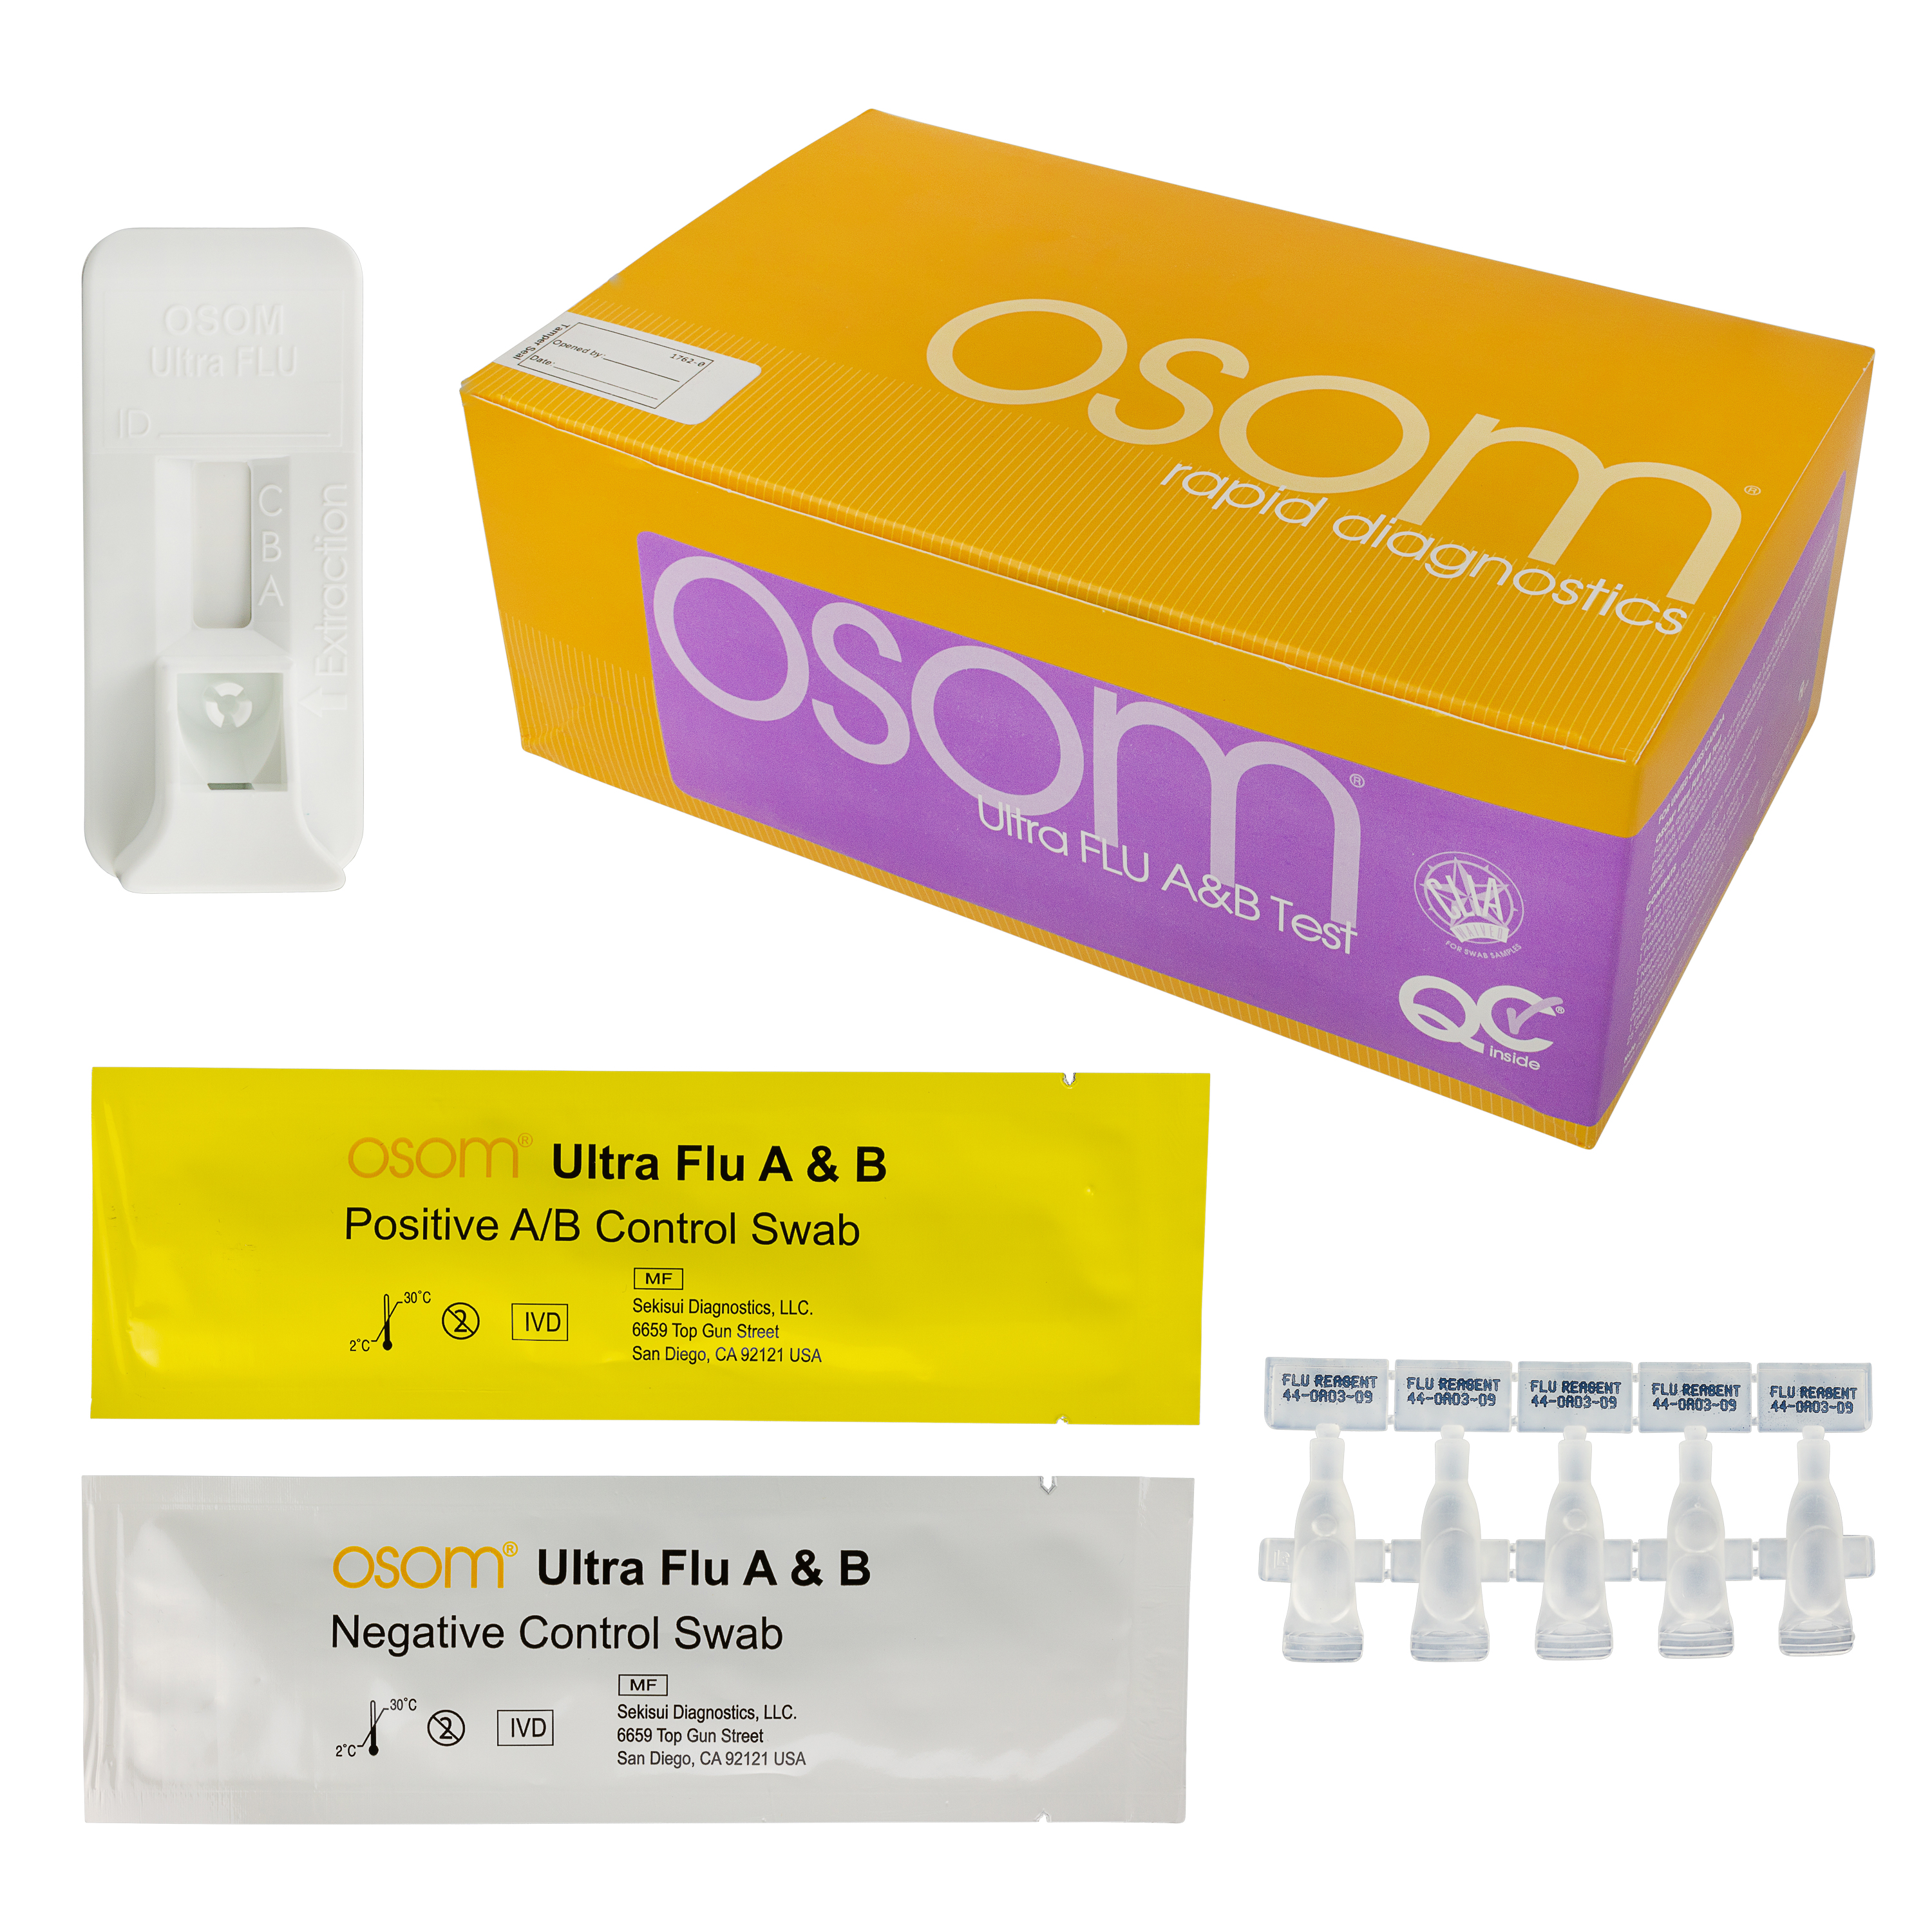
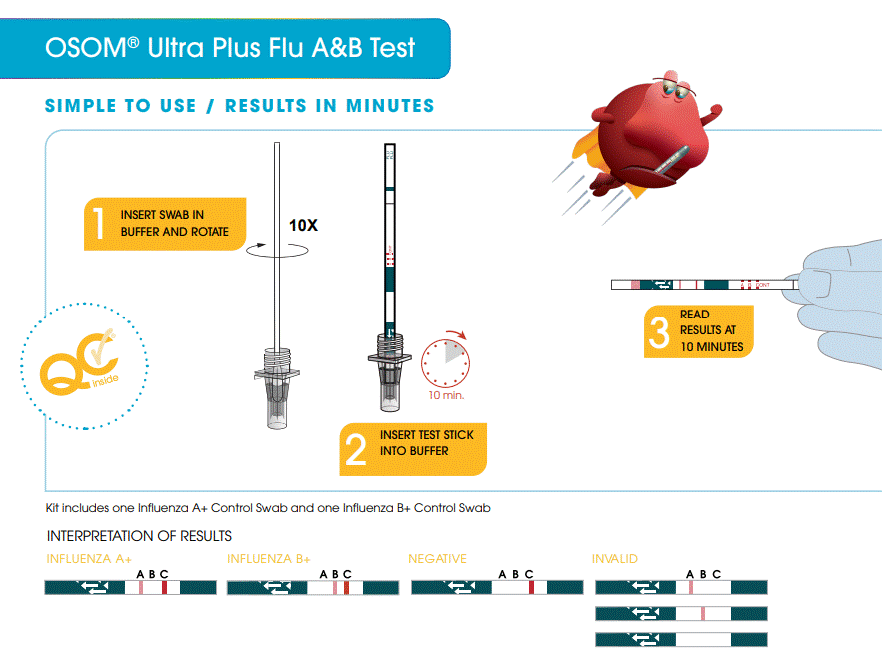
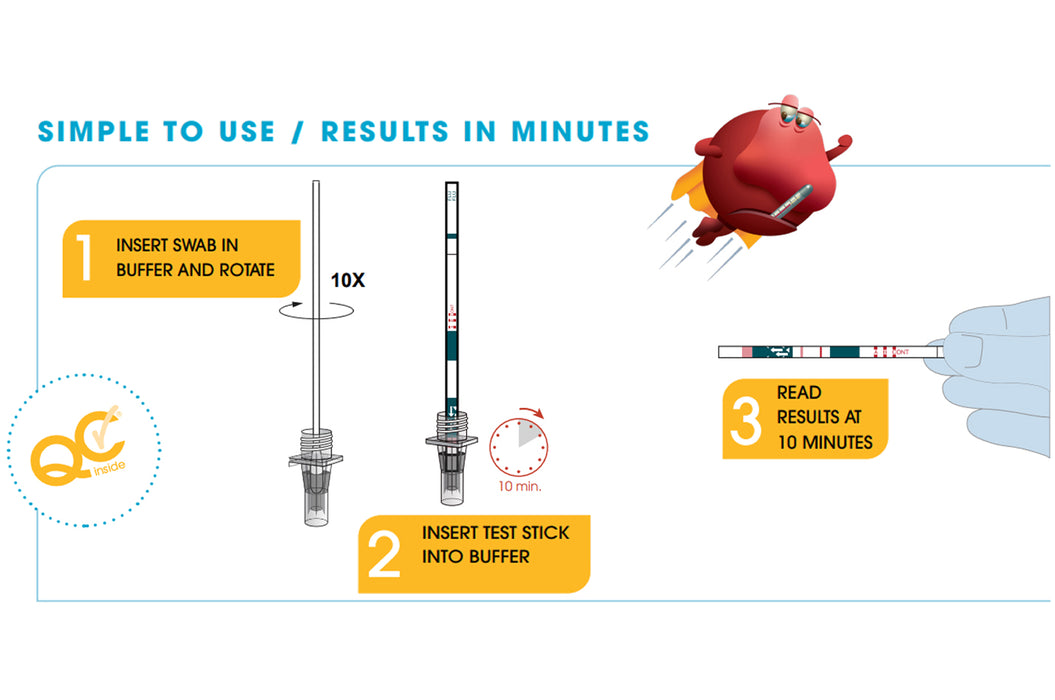
Open the pouch and lay out the device, diluent buffer dropper, and instructions card. Make sure the test is at room temperature before you start. Cold reagents throw off the flow rate and can create faint or missing control lines. Collect the specimen. Nasal aspirate is preferred by most clinicians because it pulls up more material than a anterior nasal swab. If you are using a swab, roll it firmly along both turbinates for about 5 seconds each side. Nasopharyngeal swabs work too but are unnecessary unless you are in a setting where sensitivity is absolutely critical and you have trained staff to collect them. Transfer the specimen into the diluent tube. If you used an aspirate, pipette the fluid directly. If you used a swab, squeeze and rotate the swab against the tube wall while it is submerged to release as much material as possible. Then close the cap tightly and invert the tube five times. Do not skip this mixing step. Inadequate mixing is the most common reason I see weak or indeterminate results on the bench.
Hold the dropper vertically and fill it to the marked line. Press the bulb, release, and dispense three full drops onto the sample well of the test device. Start your timer immediately after the third drop. The first drop sets the fluid in motion; the timer does not begin meaningfully until all three are deposited. Read the result at 15 minutes. Do not read it before 10 minutes. Do not read it after 20 minutes. Anything past the 20-minute window is not reliable and should be discarded. A visible colored line in the control region (C) confirms the test ran properly. Lines in the test regions (A and B) indicate positive results for influenza A and/or B. No control line means the test is invalid regardless of what appears in the test zones. I ran into a specific problem once with a batch where the control line was consistently appearing very faint, almost gray, on mostly negative specimens. The lab tech thought the device was defective. It turned out the specimen volume was slightly low because the aspirate yield was thin. Adding one extra drop of the diluent-specimen mix before dispensing into the well resolved it. The test needs a minimum fluid volume to wick properly to the conjugate pad. Thin specimens starve the flow. This is worth knowing if you work in pediatrics or with patients who have low mucous production.
Storage matters more than most people account for. Keep the sealed pouches at 2°C to 30°C. Do not freeze them. Do not use a test past its expiration date printed on the pouch. The nitrocellulose membrane and colloidal gold conjugate degrade over time, especially if the packaging has been compromised by heat or moisture. I have seen expired tests produce false positives because the gold-labeled antibodies lose their specificity and start sticking to things they should not. Interpretation can be tricky with weak test lines. A faint line in the A or B zone that is clearly visible to the naked eye should be called positive. It does not need to be as dark as the control line. The intensity of a positive line correlates roughly with antigen load but the test is qualitative, not quantitative. Do not try to grade severity based on line darkness. That is not what it is designed for. Here is a counter-intuitive point that trips people up: a negative result does not rule out influenza. The OSOM Ultra has a reported sensitivity around 70 to 80 percent for flu A and somewhat lower for flu B compared to RT-PCR. During peak season when pretest probability is high, a negative rapid antigen test should still be treated as indeterminate if clinical suspicion is strong. Many clinics confirm negatives with a molecular assay in those cases. The test is best used as a triage tool, not a definitive yes-or-no answer.
Get the Full Details
Another nuance: recent antiviral treatment can lower antigen levels below the detection threshold. A patient who started oseltamivir 24 to 48 hours before testing may return a false negative even though they genuinely have influenza. Document the medication history when you run the test. Cross-reactivity is minimal with this test. It is designed to distinguish A from B and does not typically react with RSV, parainfluenza, or rhinovirus. But it can occasionally pick up non-A/H1 influenza A strains at lower sensitivity, which is why molecular testing remains the reference standard when accuracy is critical. Dispose of the used device and specimen tube as biohazard waste. The test contains human-derived specimen material. Do not recycle the components.
Downloadable instruction sheets and IFUs are available from the manufacturer's website or through your medical supply distributor. Searching for "OSOM Ultra Flu A+B test package insert" should pull up the current version. Always verify you are looking at the latest revision since instructions can change slightly between manufacturing lots.