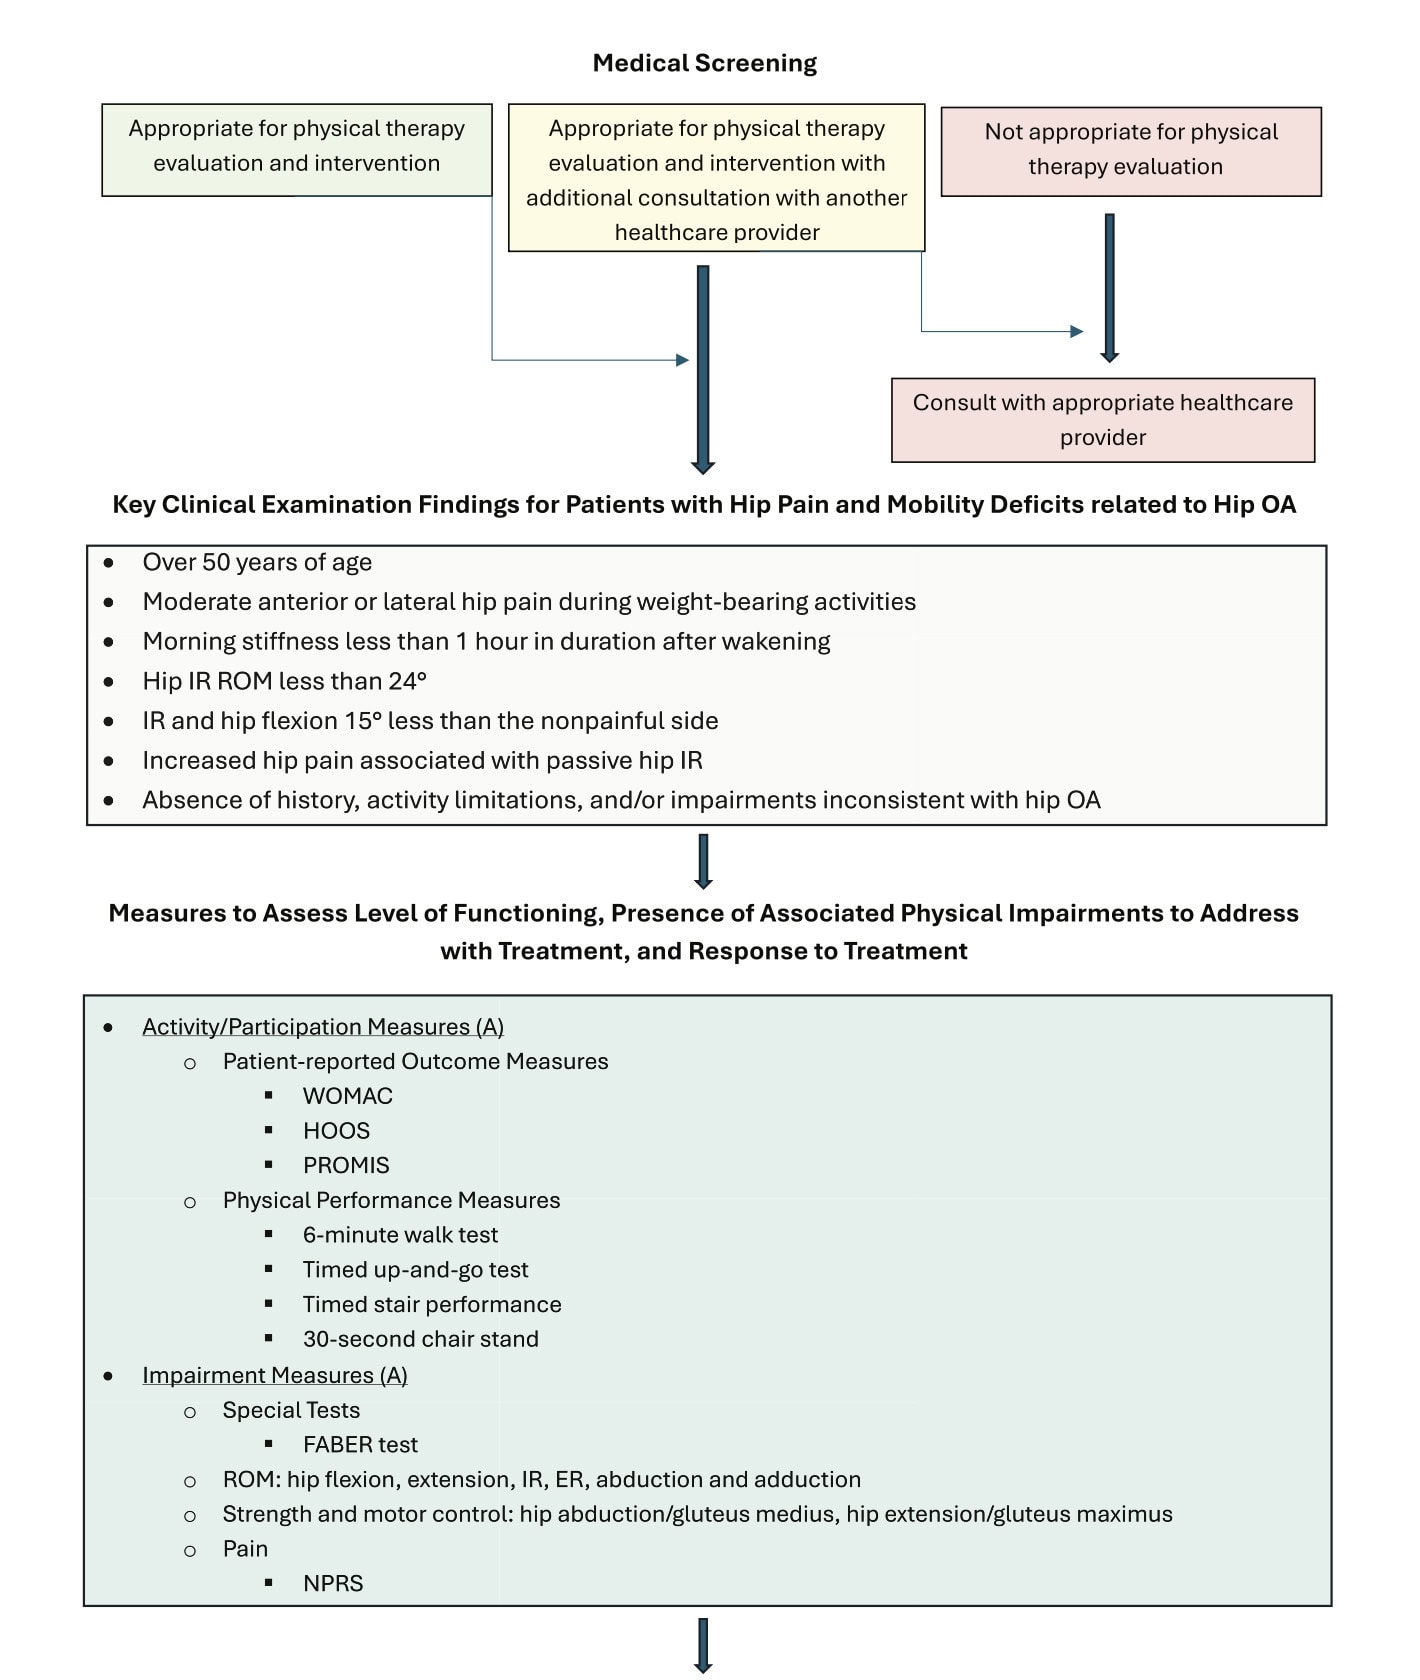
Understanding How OA Guidelines Actually Work in the Clinic
Osteoarthritis clinical practice guidelines are documents written by committees of specialists who review the available evidence and try to agree on what most patients should do. They don't represent absolute truth. They represent the best synthesis of what we know from clinical trials, systematic reviews, and expert consensus at a given point in time. The American College of Rheumatology, the Osteoarthritis Research Society International, and various national health bodies all publish their own versions. Most of them overlap significantly, though they diverge on a few key points. I've spent years reading and applying these documents, and the reality is messier than the guidelines suggest. The major guidelines converge on several foundational principles. Weight management matters, though the evidence is stronger for knee OA than for hip or hand OA. Exercise and physical therapy are recommended across the board, regardless of joint involvement. Pharmacological treatment typically follows a stepwise approach, starting with topical agents before moving to oral medications. Surgery is positioned as a last resort after conservative measures fail. The language is deliberately broad because the committees know they can't address every possible clinical scenario. These guidelines are built from systematic reviews of randomized controlled trials. The problem is that RCTs tend to study relatively healthy patients with isolated joint disease. Real patients in my clinic have diabetes, heart failure, chronic kidney disease, and multiple concurrent medications. The guidelines don't account for this well. You end up reading a recommendation to prescribe NSAIDs and immediately having to filter it through your patient's renal function, cardiovascular risk profile, and gastrointestinal history. The guideline says one thing. Your patient requires something else entirely.
I also noticed a recurring gap in how the documents handle polyarticular involvement. Multiple guidelines focus on knee OA as the default model because it has the strongest evidence base. But many of my patients have simultaneous knee and hip involvement, or knee plus hand OA. The guidelines rarely address what to do when you're treating two joints in the same person that may require different approaches. I developed a workaround where I evaluate each joint independently against the relevant guideline section, then look for conflicts in the overall treatment plan. Sometimes the knee protocol and hip protocol suggest contradictory activity levels. You have to choose based on which joint is causing the most functional impairment. Another issue is the timeframe. Guidelines reference trials that often run for six to twelve months. They don't tell you much about what happens at five or ten years. Long-term outcomes for non-surgical management are underrepresented in the evidence base. This means the recommendations feel solid in the short term but lack durability information. You're essentially applying today's best evidence to decisions that will affect patients for decades.
Reading the Recommendations Without Getting Lost
The American College of Rheumatology publishes conditional and strong recommendations. Conditional means the panel thinks most patients would choose the suggested approach, but some won't. Strong means the benefits clearly outweigh the risks for the vast majority. Understanding this distinction matters because conditional recommendations give you room to negotiate with patients who have strong preferences or specific constraints. I've found that leaning into conditional language actually improves adherence. Patients feel heard when you say the recommendation isn't absolute rather than being told what to do. The OARSI guidelines use a slightly different grading system based on agreement percentages among panel members. This creates nuances that aren't immediately obvious when you're skimming. A treatment with 70 percent agreement might sound solid, but it means nearly a third of experts disagreed. Those dissenting opinions often reflect real clinical situations where the standard approach doesn't work. I keep those edge cases in mind when patients present atypical responses to first-line therapies.
Get the Full Details

Applying the Guidelines to Actual Patients
Exercise is universally recommended, but compliance is the actual bottleneck. Most patients won't adhere to a structured exercise program unless it's modified for their pain levels and daily constraints. The guidelines suggest moderate-intensity aerobic activity, but moderate intensity means different things to different people. For a sedentary patient with severe knee OA, even walking ten minutes might be challenging initially. I break the recommendation down into smaller, more achievable units. Shorter duration, more frequent sessions, and gradual progression tend to work better than pushing for an hour of activity right away. Water-based exercise deserves more attention than the guidelines give it. Aquatic therapy reduces joint loading while allowing range of motion and strength work. The evidence supports it, but few primary care providers refer patients to aquatic programs because access is limited and insurance coverage is inconsistent. When I have patients who can't tolerate land-based exercise, I look for local pool facilities with warm water and flat bottoms. Even basic walking in chest-deep water provides meaningful benefit. Pharmacological management has shifted considerably over the past decade. Earlier guidelines were more permissive with NSAIDs and viscosupplementation. Current versions are more cautious due to safety data. Topical NSAIDs are now preferred over oral NSAIDs for knee and hand OA in many recommendations. The cardiovascular and gastrointestinal risks of oral agents are well documented. I find that patients respond better when you explain the rationale rather than just prescribing topicals and moving on. They're more likely to use them consistently if they understand why the approach changed.
When the Guidelines Don't Help
Surgical decision-making is where the guidelines become most frustrating. They generally recommend joint replacement when conservative treatment fails and quality of life is significantly impacted. But they don't specify exactly when conservative treatment has failed. That judgment call falls to the treating physician. In practice, I've seen patients delay surgery for years beyond the point where outcomes would be optimal. Muscle atrophy, fixed contractures, and compensatory gait patterns all worsen with prolonged delay. The guidelines could be clearer about timing markers, but they aren't. Another limitation is the handling of patients with inflammatory features overlaid on osteoarthritis. Some patients present with OA plus an inflammatory component, sometimes related to crystal deposition or early rheumatoid arthritis. The guidelines don't adequately address this overlap. You end up managing inflammation with additional pharmacological interventions while still following the OA framework. It works, but it's not elegant.
Practical Takeaways for Clinicians
The most useful approach is to read the guidelines as a starting point rather than a complete manual. Identify which recommendations align with your patient's presentation, then adapt the rest based on individual factors. Keep track of which recommendations are conditional versus strong. Use that distinction when discussing treatment options with patients. Pay attention to the sections on exercise and weight management even if you think you already know what to recommend, because the specific details about frequency, duration, and intensity often get overlooked in casual practice. When guidelines conflict between organizations, check the publication dates and the strength of underlying evidence. More recent guidelines tend to reflect updated safety data, particularly around NSAID use and viscosupplementation. The NICE guidelines from the UK sometimes diverge from North American recommendations, especially regarding surgical thresholds and the role of assistive devices. Understanding why they differ helps you choose which framework fits your patient better. Finally, recognize that guidelines are inherently conservative. They recommend what has been studied and proven in controlled settings. They don't capture the full range of clinical experience. Your judgment matters alongside the published recommendations. The guidelines won't replace that judgment, and they shouldn't. Use them to inform decisions, not to make decisions for you.