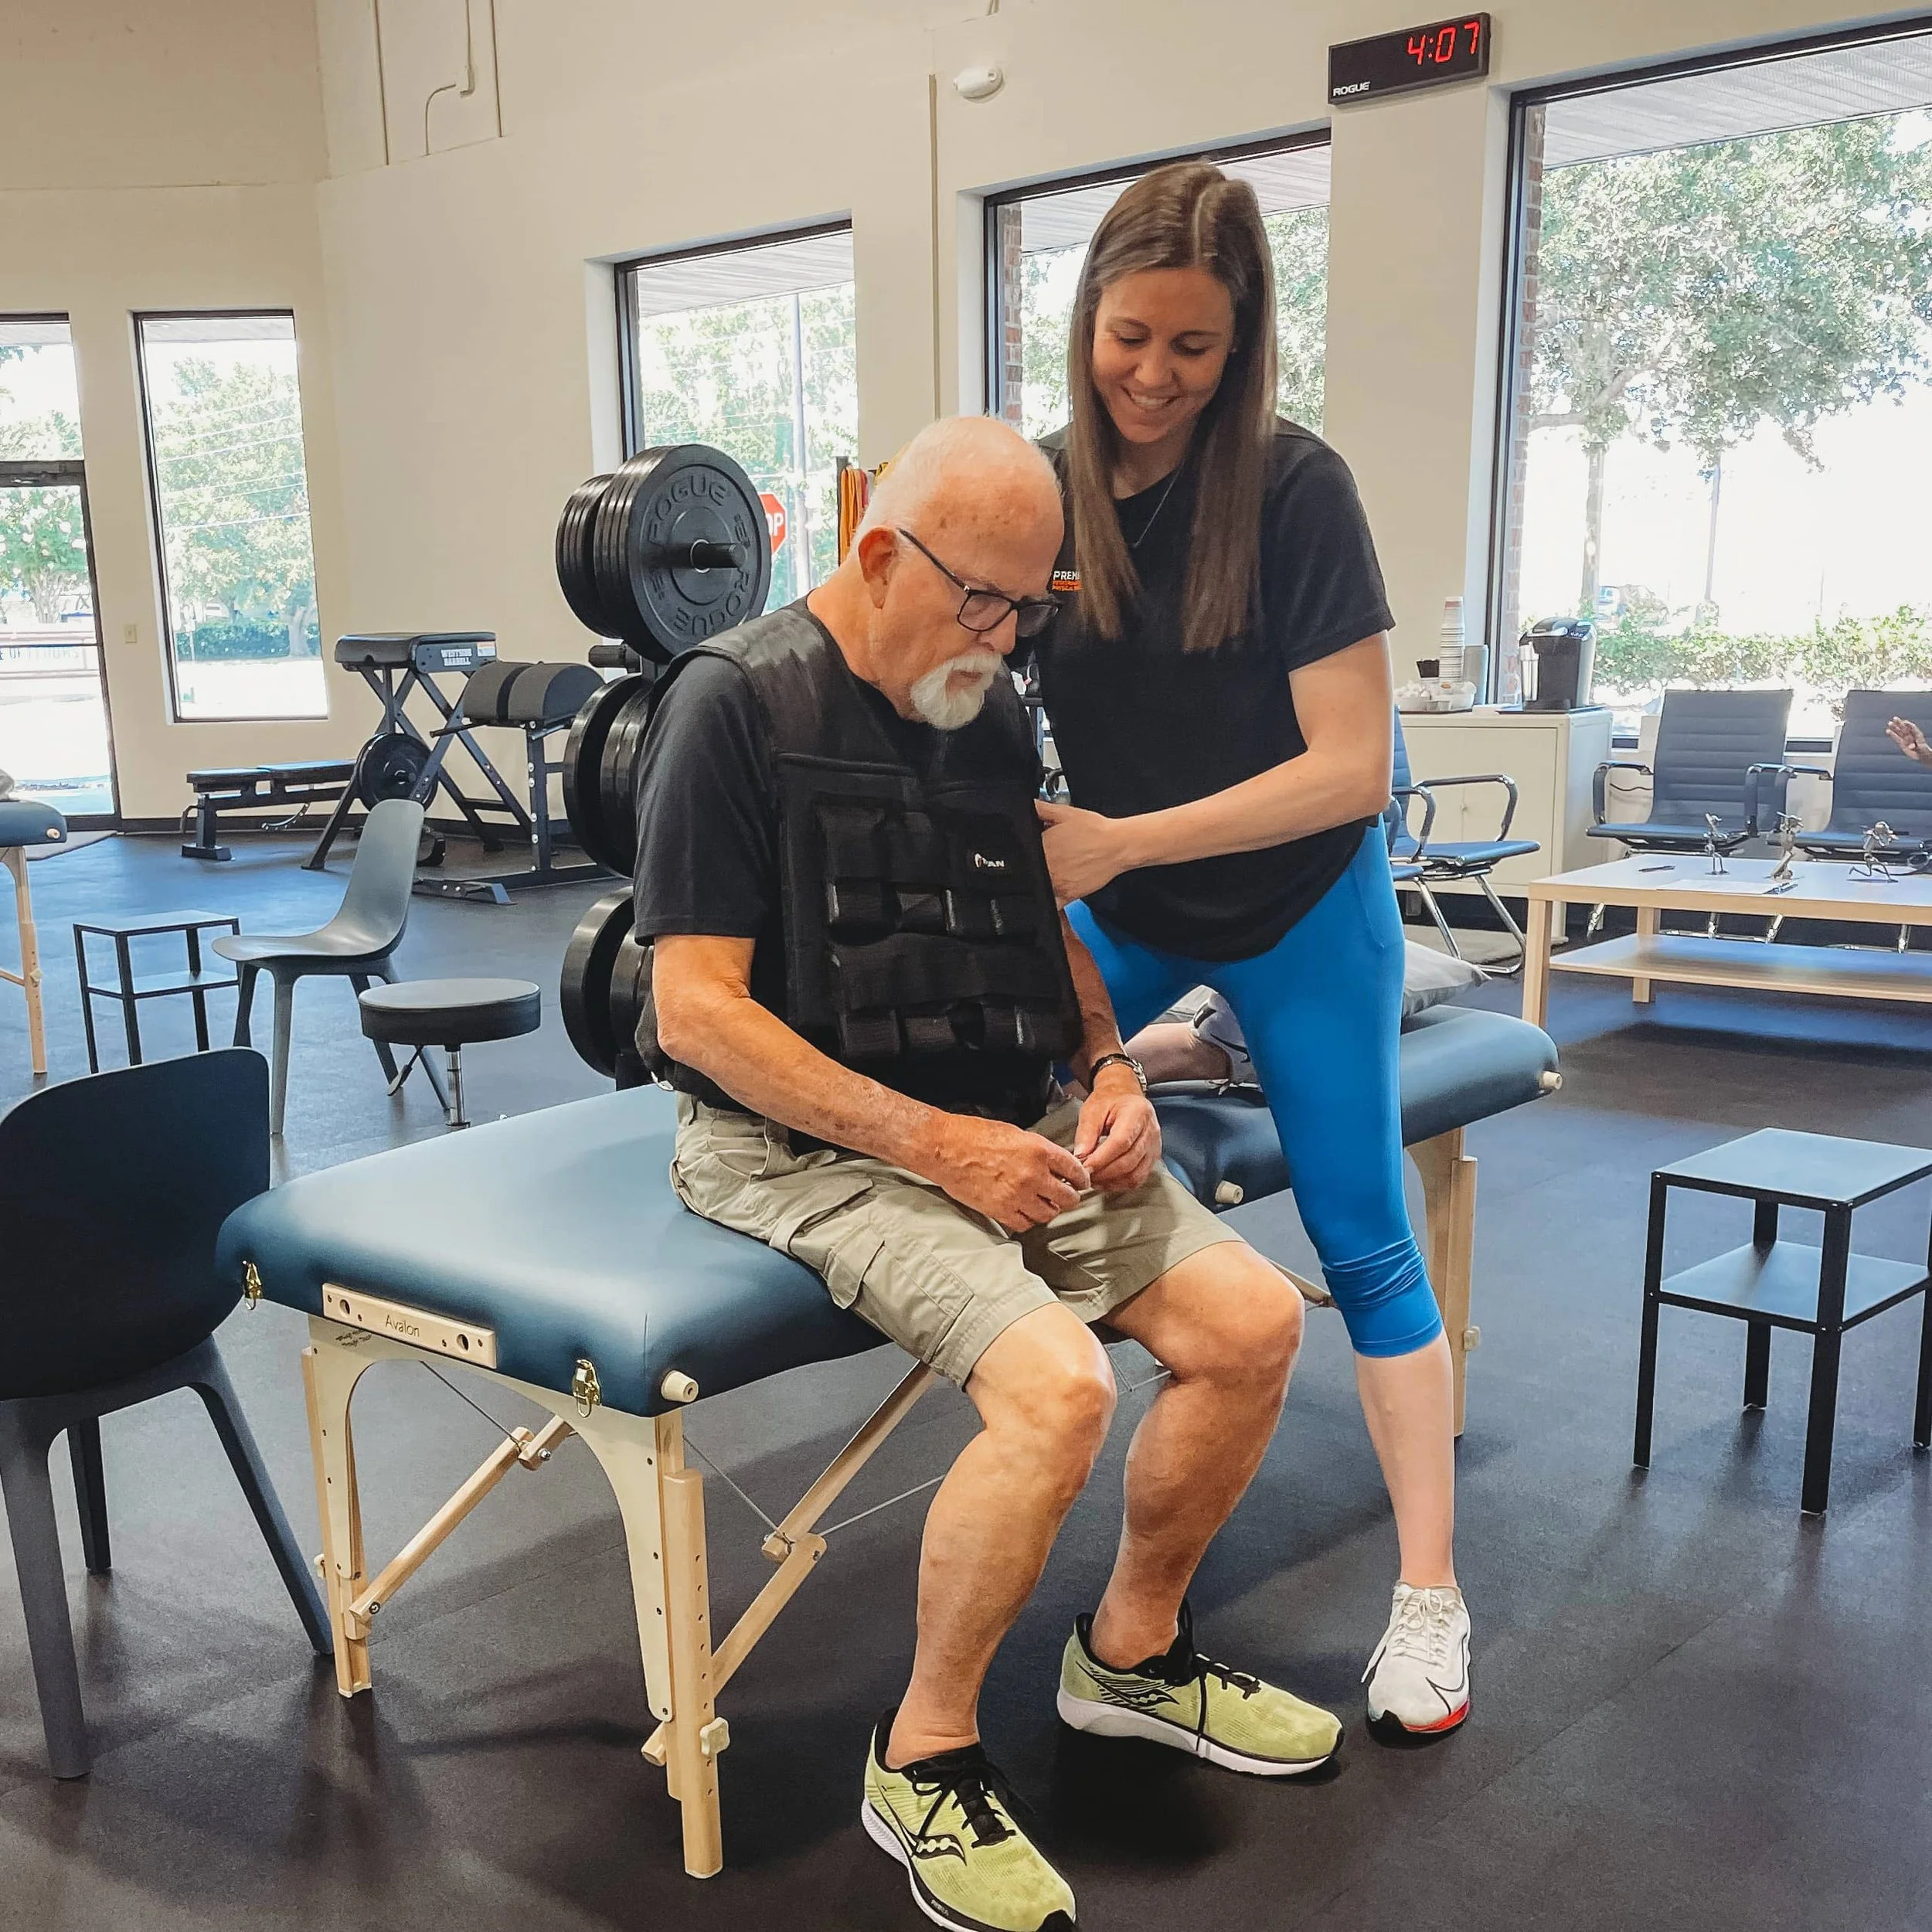
The Actual Workflow for Bone Health Exercise Prescription
I've had enough conversations about osteoporosis treatment protocols to know that most people approach it completely wrong. They think the solution is gentle walking and stretching, which is fine if you want to maintain what you have, but it won't rebuild bone density. I've watched patients spend years doing low-load activities and then suffer compression fractures anyway because nobody ever pushed them hard enough to trigger an adaptive response. The truth is that bone is living tissue that responds to mechanical stress through a process called mechanotransduction. When you place controlled axial load on the skeleton, osteocytes detect the fluid flow in the lacunocanalicular system and signal osteoblasts to lay down new bone matrix. This doesn't happen with light activity. It requires specific force thresholds, and it requires variety in the loading directions because bone adapts to the exact vectors of stress placed upon it.
Osteoporosis And Physical Therapy: What Actually Works
The exercise protocol I use generally follows this progression. First, we assess fracture risk using the patient's DEXA scan T-score, history of prior fractures, and falls risk. Then we build a program around five categories of movement. Axial loading comes first — this means exercises where the spine bears weight in a vertical direction, like heel drops performed standing, bridging, and squats. The force transmitted through the vertebral bodies during these movements stimulates the bone remodeling process more effectively than almost anything else. Second is progressive resistance training. We're talking about loads at approximately 60 to 80 percent of one-repetition maximum. Studies show that weights in this range produce the greatest increases in bone mineral density at the hip and lumbar spine. A patient might start with bodyweight squats and progress to goblet squats, then barbell back squats over several months as tolerated. The key word is progressively. There is no shortcut here. Multidirectional loading is the third component. Bone only gets stronger in the directions you load it, so rotational movements and lateral loading patterns matter just as much as vertical ones. This is why exercises like pallof presses, side planks, and weighted lunges get included. Single-leg work is particularly valuable because it increases the ground reaction force on each leg individually and challenges balance simultaneously.
Fourth, balance and proprioception training reduces fall risk, which is arguably the most important practical outcome. Falls cause fractures in osteoporotic bone far more often than the bone weakness itself causes spontaneous breaks. Tandem stances, single-leg stands, and increasingly complex balance tasks like eyes-closed stands on unstable surfaces are standard in my protocol. Every patient gets this. It's not optional. Fifth, posture and extension work addresses the kyphotic posture that develops after vertebral fractures and often precedes them. Prone back extensions, thoracic extensions over foam rollers, and scapular retraction exercises counteract the forward-flexed position. This is critical because once a patient develops a rounded upper back, any forward bending motion becomes a vertebral fracture risk.
Get the Full Details

Common Mistakes That Make Things Worse
The biggest mistake I see is recommending toe touches, sit-ups, or any exercise that involves repetitive spinal flexion under load. These movements create enormous compressive forces on the anterior portion of the vertebral bodies, which are already the weakest part of an osteoporotic spine. A single vigorous forward bend can be enough to cause a compression fracture in someone with a T-score below minus 2.5. This isn't theoretical. I had a patient who came in after doing yoga — specifically the forward fold and seated twist poses — and ended up with a new L1 vertebral compression fracture. She wasn't even told to avoid those movements beforehand. It was her own yoga instructor who recommended the class, not her physician. Another mistake is assuming that because a patient has osteoporosis, they should avoid all impact. Low-impact doesn't mean no-impact. Heel drops, marching in place, and light jogging on soft surfaces are appropriate for many patients and actually necessary for bone loading. The old advice to "just walk more" is insufficient. Walking loads the skeleton at roughly 1.2 times body weight. Running loads it at roughly 2.5 to 3 times body weight. The difference in stimulus is substantial, and most patients with moderate osteoporosis can tolerate running-level forces if they build up to them appropriately. A third error is ignoring the arms. The radius and humerus also lose density in osteoporosis, and pushing exercises like wall push-ups, overhead presses, and rowing movements load the upper extremity bones directly. I see too many programs that focus exclusively on the lower body and spine while completely neglecting the rest of the skeleton.
What the Research Actually Says and Where It Falls Short
The landmark studies in this area — the FRAX tool, the VITAMIN-D trial, various meta-analyses on resistance training and bone density — generally show that a well-designed exercise program can increase lumbar spine BMD by approximately 1 to 3 percent over 12 to 24 months. That sounds small until you consider that each 1 percent increase in BMD correlates with roughly a 10 to 15 percent reduction in fracture risk. The numbers compound. However, there is a significant limitation in the research that clinicians rarely discuss openly. Most exercise studies exclude patients with existing vertebral fractures or those on high-dose bisphosphonates, which means the results don't always translate to the patients you actually see in clinic. Patients with established osteoporosis and prior fractures respond differently — sometimes less — to the same exercise protocols. I've found that in these cases, the exercise prescription needs to be more conservative initially, with slower progression and greater emphasis on balance training before aggressive loading begins. There is also the issue of supervised versus unsupervised exercise. The studies that show the best outcomes almost always involve supervised sessions two to three times per week. An unsupervised home program typically achieves about half the bone density response because patients don't push hard enough, they skip sessions, and their form deteriorates. This doesn't mean home exercise is worthless — it means it needs to be structured, monitored, and periodically reassessed.
The Medication Question
I need to be direct here. Exercise alone is not sufficient treatment for established osteoporosis. If a patient has a T-score below minus 2.5, a history of hip or vertebral fracture, or a FRAX score that indicates high fracture risk, they need pharmacological intervention alongside exercise. Bisphosphonates like alendronate and zoledronic acid, denosumab, teriparatide, and romosozumab all work through different mechanisms and have different risk-benefit profiles. No physical therapist should be advising patients to skip medication in favor of exercise alone. That is a decision for the prescribing physician, but the evidence is clear that the combination of medications plus targeted exercise produces better outcomes than either intervention alone. That said, exercise remains important even when medications are involved. Bisphosphonates reduce bone turnover, which means the bone that exists becomes more resistant to fracture but doesn't necessarily become denser on its own. Exercise provides the mechanical stimulus that tells the body where to maintain and build bone. Without it, the medication is working against a sedentary skeleton that has no reason to invest resources in bone maintenance.

When This Approach Doesn't Work
There are scenarios where an exercise-focused approach reaches its limit. Patients with severe uncorrected vitamin D deficiency, malabsorption disorders like celiac disease, hyperparathyroidism, or multiple myeloma will not respond adequately to exercise alone because the underlying metabolic issue continues to drive bone loss. In these cases, the priority has to be treating the root cause. I've had patients who were told to start an exercise program for osteoporosis without having their calcium, vitamin D, and parathyroid hormone levels checked. Six months later, their bone density had worsened, and the real problem was undiagnosed secondary hyperparathyroidism. The exercise wasn't the issue. The missed diagnosis was. Another limitation is compliance. The programs that work require consistent effort over years, not months. Patients often drop out after the initial motivation fades, and bone density gains are lost within 6 to 12 months of stopping. There is no long-term study showing that patients maintain exercise adherence beyond two or three years without some form of ongoing support or accountability structure.
Practical Starting Point
If you're looking for where to begin, the minimum effective dose appears to be three sessions per week of supervised resistance training at moderate to high intensity, combined with daily balance work and weight-bearing aerobic activity. Start with two sets of 8 to 12 repetitions for major muscle groups, progress to three sets over 4 to 6 weeks, and increase the load by 5 to 10 percent when the current weight feels manageable for all sets and repetitions. Avoid any movement that causes spinal flexion under load. If a movement hurts, stop. Pain is not a useful signal in this context — it's a stop signal. Getting a baseline DEXA scan and a FRAX calculation before starting any program gives you something to measure against. Without baseline numbers, you're just guessing whether anything is working.