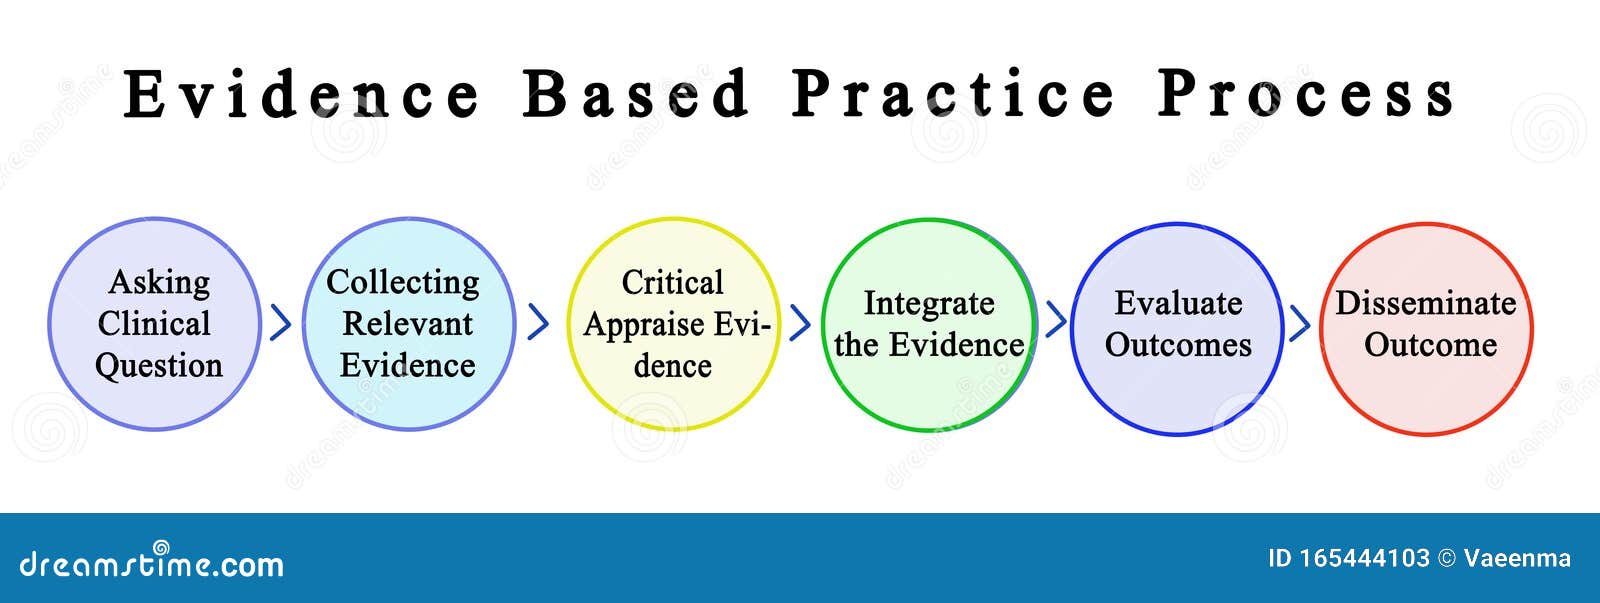
So You Want to Use Outcome Informed Evidence Based Practice
Most people treat outcome tracking as a compliance exercise. They hand a client a brief questionnaire at intake, do it again at discharge, and call it done. That is not Outcome Informed Evidence Based Practice. That is just paperwork with delusions of grandeur.
The actual work starts when you notice a score isn't moving and you change something about the intervention. The framework was developed by researchers like Scott Miller and colleagues, building on work in therapy outcome monitoring. It has since spread into social work, primary care behavioral health, and community mental health settings where accountability matters. The core idea is simple enough: use routinely collected client outcome data to inform clinical decisions alongside research evidence and clinical expertise. But the simple part is not the hard part.
Getting Started With Outcome Informed Evidence Based Practice
You need three things before you can do this right. First, a validated brief outcome measure you can administer at every session or at regular intervals. OQ-45.2, the Session Rating Scale, the Clinical Outcomes in Routine Evaluation-Outcome Measure (CORE-OM), or the Child Outcome Rating Scale if you work with youth. Pick one and stick with it. Switching measures mid-stream creates nonsense data that you will misinterpret.
Second, a system that returns scores to you before the next session. If you are printing paper forms and scoring them by hand three days later, the data is already dead. It tells you what happened. It does not tell you what to adjust. Electronic scoring that delivers a graphical trajectory to your phone or dashboard within twenty-four hours is the minimum viable threshold.
Third, and this is the part everyone skips, you need agreed-upon action thresholds. What does a stagnant score mean? What does a worsening score require? Write this down before your first case. When anxiety is not improving over four sessions using CBT protocols, the outcome tells you to switch or augment. When a young client's SRS drops below a certain range, the outcome tells you the therapeutic alliance is off and you spend the next session addressing the relationship, not the diagnosis.
I learned this the hard way. A few years ago I was working with a client whose PHQ-9 dropped from 18 to 12 in three sessions, which looked fine on paper, but the Session Rating Scale scores had been flatlining around 8 the entire time. The outcome numbers were pulling in opposite directions and I almost missed the signal. I had trained myself to read the symptom scale and ignore the alliance measure. What actually happened was the client was tolerating the sessions poorly but still performing behavioral activation exercises and getting temporary relief from activities. Stopping there would have been a mistake. I shifted to a more relational focus in the fourth session and the PHQ-9 subsequently dropped to 7 over the next six weeks. The alliance measure had been correct the whole time. The symptom measure had just been lagging.
The method in practice
Administer the chosen measure at intake and at least every four sessions after that, or every session if your caseload allows. Review the score graphically before each appointment. Set a rule: if the score worsens across two consecutive administrations, schedule a process consultation or supervisory review within five days. If the score plateaus for four sessions despite protocol fidelity, consider a treatment change. Document the decision and the rationale. That documentation is your audit trail. It is also what separates deliberate practice from guessing.
You will need training. Not a two-hour webinar. Actual training in how to interpret the scales, how to give feedback to clients without causing defensiveness, and how to use the data in supervision. Most measure publishers offer training packages. Budget at least six to eight hours of structured learning per clinician before you roll this out. The return on that investment appears within three months if the system is set up correctly.
Where This Actually Works and Where It Does Not
Outcome Informed Evidence Based Practice works best in high-volume, high-turnover environments where clinicians see many different presentations and need a common language to discuss cases. It also works well when supervisors have access to aggregated data and can identify patterns across the team. A clinic director who reviews monthly aggregate OQ scores can spot drift faster than any chart audit.
It breaks down quickly in several common scenarios. Acute crisis settings do not tolerate repeated measurement. If someone is presenting with active suicidality, you are not handing them a thirty-item inventory every session. You triage and treat. The data comes later.
Chronic complex cases with comorbid personality pathology and multiple systemic stressors also resist clean score trajectories. A client with borderline features and unstable housing may show a score pattern that looks like regression every time their life situation changes. Reading that as treatment failure is a category error. The outcome data is reflecting life, not just the intervention. You have to factor that in or the system will push you toward unnecessary treatment changes.
I ran into this with a client in a community mental health program who had a PHQ-9 that bounced between 14 and 21 for six months while their life circumstances stabilized. We had two supervisors push for a medication consult and a third push for a different evidence-based protocol. None of it addressed the real issue: the client was functionally improving, managing crises better, and maintaining employment, but the questionnaire was not sensitive to those gains. We switched to a functional assessment framework alongside the outcome measures and stopped letting the score alone dictate the treatment plan. The score eventually tracked with the improvement once the housing stressor resolved. It was a reminder that outcome measures are indicators, not diagnoses.
There is a counter-intuitive point here that most beginners miss. Higher fidelity to a protocol does not always correlate with better outcomes when you add routine outcome monitoring. Studies have shown that clinicians who rigidly follow a manual while ignoring disconfirming outcome data actually perform worse than clinicians who use the data to flex their approach. The evidence base supports structured interventions. It does not support treating the protocol as the outcome. The outcome is the outcome. The protocol is a tool.
Another nuance that is easy to overlook is the difference between statistical significance and clinical significance in individual case data. A drop of three points on a PHQ-9 is not clinically meaningful. A drop of five or more is the conventional reliable change threshold. A plateau at fourteen is not a failure if the client functions better at home and work than they did at twenty-two. Quantitative cutoffs are heuristics. They are not laws.
Implementation Practicalities
If you are setting this up in a clinic, the infrastructure matters more than the theory. Start with one measure. Pick the one your team finds least objectionable. Get electronic administration going. Most EMR systems now have built-in support for common outcome measures. If yours does not, consider an independent platform like ThriveMS or the Outcome Assessment package from PSYCOM. These tools integrate with most health IT systems and automate score calculation and graph generation. Expect to spend two to four weeks on setup before you see clean data. Budget accordingly.
Train the front desk staff. This sounds trivial until you realize that a misplaced instruction on the intake form can cause a client to skip the measurement entirely or complete it in a state of confusion. The person who hands the tablet to the client determines whether the data is usable. One sentence on the screen, not a paragraph.
Supervision must incorporate the data. If your clinicians submit outcome reports and then never discuss them in supervision, you have created an administrative burden with zero clinical value. Build a standard ten-minute agenda item into every group supervision session: review any client whose score crossed a predefined threshold since the last meeting. That is it. Ten minutes. If the culture does not support this, the program will fail within six months regardless of how good the technology is.
There is also a cost consideration that rarely gets discussed. Routine outcome monitoring increases documentation load initially by approximately fifteen to twenty minutes per week per clinician. After the novelty wears off and the workflow stabilizes, it typically reduces charting time by about ten to fifteen minutes per week because the structured data replaces narrative description for progress notes. The net effect is roughly neutral after three months, but the first three months are unpleasant. Plan for that friction.
When to Stop Relying on This Method
Outcome Informed Evidence Based Practice is not appropriate as a standalone decision-making framework. It should never replace clinical judgment. It should never replace a thorough assessment. It is a supplement, not a substitute. Using it as a proxy for competence is a common institutional failure mode. Administrators who reward clinicians for perfect data submission rates without evaluating the clinical reasoning behind score-based decisions are creating a gaming environment, not a learning environment.
In my experience, the single biggest predictor of successful implementation is whether senior leadership treats the data as a quality improvement tool rather than a performance management tool. The moment clinicians feel the scores will be used against them in evaluations or billing reviews, they will find ways to game the system. Clients will do the same. The data degrades and everyone loses.
The alternative for settings that cannot support full outcome monitoring is simpler. Use a single validated measure at intake and discharge only. That is not as useful, but it is better than nothing. And it does not carry the same implementation burden or risk of unintended consequences.
If you want the actual tools, the standard measures are publicly available through their respective publishers. The OQ measures are available through Quality Partners of Redwood. The CORE measures are available through CORE Office. Free versions exist for some tools, though licensing terms vary. There is no single download link that covers everything because the methodology is not a product. It is a practice model. The closest thing to a comprehensive guide is the literature on feedback-informed treatment, which overlaps substantially with outcome-informed EBP. Books and manuals by Scott Miller, Tim Anderson, and Robert Hubble provide the detailed procedural guidance. Expect to spend a few weeks reading before you feel competent enough to run this without supervision.