Acute Pain Documentation That Actually Survives a Chart Audit
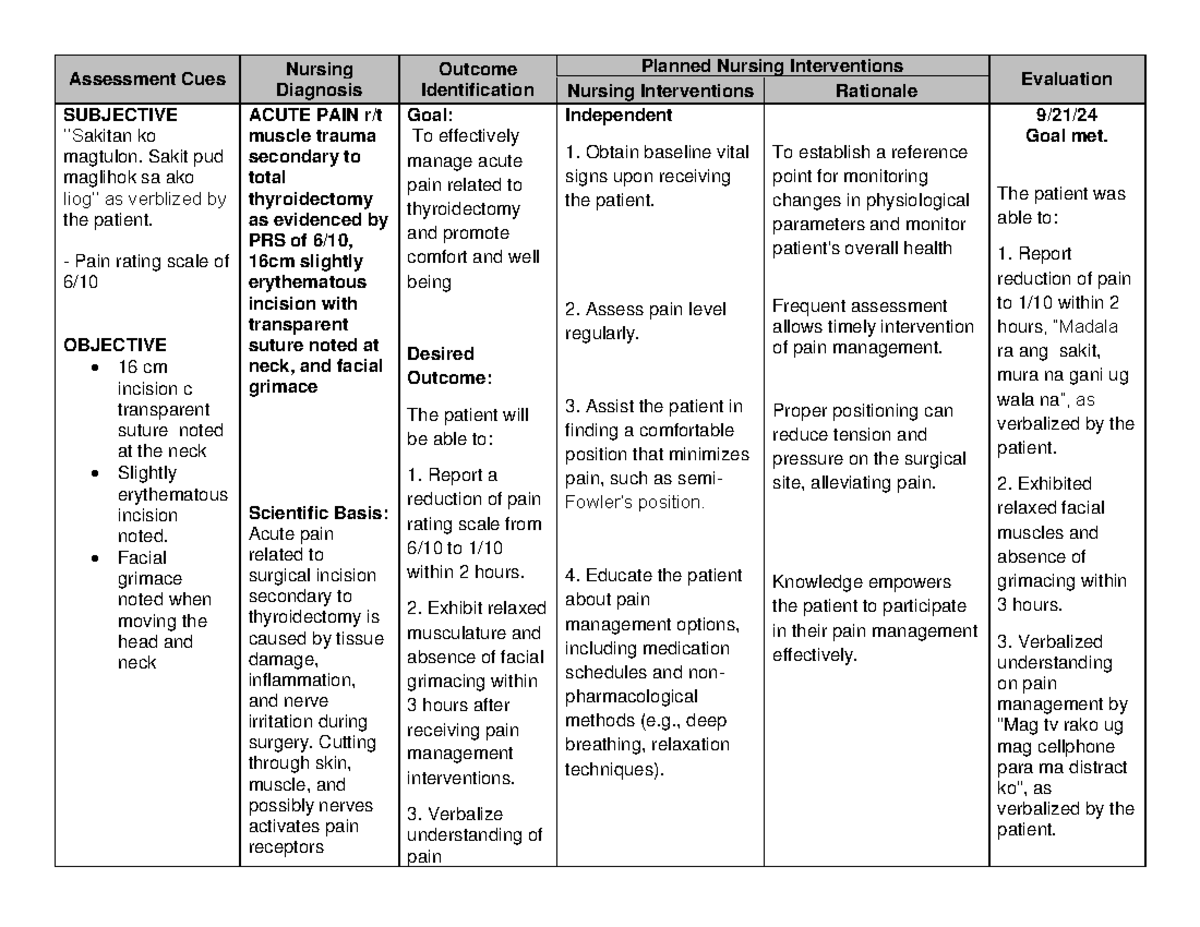
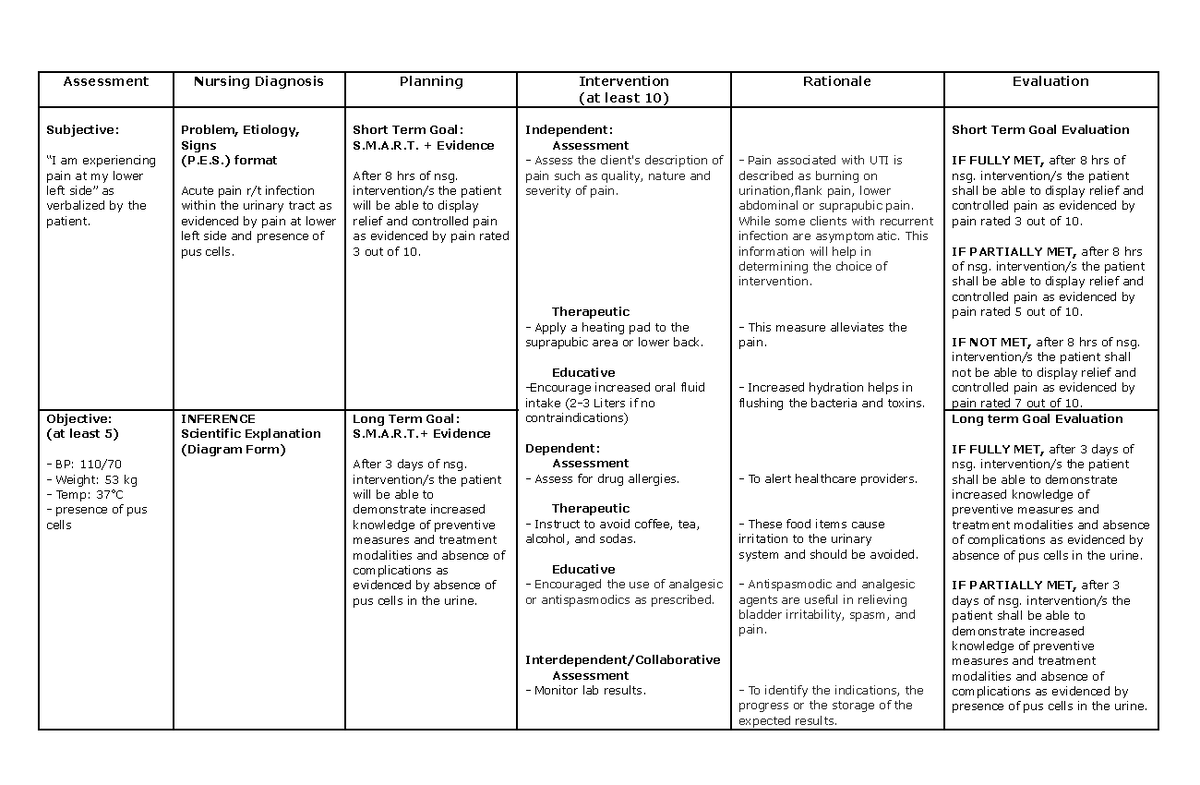
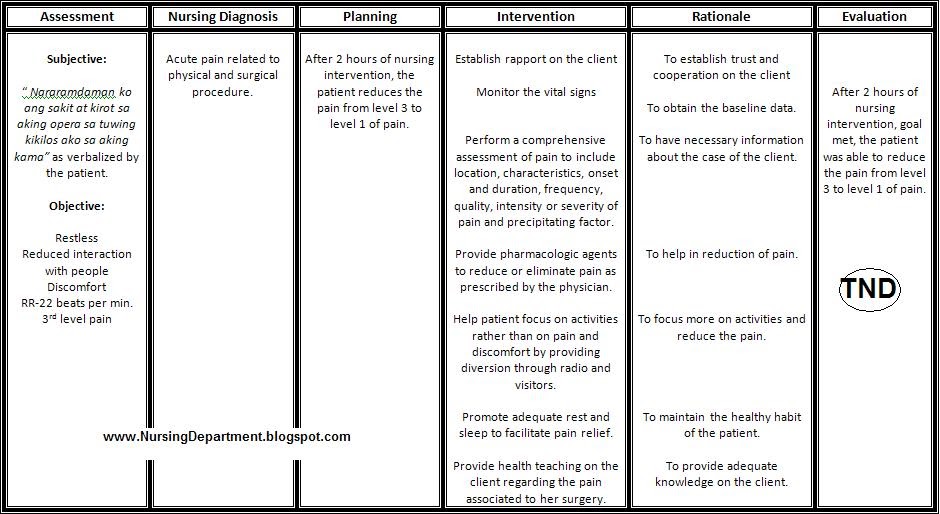
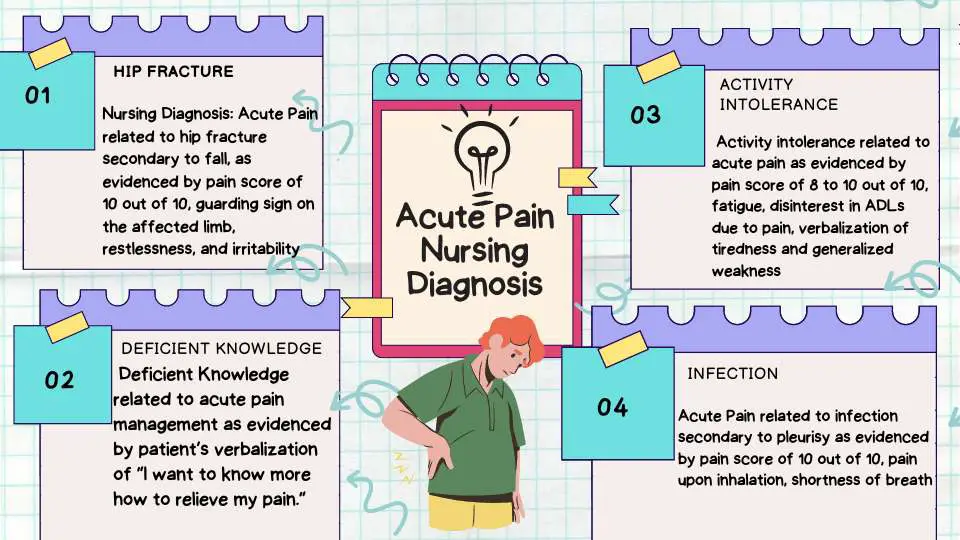
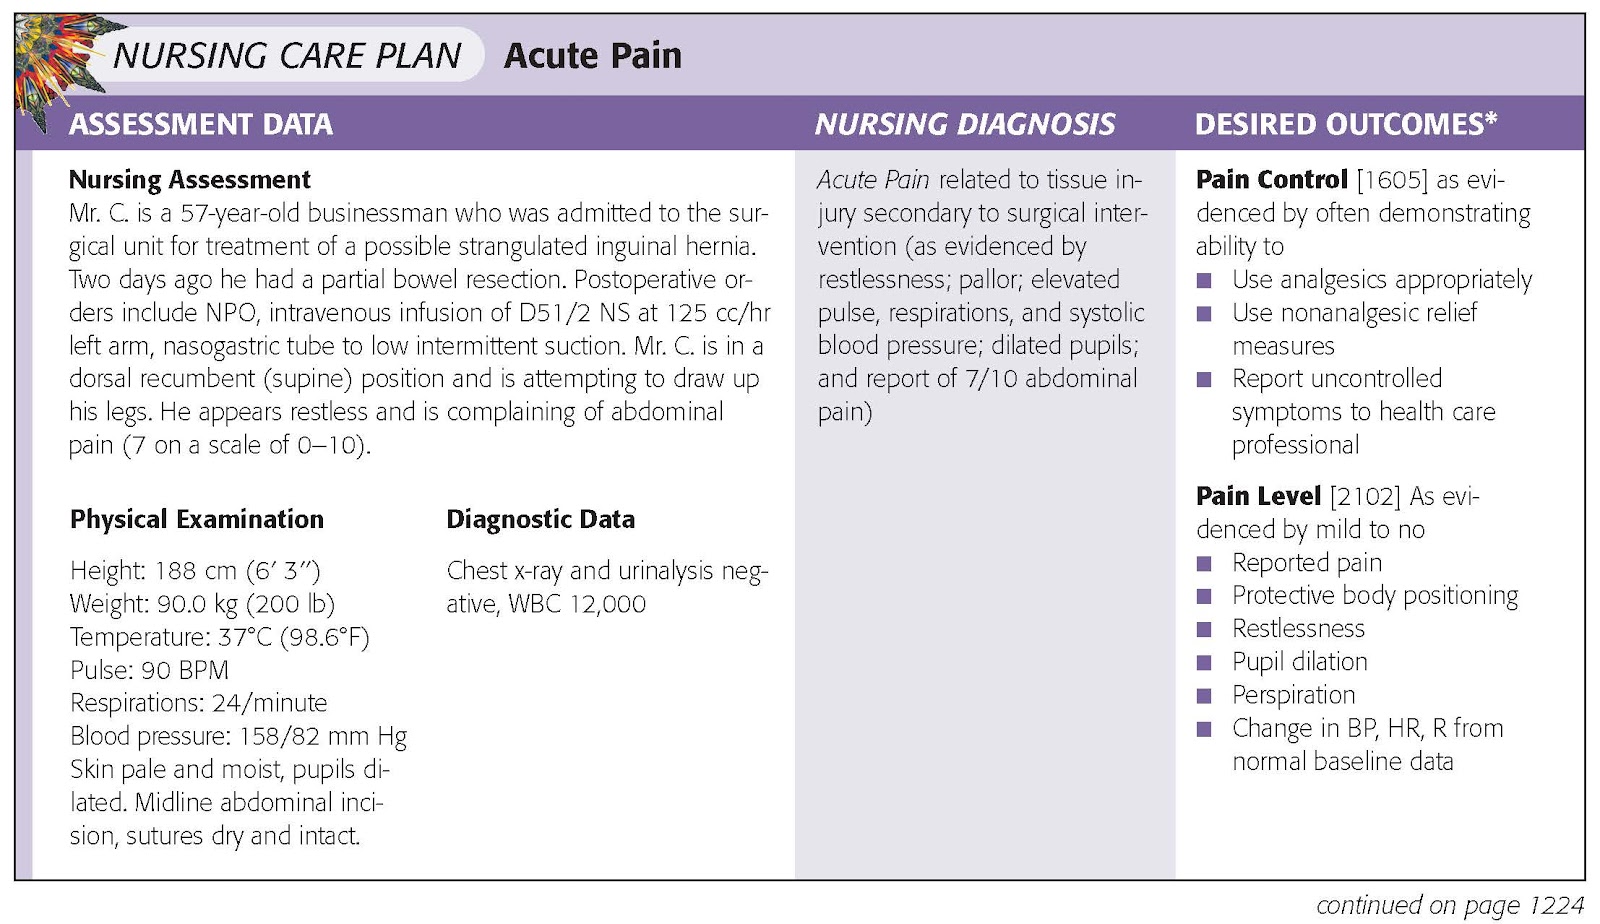
Acute pain nursing diagnosis is one of the most frequently written but least accurately documented diagnoses on hospital floors. I have watched experienced nurses spend twelve minutes typing up a perfectly adequate assessment, only to have a chart auditor flag it within an hour for missing a critical component. The problem is never the knowledge gap. It is the system and the pace at which you are working when the documentation happens. A correct acute pain diagnosis follows a specific PE format — Problem, Etiology, and Symptoms. The problem statement should read as Acute Pain, the etiology must reference a specific physiological insult or surgical procedure, and the symptoms need to include measurable indicators: location, intensity using a validated scale, quality descriptors, and timing patterns. That is the textbook standard. In practice, most nurses write something that looks like this on their shift: "Patient has acute pain due to hip replacement." That is not a complete nursing diagnosis. It is missing symptom data entirely. It will not hold up if anyone reviews the chart after discharge, and it does not guide actual care planning either. I remember working a med-surg rotation where we had three patients admitted for acute cholecystitis. All three nurses wrote basically the same diagnosis during the shift change overlap. Two of the charts got flagged by the auditors. The third one was accepted because the incoming nurse noticed a discrepancy — the pain scale had been documented as 8/10 but the patient was actively playing cards and laughing on the unit television. That mismatch between subjective report and observable behavior is exactly the kind of thing auditors look for. The workaround I used for that particular case was adding a brief note in the nursing assessment section explaining the patient's baseline behavior pattern and documenting that the reported pain level was consistent with the physiological diagnosis. It took thirty seconds and eliminated the audit flag. You do not need to convince anyone the patient is faking. You just need to acknowledge the discrepancy and document your clinical judgment about it.
The most common pitfall I see with acute pain nursing diagnosis is conflating the medical diagnosis with the etiology in the nursing diagnosis. When the etiology reads "due to renal calculi," you are restating the physician's diagnosis, not identifying the nursing concern. The correct etiology for a pain nursing diagnosis should reference the nociceptive or inflammatory process that the nurse is managing independently. "Related to tissue trauma and inflammatory response secondary to nephrolithiasis" is more accurate. It tells another clinician what you are actually addressing in the care plan without relying on the medical diagnosis alone. Here is something that tends to surprise new nurses: documenting pain as 0 out of 10 after an intervention does not mean you drop the nursing diagnosis. The diagnosis stays active until the underlying etiology has fully resolved. If you document a post-operative patient at 2/10 pain two hours after administration of oxycodone, you still carry the acute pain diagnosis because the surgical trauma is still present. What changes is the severity descriptor in the symptoms portion of the diagnosis. You move from "moderate to severe" to "mild" or you simply remove the severity qualifier altogether. The diagnosis persists until the pain source is clinically resolved, not until the score hits zero on a single assessment.
How to Write and Maintain the Diagnosis Across a Shift
Start with the admission assessment. Do not wait until the pain medication due time to begin documenting the etiology and symptom cluster. Write the initial pain nursing diagnosis within the first thirty minutes of the shift, before you have done anything about the pain yet. That gives you a baseline to compare every subsequent intervention against. Without a documented baseline, your pain reassessments become isolated data points instead of a trend. Use the PEP mnemonic during your assessment: Provoking and palliating factors, Each quality of the pain, Pain characteristics including location, severity, and timing. That is the same PQRST framework most programs teach you, but written with the specific acronym makes it faster to run through mentally while you are standing at the bedside. You do not need to write all five letters out in the formal diagnosis line. Just use them to make sure your assessment is complete before you commit it to the chart. For post-surgical patients, document the surgical procedure as the etiology reference. For trauma, document the specific injury type and mechanism. For medical admissions with pain as the primary complaint, the etiology is usually "related to inflammatory process" or "related to tissue ischemia" depending on the presenting condition. Never write "related to patient's condition." That is a red flag for every auditor and every charge nurse who reviews the chart. It is too vague to be useful and it tells no one what you are actually treating.
Get the Full Details
One more thing that gets overlooked: the interdisciplinary language mismatch. Physicians document pain levels in their progress notes using different scales or different terminology than what appears in the nursing flowsheet. I had a patient whose surgical attendings wrote "patient is comfortable" in their notes while the nursing pain assessments showed 5 to 7 out of 10 consistently. The resulting audit trail looked contradictory and defensive. The fix was straightforward — add a short phrase to your nursing diagnosis documentation that acknowledges the patient's reported experience and your rationale for the documented score. Something as simple as "patient reports 6/10 despite verbal tolerance and engagement with family" closes that gap before anyone can question the discrepancy. The real downside to this approach is that it requires discipline during busy shifts. You cannot write a solid acute pain nursing diagnosis in twenty seconds during a code or a rapid admit-discharge turn. It takes approximately four to six minutes of focused assessment and documentation time per patient. On a twelve-bed med-surg floor during peak admission hours, that is manageable if you start early in the shift. It becomes impossible if you push it to the end of your shift when you are already behind on medications and discharge paperwork. Plan around it. Front-load the pain assessment and diagnosis during your initial walkthrough rather than trying to catch up on it after everything else.