
Understanding the Pain Assessment Faces Scale
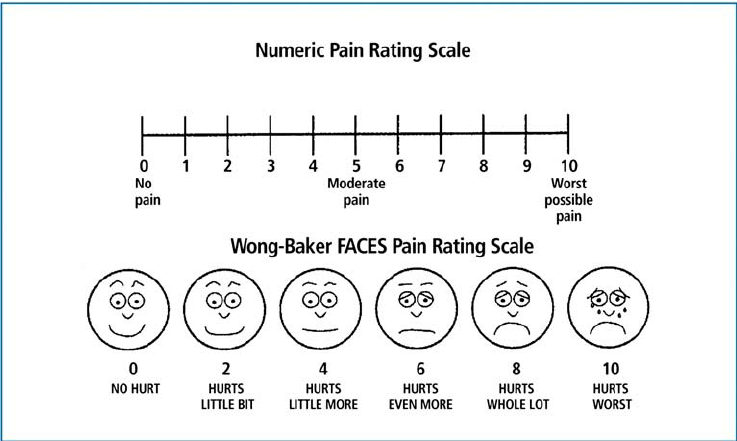
The Pain Assessment Faces Scale, often called the FACES scale or Wong-Baker scale, is a visual tool clinicians use to measure pain intensity. It displays six faces ranging from a smiling face with no discomfort to a tearful face expressing severe pain. Patients point to the face that best represents their pain level. I have used this tool extensively in pediatric and geriatric settings over the past twelve years. The Faces Pain Assessment Faces Scale works well in most cases, but it has clear limitations that many practitioners overlook.
How the Scale Works in Practice
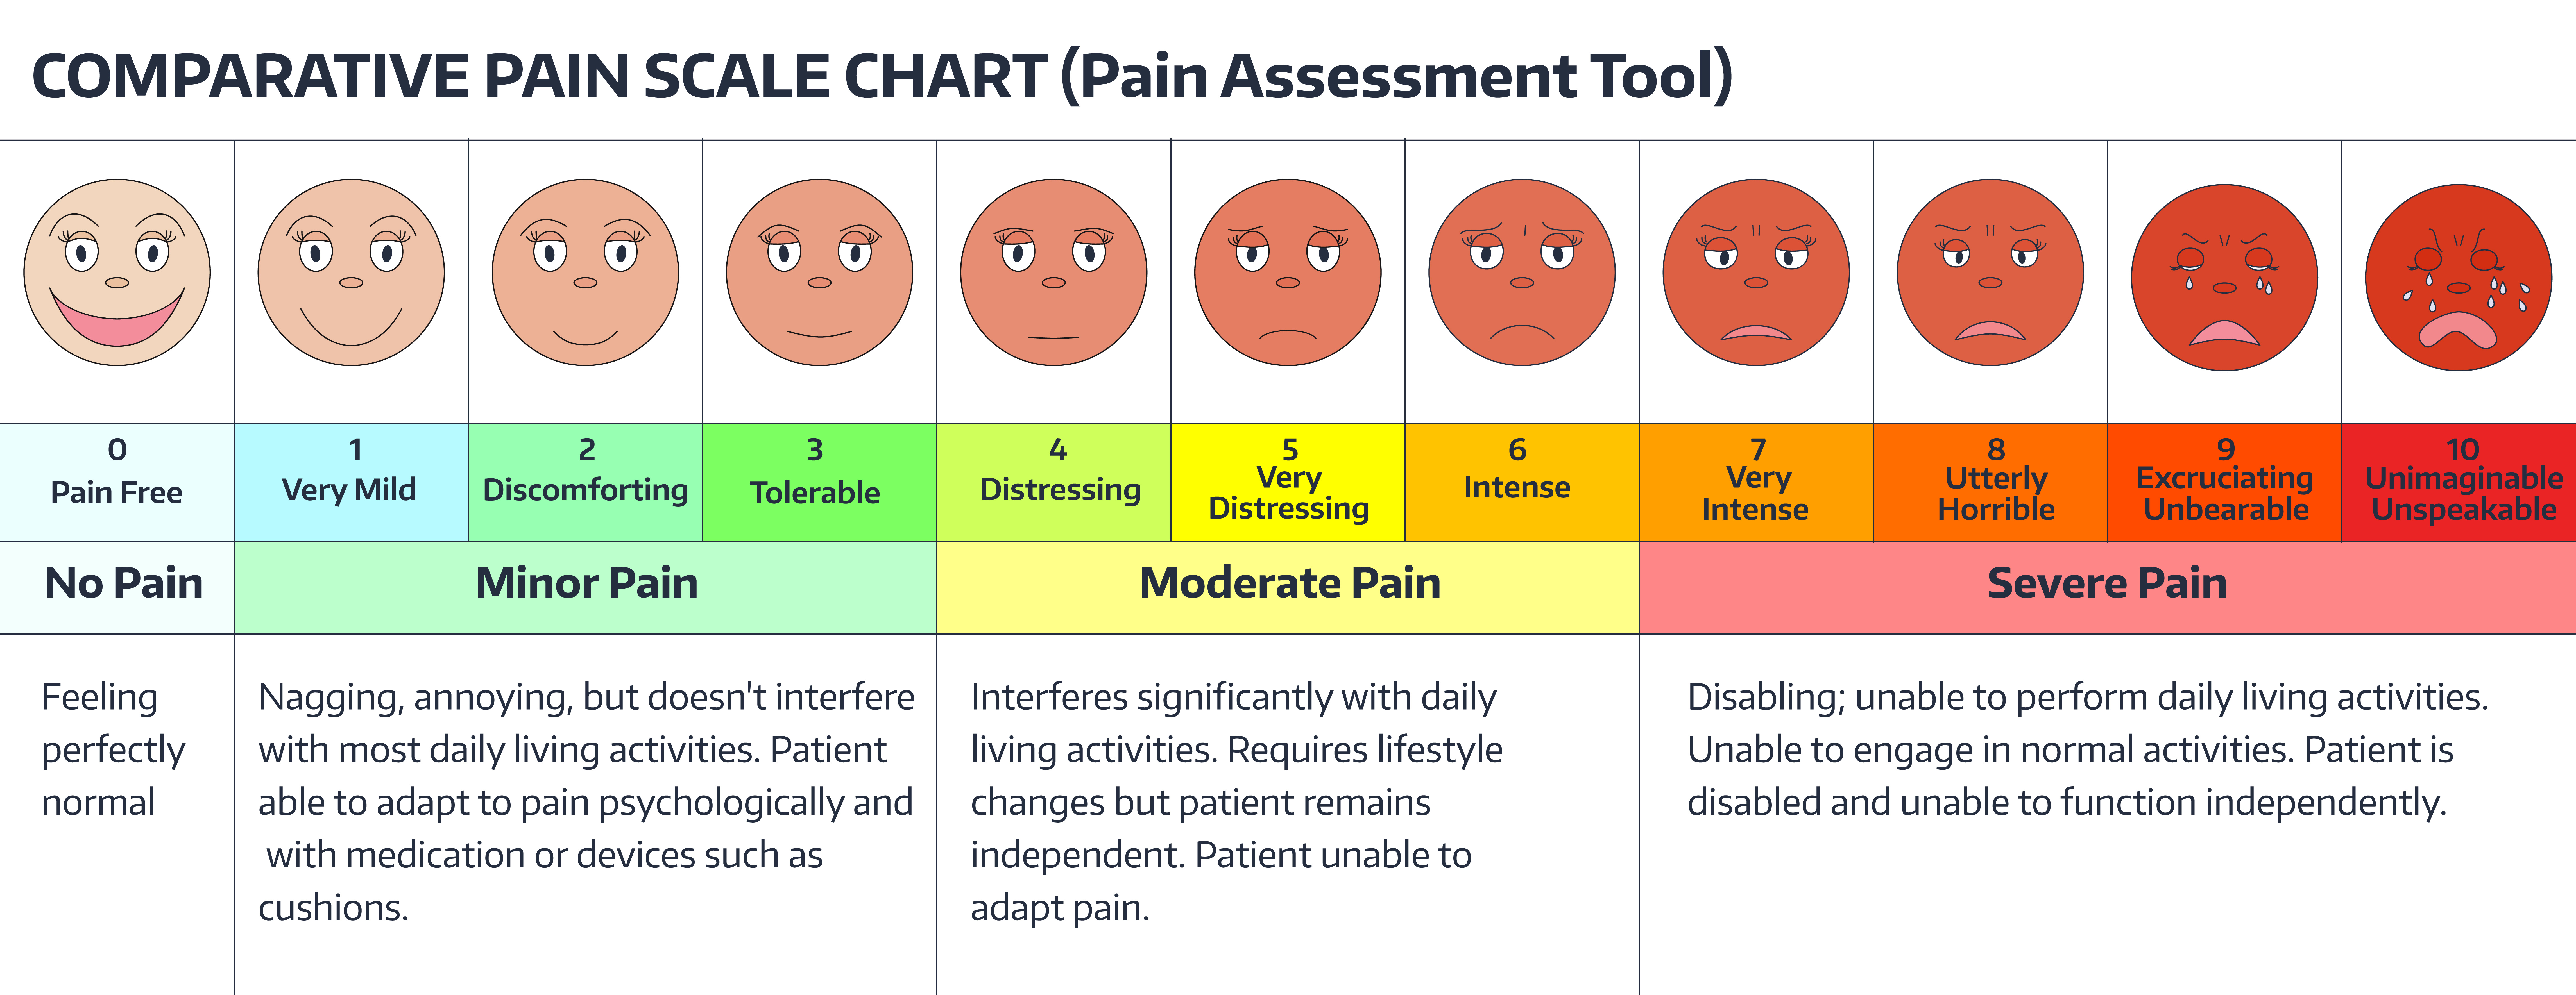
Each face represents a numerical value from 0 to 10. Face 0 shows a happy expression indicating no pain. Face 2 represents mild discomfort. Face 4 indicates moderate pain. Face 6 suggests fairly severe pain. Face 8 reflects very severe pain. Face 10 depicts the worst pain imaginable. The scale was developed by Keri Wong and Donna Baker in 1983. They worked specifically with children who struggled to understand abstract numerical scales. The visual approach made pain measurement more accessible for young patients. When I first started using the FACES pain rating scale, I noticed something interesting. Children aged 3 to 4 could reliably use the scale, but children under 3 struggled. They could point to faces, but they had difficulty connecting the facial expression to their actual pain experience.
The standard administration takes about 2 to 3 minutes. You show the patient the scale, explain that each face represents a different level of pain, and ask them to point to the face that matches how they feel. That is the entire process.
Get the Full Details
Common Misunderstandings About the Faces Pain Scale
Many healthcare workers treat the Faces pain assessment scale as a standalone diagnostic tool. This approach creates problems. The scale measures pain intensity only. It does not assess pain quality, location, duration, or functional impact. I encountered a specific issue with elderly patients in a long-term care facility. Several residents scored their pain as a 2 on the FACES scale consistently. When I investigated further, I discovered they had severe pressure ulcers. They did not want to appear dramatic or bother staff. They minimized their pain ratings. The workaround was to combine the Faces Pain Assessment Faces Scale with verbal descriptors. I asked patients to describe their pain using words like mild, moderate, or severe. This conversation revealed pain levels much higher than the face ratings suggested.
Another frequent mistake involves cultural interpretation. In some Asian cultures, stoicism is highly valued. Patients may rate their pain lower than experienced to avoid being seen as weak. In Middle Eastern cultures, emotional expression of pain is more acceptable. These cultural differences directly affect scale reliability.
Administration Techniques That Actually Work
Proper administration requires specific techniques. Start by showing the complete scale to the patient. Ensure adequate lighting and proper viewing distance. The faces should be clearly visible without glare or distortion. For pediatric patients, use simple language. Say "point to the face that looks like how you feel inside." Avoid technical terminology. Do not ask "on a scale of 0 to 10" with young children. They do not grasp numerical concepts reliably. I found that asking patients to rate their pain before, during, and after an intervention provides valuable data. This serial assessment tracks treatment effectiveness. The change in face selection over time indicates whether medication or other interventions are working.
For non-verbal patients, observe behavioral indicators alongside the scale. Restlessness, grimacing, guarding behavior, and vocalizations provide additional context. The Faces Pain Assessment Faces Scale alone may underestimate pain in these populations.
Limitations and When to Use Alternatives
The scale has documented limitations. It works poorly for patients with cognitive impairment. Dementia patients may select faces randomly without understanding the connection between facial expression and pain intensity. Patients with certain facial paralysis conditions cannot reliably use the scale. Bell's palsy, stroke survivors with facial weakness, and patients with congenital facial anomalies struggle to interpret the expressions correctly. I recommended alternative tools in these scenarios. The FLACC scale works better for infants and non-verbal patients. The Numeric Rating Scale suits literate adults. The Visual Analog Scale provides continuous measurement for research settings.
TheFaces Pain Assessment Faces Scale typically takes 2 to 5 minutes for administration. Documentation requires recording the face number selected. This documentation supports billing and quality metrics in clinical settings.

Practical Applications Across Populations
Pediatric pain management represents the primary use case. Emergency departments use the scale for acute pain assessment. Surgical units employ it for post-operative pain monitoring. Oncology clinics rely on it for chronic pain management in children. Geriatric applications require careful consideration. Frail elderly patients may have difficulty distinguishing between facial expressions. Vision impairment affects scale usability. Hearing loss complicates administration instructions. I encountered a specific problem with a 78-year-old patient recovering from hip replacement surgery. She scored her pain as 2 on the FACES scale consistently for three days. Physical therapy revealed she was not participating in mobilization due to uncontrolled pain. The face ratings underestimated her actual pain experience.


