How the Pediatric Assessment Triangle Actually Works in the Field
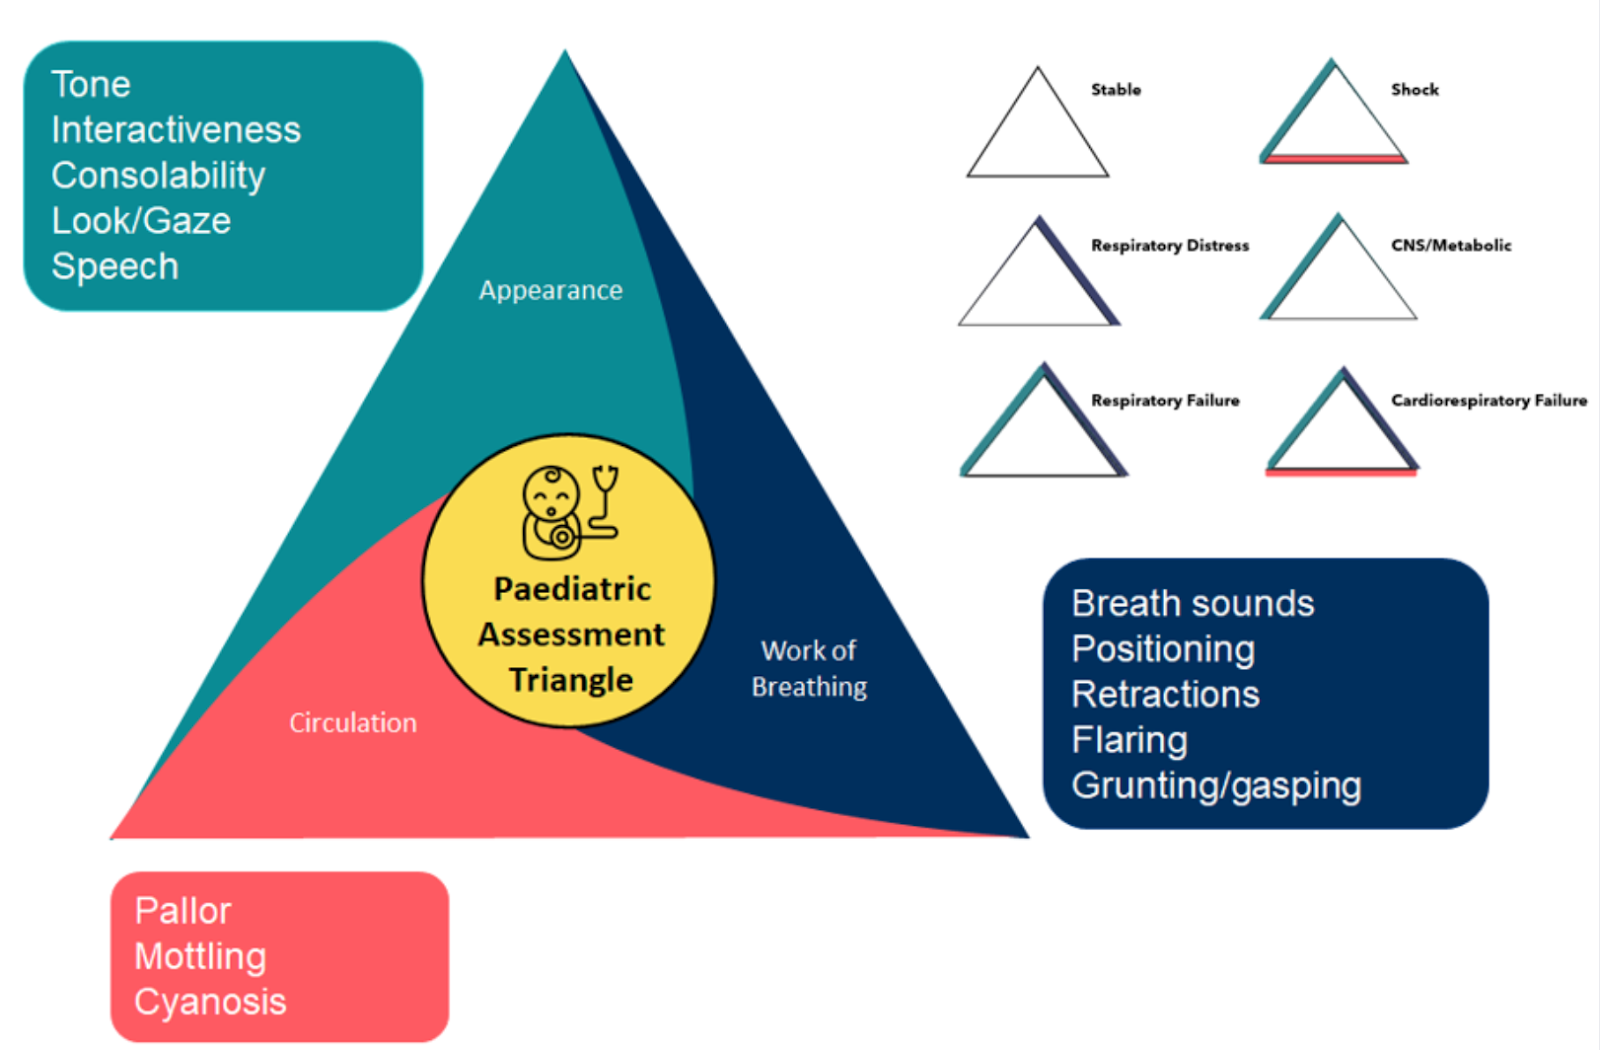
The Pals Pediatric Assessment Triangle is a rapid visual tool used at the very first moment you see a sick child. You don't touch them yet. You don't take a heart rate. You stand at the end of the bed or look at them on the gurney and assess three things simultaneously. Appearance, work of breathing, and circulation to skin. Each one tells you whether this kid is going to crash in the next thirty seconds or whether you have time to be thorough. I learned this on a Saturday night in the ED when a mother brought in what she called a "stomach bug." The kid was sitting on the floor playing with a toy. Normal appearance score. But the work of breathing was clearly elevated and the skin was mottled. This kid was in early decompensated shock and I should have flagged it immediately instead of waiting for the full exam. We started IV fluids and called for a pediatric anesthesia consult before the vitals even came back. The triangle caught it before the numbers did.
What the Pals Pediatric Assessment Triangle Actually Measures
The triangle breaks down into three domains, and each domain has five possible appearance descriptors that most people shorten to the word SAFE: Socialization, Affect, motor activity, speech or language, and consistency of appearance with normal growth. A kid who is looking around, making eye contact, and interacting normally scores well here. A kid who is limp, not tracking, or inconsolable scores poorly. You pick this up in under ten seconds. Work of breathing covers the mechanics. Are they using accessory muscles? Is there nasal flaring? Grunting? Retractions? You also consider whether the respiratory rate looks appropriate for the age, though the triangle is meant to be quick enough that you're not pulling out a chart. Just looking at whether the effort is visibly increased is enough to move them from normal to abnormal. Circulation to skin is the third leg. You look at color and perfusion. Is the skin pink and warm? Or is it pale, mottled, or cyanotic? This isn't about pulse oximetry or capillary refill time at this stage. You're doing a visual scan. Mottling over the trunk, especially, is a red flag that the child is compensating poorly.
Each of the three legs produces a score of normal or abnormal. If all three are normal, the child is stable and you have time. If any one is abnormal, you escalate. If two or all three are abnormal, the child is critically ill and you treat aggressively and immediately while calling for help. The triangle is not diagnostic. It's a triage signal. One thing beginners consistently get wrong is treating the triangle as a substitute for a full assessment. It is not. It is the first five seconds before everything else. I once had a resident spend two minutes analyzing the appearance component of a seizure child who was actually post-ictal and fine. Meanwhile the work of breathing component showed subtle stridor that needed attention. The triangle rewards speed, not deliberation. Another counter-intuitive point is that normal work of breathing does not equal a stable airway. A child with a large foreign body aspiration can have perfectly normal respiratory effort for a long time before suddenly obstructing. The triangle will show normal work of breathing and the child may appear fine, but the appearance score might be off because they're agitated or fearful. In practice, if the clinical story doesn't match the triangle, trust the story. I had a four-year-old who came in after a likely peanut aspiration. Work of breathing looked normal at first glance. But the appearance was off and the history was right. We intubated before he desaturated. The triangle flagged the concern but the history told the real story.
Get the Full Details
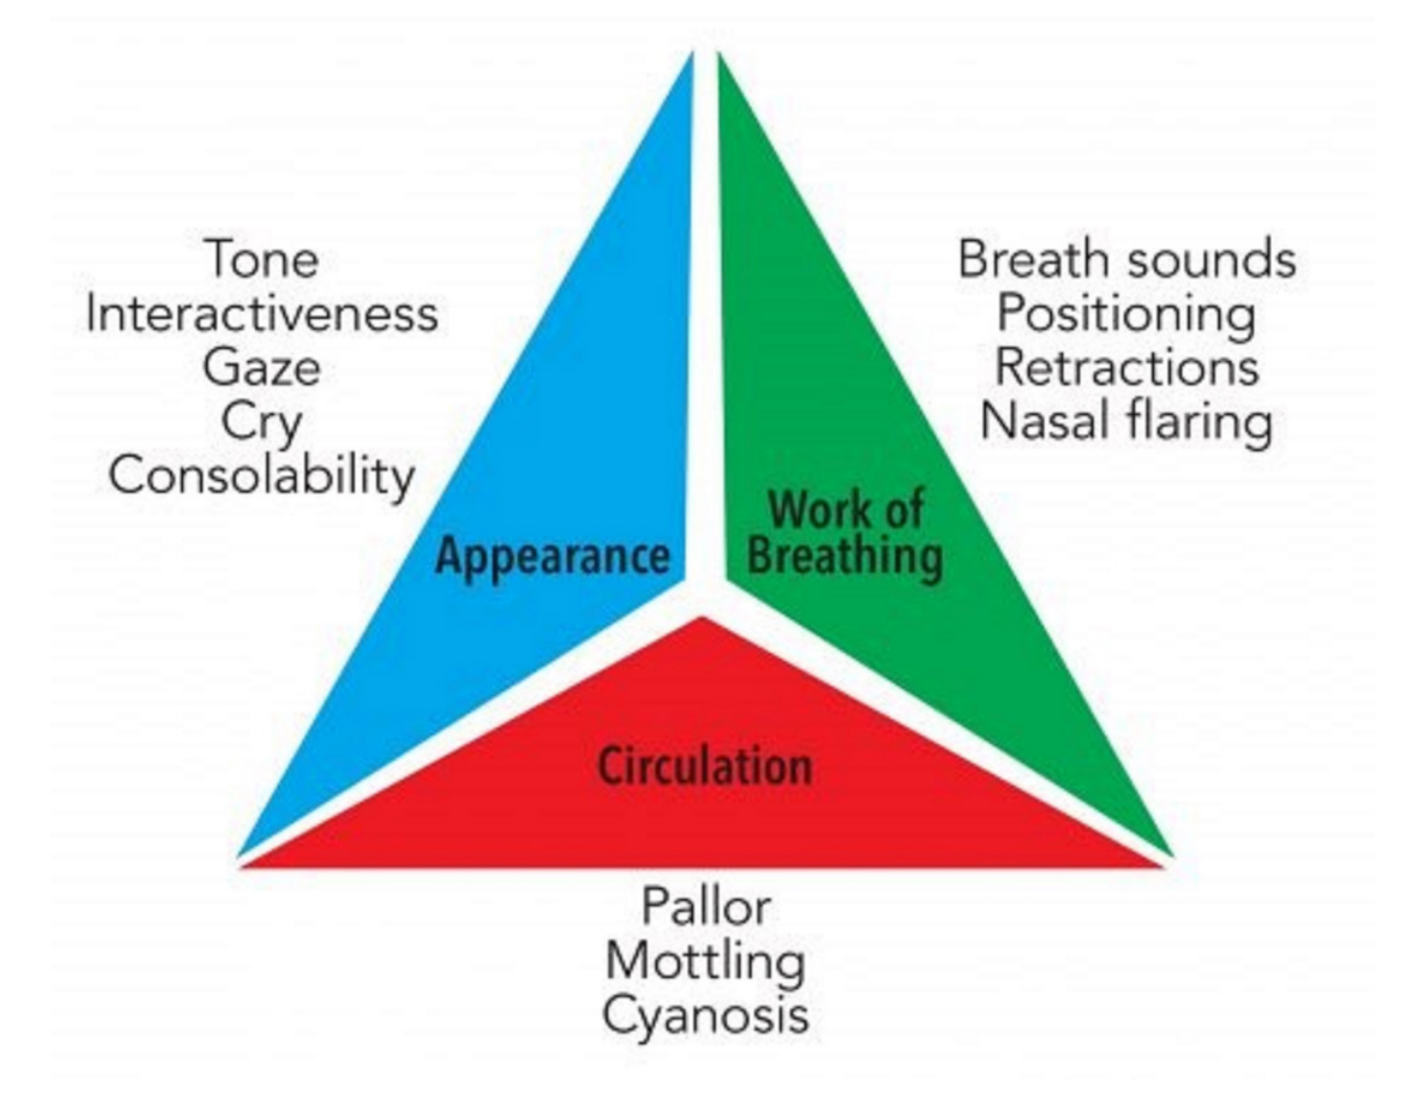
The triangle also breaks down in certain populations. Children with chronic lung disease may always have increased work of breathing. That doesn't mean they're acutely deteriorating. You have to know their baseline. Similarly, children with darker skin tones can make the circulation to skin assessment harder because mottling and pallor are less visible. In those cases you look at the lips, tongue, and nail beds more carefully, or factor in perfusion signs like delayed capillary refill once you actually touch the child. The triangle is a starting point, not a finished diagnosis. If you want a visual reference to hang in the resuscitation bay, most institutional websites and the AAP publish printable versions. Search the AHA PALS provider manual or your hospital's emergency department intranet for the triangle diagram. You'll find it as a standard one-page figure. That said, memorizing it is more useful than printing it because you won't have time to look it up when a child arrives with respiratory distress. The Pals Pediatric Assessment Triangle won't replace your judgment, but it will replace your hesitation. Most of the time you can tell within fifteen seconds whether a sick child needs immediate intervention or a calm workup. The trick is learning to trust that first impression instead of second-guessing it while you wait for a blood pressure that may not come back in time.