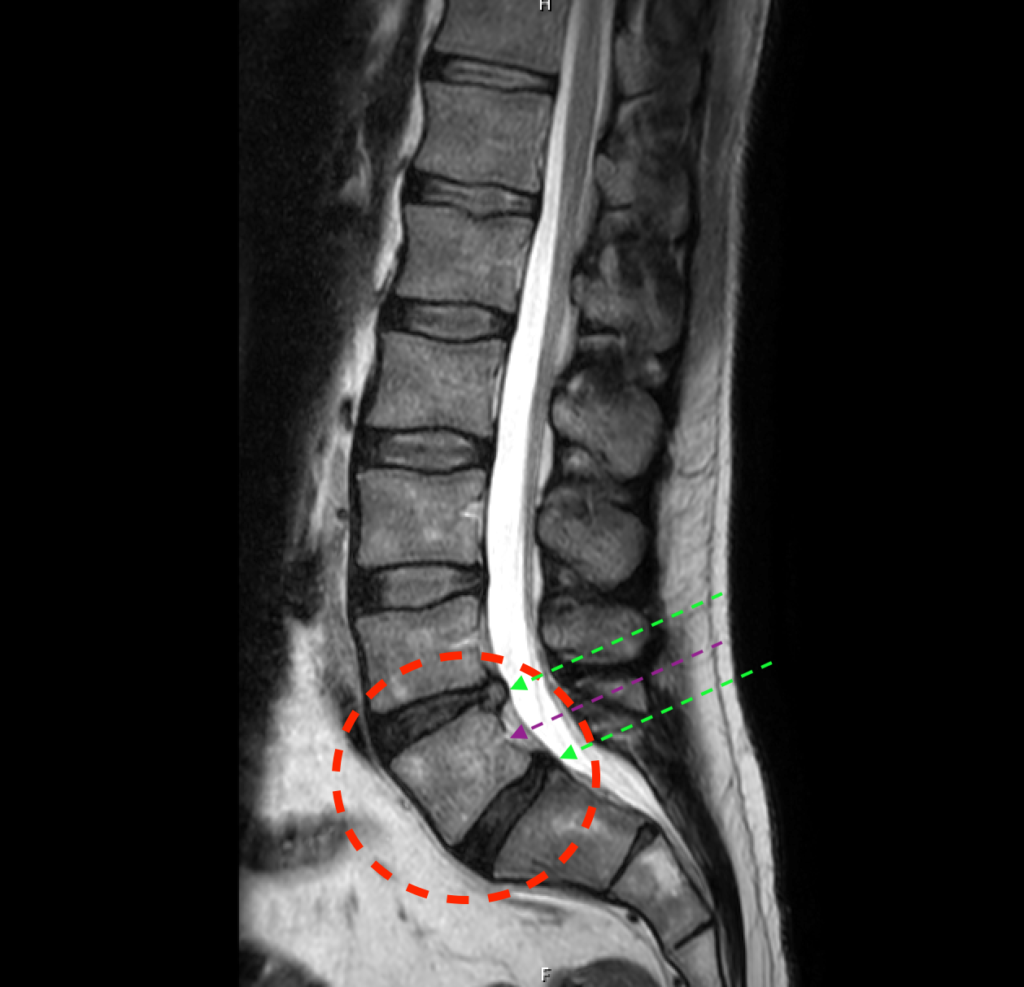
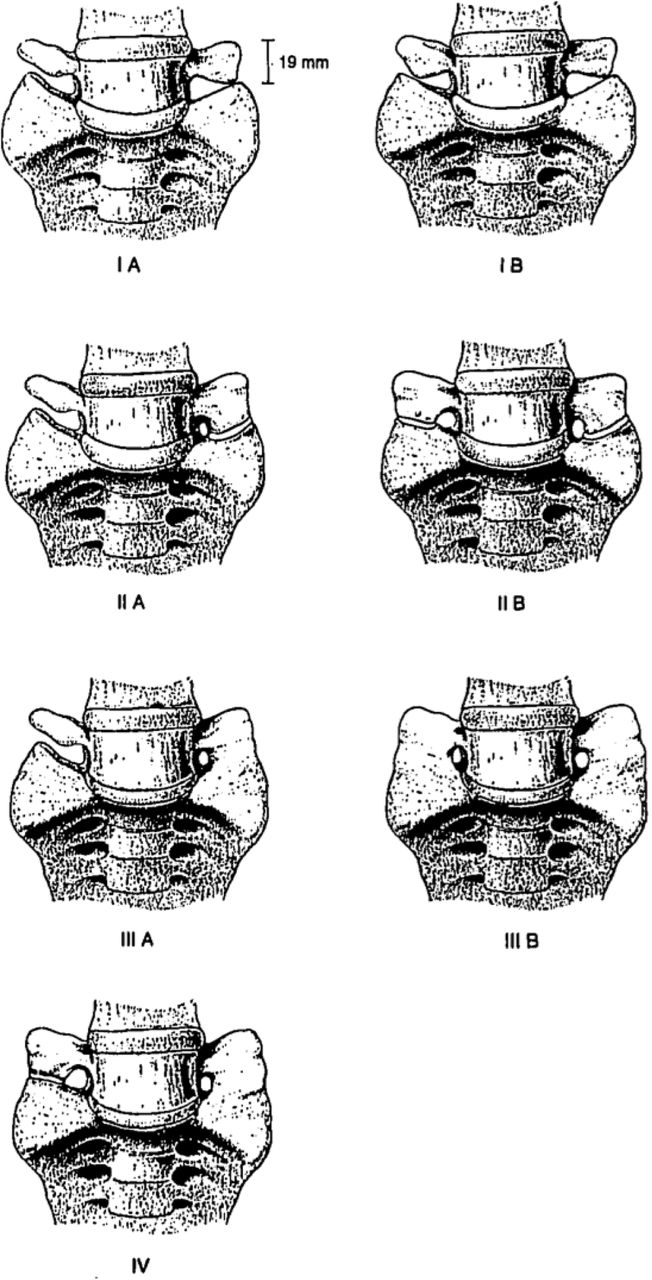
The sacrum is supposed to be fused. It's that triangular bone at the bottom of your spine wedged between the hip bones. L5 sits on top of it, and normally S1 doesn't move relative to the rest of the pelvis. Partial lumbarization of S1 means some of those fusion points didn't quite close during development. You end up with one or two segments that should be solid having instead retained a disc-like space. It's not rare - maybe 10-15% of people have some degree of it, though most never know.
The terminology gets sloppy in radiology reports. Some writers call it sacralization when L5 drops into the sacrum instead. They're opposites. Lumbarization is the upper vertebra failing to merge downward. Sacralization is the lower one pulling up. Get them backwards and your surgical plans look wrong.
Partial Lumbarization Of S1: Clinical Presentation
Patients usually present because they already had back pain from something else and the CT happened to catch it. The disc space at S1 level can degenerate slightly faster than surrounding segments because it's mobile where it shouldn't be. That extra motion creates microtrauma over decades. You see it on MRI as increased T2 signal in the disc or endplate marrow edema.
I had a patient last year - 42-year-old mechanic, chronic low back pain for eight years. Imaging showed a clear disc space between S1 and S2 that shouldn't have been there. The real problem was that the pseudoarticulation was catching during extension. Standard PT wasn't touching it because nobody identified the anatomical variant. Once I mapped it clearly on flexion-extension X-rays, we knew what we were dealing with.
The diagnostic trick is remembering to check both sides. Sometimes you get partial lumbarization on the left and full sacral fusion on the right. That asymmetry creates rotational stress patterns that don't follow the usual mechanical low back pain models. The patient will complain of pain shooting into one buttock more than the other, and it won't track with typical radiculopathy patterns.
How to Actually Identify It
Start with standing AP and lateral X-rays. Look for a horizontal radiolucent line at the S1 level. That's your disc space masquerading as a fusion defect. The trick is distinguishing it from a fracture or degenerative cleft. A developmental pseudojoint will have smooth, corticated edges. Something traumatic looks ragged.
CT with 3D reconstruction is where this becomes concrete. You can see the actual morphology of the transverse processes and whether they're fusing into the ilium on either side. Some patients have incomplete fusion anteriorly but solid posterior elements. Others are the reverse. The pattern matters for surgical planning if you ever need to go in.
MRI shows the soft tissue consequences. Watch for disc desiccation at that abnormal segment. The disc might look older than it should for the patient's age. Also check for nerve root impingement at the foraminal level - the extra mobility can stretch the L5 or S1 roots differently than a normal spine.
I learned to measure the intervertebral distance specifically. Normal sacral segments show zero distance. When you see even 2-3mm of space at S1 level in an adult, that's your abnormality. Compare it to L4-L5 above for reference. The disc at the pseudojoint will often be narrower than the adjacent normal disc.
Treatment Realities
Most cases don't need intervention beyond conservative management. The pseudoarticulation is stable enough that it doesn't cause problems in the majority of people. When it does cause issues, start with activity modification and physical therapy targeting the multifidus and transversus abdominis. Those deep stabilizers compensate for the extra motion.
I've seen patients try standard McKenzie extensions for this and make it worse. The extension loads that pseudojoint directly. Instead, focus on flexion-biased exercises and core endurance. Hold positions longer - 30 seconds minimum rather than quick reps. The goal is building endurance in the stabilizers, not flexibility.
When conservative measures fail after six months, epidural steroid injections can help identify the pain generator. If the injection at S1-S2 level provides significant relief, you've confirmed the source. The volume should be smaller than typical - 1ml rather than 3ml - because you're targeting a specific articulation, not a broad inflammatory process.
Surgical options exist but carry real risks. Fusion of the pseudojoint can work, but you're operating on a segment that's already anomalous. The blood supply might be different. The bone quality could be altered from decades of abnormal mechanics. I'd only consider surgery after exhaustive conservative treatment and when the pain is genuinely disabling.
The alternative approach some surgeons use is decompression if there's nerve entrapment. But that doesn't address the underlying instability. You might relieve the root symptoms while leaving the painful pseudojoint intact. That's a tradeoff worth discussing honestly with the patient.
What I Wish Radiologists Would Do Better
Measure and report the exact dimensions of that disc space. "Possible lumbarization" isn't useful for a surgeon. Give me the mm of separation, the cortical margin characteristics, and whether there's associated degenerative change. The treating physician needs specifics, not hedging.
Also mention the contralateral side. If you see partial fusion on one side and normal anatomy on the other, that's clinically significant. Asymmetric variants create asymmetric stress patterns that affect treatment decisions. Don't just report what you see in passing.
I've reviewed scans where the report missed the anomaly entirely because the reader was focused on something else. The lumbarization was right there at S1, obvious once you knew what to look for. Take an extra five seconds to trace each sacral segment. It prevents missed diagnoses.
Gallery Partial Lumbarization Of S1
Lumbarization Of S1 Vertebral Body
Lumbarization Of S1 Vertebral Body
Lumbarization Of S1 Vertebral Body
Figure 2 from Morphological traits in sacra associated with complete and partial lumbarization ...
Pp for lumbarization and sacralization by Dr Dhruv Taneja Assistant P…