The Torso Isn't Just One Solid Chunk of You
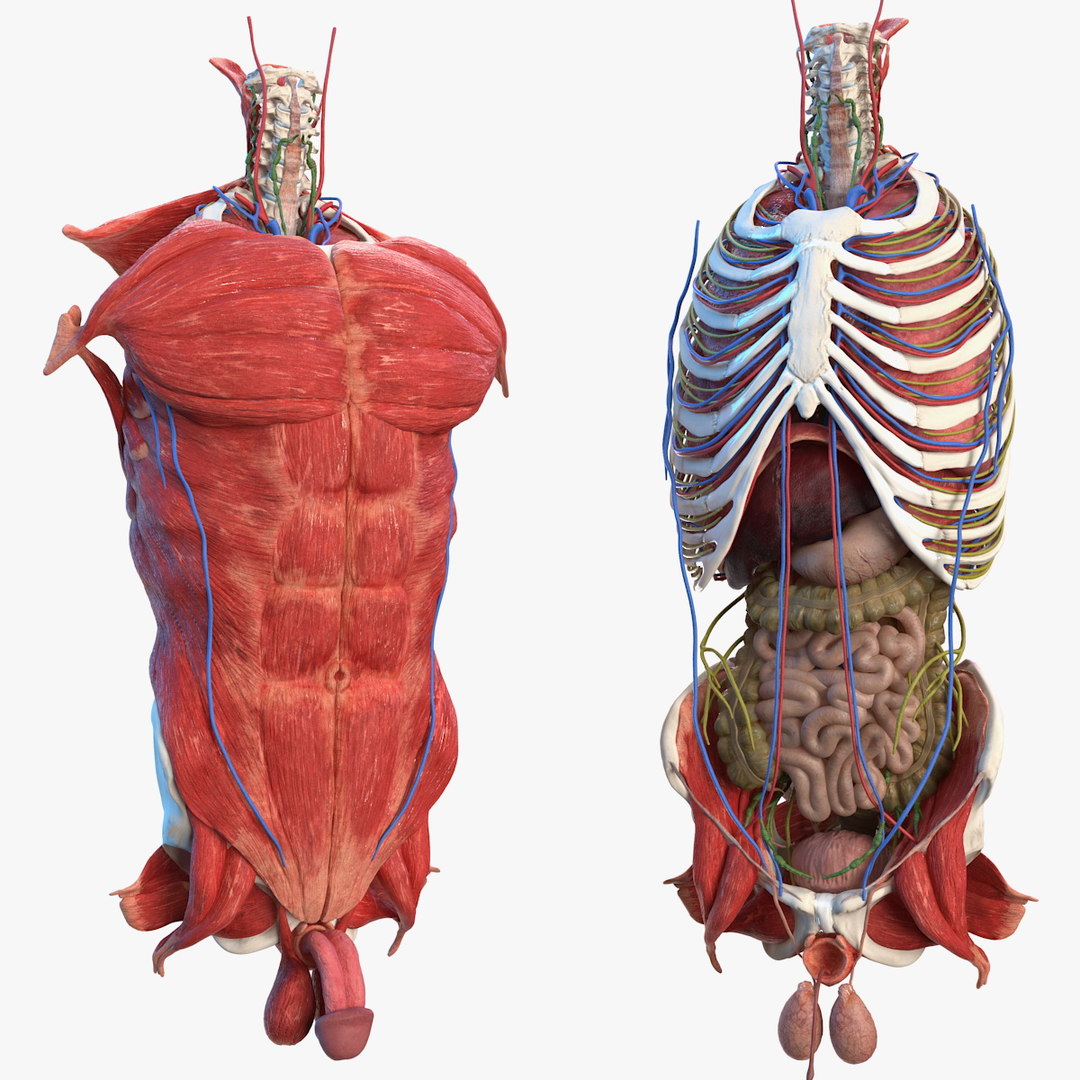
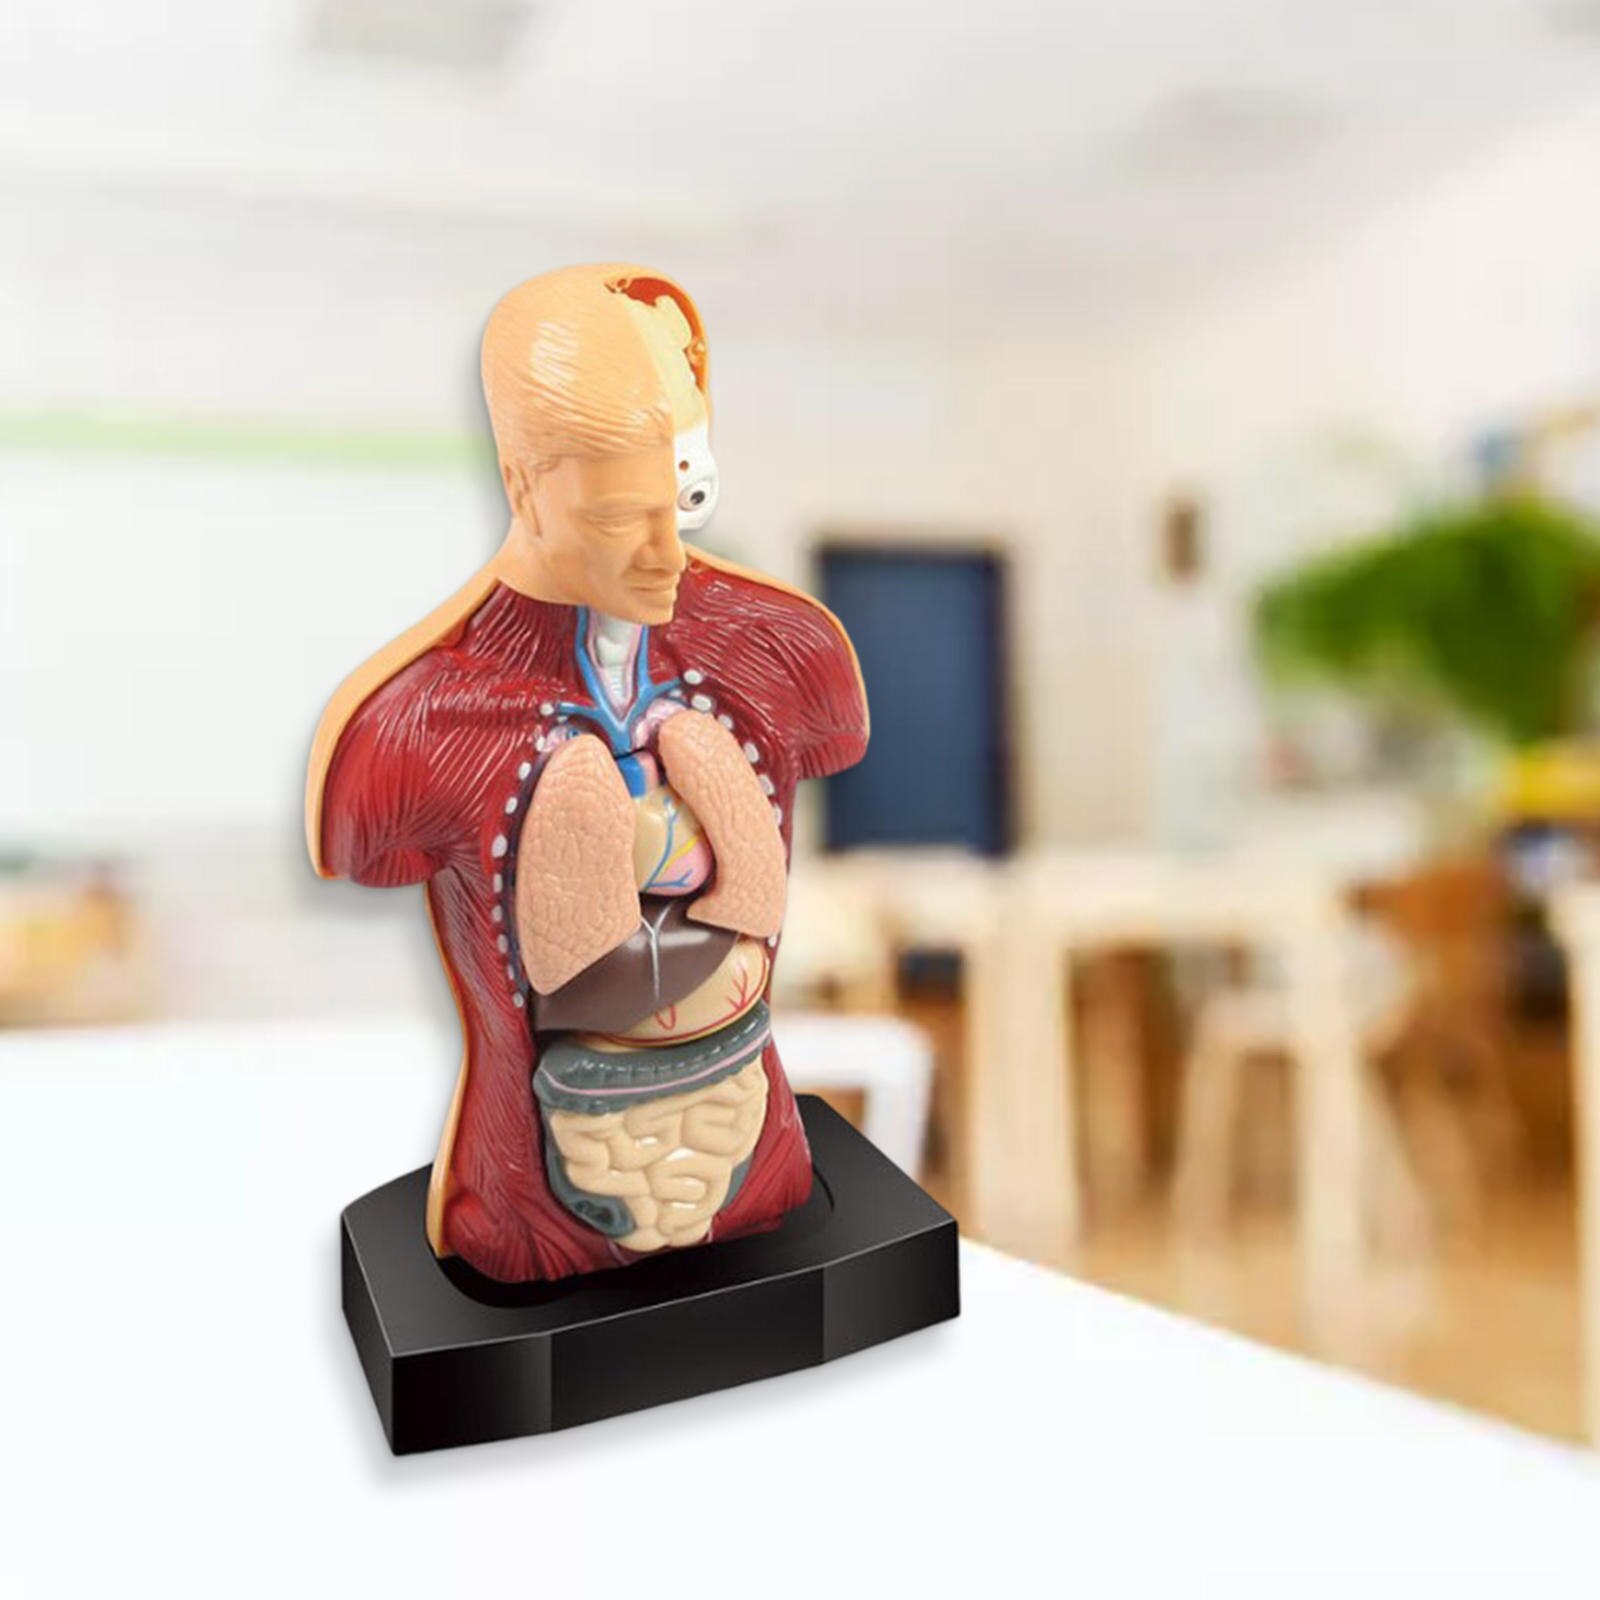
When people talk about the torso, they're usually referring to the trunk of the body—the central mass between the neck and the hips. But if you actually try to teach someone about it, or even just draw it on a diagram for a medical illustration job, you quickly realize it's not nearly as simple as saying chest, stomach, and back. The torso is a collection of regions, cavities, and layers that interact in ways most textbooks gloss over. I spent years doing anatomical reference work for game development and medical training materials, and the stuff I ran into with torso anatomy is what actually matters in practice. The torso is divided into two major cavities: the thoracic cavity and the abdominopelvic cavity. The thoracic cavity is protected by the rib cage and contains the heart, lungs, and major blood vessels. The abdominopelvic cavity sits below the diaphragm and houses the digestive organs, kidneys, and reproductive organs. Between these two cavities sits the diaphragm, a dome-shaped muscle that's basically the most important breathing muscle you own. When you inhale, it contracts and flattens. When you exhale, it relaxes back into a dome shape. That's it. It's not complicated, but it's also not something most people understand when they're trying to get the proportions right on a drawing or model.
Working With Parts Of Body Torso in Practice
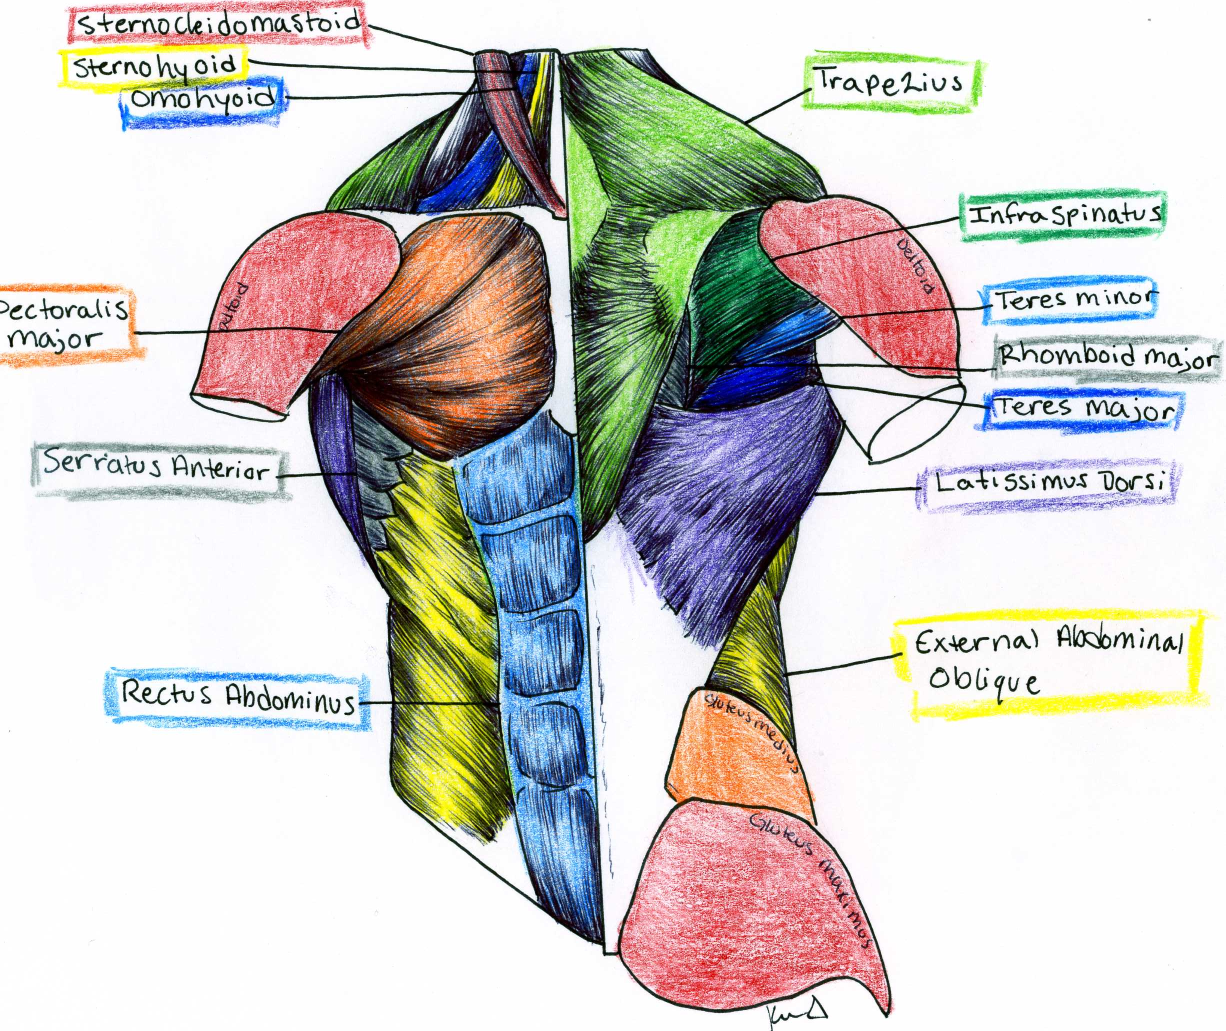
The surface anatomy of the torso is where things get interesting. The bony landmarks are your real guideposts: the clavicle, the sternum, the xiphoid process, the iliac crests, the costal margin. These are the points you can actually feel on a living person. Everything else—the muscles, the organs—is layered underneath and largely invisible from the outside. In my work, I'd always start by having the person or reference stand in a neutral anatomical position and then map those bony landmarks onto the surface before even thinking about muscle groups or organ placement. The external abdominal wall is built from three layers of flat muscles: the external oblique, the internal oblique, and the transversus abdominis. Each layer runs in a different direction. The external obliques run downward and forward, like your hands in your front pockets. The internal obliques run perpendicular to those, upward and forward. The transversus abdominis wraps horizontally around the core. This layered arrangement is why your core can rotate, flex, and stabilize—all at the same time. Beginners always draw the abdomen as a single flat surface or just slap on a six-pack without understanding the underlying geometry. The six-pack (rectus abdominis) is just one structure sitting on top of all three of those flat muscle layers, and it only shows up clearly in people with low body fat. One thing that trips people up constantly is the distinction between the thorax and the abdomen. The thorax is technically only the upper part of the torso—the rib cage area. The abdomen is everything below the thorax down to the pelvis. The entire structure from the base of the neck to the pubic symphysis is the trunk or torso. I remember working with a sculptor who kept making the waistline way too high on his figures because he was confusing the natural waist with the bottom of the rib cage. The bottom of the rib cage (the costal margin) is actually several inches above the natural waist. That gap between them is where the internal obliques and transversus abdominis fan out, and it creates the subtle taper that makes a torso look natural instead of blocky.
Here's a specific problem I ran into that nobody really warns you about: when you're building a digital human model or doing any kind of 3D work involving the torso, the skin doesn't move uniformly over the muscles. I was rigging a character model once and the torso mesh was deforming horribly during rotation animations. The problem wasn't the mesh resolution or the bone placement. It was that I'd treated the torso as a single deformable unit. In reality, the skin slides over the underlying muscle layers, and each muscle layer can shift slightly relative to the others. The solution was to add secondary deformation bones along the costal margin and the iliac crest, with weight maps that simulated that sliding effect. It took about four hours to get it right, but once it was done, the rotation and bending animations looked completely natural instead of like the character was wearing a poorly fitted wetsuit. The back of the torso gets short shrift in most anatomy references, but it's arguably the most structurally complex region. The erector spinae group runs vertically along the entire length of the spine. The latissimus dorsi is a massive flat muscle that covers the lower back and inserts into the humerus. The trapezius covers the upper back and connects the skull to the shoulders and spine. These three muscle groups overlap in ways that create the distinctive contours of a developed back. Most people drawing or modeling the torso from behind just shade in a vague outline and call it a day. The real detail is in how the scapula sits on top of the rib cage and moves with arm motion, how the spine creates a vertical groove down the center, and how the iliac crest creates a curve at the base. Internal organ placement is another area where convention and reality diverge. The liver is on the right side, the stomach is on the left, the spleen is tucked under the rib cage on the left, and the appendix is in the lower right quadrant. But organ size and position vary significantly between individuals. A full stomach pushes against the diaphragm and can shift nearby organs. Body position matters too—organs shift when you lie down versus stand up. I learned this the hard way when I was cross-referencing CT scan images with surface anatomy diagrams and noticed that the liver's inferior edge extended well below the costal margin in some subjects and barely reached it in others. There's no single "correct" position. The textbook diagrams are averages, and real human bodies don't care about averages.
Get the Full Details

If you're learning torso anatomy for artistic or medical purposes, palpation is your best tool. Find a willing friend or partner and have them stand in front of you. Locate your own sternum, then trace the costal margin down to the xiphoid process. Move your hands down to the iliac crests. Feel the midline from the umbilicus to the pubic symphysis. Now have them take a deep breath and feel the rib cage expand. Then have them flex their abs and feel the rectus abdominis contract. This takes maybe five minutes and will teach you more than reading twenty pages of descriptive anatomy. You'll understand spatial relationships that diagrams can't convey, like how the rib cage actually moves during breathing or how the abdominal muscles tighten and shift when you engage your core. The blood supply to the torso is another thing that matters more than you'd think if you're working in any applied field. The aorta runs down through the thoracic cavity as the thoracic aorta and continues as the abdominal aorta below the diaphragm. Intercostal arteries supply the spaces between the ribs. The celiac trunk, superior mesenteric artery, and inferior mesenteric artery branch off the abdominal aorta to supply the digestive organs. On the venous side, the inferior vena cava runs parallel to the aorta. This isn't just trivia. If you're doing anything involving trauma simulation, surgical training, or even just accurate depiction of bleeding, the vascular layout determines everything about where blood comes from and where it goes. Nerve supply follows a similar pattern. The intercostal nerves run along the inferior border of each rib. The phrenic nerve controls the diaphragm. The vagus nerve provides parasympathetic innervation to the thoracic and abdominal organs. The sympathetic trunk runs along either side of the vertebral column. Understanding this helps explain why certain injuries produce specific symptoms. Damage to the intercostal nerves causes not just loss of sensation in a band-like pattern around the chest but also weakness in the intercostal muscles, which compromises breathing. That's a clinical detail that most general anatomy sources mention in passing but rarely explain in a way that connects the anatomy to the actual function.
One counter-intuitive fact about the torso that most people miss: the torso is surprisingly flexible. We tend to think of the rib cage and spine as rigid structures, but they're designed to move. The thoracic spine has more rotational capacity than the lumbar spine. The rib cage expands laterally and anteriorly during breathing. The lumbar spine flexes, extends, and laterally bends. Even the sacrum has a small amount of mobility relative to the ilium at the sacroiliac joints. This flexibility is what allows us to breathe, bend, twist, and absorb impact. It's also why torso injuries can be so deceptive—a person might have significant internal damage with relatively minor external signs because the torso's structure absorbs and distributes force in ways that don't always produce obvious bruising or deformity. For anyone studying this for practical application, whether that's art, animation, medicine, or fitness, the key takeaway is that the torso is a dynamic structure, not a static shell. The bones provide the framework, the muscles provide movement and protection, the organs handle metabolism and reproduction, and the fascia and connective tissue hold it all together while allowing layers to slide past each other. Treat it as a system and you'll understand it far better than if you memorize a list of parts. And if you ever find yourself in a situation where you need to assess torso anatomy quickly—whether that's identifying muscle groups on a live model, interpreting an imaging study, or just drawing something that looks right—start with the landmarks. The rest follows from there.