Understanding The Anatomy That Keeps You From Falling Over
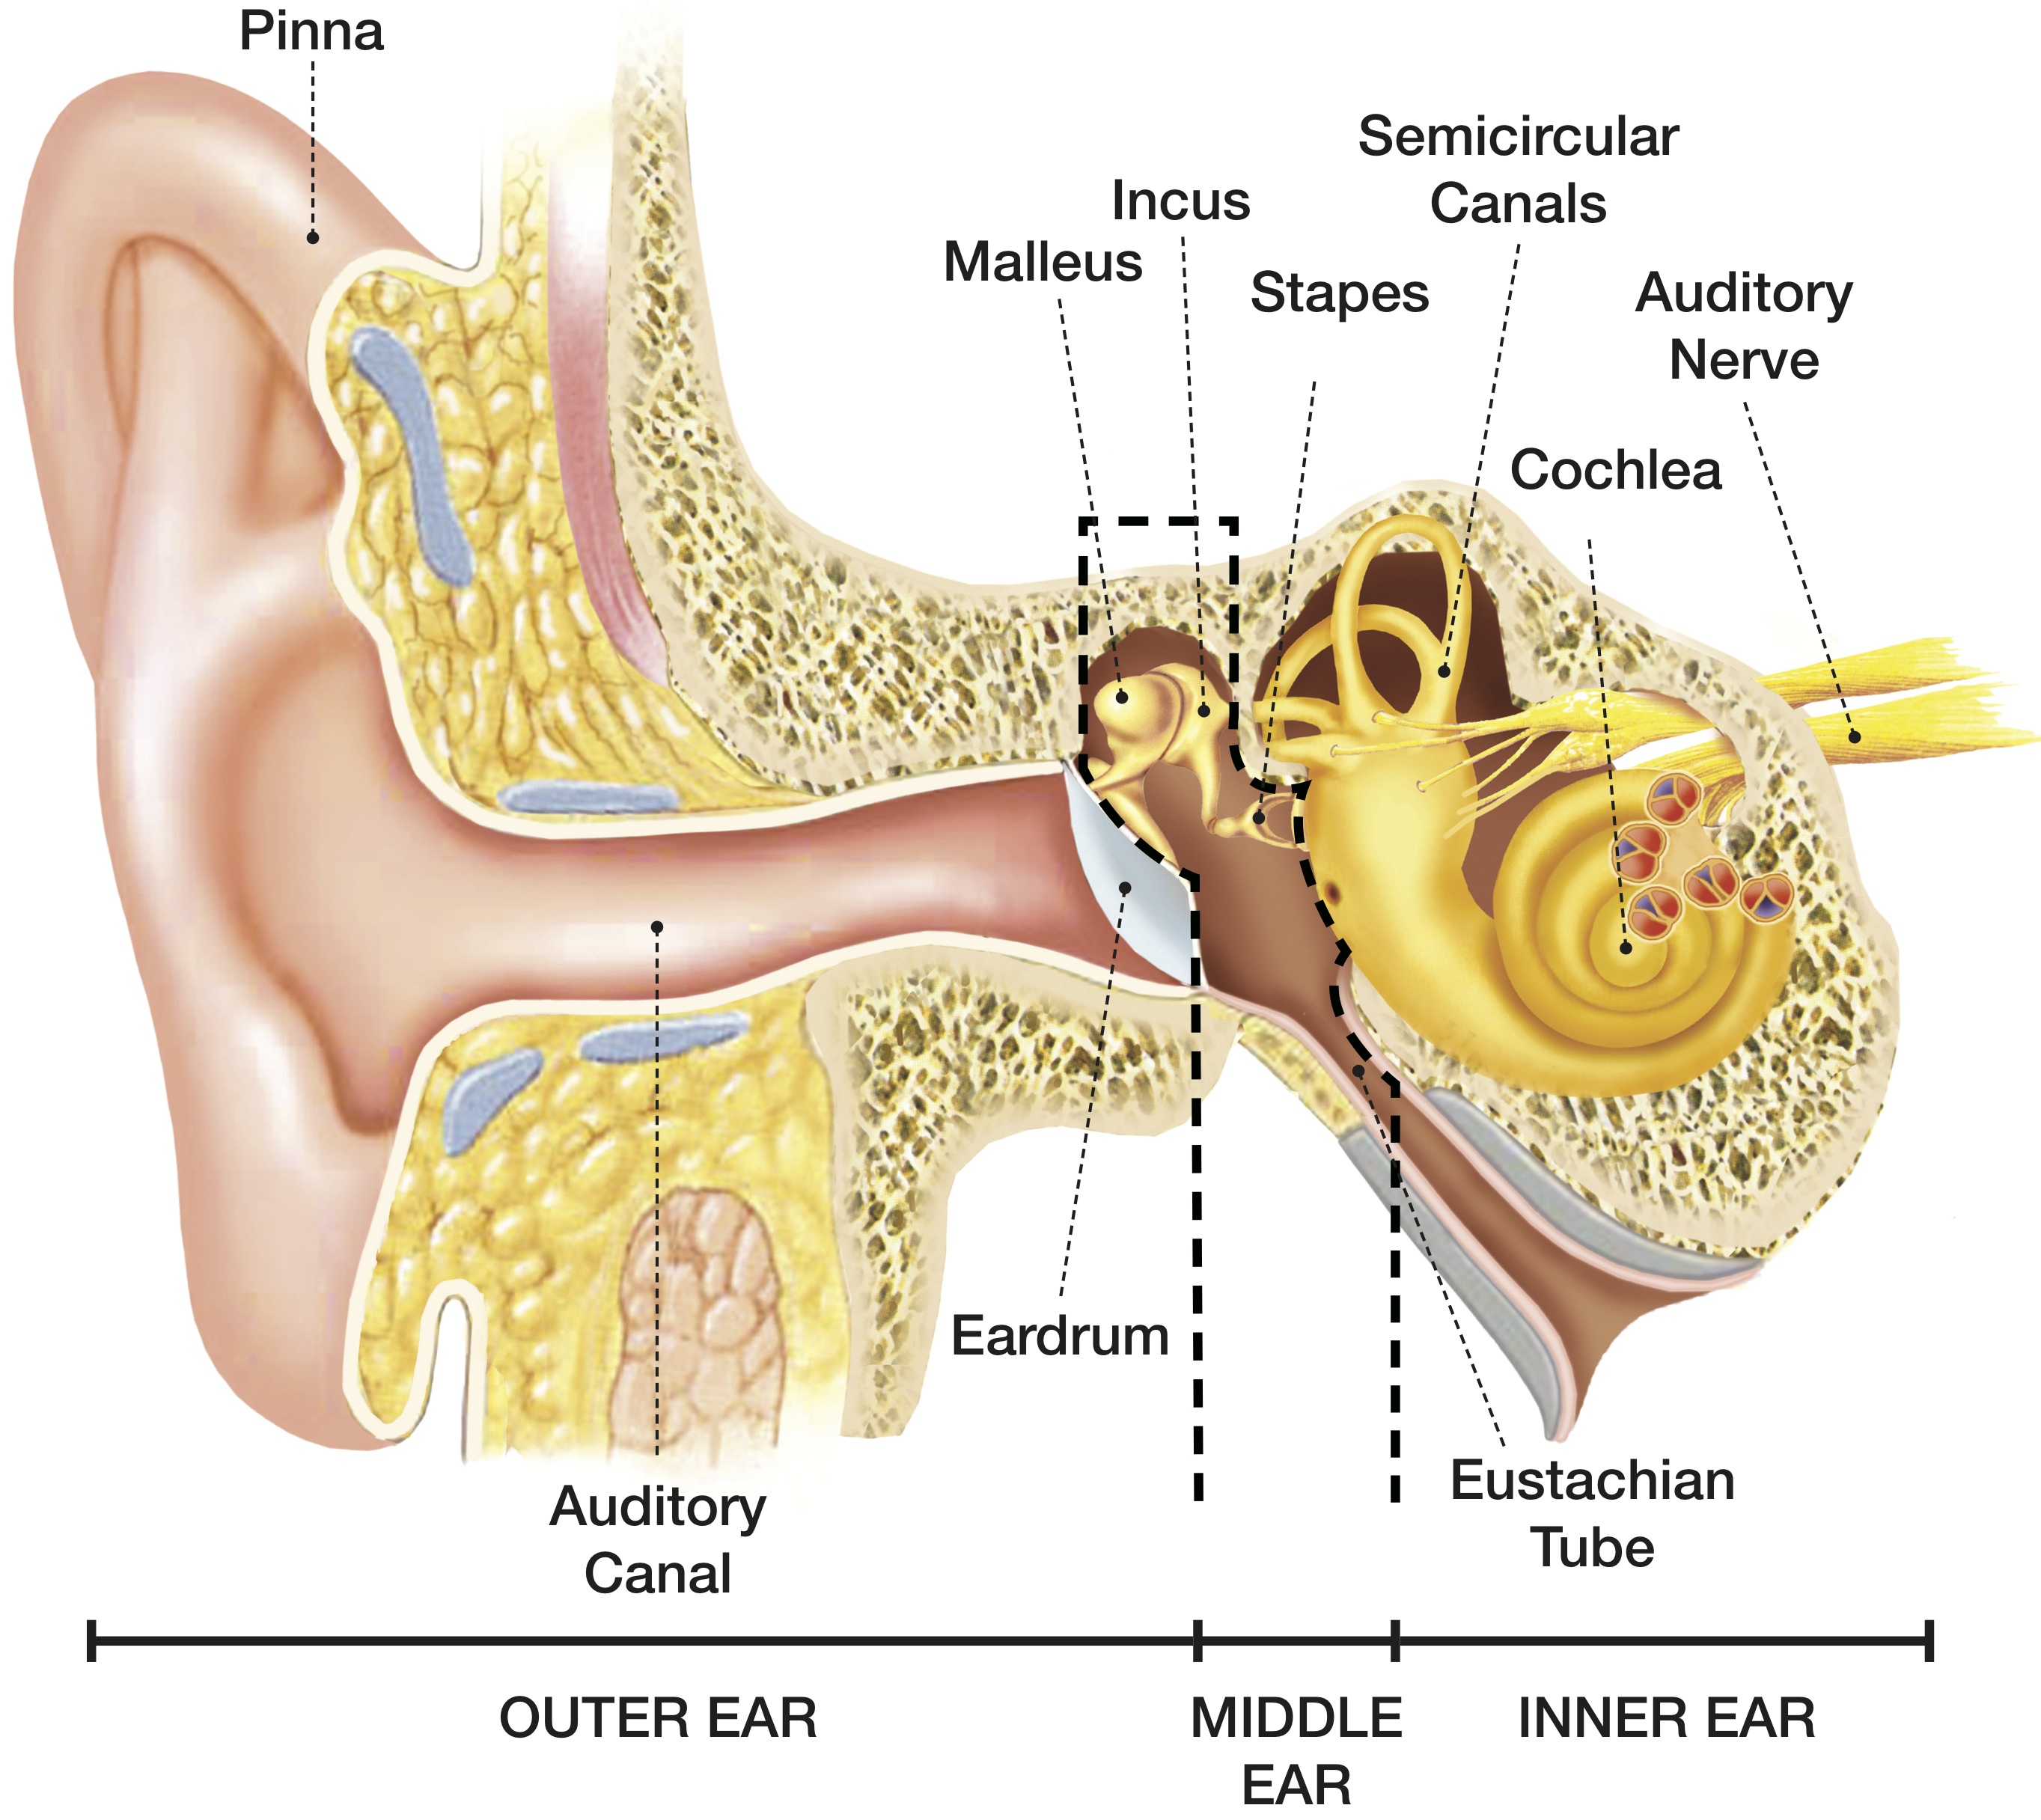
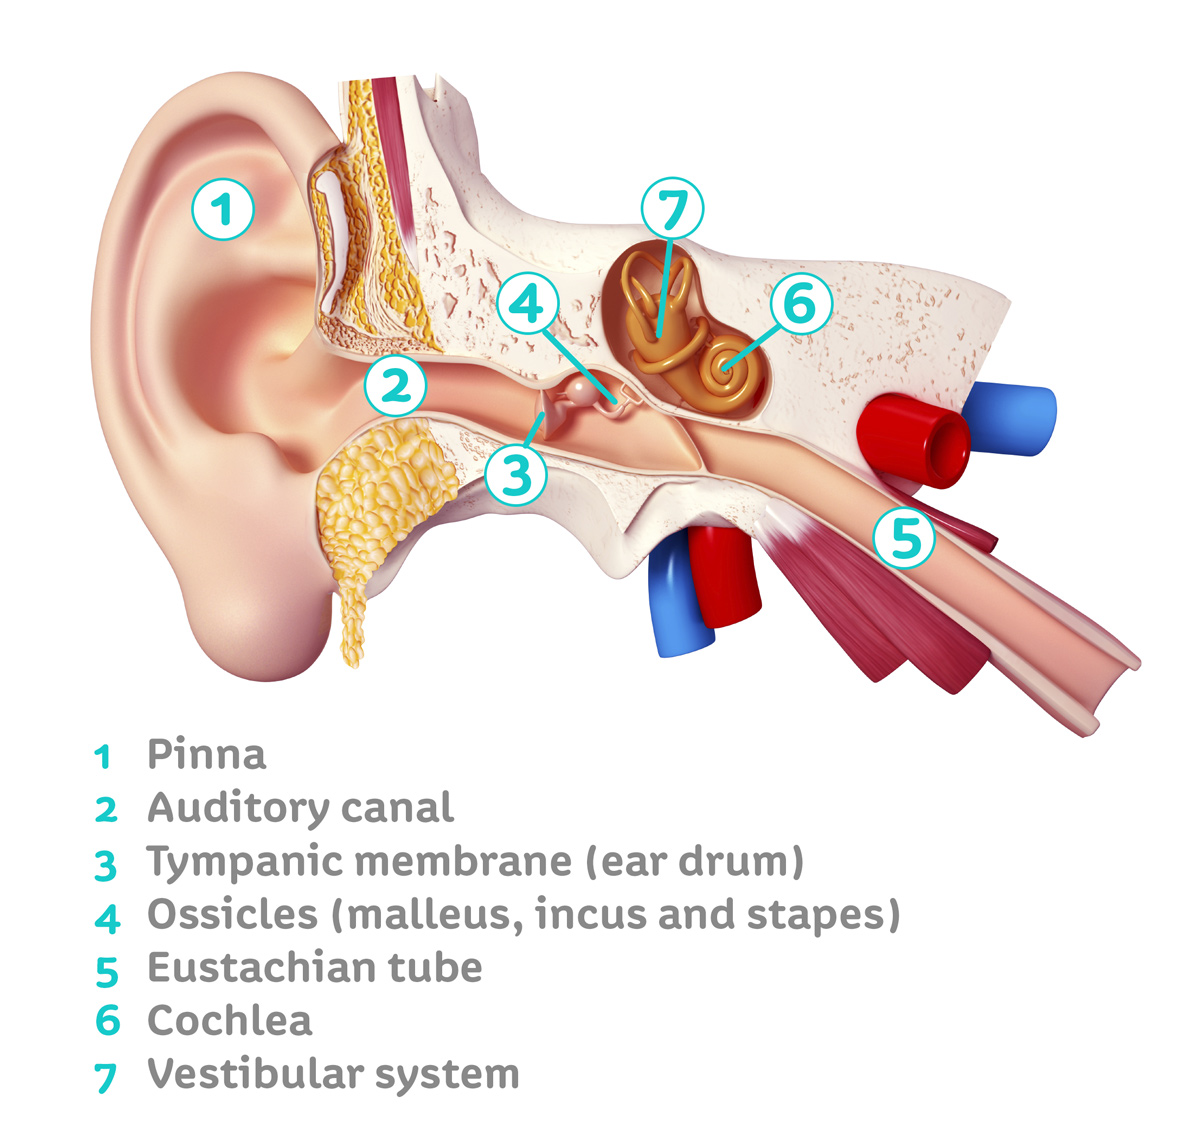
The inner ear sits deep inside the temporal bone, roughly the size of a snail shell, and it does two jobs simultaneously: translating sound into neural signals and measuring every micro-movement of your head in three dimensions. Most people think of it as a single organ. It is not. It is a cluster of specialized structures with separate functions, and confusing them is how you get the wrong diagnosis.Common Parts Of The Inner Ear And What They Actually Do
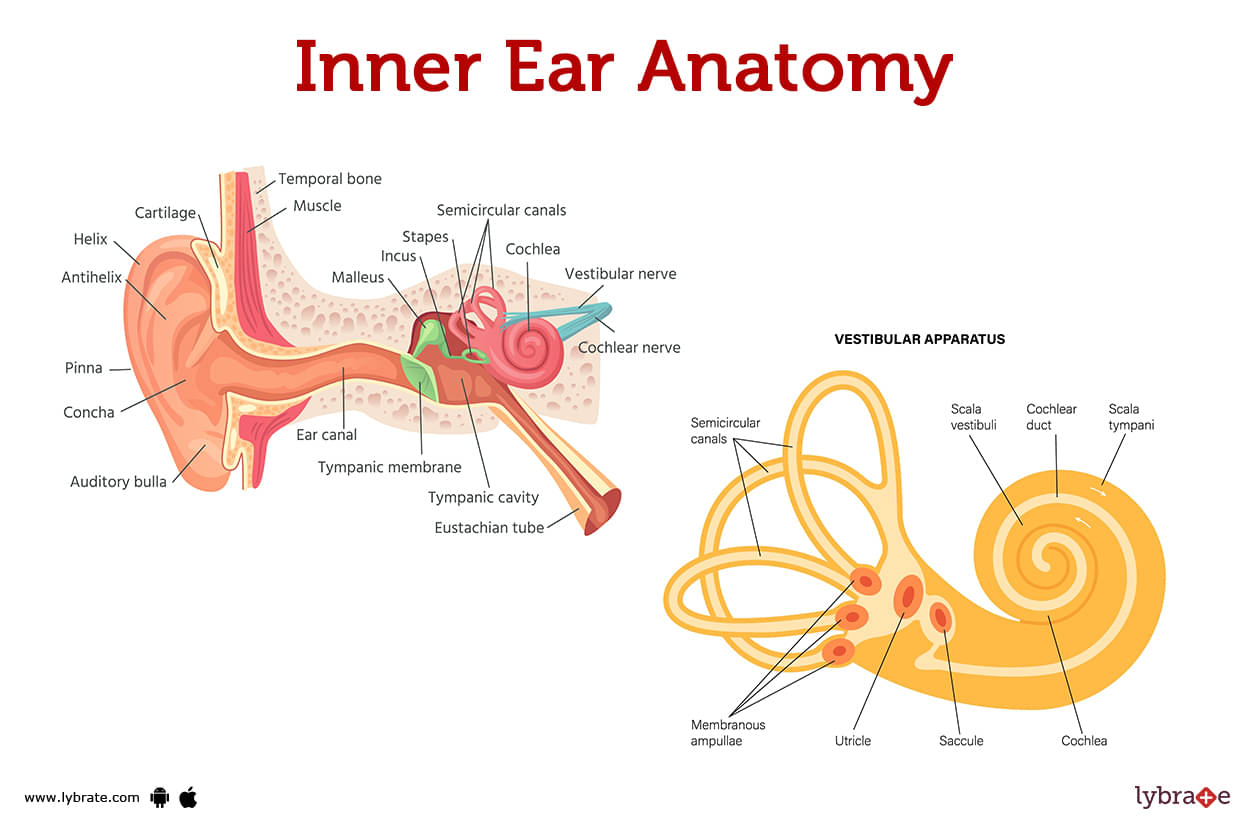
The cochlea is the spiral-shaped hearing organ. Inside it, the basilar membrane runs the length of the coiled tube, vibrating at different points depending on frequency. High frequencies peak near the base. Low frequencies travel all the way to the apex. Hair cells sit on top of that membrane, and when the membrane moves, their stereocilia bend. That bending opens ion channels, creates an electrical signal, and sends it down the auditory nerve. That is the entire mechanism for hearing. The vestibular system handles balance and spatial orientation. It consists of three semicircular canals oriented at roughly right angles to each other, plus two otolith organs called the utricle and the saccule. The canals detect rotational acceleration. When you turn your head, fluid inside the canals lags behind due to inertia, pushing against a structure called the cupula. Hair cells embedded in the cupula fire signals that tell your brain exactly which way and how fast you are rotating. The utricle and saccule detect linear acceleration and gravity. Tiny calcium carbonate crystals called otoconia sit on a gel layer above their hair cells. When you move forward in a car or tilt your head, those crystals shift and pull on the gel, bending the hair cells. The utricle responds primarily to horizontal movement. The saccule responds to vertical movement. Both feed into the same vestibular nerve that runs alongside the auditory nerve out of the inner ear.
The endolymph and perilymph are the two fluids that fill these spaces, and their composition matters more than most people realize. Endolymph, which bathes the sensory organs inside the cochlea and vestibular structures, is rich in potassium and has a positive electrical potential. Perilymph, which surrounds the membranous labyrinth, resembles extracellular fluid with high sodium and low potassium. The potassium gradient across the hair cell membranes is what drives the transduction process. Disrupt that gradient and hearing and balance fail together.
How The Components Work Together Under Stress
I once treated a patient who presented with episodic vertigo and roaring tinnitus. The initial diagnosis was benign paroxysmal positional vertigo, or BPPV, because the Dix-Hallpike test produced nystagmus. But the nystagmus had an atypical direction. Standard Epley maneuvers produced zero improvement over three attempts. That should have been the first red flag, but the vertigo and positional component made it easy to fall into a BPPV confirmation bias. What we found later was endolymphatic hydrops—excess fluid pressure in the inner ear spaces. The fluid buildup was distorting the basilar membrane and the vestibular sensors simultaneously, causing symptoms that mimicked BPPV almost perfectly. The workaround was a combination of dietary sodium restriction, a diuretic prescription, and repeat vestibular testing to rule out other causes before confirming the pressure changes through caloric testing and MRI. That case taught me to always check for low-frequency sensorineural hearing loss when treating presumed BPPV, because it shows up in about a third of Meniere's cases early in the disease course.
Get the Full Details

Counter-Intuitive Details Beginners Miss
One thing that trips people up is the relationship between the cochlear duct and the basilar membrane. The cochlear duct sits between the scala vestibuli and scala tympani, and the basilar membrane forms its floor. The organ of Corti sits on top of the basilar membrane. When sound waves enter through the oval window, they create a traveling wave along the basilar membrane. The peak of that wave depends entirely on frequency. A 4000 Hz tone peaks about 5 millimeters from the base. An 200 Hz tone reaches its maximum near the apex, roughly 30 millimeters in. This tonotopic organization is fixed and precise, and damage to a specific region produces a very specific hearing loss pattern on an audiogram. Another detail that is frequently misunderstood is the role of the efferent olivocochlear system. These are nerve fibers that travel from the brainstem back into the cochlea, targeting the outer hair cells. Their function is not to amplify sound but to dampen it. They reduce the gain of the cochlear amplifier, which protects the inner ear from acoustic trauma and improves signal detection in noisy environments. When this feedback loop is damaged, people often report difficulty understanding speech in background noise despite having normal pure-tone thresholds. That is a common clinical presentation that gets missed because standard hearing tests look fine.
Limitations And Failure Modes
The inner ear does not regenerate. Hair cells in mammals are terminal cells. Once they are damaged by loud noise, ototoxic medications, or aging, they do not grow back. This is not a theoretical limitation. It means that sensorineural hearing loss is permanent, and the only interventions are amplification through hearing aids or replacement through cochlear implants. There are ongoing gene therapy and stem cell research programs, but nothing clinically available yet. Vestibular compensation is another area where expectations often exceed reality. After acute vestibular loss from surgery, infection, or trauma, the brain can partially compensate through vestibular rehabilitation exercises. Most people regain enough function for daily activities within weeks to months. But fine-tuned balance on uneven surfaces, rapid head movements during sports, or performance in low-light conditions often remain impaired. The central nervous system adapts, but it cannot restore the peripheral input that is gone. There is also a diagnostic blind spot with superior canal dehiscence syndrome. A thinning or absence of bone over the superior semicircular canal creates a third mobile window in the inner ear. Sound and pressure transmit abnormally, causing autophonia, sound-induced vertigo, and conductive-looking hearing loss on audiometry even though the middle ear is intact. The threshold for suspecting this is low whenever a patient presents with what looks like conductive hearing loss but has a normal otoscopic exam. High-resolution temporal bone CT is the standard diagnostic tool, and it will show the dehiscence directly if you know where to look.
Practical Steps For Evaluating Inner Ear Function
Start with pure-tone audiometry to establish baseline hearing across frequencies. Then do tympanometry to rule out middle ear pathology. If the tympanogram is normal and hearing loss persists, move to vestibular testing. Videonystagmography, rotary chair testing, and VEMP (vestibular evoked myogenic potentials) provide complementary data. VEMP is particularly useful for isolating saccular and inferior vestibular nerve function, which standard caloric testing cannot assess. When interpreting results, always correlate the findings with the patient's symptom profile. An abnormal vestibular test in an asymptomatic patient may represent an incidental finding rather than a active disorder. A normal test in a patient with classic symptoms does not rule out inner ear pathology, especially in early-stage Meniere's disease where tests can be normal between attacks. Repeat testing over time is often necessary. The anatomy is straightforward in theory. The physiology becomes complicated the moment you try to apply it to real patients. The inner ear is small, enclosed in bone, and electrically active in ways that are difficult to measure non-invasively. Every diagnostic step requires understanding both the structure and the fluid dynamics that make it work. Skipping that step leads to misdiagnosis, wasted treatment time, and patients who leave worse off than when they arrived.