So You Need To Understand The Nervous System
Most people treat this like a middle school biology diagram and move on. That works fine until you actually need to explain why a patient can't feel their left pinky after a minor wrist injury, or why a drug that blocks peripheral receptors doesn't fix chronic migraine. The framework is simple on paper. The details bite you if you don't pay attention to them. I spent years sorting through neurology referrals where the root cause was missed because someone conflated central and peripheral presentations. One case that still sticks out involved a 34-year-old who kept coming in with tingling that started in both feet and slowly climbed upward. Every textbook pathway suggested Guillain-Barré. But when I actually traced the dermatomes and compared reflex patterns against the progression timeline, the answer wasn't in the CNS at all. It was vitamin B12 deficiency mimicking a spinal cord lesion. You don't catch that by memorizing parts. You catch it by understanding how each part behaves under stress.
Parts Of The Nervous System Breakdown
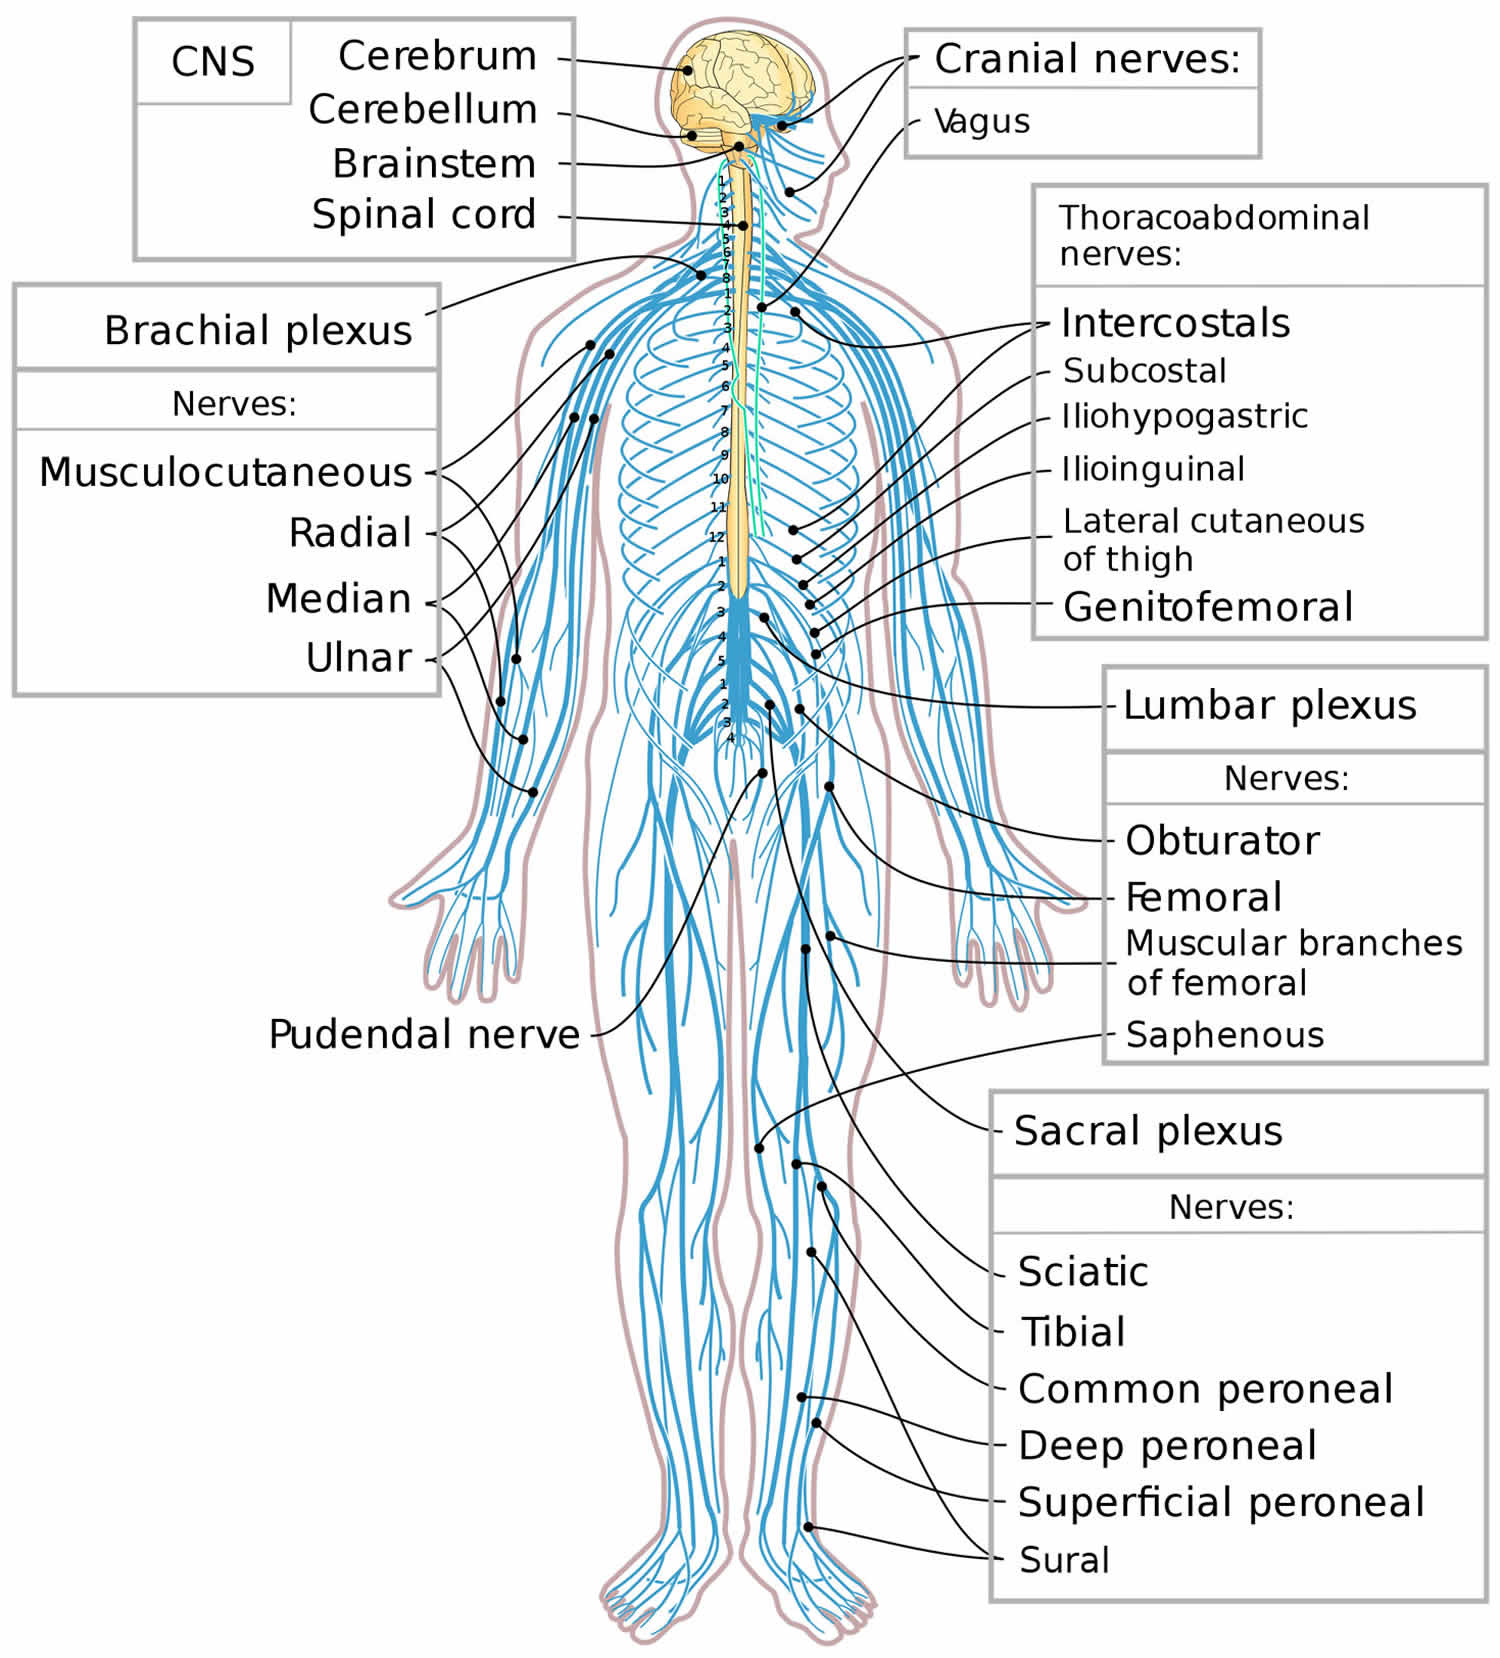
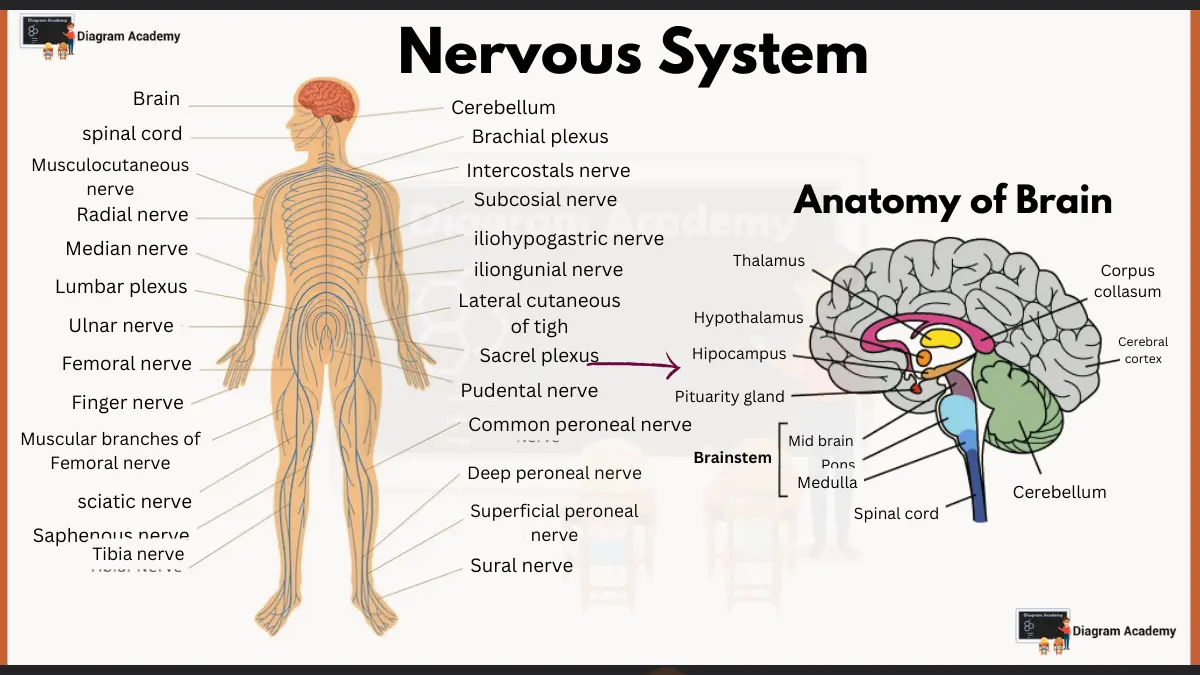
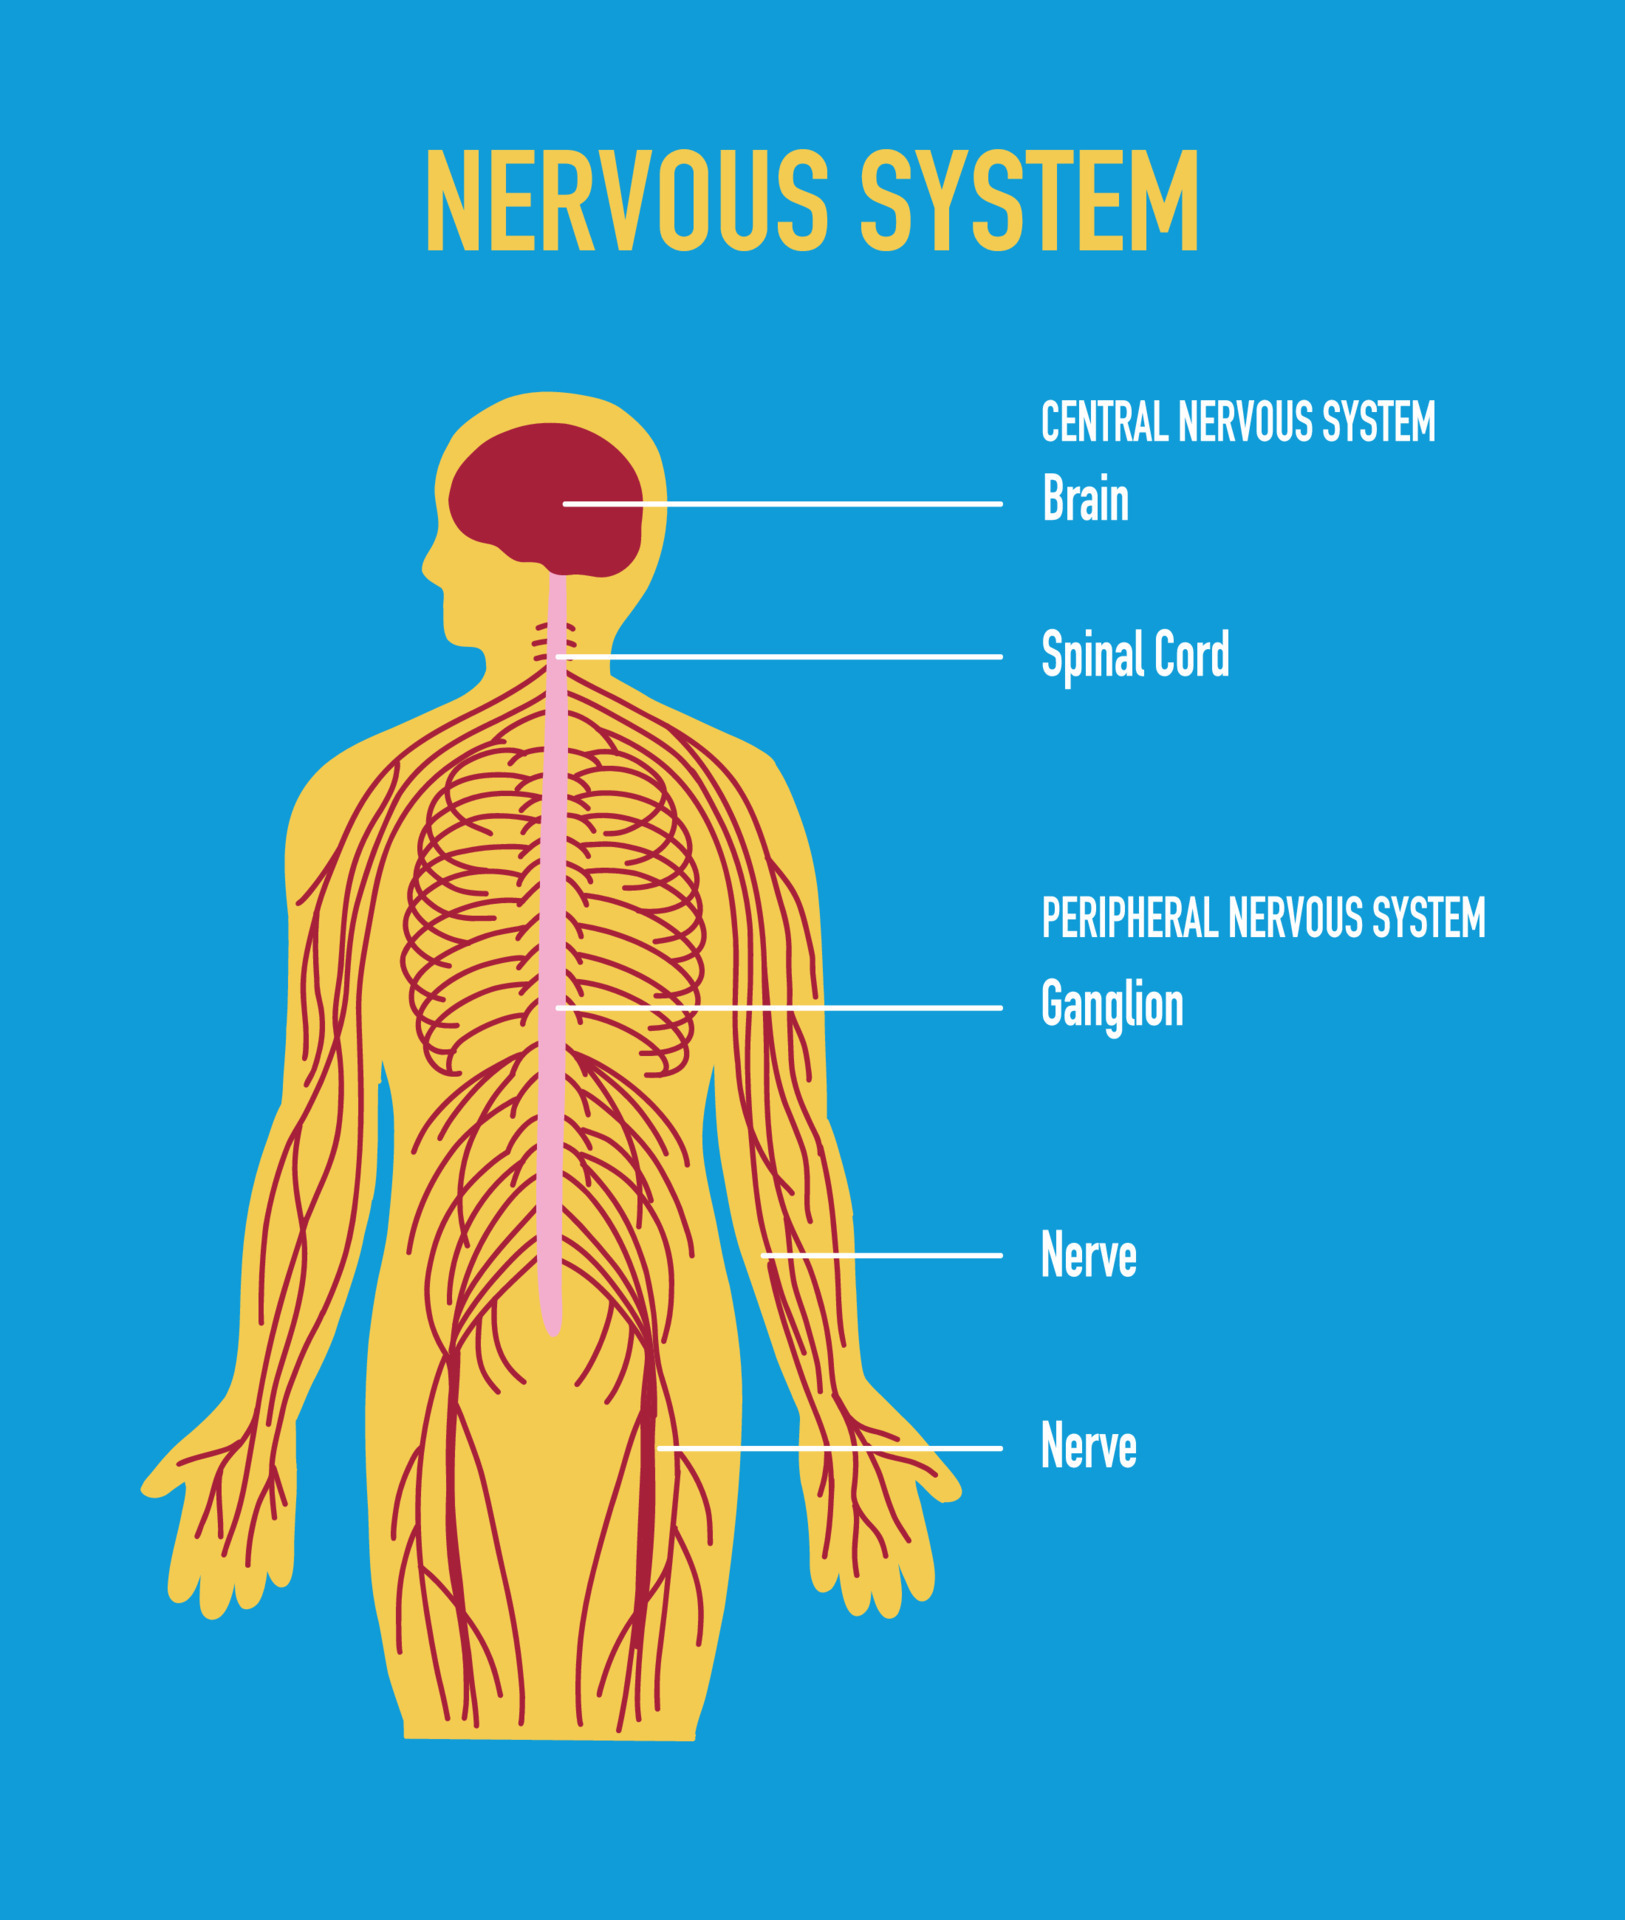
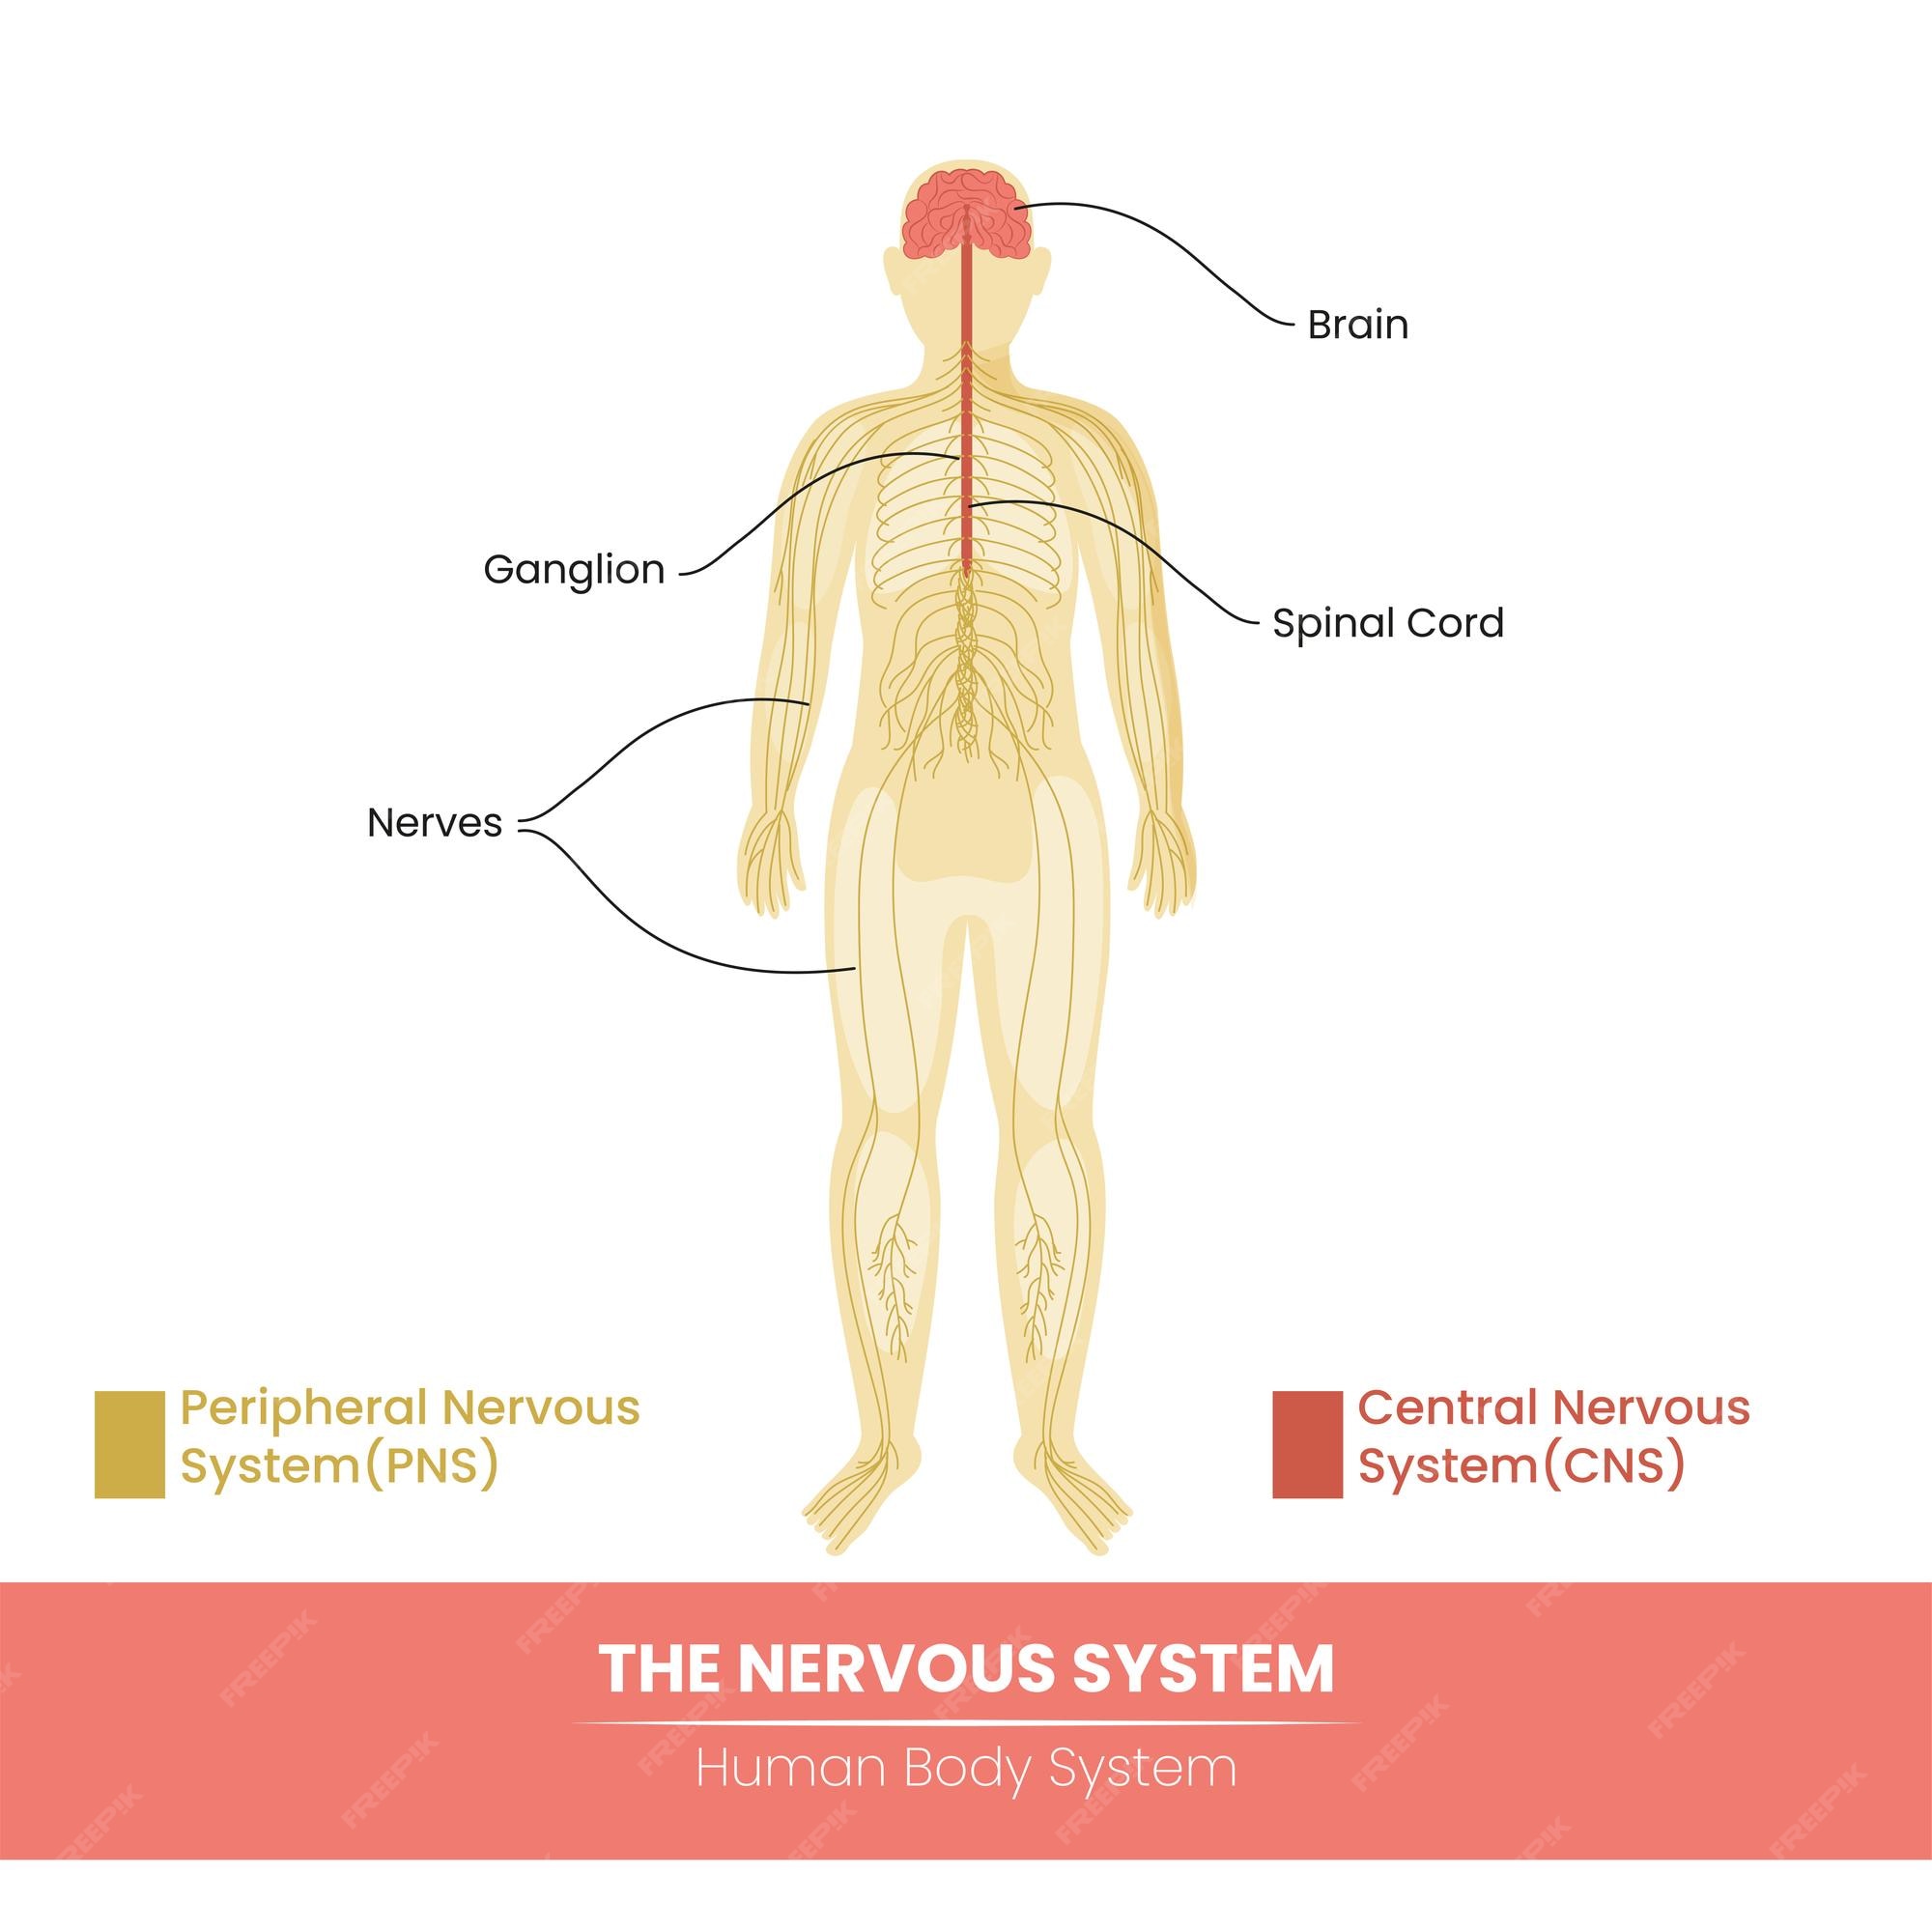
Let me just lay this out without decoration. The nervous system splits into two major anatomical divisions: the central nervous system and the peripheral nervous system. That is the broad stroke. Everything else flows from that split. Central Nervous System (CNS) The brain and the spinal cord. That is it anatomically. But functionally this is where integration happens. Sensory input arrives. It gets processed. Motor commands get issued. The CNS doesn't just relay information like a telephone switchboard. It makes decisions at every level. Reflex arcs in the spinal cord bypass the brain entirely. You pull your hand off a hot stove before your brain even registers heat. That is the CNS operating without central oversight, and it matters clinically because spinal cord injuries don't always mean total paralysis below the lesion. Some reflex pathways remain intact depending on where the damage sits.
Peripheral Nervous System (PNS) Everything outside the brain and spinal cord. Nerves, ganglia, sensory receptors. The PNS has two functional subdivisions that people routinely blur together. The somatic nervous system handles voluntary control of skeletal muscles and conveys sensory information from the skin, joints, and muscles to the CNS. The autonomic nervous system runs everything you don't consciously control: heart rate, digestion, respiratory rate, pupillary response, glandular secretion. The autonomic system then splits into the sympathetic division, the parasympathetic division, and increasingly recognized, the enteric nervous system. The enteric system alone contains roughly 500 million neurons. It can operate independently of the brain and spinal cord. It manages gastrointestinal motility, secretion, and blood flow on its own. Most general textbooks still relegate it to a footnote, which is a mistake if you are studying real clinical presentations.
Get the Full Details
How These Parts Actually Interact
Here is where people get tripped up. The divisions are not isolated boxes. They overlap constantly. A single stimulus triggers responses across multiple subsystems simultaneously. Consider blood pressure regulation. Baroreceptors in the carotid sinus and aortic arch detect a drop in pressure. Signals travel via the glossopharyngeal and vagus nerves to the medulla in the brainstem. The CNS processes this and sends efferent signals through the sympathetic nervous system to increase heart rate and constrict blood vessels. Simultaneously, the renin-angiotensin-aldosterone system kicks in over a longer timeframe. That is CNS, PNS somatic, PNS autonomic sympathetic, and endocrine all working as one loop. If you study each part separately without mapping the connections, you will miss how failures cascade. I once worked through a case of a patient with orthostatic hypotension where every individual component tested normal. Heart rate response was intact. Vascular constriction was adequate. Autonomic reflexes were preserved. The issue turned out to be impaired baroreceptor resetting due to prolonged bed rest. The parts worked. The integration between them was degraded.isolated testing missed it entirely. You have to look at the system, not just the components.
Common Pitfalls When Learning This Material
The biggest mistake I see students and clinicians make is treating the somatic and autonomic systems as completely separate. They are not. There is significant crossover. The dorsomedial hypothalamus projects to both somatic motor pathways and autonomic centers. Stress responses involve voluntary muscle tension and involuntary cardiovascular changes at the same time. When you are learning the Parts Of The Nervous System, do not draw hard lines between these categories. Another trap is assuming that all autonomic control is involuntary in the strict sense. You can learn to modulate heart rate through biofeedback. You can voluntarily influence gastric emptying to some degree through breathing patterns and stress management. The boundary between somatic and autonomic is functional, not absolute. The Enteric Nervous System example above illustrates this perfectly. It operates independently, but the brain and spinal cord regularly send modulatory signals that speed it up or slow it down. A third issue is the sympathetic versus parasympathetic oversimplification. Introductory courses teach that sympathetic is fight-or-flight and parasympathetic is rest-and-digest. That is roughly correct but dangerously incomplete. There are exceptions everywhere. The sympathetic system causes vasodilation in skeletal muscle during exercise. The parasympathetic system is active during sleep but also during digestion and sexual arousal. Some organs receive only sympathetic innervation. The adrenal medulla, most blood vessels, and the sweat glands are exclusively sympathetic. If you memorize the dichotomy without the exceptions, you will struggle with clinical scenarios.
What This Means In Practice
If you are studying for an exam, draw the system as a set of overlapping circles rather than a hierarchy. Map every organ to its innervation sources. Note which pathways are dual-innervated and which are single. Track the neurotransmitters at each synapse. Acetylcholine appears at all preganglionic synapses in both somatic and autonomic divisions, at parasympathetic postganglionic synapses, and at sympathetic postganglionic synapses to sweat glands. Norepinephrine dominates sympathetic postganglionic transmission except at those sweat glands. Knowing the neurotransmitter patterns tells you more about drug interactions than memorizing organ lists ever will. If you are dealing with patients, focus on the transitions between systems. Most neurological disorders present at the boundary. A stroke in the brainstem affects both cranial nerve nuclei and descending autonomic pathways. Multiple sclerosis disrupts both CNS white matter tracts and peripheral myelin in some variants. Diabetic neuropathy starts peripherally but eventually involves central processing of sensory input. The boundary is where the pathology shows up.
Where The Model Falls Short
The standard Parts Of The Nervous System framework has real limitations. It is built on anatomical boundaries that do not always reflect functional reality. The enteric nervous system being lumped under the autonomic nervous system is one example. The immune system's interaction with neural tissue, neuroimmunology, is barely acknowledged in most curricula despite being clinically significant. Neuroinflammation drives progression in conditions like Alzheimer's and Parkinson's, but the classic model gives you no tools to think about that. The peripheral nervous system classification also struggles with proprioception. The Golgi tendon organ and muscle spindle send continuous feedback to the cerebellum that shapes movement without conscious awareness. Is that somatic or autonomic? It sits in between. The model forces it into the somatic category, but functionally it operates more like an automatic regulatory loop. For advanced work, supplement the standard framework with a network-based approach. Map connections rather than compartments. The default mode network, salience network, and central executive network in the brain don't respect CNS versus PNS boundaries. They span both. If you want to understand how the nervous system actually works, the compartment model is a starting point, not a destination.