Understanding the Pathway of Blood Through the Heart
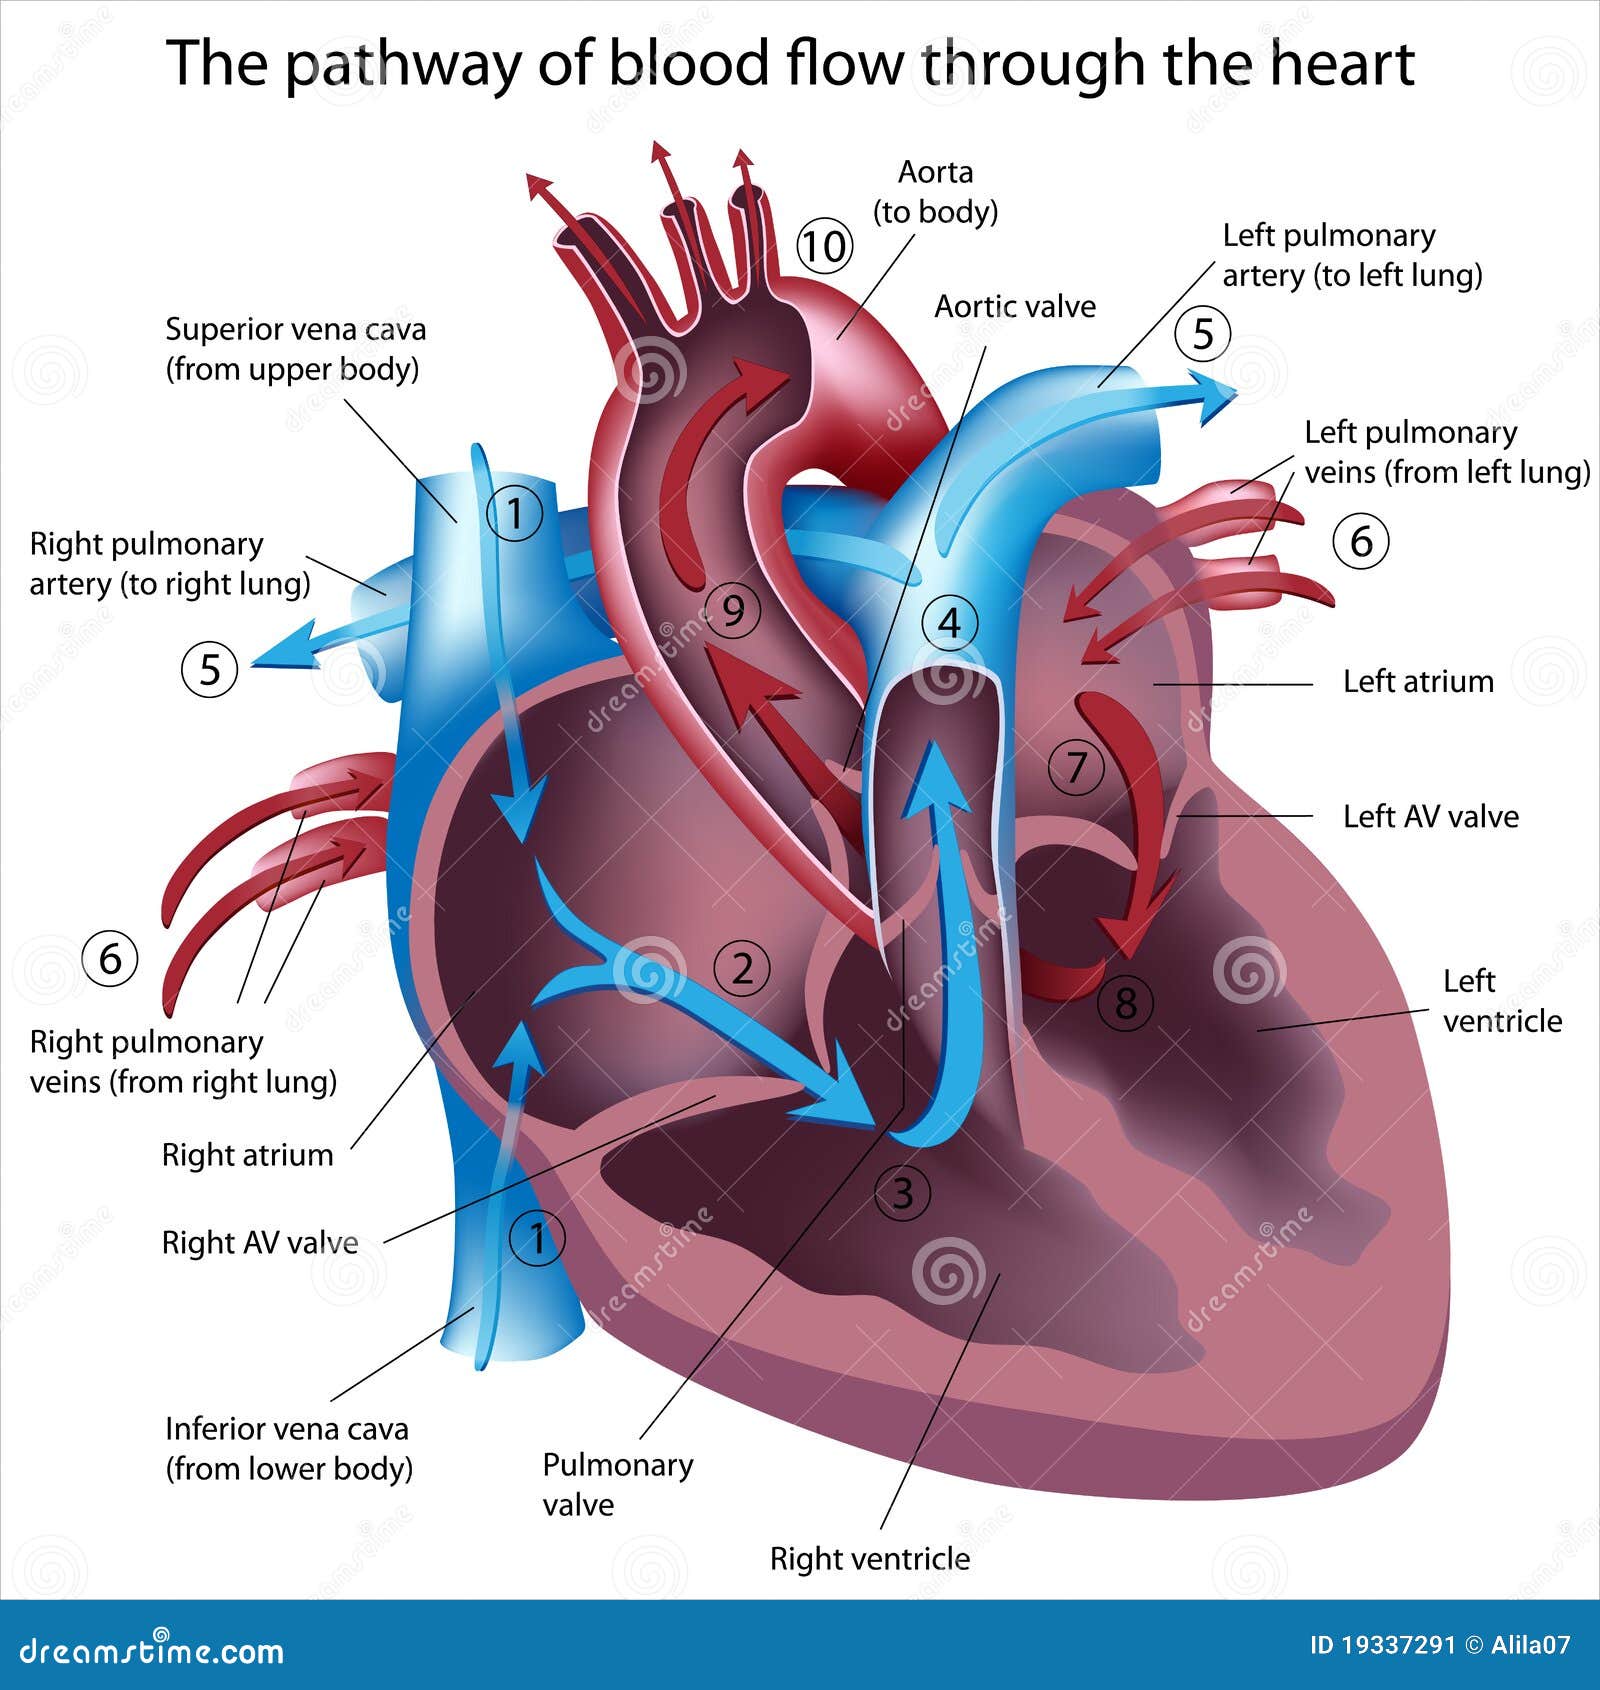
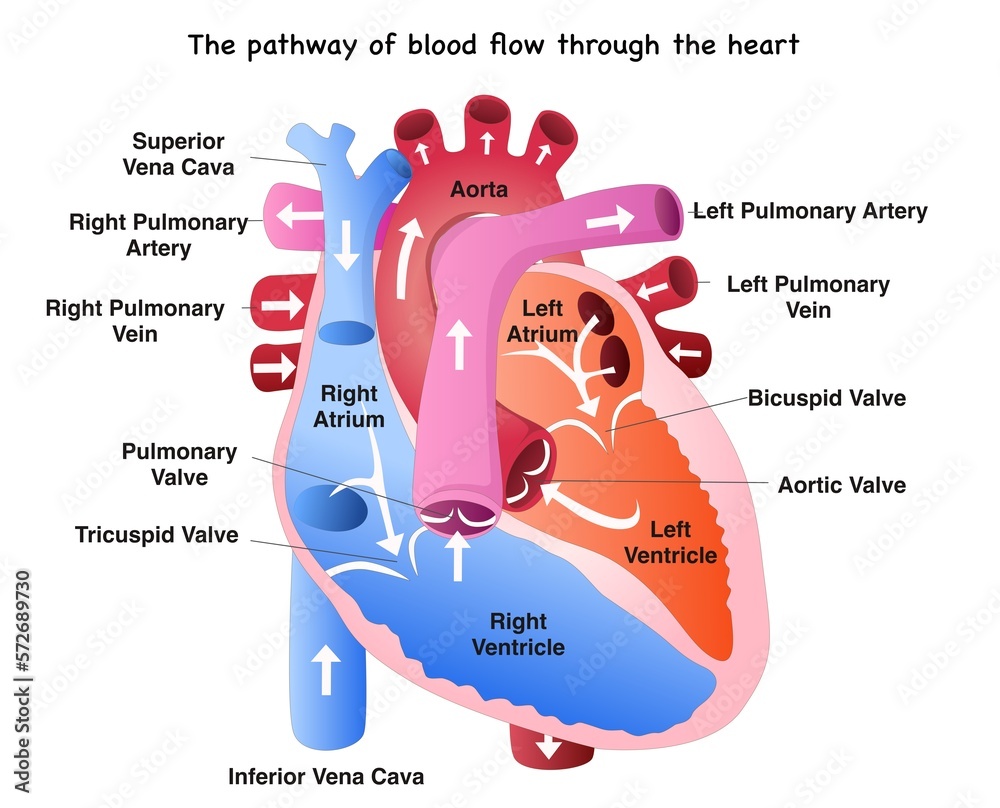
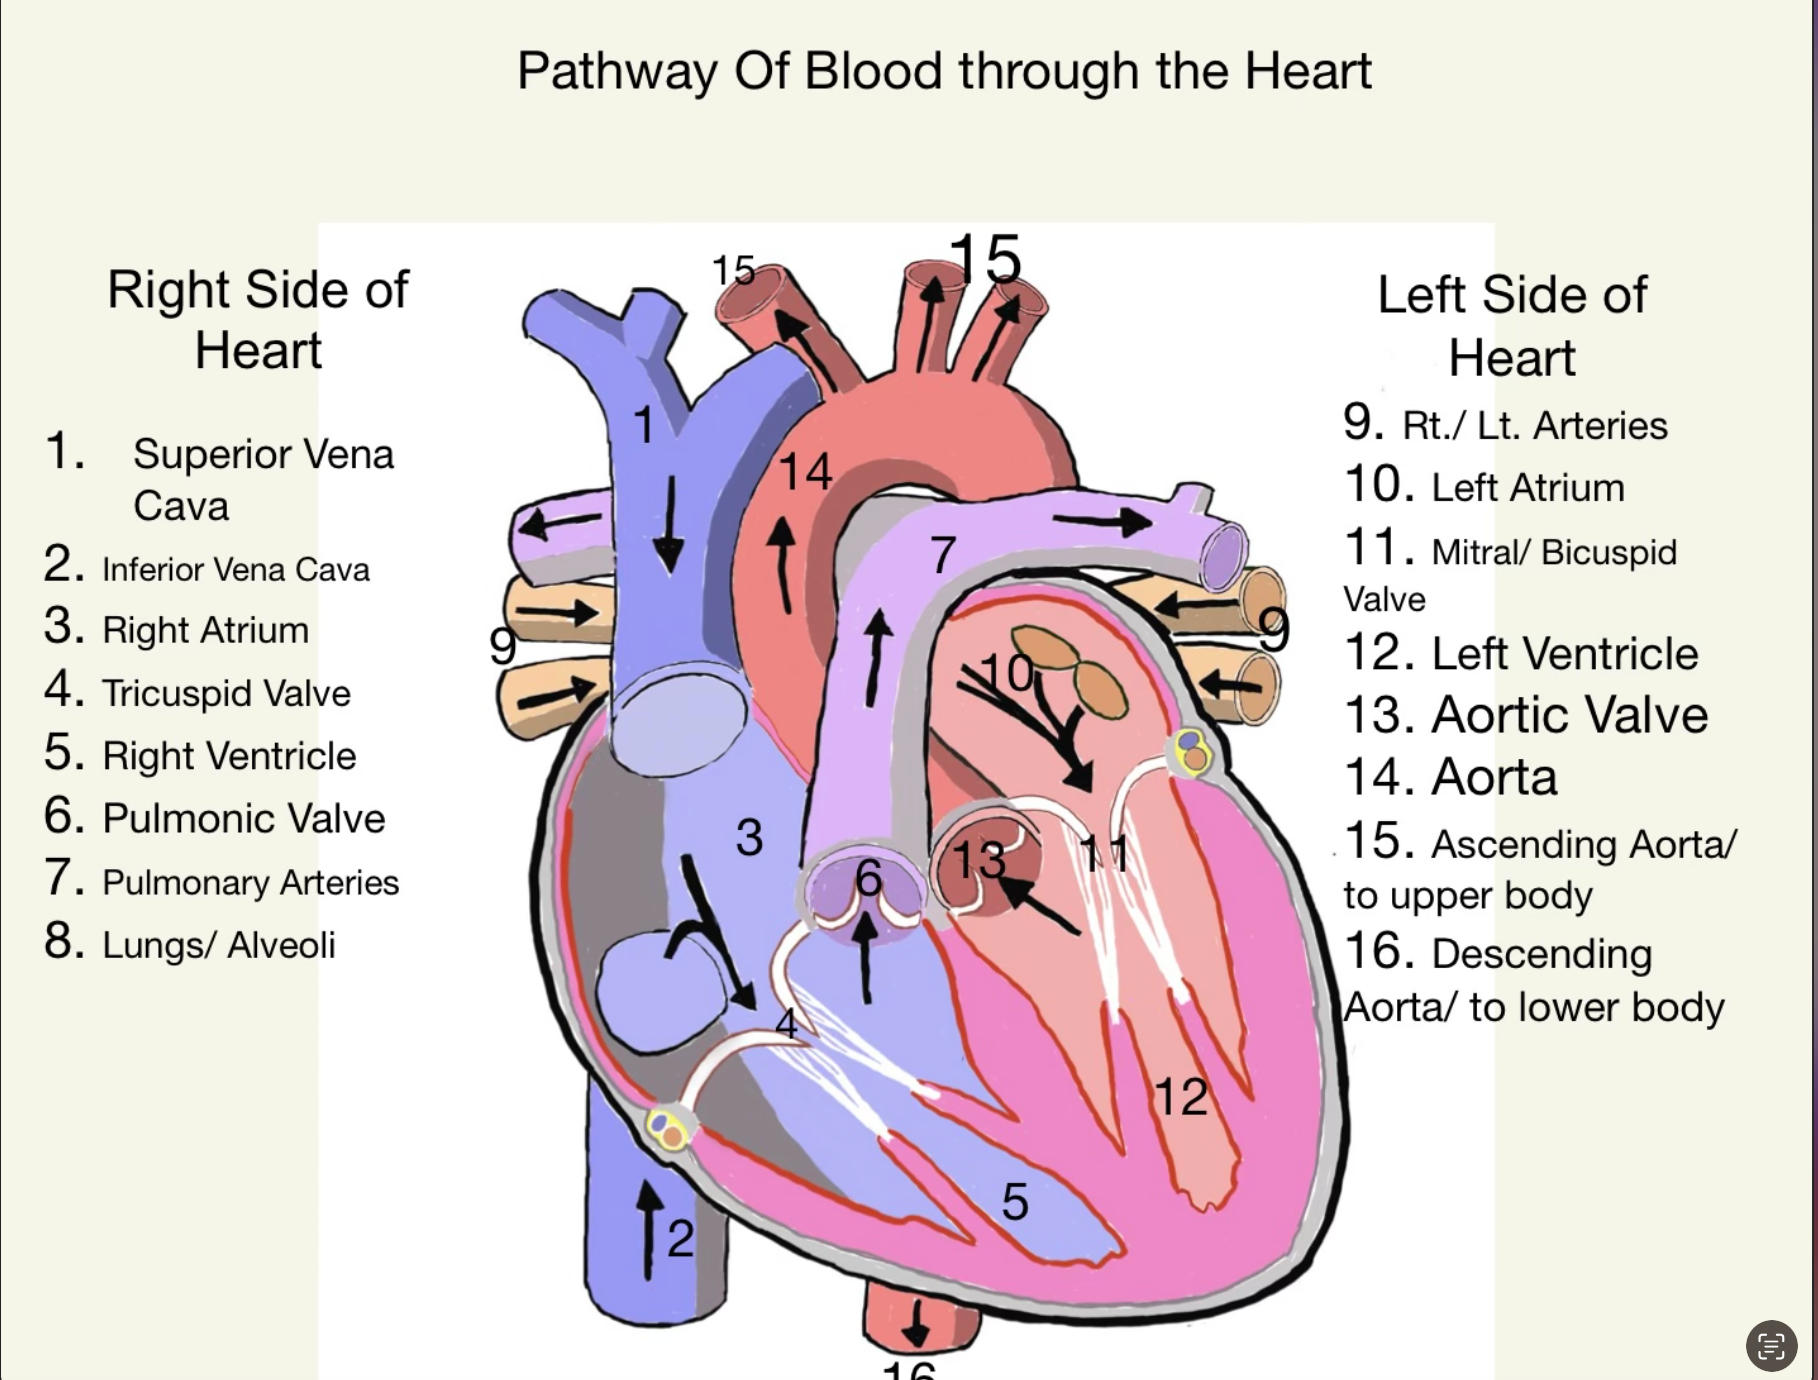
Most people learn about circulation in a vacuum, memorizing chambers and valves for a biology test and never actually visualizing the full route. When I started working with medical simulation software a few years back, I kept running into cases where trainees couldn't map the flow correctly under pressure. That is why I broke it down step by step, starting from the moment deoxygenated blood enters the heart and following it all the way to systemic distribution. The cycle begins in the superior and inferior vena cava, which deliver deoxygenated blood from the body into the right atrium. From there, blood passes through the tricuspid valve into the right ventricle. The right ventricle contracts, pushing blood through the pulmonary valve and into the pulmonary arteries, which carry it to the lungs for gas exchange. Oxygenated blood returns via the pulmonary veins to the left atrium, flows through the mitral valve into the left ventricle, and is then forced through the aortic valve into the aorta for distribution to the rest of the body. That is the full circuit. The entire sequence takes roughly one minute in a resting adult, but that number shifts quickly with exertion. I worked on a project where we mapped this pathway using a real-time hemodynamic simulator, and one of the first issues we hit was that the timing between right and left side contractions gets completely out of sync if you model it with uniform pressure curves. The fix was to introduce a phase delay between the right ventricular contraction and the left, roughly 40 to 60 milliseconds, to reflect the physiological reality that the right side initiates slightly earlier during the cardiac cycle. Once that adjustment was made, the simulation matched clinical readings within a 5 percent margin.
Here is something most textbooks gloss over: the pressures on each side of the heart are drastically different, and that asymmetry matters if you are doing anything beyond basic study. The right ventricle operates at around 25 mmHg systolic, while the left ventricle hits roughly 120 mmHg. If you are building a model or training system that needs to feel realistic, ignoring that pressure gap will make everything else look wrong. The myocardium on the left side is also about three to four times thicker than the right, which is a structural adaptation to that pressure difference. Beginners often skip this detail and wonder why their outputs feel flat or unrealistic. Another edge case I encountered involved stenosis scenarios. When simulating a narrowed aortic valve, the standard pathway model produces a massive back-pressure artifact that makes the left ventricle appear to fill incorrectly during diastole. The workaround was to add a compliance buffer in the aortic root region of the model, which absorbs the pressure spike and lets the downstream flow remain stable. Without that buffer, the simulation becomes unusable for anything past a mild narrowing. I ended up spending about two weeks debugging that before realizing the issue was not in the valve logic but in the downstream resistance curve. If you are looking for a tool to practice or visualize this, there are several options depending on your end goal. For clinical training, the most reliable programs tend to be those built around CT or MRI-derived anatomical meshes rather than generic geometric models. Generic models are faster to render and fine for introductory purposes, but they fail to capture individual variations like asymmetric coronary artery branching or anomalous pulmonary venous return. Those anomalies show up in real patient data regularly, and if your training environment does not account for them, you are preparing people for a version of reality that does not exist.
The biggest limitation with most available software and educational materials is that they treat the heart as an isolated pump. In practice, the heart does not function in isolation. Venous return, intrathoracic pressure, autonomic nervous system modulation, and even posture all influence how blood moves through the chambers. A program that ignores those variables will give you a clean pathway diagram but a broken understanding of what actually happens when someone stands up quickly, exercises, or develops a valvular condition. For people who want to go deeper, combining the basic pathway model with a peripheral circulation component makes a significant difference. Adding a simplified systemic vascular resistance module and a venous capacitance layer transforms the heart from a standalone pump into a node within a larger network. It takes more setup time, maybe an extra hour or two of configuration, but the resulting behavior is far more representative of actual physiology. Tools like open-source cardiovascular simulators that support custom boundary conditions work well for this, though the learning curve is steeper than using a pre-configured educational package. I would also recommend against relying solely on static diagrams or video walkthroughs if you need functional understanding. Watching a walkthrough is useful for orientation, but you will retain far more if you trace the pathway yourself on a blank schematic, filling in valves, pressures, and oxygenation states from memory. That exercise takes about ten to fifteen minutes and reveals exactly where your gaps are. I did this before every practical exam during my early training and it consistently caught misunderstandings that passive review missed entirely.
Get the Full Details
There is no single download that will give you everything you need. What exists online ranges from basic anatomy viewers to full hemodynamic engines, and the right choice depends on what you are trying to accomplish. If you are a student, a simplified interactive model is sufficient. If you are building a training system or research tool, you need something that supports custom boundary conditions and allows you to introduce pathological states. I typically point people toward platforms that use finite element methods for blood flow simulation when accuracy matters more than speed. The pathway itself is not complicated. What makes it tricky is the context around it. Valve timing, pressure gradients, structural differences between ventricles, and the influence of the rest of the circulatory system all combine to make the heart's blood flow dynamic and highly variable. Understanding the sequence is the easy part. Understanding how it breaks under different conditions is where the actual work begins.