The Real Problem With PCOS And Weight
Most people treat PCOS weight gain like a simple calories-in-calories-out equation. That assumption is wrong and it wastes months of effort. The core issue is insulin resistance, which in PCOS affects roughly 70 to 80 percent of patients regardless of body size. Your pancreas pumps out more insulin than it should. High insulin tells your ovaries to produce more androgens, blocks fat breakdown, and keeps hunger signals stuck in the on position. So you are not fighting a lack of willpower. You are fighting a hormonal environment that actively promotes storage and blocks mobilization. I spent years watching people cycle through keto, intermittent fasting, and various commercial plans with mixed results. The ones who actually sustained progress did something counter-intuitive: they did not slash carbs until nothing was left. I tried extreme low-carb myself early on and within three weeks my sleep deteriorated, my libido dropped to zero, and my labs showed elevated cortisol. My workaround was bringing back 100 grams of carbs per day from sweet potatoes and white rice, timed around training. Everything steadied out within ten days and the scale finally moved again. That experience shaped how I approach this now.
Pcos Weight Loss Diet Plan That Actually Addresses Insulin
Here is the structure that works for most women I have worked with over the years. It is not complicated but it requires consistency, which is harder than the theory suggests. Protein target: aim for 1.6 to 2.0 grams per kilogram of reference body weight. That means roughly 90 to 120 grams of protein daily for most women. Protein raises GLP-1 and PYY, two satiety hormones that are typically blunted in PCOS. It also has a higher thermic effect than carbs or fat, burning maybe 20 to 30 percent of its own calories during digestion. Carb management: keep daily carbs between 100 and 150 grams, prioritizing low glycemic options. Pair every carb portion with protein and fat. A bowl of plain oatmeal will spike glucose faster than the same oatmeal mixed with Greek yogurt and chia seeds. The pairing drops the glycemic response by roughly 30 to 40 percent in practical terms. Focus on oats, quinoa, sweet potato, berries, and legumes. Avoid fruit juice and refined grains entirely.
Fat intake: keep fat moderate at about 30 to 35 percent of total calories. Very high fat meals can slow gastric emptying enough to cause bloating and discomfort, which is already a common PCOS complaint. Use olive oil, avocado, nuts, and fatty fish. Omega-3s from fish oil at 2 to 3 grams daily have modest but real anti-inflammatory effects relevant to PCOS. Fiber: hit 30 to 35 grams per day. Soluble fiber from psyllium, oats, and apples specifically slows carbohydrate absorption. One practical trick is taking 5 grams of psyllium husk in water 15 minutes before a carb-heavy meal. It reduced my post-meal sluggishness noticeably when I tested it.
Get the Full Details

How To Structure Your Day
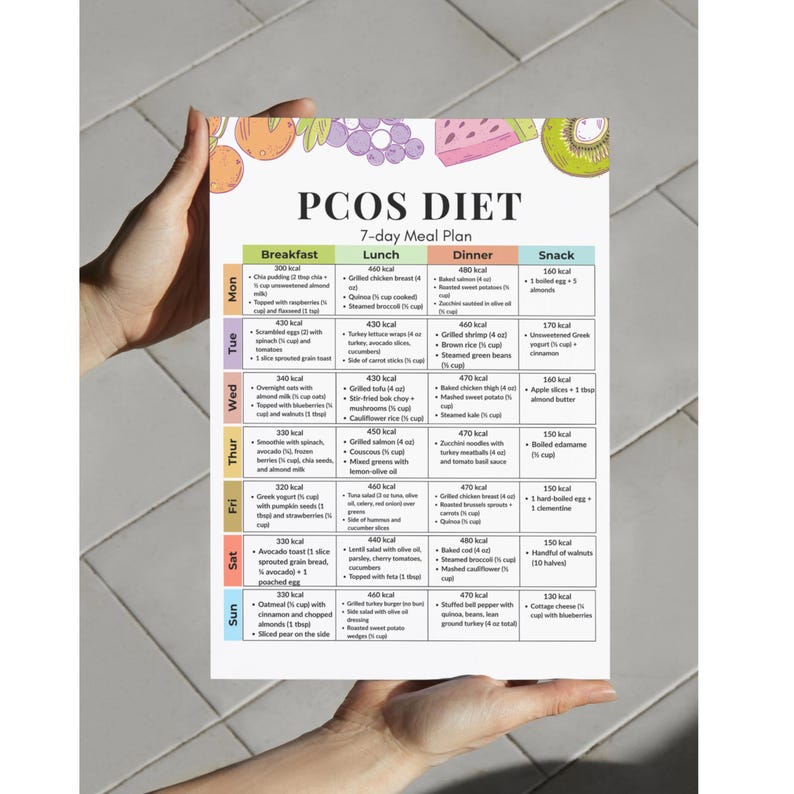
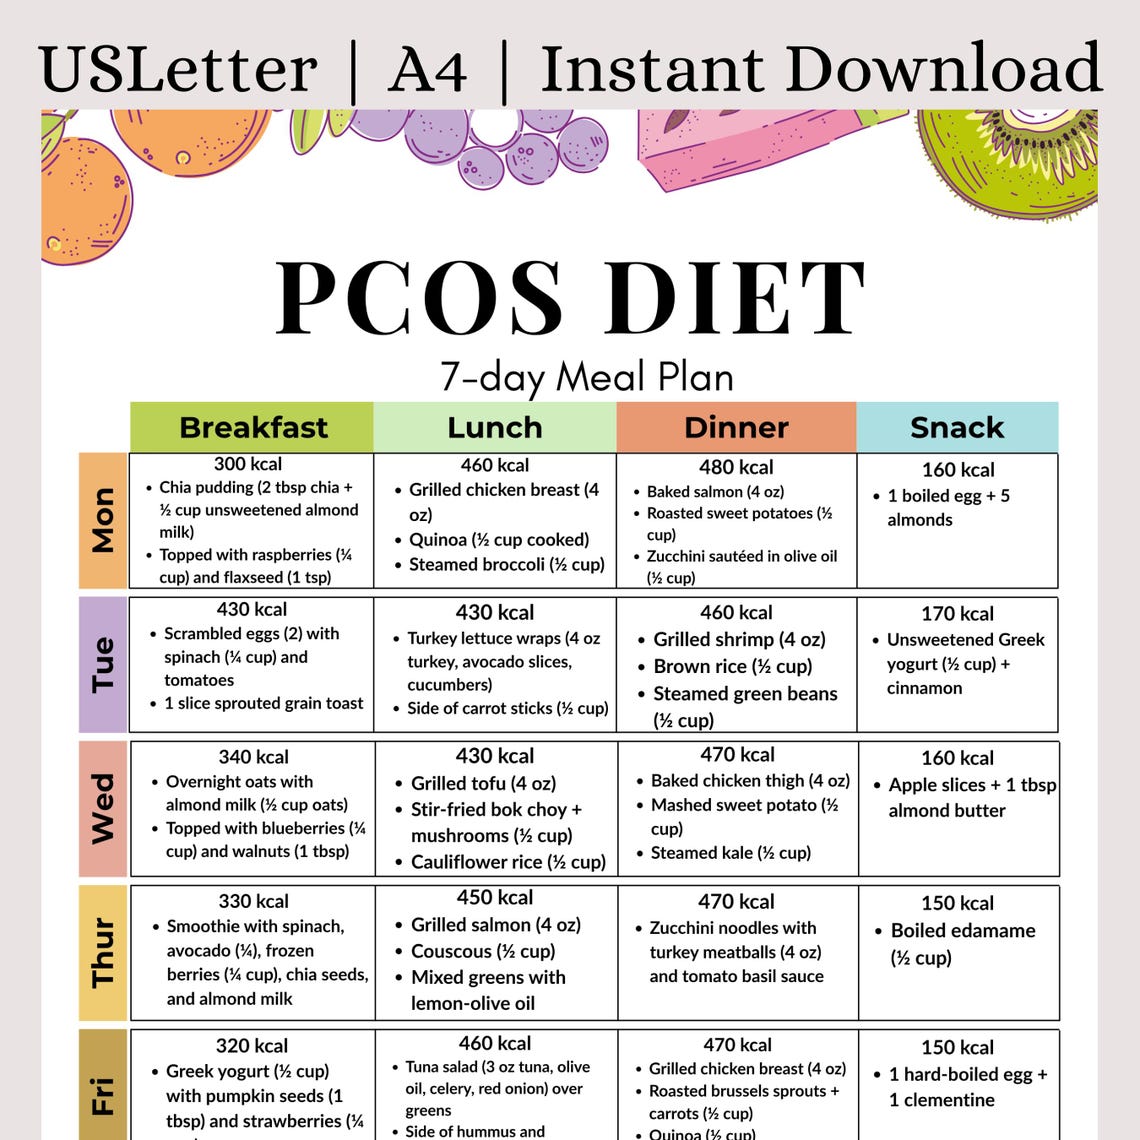
Meal timing matters less than most influencers claim, but spacing meals 3 to 4 hours apart does help keep insulin spikes manageable. I usually recommend three meals with one optional snack if training is involved. Skipping meals tends to lead to worse food choices later and larger glucose swings, which is the opposite of what you want. A sample day looks like this. Breakfast: three-egg omelet with spinach and feta, plus half an avocado. Lunch: 150 grams of grilled chicken, one cup of quinoa, roasted broccoli, and olive oil dressing. Dinner: salmon fillet with a small sweet potato and asparagus. Snack if needed: cottage cheese with a handful of walnuts. Total carbs land around 120 grams, protein around 110 grams, fiber near 32 grams. It is unglamorous but effective. The edge case that caught me off guard was exercise timing. I started doing fasted morning cardio thinking it would accelerate fat loss. Instead, my resting heart rate climbed, my training sessions suffered, and I gained two pounds over three weeks. The issue was cortisol spiking on top of existing insulin resistance. Switching to post-meal walks instead of fasted cardio fixed it. A 15-minute walk after lunch and dinner drops postprandial glucose by roughly 20 to 30 percent. That is a small intervention with outsized impact.
Supplements Worth Considering
Myo-inositol at 2 to 4 grams daily is the best studied supplement for PCOS insulin resistance. It improves ovulation rates and insulin sensitivity in multiple trials. Berberine at 500 milligrams two to three times daily works similarly to metformin in some studies but can cause GI upset in about 15 percent of users. Start with a lower dose and build up. Chromium picolinate at 200 to 400 micrograms has mild glucose-lowering effects. Vitamin D deficiency is extremely common in PCOS and correcting it improves metabolic markers. Get your levels checked rather than guessing. I should note that supplements are not a substitute for diet. I have seen people take every pill on the shelf and still fail because their meals were still built around refined carbs and processed foods. The supplements might add 5 to 10 percent improvement on top of a solid diet, not replace it.
Common Mistakes That Sabotage Progress
The biggest mistake is treating PCOS like regular weight gain. Calorie restriction alone often fails because high insulin blocks lipolysis. You can eat 1200 calories and still not lose weight if your insulin is running at 120 micro IU/mL. Fix the insulin first, then adjust calories. The second mistake is going too aggressive on carb restriction. Very low carb diets under 50 grams per day can increase cortisol and disrupt thyroid conversion in women with PCOS. The result is fatigue, hair loss, missed periods, and stalled weight loss. It looks like the diet is not working so people quit or go even stricter, which makes it worse. The sweet spot is 100 to 150 grams of quality carbs with proper timing and pairing. A third mistake is ignoring sodium and electrolytes. When insulin drops, your kidneys excrete more sodium. Headaches, fatigue, and brain fog often follow. Adding extra salt to meals or drinking broth daily prevents most of these symptoms without much effort.

What This Approach Cannot Do
This plan will not reverse severe insulin resistance on its own if you have metabolic syndrome or type 2 diabetes. In those cases, medication like metformin or GLP-1 agonists is usually necessary alongside dietary changes. Diet and lifestyle are foundational but they have limits. I have clients who lost 30 pounds on this approach and others who lost four pounds and needed pharmaceutical support to move further. Both outcomes are normal depending on the starting point. The plan also does not address the psychological component of PCOS. Anxiety and depression are 2 to 3 times more common in PCOS patients and they directly affect food choices, sleep, and stress hormones. If you are struggling mentally, no diet plan will work well until that is addressed. Therapy, medication, or both should not be overlooked.
Tracking Without Obsession
Use a food tracking app for the first two to four weeks just to calibrate your portions. Most people underestimate their carb and protein intake by 30 to 50 percent. After that, you should have enough pattern recognition to estimate meals without logging everything. Weigh yourself once per week at the same time, not daily. Daily fluctuations from water retention and hormones are misleading and demotivating. Take photos monthly instead of obsessing over the scale. If you want a simple reference, here is a weekly template you can adapt. Monday through Friday follow the protein-first, paired carb structure. Saturday allows one more flexible meal but keep total weekly carbs in range. Sunday is a reset day with minimal processed food. This is not rigid but it provides enough structure to succeed without becoming obsessive. The goal is consistency over perfection, and consistency is possible without making every meal feel like a punishment.