What the Peabody Fine Motor Assessment Actually Tests
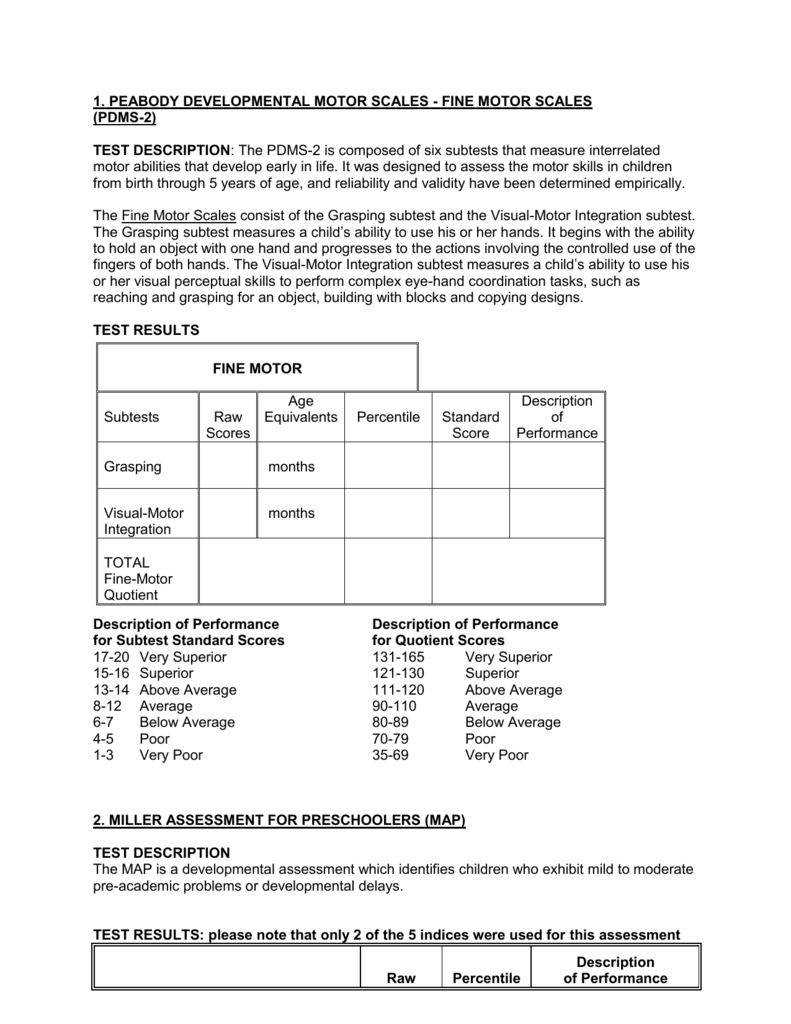
The Peabody Developmental Motor Scales—specifically the Fine Motor subscale—measures how children coordinate small muscle movements in their hands and fingers. It is not a comprehensive intelligence test or a behavioral screening. It is a standardized, norm-referenced instrument that captures where a child sits relative to peers. If you are looking for a quick developmental snapshot, this is the right tool. If you need something to diagnose a specific neurological condition, you will need to supplement it. When I ran my first battery, I expected everything to fall neatly into percentiles and standard scores. The reality was messier. A child might score below the 10th percentile on pencil grip but above the 50th on buttoning. The subscale breakdowns exist for exactly that reason: they isolate fine motor from gross motor so you can see where the gap actually lives. A composite score sounds authoritative, but it often smooths over the very inconsistency that matters most for intervention planning. I have seen occupational therapists lean too hard on a single standard score. One kid scored a 42 on fine motor and every evaluator assumed severe delay. What actually happened was he had early childhood cerebral palsy affecting his right side more than his left. When we administered the Peabody Fine Motor Assessment item by item and tracked which hand was used, the asymmetry told a completely different story than the composite number. The takeaway is straightforward: never trust the aggregate without reviewing the raw item performance.
The manual reports standard scores with a mean of 100 and a standard deviation of 15. That means anything between 85 and 115 falls within the average range. Below 70 is significantly below average. Between 70 and 84 is borderline. These bands are not thresholds for eligibility determinations in every state, and they should not be treated as such. I have watched school districts deny services based solely on a score just above 70, ignoring the qualitative data that accompanied it. That is a mistake.
How to Administer It Properly
Administration takes roughly 20 to 30 minutes for children between 1 month and 18 years of age, depending on the child's attention and motor capacity. You need the stimulus kit: small blocks, a lacing bead, coins, marbles, puzzle pieces, crayons, and a few other standardized materials. Everything comes in the official kit, and substituting your own objects will invalidate the norms. Do not do it. Start at the child's developmental level rather than age level if you are working with a child who has a known delay. The manual includes branching rules that let you move up or down the items. I usually begin five months below the child's chronological age when the referral indicates a possible motor delay. This prevents the child from getting frustrated immediately and gives you a clearer picture of the lower end of their ability range. Then you branch upward until they miss two consecutive items at the same level, which signals the ceiling. Here is a practical edge case that nobody warns you about. A child with bilateral hand tremors from a medication side effect will perform inconsistently on items that require sustained static grip, like holding a crayon while coloring. On the Peabody Fine Motor Assessment, the scoring guide assumes a consistent motor output. I ran into this with a nine-year-old on stimulant medication for ADHD. His scores dropped by nearly 15 points on the manual administration versus a second session when the dose had worn off. I noted the timing in my report and recommended a retest under different conditions. Without that notation, the low score would have looked like a permanent deficit.
Get the Full Details

Scoring and Interpretation
Scoring is dichotomous: the child either performs the item correctly or does not. There is no partial credit. Each item has a specific criteria defined in the manual, and the criteria are strict. A block tower that wobbles and falls during the transition phase does not count. A scribble that stays entirely within a printed circle counts. These distinctions matter because they affect the raw score, which then converts to a standard score through the norm tables. The manual provides age equivalent scores, standard scores, percentile ranks, and motor quotients. Use all of them, but prioritize the standard scores and percentile ranks for clinical decision-making. Age equivalents are tempting because they sound intuitive, but they are not equal-interval units and should never be the primary metric in a formal report. I once saw a pediatrician write that a child improved by two age months after six months of therapy. Two age months at different points on the scale does not represent the same amount of actual developmental change. The standard score improvement told the real story, and it was substantially larger. One counter-intuitive finding from my experience is that children with visual perceptual weaknesses often score lower on Peabody fine motor items than their actual motor capacity warrants. Items that require visual-motor integration, like copying a cross or a square, can drag a score down even when the child's pure fine motor execution is intact. I have recommended separate visual-perceptual testing whenever the fine motor score is unexpectedly low compared to the gross motor score on the same battery. The discrepancy itself is diagnostic information.
Common Pitfalls
The most frequent error I see is administrators reading instructions verbatim instead of demonstrating the task. The Peabody Fine Motor Assessment items are designed so that a model demonstration is sufficient and often superior to verbal explanation. A three-year-old will not follow a verbal description of how to stack blocks. She will watch you do it once and then try it herself. Reading the script word-for-word adds time and introduces comprehension variables that have nothing to do with fine motor ability. Another pitfall is administering in the wrong environment. Background noise, visual distractions, and uncomfortable seating all affect performance on fine motor tasks more than people realize. Fine motor requires focus and bilateral coordination. A child who is cold, hungry, or overly stimulated will not perform at baseline. I always check the room conditions before starting and reschedule if the child is clearly uncomfortable. The data is not worth collecting if the conditions are not controlled. The Peabody also has a known limitation with children who have unilateral motor impairments. The standard administration assumes bimanual use for many items. A child with hemiparesis may be able to complete the items with adapted techniques, but the normative data does not account for this population. In those cases, I document the adaptations used and treat the resulting score as descriptive rather than norm-referenced. There is no published validity for scaled scores in that group, and presenting it as such is misleading.
Where to Get the Materials
The assessment is published by Pearson Clinical. You can order the complete kit with stimulus materials, record forms, and manual through Pearson's direct channel or through authorized educational distributors. The current edition is the second edition, which expanded the age range and updated the normative sample. Earlier editions are still valid for comparison purposes but should not be mixed with the second edition norms. Keep your edition straight when you pull score tables. Training is strongly recommended before independent administration. Pearson offers webinars and in-person workshops, and many university programs include Peabody administration in their graduate curricula. I completed a supervised practicum module before I felt comfortable scoring independently. The branching rules and stop criteria are simple in theory but easy to misapply under time pressure. A half-day training course usually covers the common scoring errors and lets you practice with recorded examples.

Alternatives and When to Use Something Else
If you need a shorter screen, the Bruininks-Oseretsky Test of Motor Proficiency has a fine motor brevity form that takes about ten minutes. It is less comprehensive but sufficient for eligibility screening in some school settings. If you are working with infants under 12 months and need something more granular, the Bayley Scales of Infant Development provide finer granularity at the lower age range. The Peabody covers that range too, but the Bayley items are more sensitive to subtle changes in the first year. For children with significant intellectual disabilities or sensory impairments, the Peabody Fine Motor Assessment may not yield meaningful scores regardless of administration quality. I have encountered cases where the child could not attend to the stimuli well enough to complete even the earliest items. In those situations, a criterion-referenced observational tool like the Pediatric Evaluation of Disability Inventory or a detailed occupational therapy clinical observation provides more useful data than a standardized score that cannot be reliably obtained. Documentation quality matters as much as the score itself. I always include notes on the child's approach to items, any compensatory strategies used, and environmental factors that may have influenced performance. A standard score of 68 means very different things depending on whether the child was cooperative and focused or refusing to engage after the first five items. The number alone is insufficient for any meaningful clinical or educational recommendation.