What Actually Happens When You Get Pelvic Physical Therapy For Blocked Fallopian Tubes
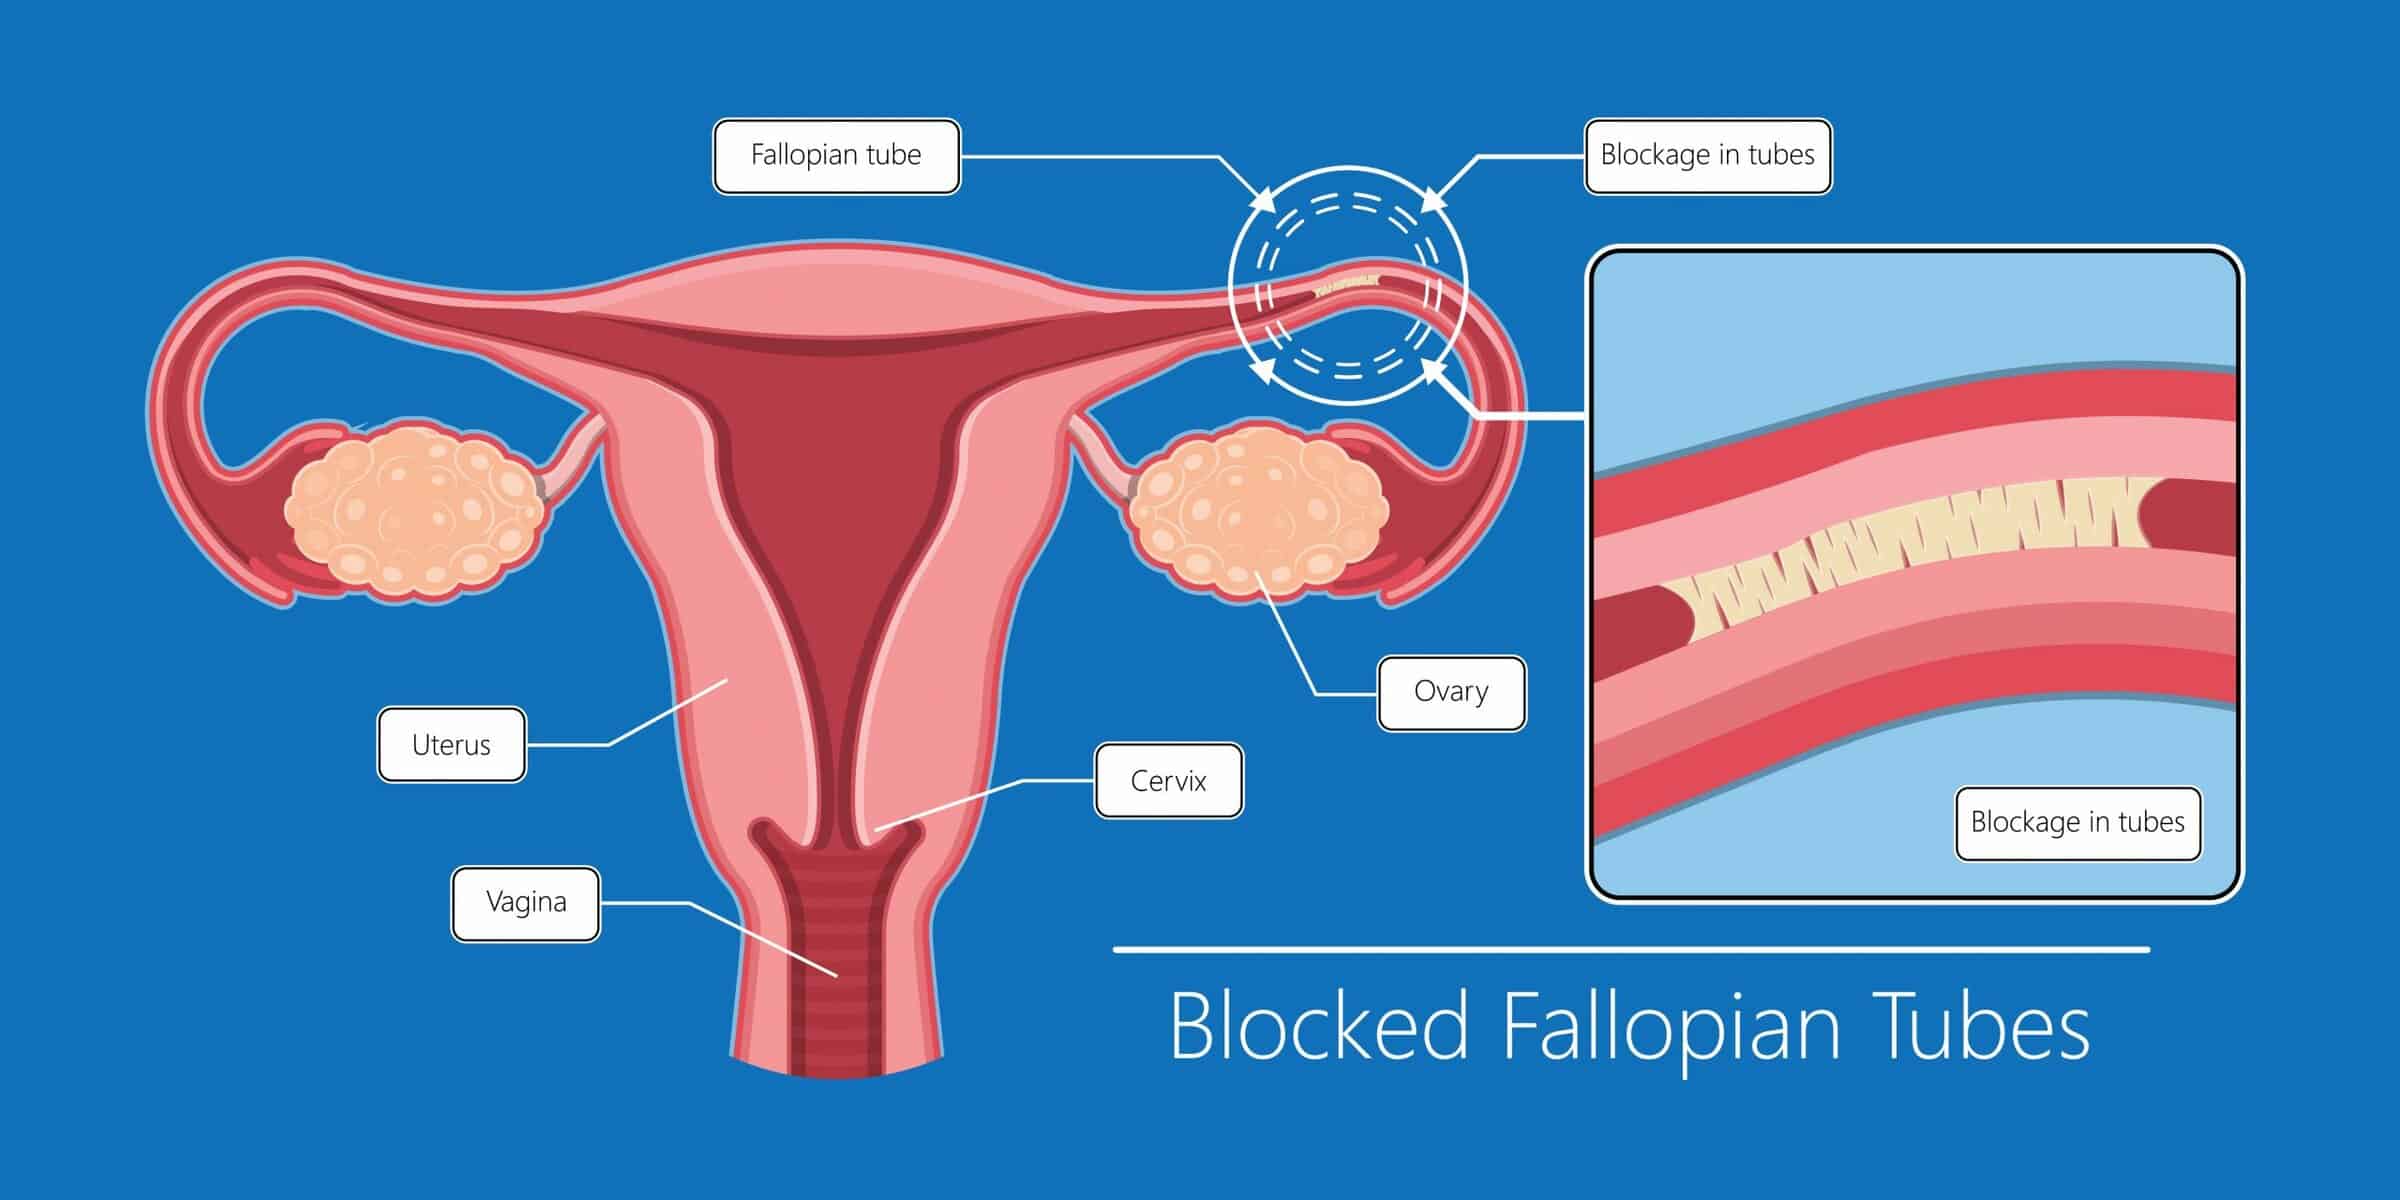
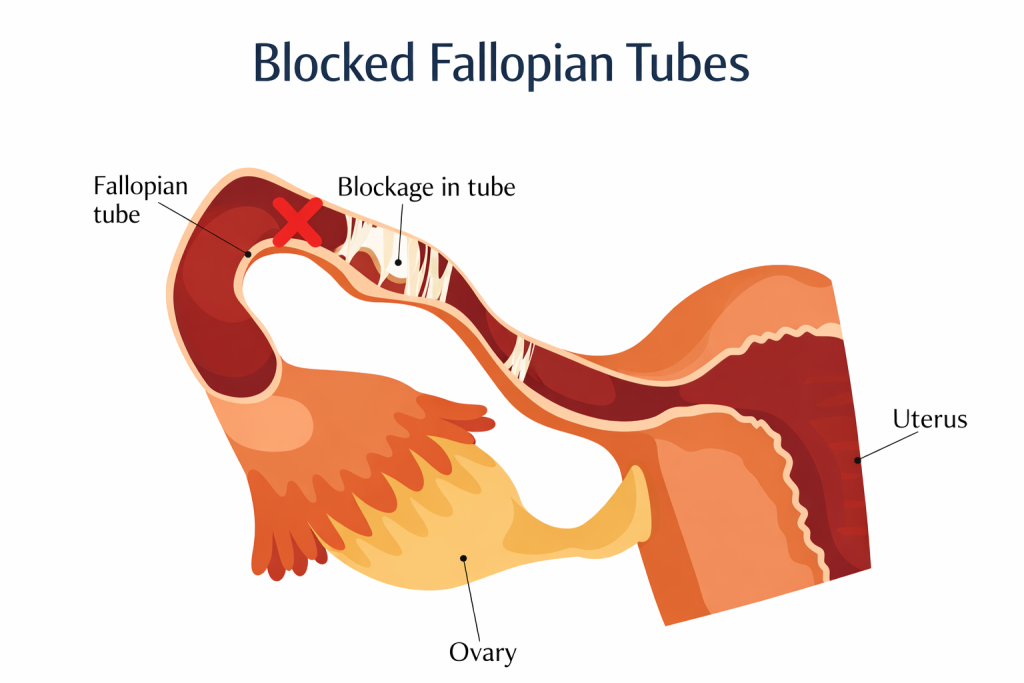
Blocked fallopian tubes are usually caused by scar tissue, past pelvic infections like chlamydia, endometriosis, or surgical adhesions. Pelvic physical therapy does not unblock the tubes themselves. What it does is address the surrounding pelvic floor musculature, connective tissue restrictions, and neural irritation that often accompany tubal pathology. I have seen this play out in clinic after clinic. The approach involves internal and external myofascial release of the pelvic floor, particularly the levator ani complex, obturator internus, and piriformis. These muscles sit in close anatomical relationship to the uterosacral ligaments and the broad ligament, which in turn attach near the fallopian tube region. When there is chronic hypertonicity or trigger point activity in these structures, you can get referred pain, pelvic congestion, and restricted tissue mobility that may contribute to a hostile pelvic environment around the tubes. A typical session runs about 60 minutes. The therapist starts with external work along the lower abdomen, adductor insertions, and gluteal region. Then internal work follows using single-digit gloved fingers with adequate lubrication. The patient should be able to stop the session at any point. It is not a passive treatment. You will be asked to perform diaphragmatic breathing patterns during the manual work so the pelvic floor can down-train its resting tone.
I worked with a patient last year who had bilateral hydrosalpinx confirmed on HSG. She had been in constant pelvic pain for three years and was scheduled for salpingectomy. We tried six weeks of targeted pelvic PT alongside her medical care. The pain scores dropped from an 8 to about a 3 on her daily log, but the tubes remained blocked. This is an important distinction. PT improved her symptom burden and tissue mobility around the pelvis, but it did not reopen the tubal lumen. If you are looking for tubal recanalization, you need to discuss interventional options like laparoscopic surgery or transcervical catheter-based procedures with your reproductive endocrinologist or surgeon.
The Mechanics Behind the Treatment
Pelvic floor muscle hypertonicity creates a compression effect on the neurovascular structures and lymphatic drainage pathways in the pelvis. Chronic elevation of the levator plate can restrict lymph flow and venous return, potentially contributing to pelvic congestion and inflammatory mediator accumulation in the adnexal region. Manual therapy aims to reduce this compressive load. Specific techniques include slow sustained pressure on trigger points in the obturator internus, which sits along the lateral pelvic wall adjacent to the obturator foramen. I typically hold each point for 90 to 120 seconds while the patient breathes through it. Releasing that muscle often produces a noticeable shift in deep pelvic ache within a single session. Another technique I use frequently involves cross-friction mobilization of the uterosacral ligaments. These ligaments run from the cervix to the sacrum and can become fibrotic after pelvic inflammation. Working along their length with gentle shearing forces can improve gliding between fascial layers. You will often feel a gritty or nodular texture under the fingers when adhesions are present. This is not painful in a damaging way but it is uncomfortable, and patients sometimes describe it as a deep bruising sensation. The external component targets the lower abdominal wall, particularly the transverse abdominis and internal oblique insertions near the pubic crest. Scar tissue from prior C-sections or laparoscopic procedures can tether these layers to the underlying fascia. I use manual skin rolling and subcutaneous mobilization to restore glide. This part of the treatment is often overlooked but it matters. A restrictive abdominal wall can pull on the pelvic floor indirectly through the thoracolumbar fascia and inguinal canal region, creating a chain of tension that no amount of internal work alone can resolve.
Get the Full Details
What to Expect Over Multiple Sessions
Most patients need between 8 and 12 sessions spaced once weekly. Some improve faster, others take longer depending on the chronicity of their pelvic floor dysfunction and the extent of their underlying condition. I track progress using a combination of subjective pain scales, bladder and bowel function questionnaires, and manual re-assessment of muscle tone. A patient who comes in with a Grade 3 hypertonic pelvic floor will typically drop to Grade 1 or 2 over the course of treatment if they also do prescribed home exercises. Home exercises usually involve reverse Kegel breathing, where the patient practices gently bulging and relaxing the pelvic floor rather than contracting it. Most people have been doing traditional Kegels their entire lives and actually need the opposite. Stretching protocols for the hip flexors and adductors are also commonly prescribed because tightness in those muscles pulls on the pelvic floor attachment points. I recommend holding stretches for at least 90 seconds per position, three sets daily, rather than the standard 30-second holds you see in generic online routines. There is a practical issue I run into repeatedly. Patients want immediate results. They hear about blocked fallopian tubes and hope PT will open them. I have to manage expectations from session one. Pelvic PT is effective for managing pelvic pain, improving tissue mobility, and supporting overall pelvic function, but it is not a proven treatment for tubal obstruction itself. The evidence base for PT improving fertility outcomes in women with tubal factor infertility is limited to small case series and anecdotal reports. Larger randomized controlled trials do not currently exist.
When It Does Not Work And What to Do Instead
If your blocked tubes are due to dense proximal tubal occlusion from scarring or a large hydrosalpinx with significant fluid accumulation, pelvic PT will not change that anatomical reality. In those cases, the standard medical pathways are laparoscopic salpingostomy, proximal tubal cannulation, or in vitro fertilization with embryo transfer. Hydrosalpinx fluid can be toxic to embryos and reduce IVF success rates by roughly 50 percent, so many reproductive specialists recommend salpingectomy before attempting IVF even if the patient also pursues pelvic PT for pain management. I had a patient who came to me after failing two rounds of IVF. She had unilateral hydrosalpinx that was missed on her initial ultrasound. We spent eight weeks working on her pelvic floor hypertonicity and her pain decreased significantly. But when she went back to her REI for round three, the hydrosalpinx was still there and the cycle was unsuccessful. After salpingectomy, her next IVF transfer succeeded. The PT helped her cope with the chronic pain and improved her quality of life, but the definitive treatment for the blocked tube was surgical. This is the hard truth I tell patients early on.
Practical Considerations for Finding a Therapist
Not all pelvic floor therapists are trained to the same level. Look for someone with advanced certification such as a WCS (Women's Health Clinical Specialist) or completion of a post-professional residency in pelvic health. The Herman and Wallace Institute and the Pelvic Rehabilitation Medicine practice model are reasonable benchmarks for education quality. During an initial evaluation, the therapist should perform a thorough external and internal assessment, discuss your specific diagnosis, and explain what they can and cannot treat. If they promise to unblock your tubes, walk away. That is not within the scope of physical therapy. You should also verify that your insurance covers pelvic floor PT in your area. Out-of-network rates typically range from $120 to $200 per session. Some clinics offer package discounts. If cost is a barrier, university-based physical therapy clinics often provide reduced-rate services supervised by licensed faculty therapists. The combination of accurate diagnosis, realistic expectations, and appropriate treatment selection is what determines whether pelvic physical therapy helps you or just wastes your time and money. For pelvic pain and functional improvement alongside tubal factor issues, it can be valuable. For actually reopening blocked fallopian tubes, the data does not support it as a standalone intervention.