Working with health behavior change models is messy
I spent years implementing structured programs in community health settings, and the Pender model comes up constantly in those conversations. It is not a cure-all. It is a framework people use to organize their thinking about why individuals decide to adopt or skip health behaviors. The model itself centers on how a person perceives their own capabilities, what outcomes they expect, and the personal and social factors that shift their motivation toward action. It moved past earlier deficit-based approaches by emphasizing positive health behaviors rather than just disease prevention. Here is what actually happens when you try to apply it in a real program. You sit down with a target population, often middle-aged adults discussing weight management or medication adherence, and you ask them to walk through their decision-making process. You quickly notice gaps between what they say matters to them and what they actually do. That gap is exactly where the model becomes useful as a diagnostic tool, not as a script to follow rigidly.
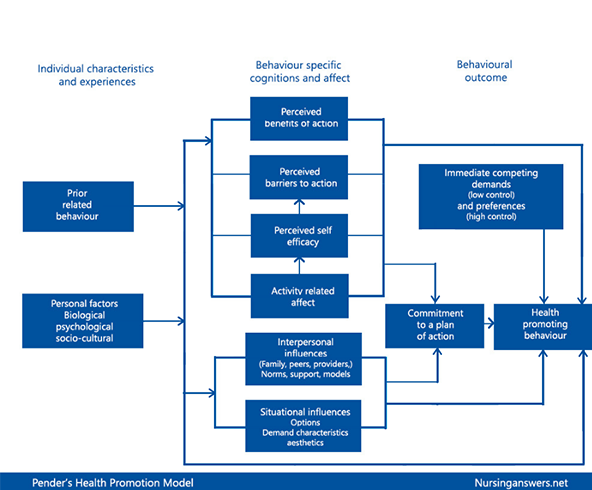
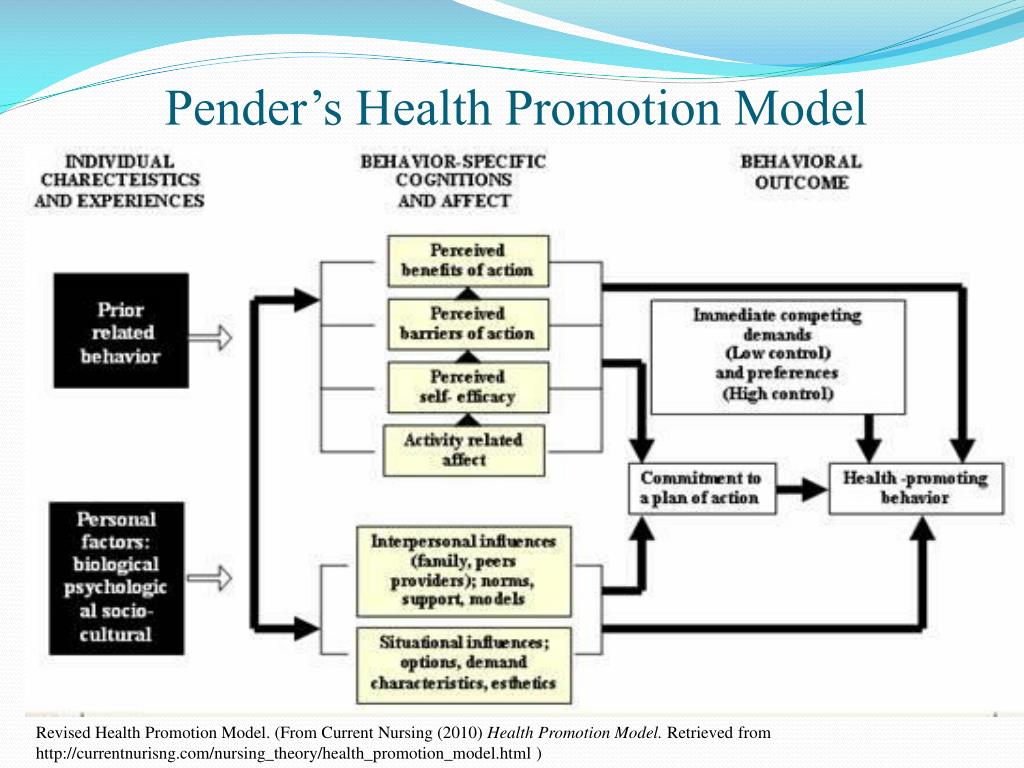
The core components break down into a few clusters. There are individual characteristics like age, ethnicity, and available resources. Then you have behavior-specific cognitions: perceived benefits of the action, perceived barriers standing in the way, activity familiarity, and self-efficacy, which is basically confidence in your ability to execute the behavior. Motivational factors tie these together, and the immediate outcome is either commitment to act or the actual behavior itself. I ran into a stubborn case a few years back working with a diabetes prevention group in a rural clinic. The women in the group understood the benefits. They could recite the dietary guidelines. They scored high on self-efficacy in surveys. Yet attendance at cooking sessions dropped below thirty percent after the third week. The model alone did not explain the drop. I needed to dig into the environmental context, and that meant looking at transportation access, childcare responsibilities, and the simple fact that fresh produce was not available within a ten-mile radius of most participants' homes. We shifted the intervention to focus on portable meal prep using local staples and scheduled sessions around school pickup times. Attendance climbed to sixty-five percent over the next cycle. The model still held. It just needed supplementary variables to make sense of the barrier side of the equation. If you are using this for program design, start by mapping perceived barriers before you write any materials. Most teams jump straight to benefits because benefits are easier to communicate. Barriers are messier, but they are usually what determines whether someone follows through. A practical way to surface them is to ask open questions during intake interviews rather than relying on checklists. People will mention things you did not anticipate, like fear of judgment at a new gym or confusion about reading nutrition labels.
Self-efficacy deserves special attention because it tends to be under-measured. Generic confidence questions inflate scores without capturing behavior-specific readiness. Use validated scales when possible, or at least phrase questions around the exact actions you want people to take, such as walking for thirty minutes three days a week rather than being more active in general. That specificity changes the data enough to matter when you are planning interventions. Activity familiarity is another component people overlook. Someone who grew up swimming or playing team sports enters a wellness program with a different psychological baseline than someone whose physical activities were limited to household chores. The model accounts for this, but the intervention design often does not. Recognize that gap and adjust pacing accordingly. Beginners need shorter, more frequent sessions with clear progress markers. Experienced participants can handle longer durations with less hand-holding. There are limitations worth acknowledging upfront. The model assumes a rational decision-making process that does not always match reality. Emotions, habit loops, and social pressure can override cognitions entirely. It also lacks strong guidance on how to sustain behavior over extended periods. Short-term commitment does not equal long-term maintenance, and the framework does not provide detailed strategies for the relapse phase, which is where many programs fail anyway.
Get the Full Details

Another drawback is the documentation burden. Proper application requires collecting perception data across multiple domains before you can design targeted interventions. That takes time, staffing, and a willingness to iterate based on findings rather than sticking to a preset curriculum. Smaller organizations with limited budgets often skip steps or rush through assessments, which undermines the whole approach. If you need a simpler starting point for quick screenings, tools like the Health Belief Model or the Transtheoretical Model may be more efficient depending on your goals. The Pender model works best when you have the resources to do it properly, which means investment in participant assessment and flexible program design. When you are ready to put it into practice, download or print a copy of the original model diagram from the nursing theory archives. Having the visual in front of you while you conduct interviews makes it easier to spot which cognitive domain a participant is struggling with. Cross-reference their responses against perceived benefits, barriers, self-efficacy, and familiarity, then tailor your next session to address the weakest link rather than reinforcing what already works.
Peter and Jancek did later refinements to the model that expanded the behavioral outcomes and incorporated additional contextual variables. Those updates are worth reading if your program deals with complex populations where family dynamics, cultural norms, and healthcare access interact in unpredictable ways. The core structure remains useful across different settings, but the refinements make it more adaptable to real-world complexity. Track your outcomes honestly. If participation drops, do not assume the model failed. Check whether new barriers emerged, whether self-efficacy scores shifted, or whether the intervention design mismatched the population's actual daily routines. Small adjustments based on data usually yield better results than doubling down on a plan that is clearly not working. One last thing that is not obvious from textbooks: involving participants in the barrier-identification phase improves engagement more than any material you hand out. People respond when they feel heard, and the model gives you a structured way to honor that without abandoning rigor. Keep it simple, stay flexible, and let the data guide your next move.