Repeating the Mechanics Until They Stick
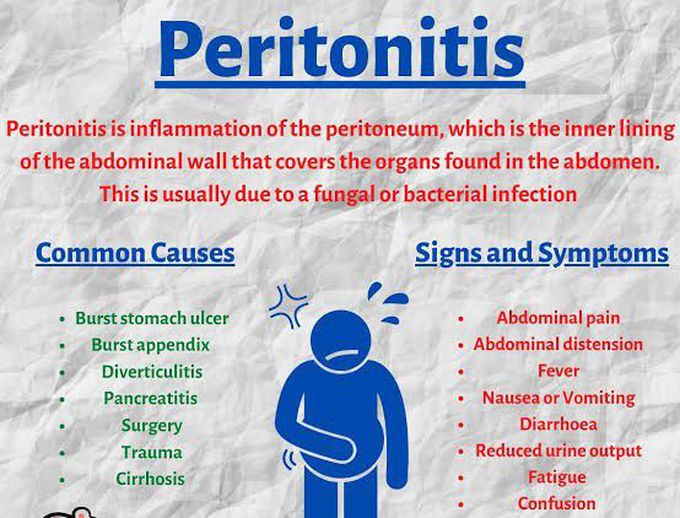
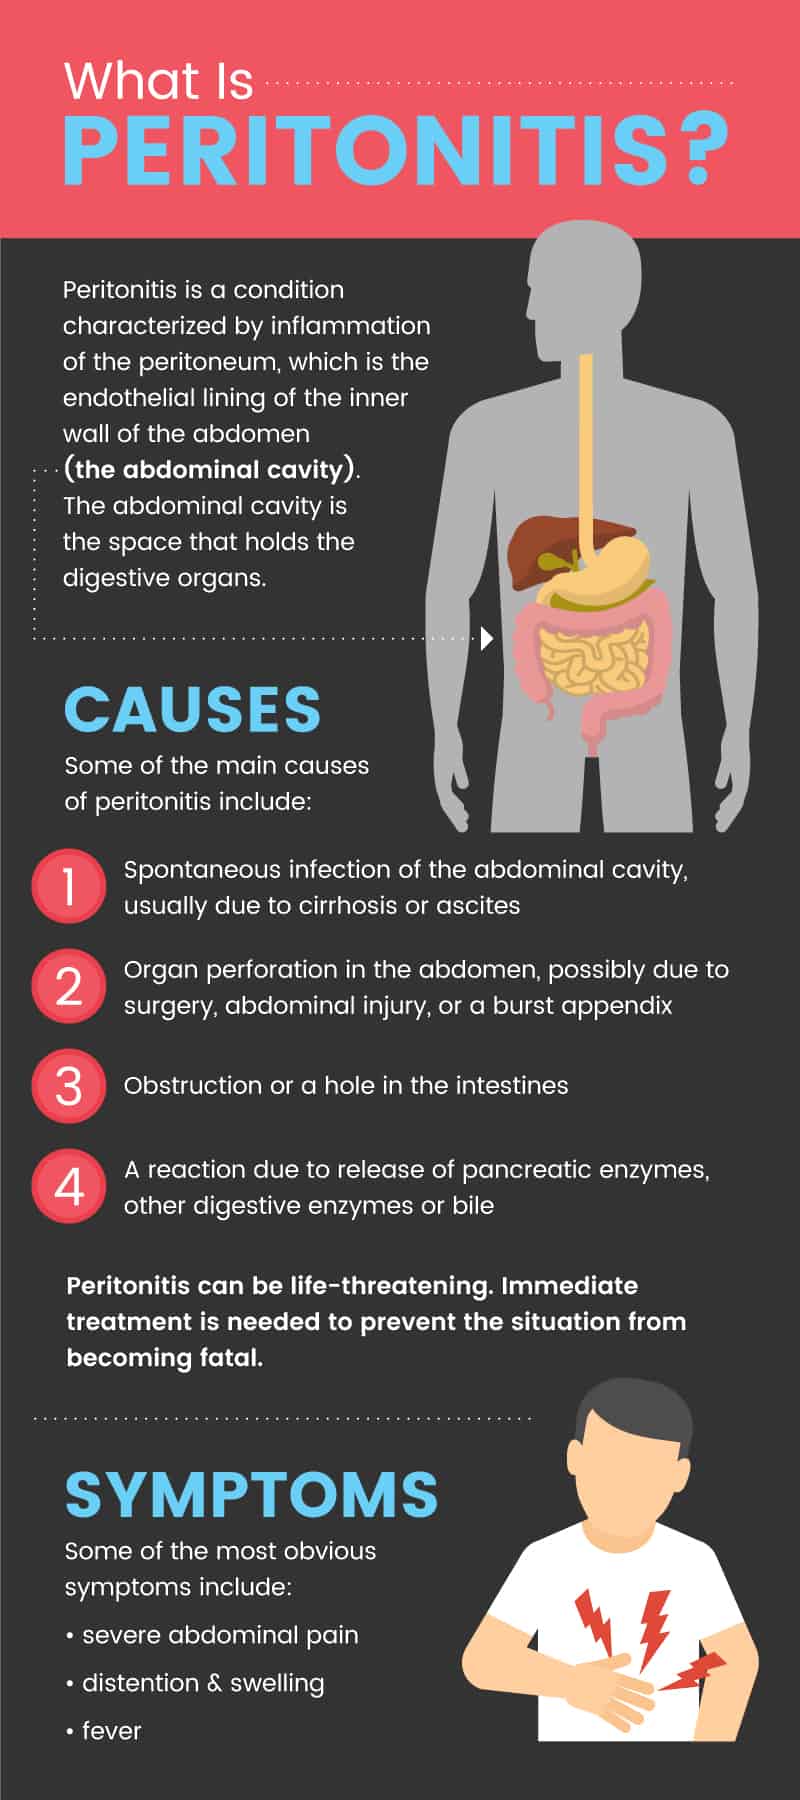
The peritoneum doesn't give you much to work with when it's irritated. It's a thin membrane, and early in the process the signs are subtle enough that experienced clinicians miss them. The whole exam is basically a series of gentle provocations designed to see if the patient can't hide the response. You're looking for involuntary guarding, rebound tenderness, and the ability of the patient to move without triggering sharp pain. Most people learn these as bullet points on flashcards. They're not. They're tactile. You have to feel them. Start with observation. Watch the patient's breathing. If they're taking shallow breaths because deep inspiration drags the inflamed peritoneum against the abdominal wall, you've got your first clue. Then have them lie flat with knees slightly flexed. That relaxes the rectus abdominis just enough. If they resist, if they clench, you note that before you even touch them. Now the hands go on. Light palpation first. Systematic. Right lower quadrant, right upper, epigastrium, left upper, left lower. You're mapping baseline tenderness. Then you push deeper. The moment you feel the abdominal muscles suddenly rigid under your fingers and the patient winces, that's involuntary guarding. Voluntary guarding is different. That's a protective reflex they can control. Involuntary is the real thing. It means the peritoneum is angry enough to fire reflexes you can't will away.
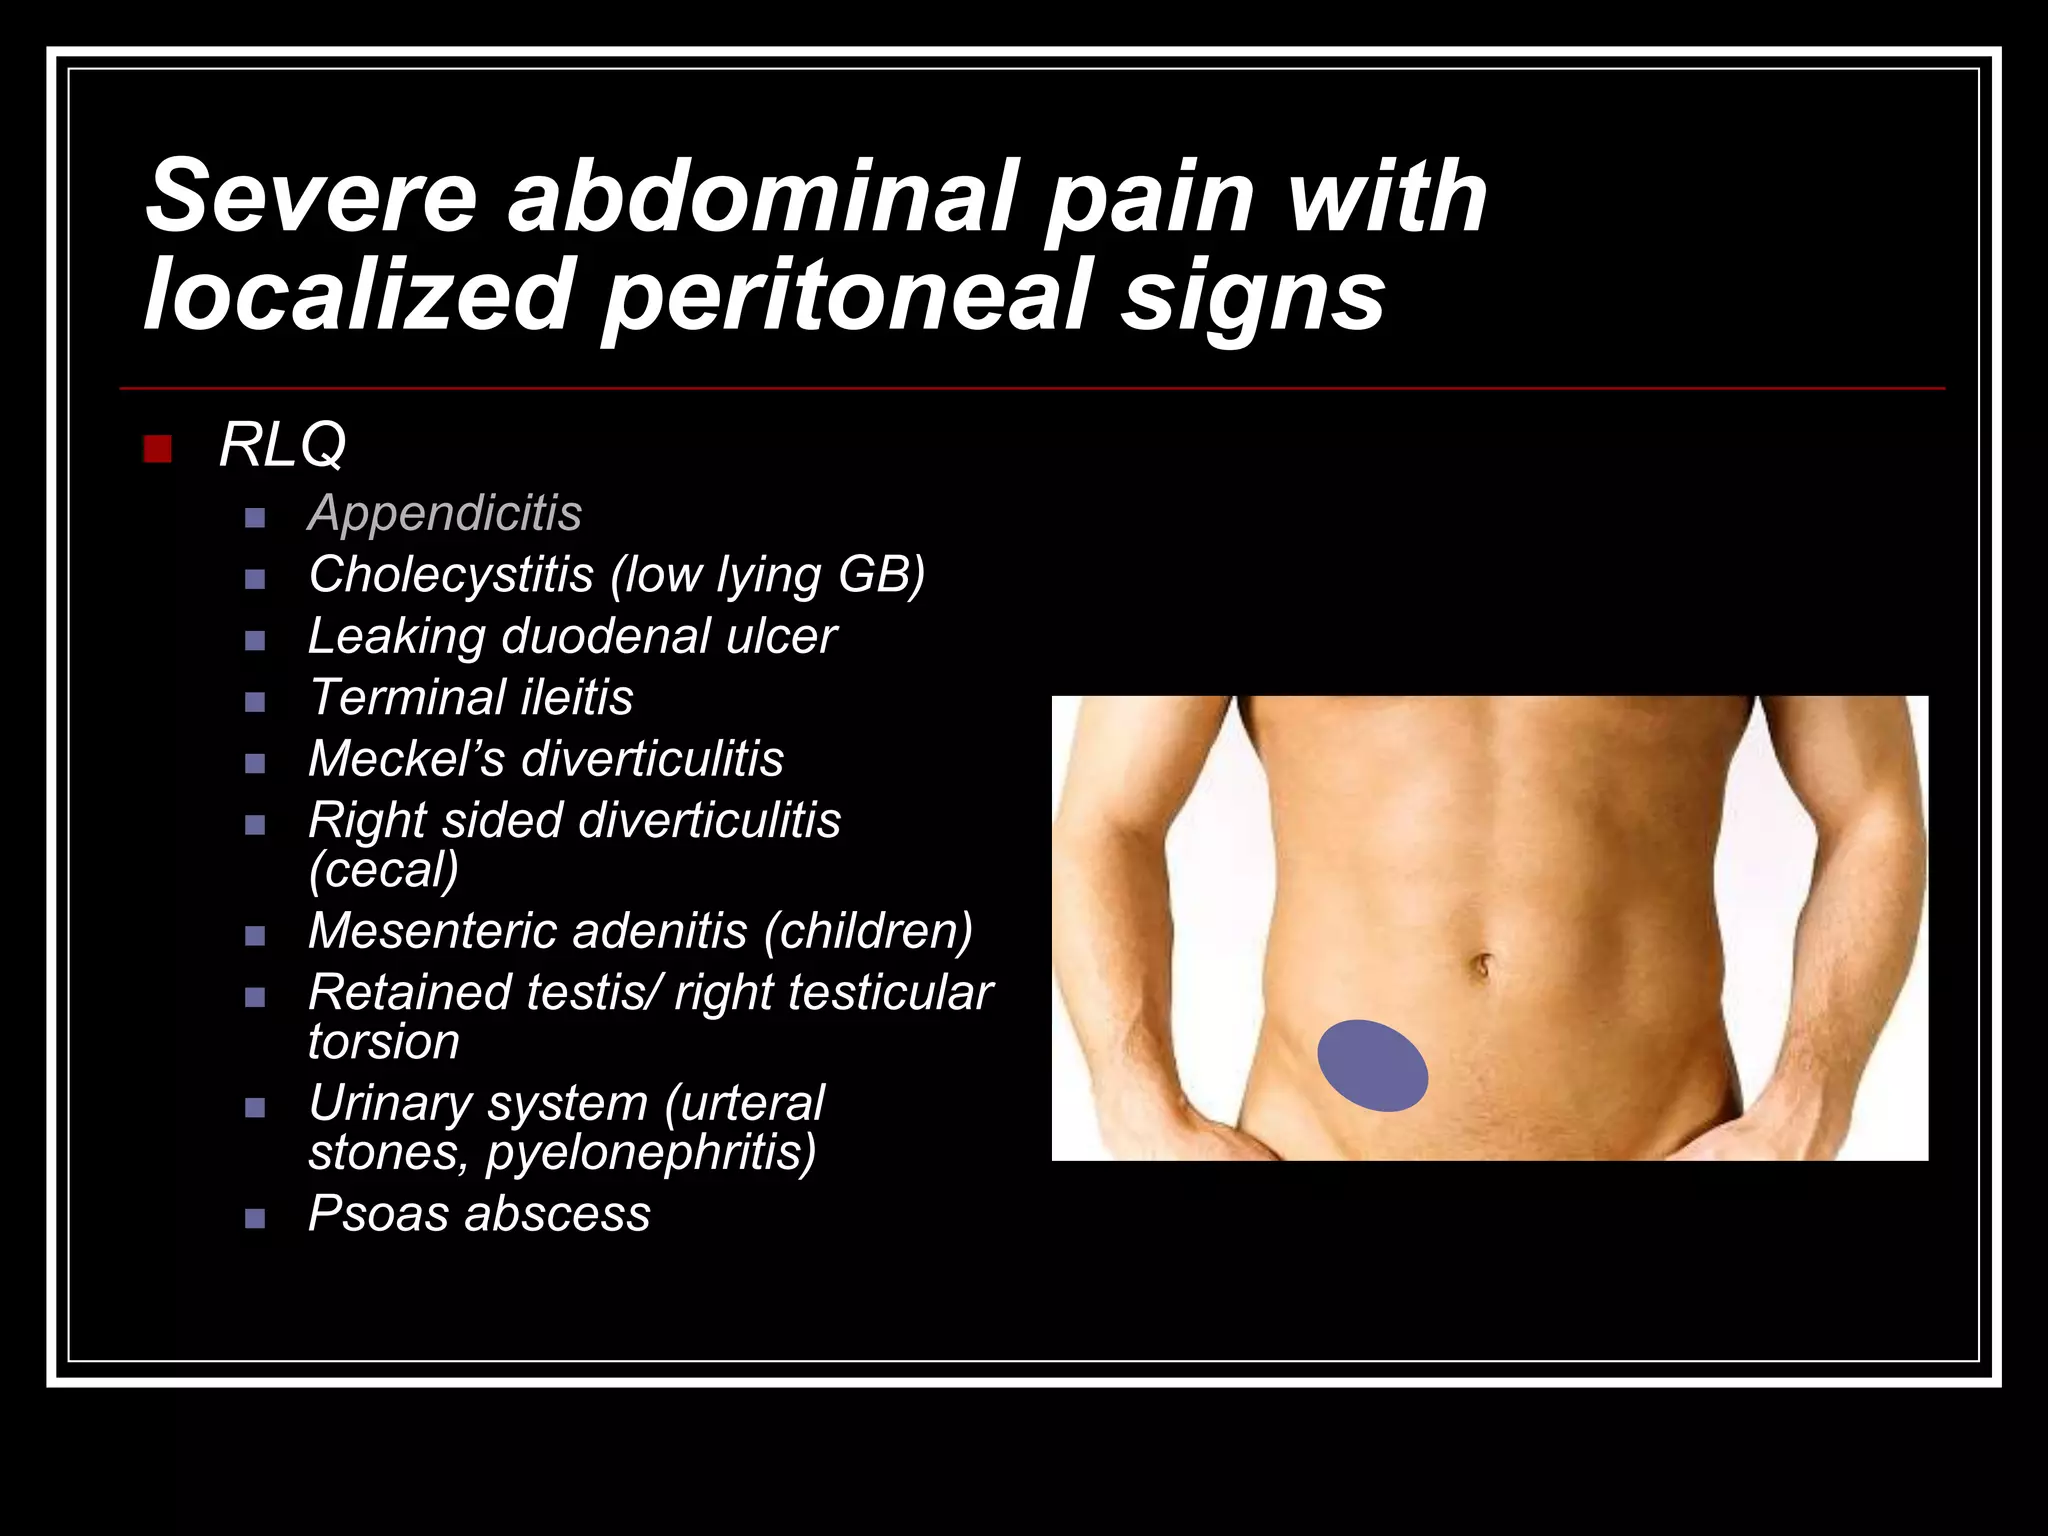
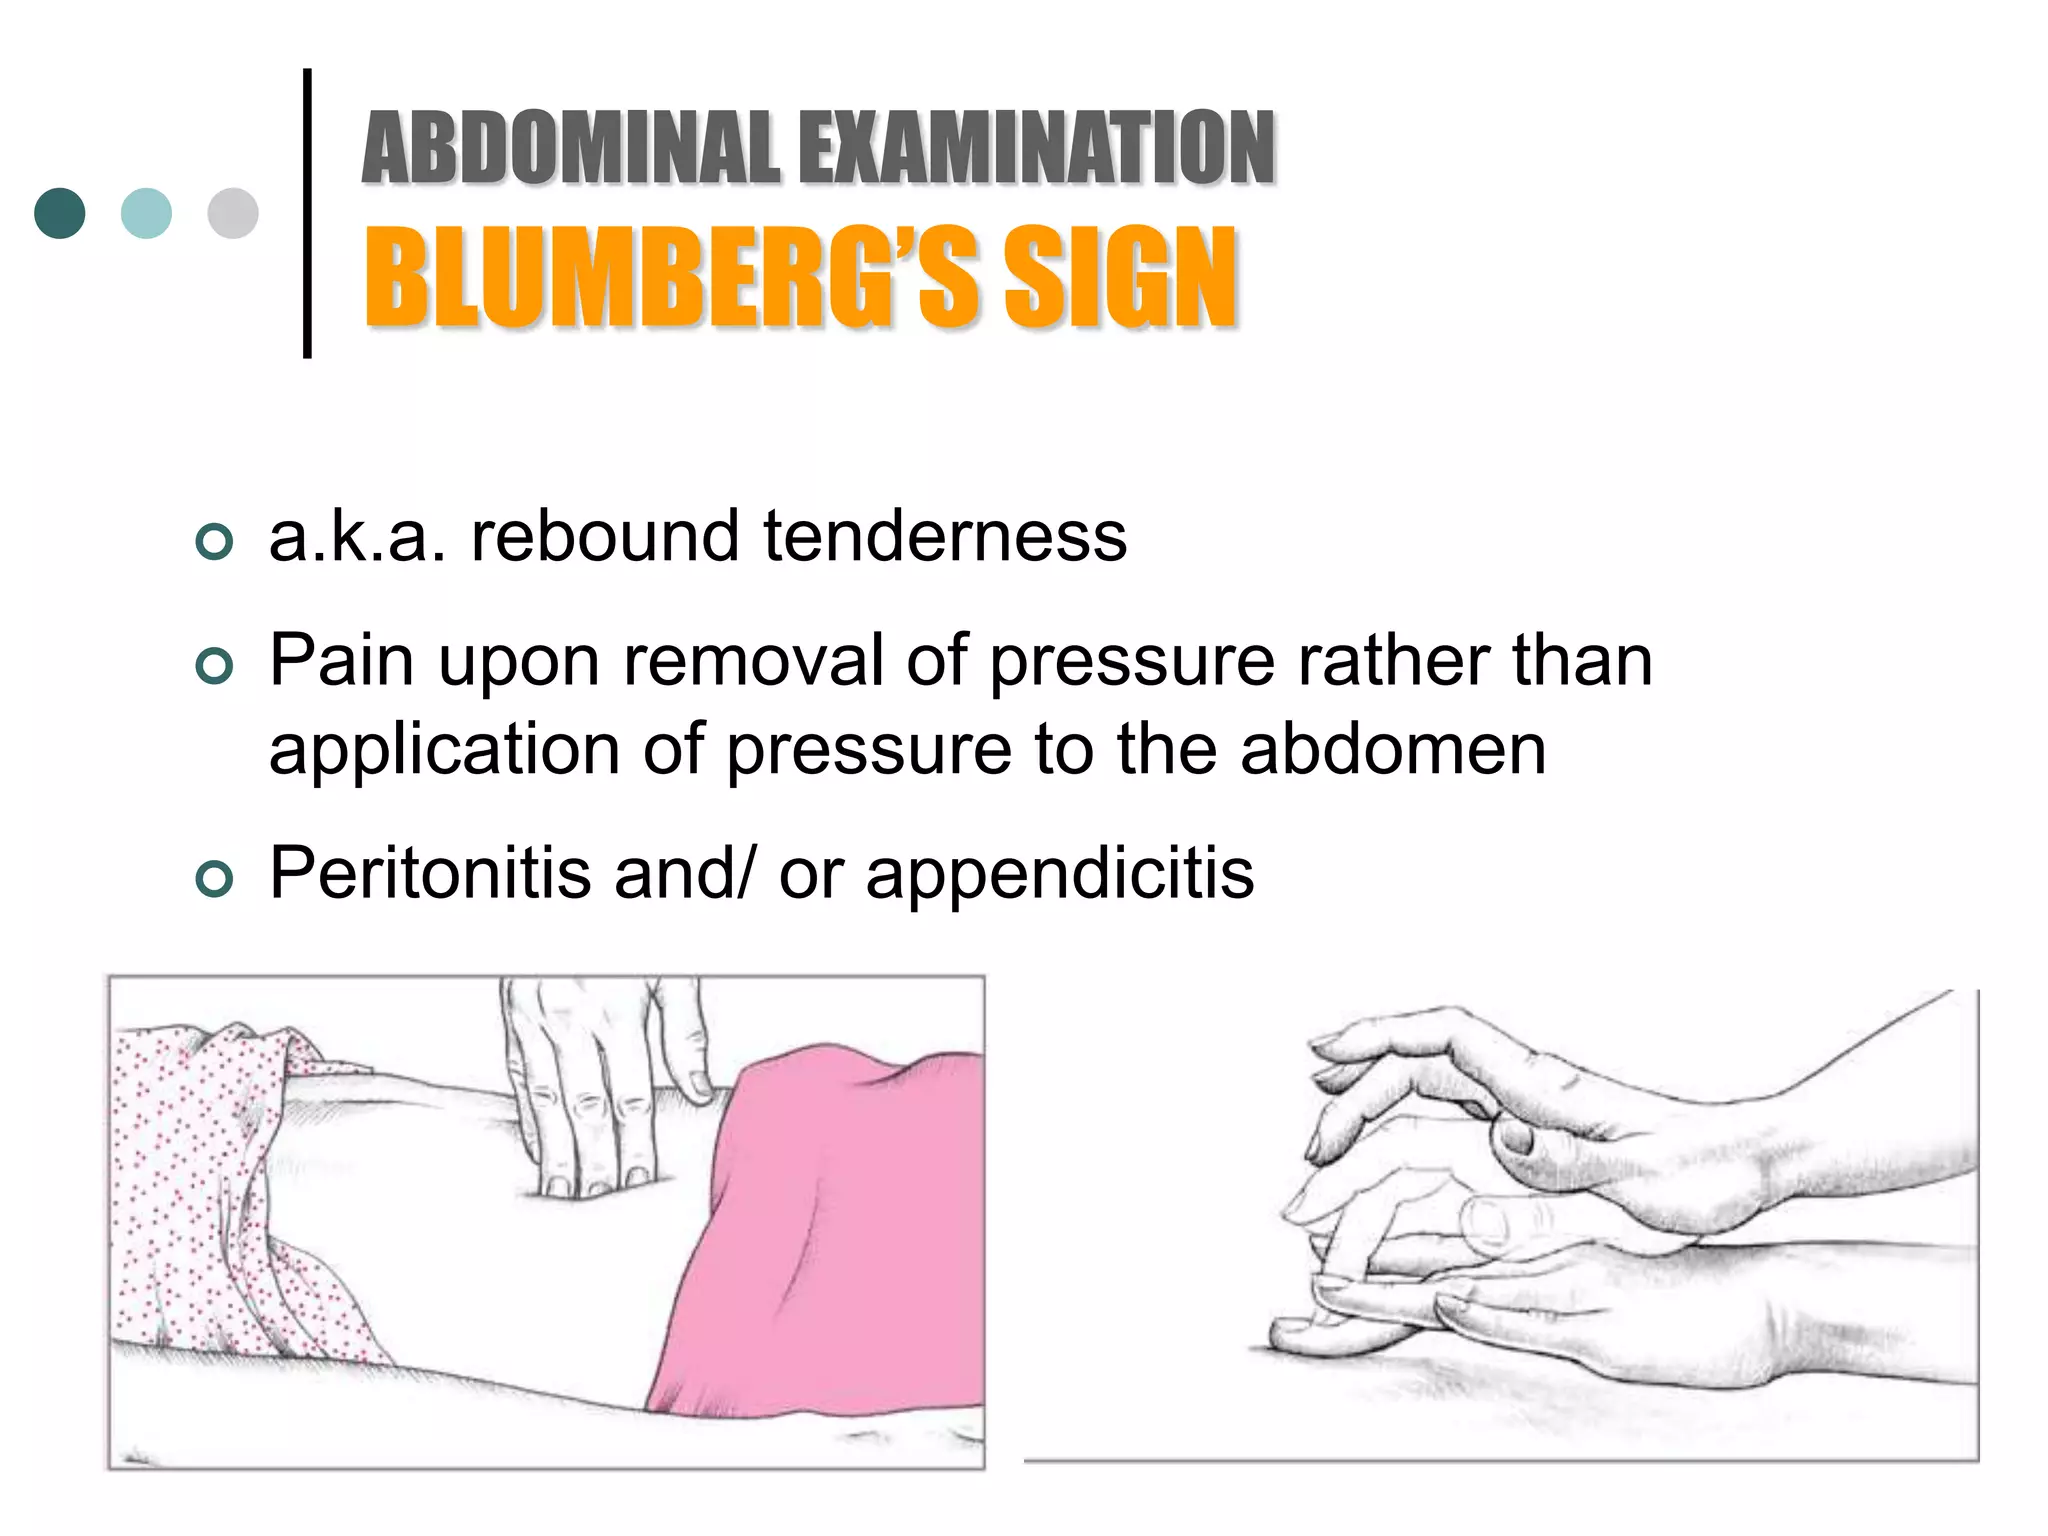
Rebound tenderness is the classic sign but also the one people overuse. Press slowly, hold for a second, then lift your fingers quickly. A positive result is when the pain hits hardest on release, not on compression. That's the counterintuitive part beginners keep getting wrong. They press hard and the patient yelps, then they call it positive. It's not. The rebound component matters. If the pain is the same during compression and release, you've got visceral or muscular tenderness, not peritoneal. I ran into a case last year where a patient had atypical appendicitis. The cecum was retrocecal, tucked behind the colon. Classic McBurney's point tenderness was absent. Rebound was minimal. What I caught was the psoas sign instead. I extended the patient's right leg and felt the resistance. Pain on extension. The appendix was irritating the psoas muscle directly. If I'd stopped after a normal-looking board exam, I would've sent them home. That's why you don't rely on any single sign. You run through the battery and let the pattern speak. There's also the obturator sign. Flex the hip and internally rotate the knee. Pain suggests a pelvic appendix irritating the obturator internus. Again, anatomical variation changes everything. A pregnant patient with a displaced appendix might not show any of the standard signs until late. An elderly patient with blunted immune response might barely react at all. You have to know when the absence of signs doesn't mean the absence of disease.
Another thing worth noting: the costophrenic angle. If you suspect subphrenic irritation, like from a perforated peptic ulcer, tapping along the lower rib margins can elicit referred pain. It's an old maneuver. You rarely see it in textbooks anymore. But it saved me once with a patient whose CT was equivocal and whose direct tenderness was nowhere to be found. The referred pain pointed me to the right area. Drainage happened forty minutes later instead of four. Documentation matters more than people think. Noting exactly where you pressed, how deep, and what the response was creates a trail that tells the whole story. "Diffuse tenderness with rebound most pronounced in the right lower quadrant" carries more weight than "peritoneal signs present." Specificity reduces diagnostic error. It also protects you when the next clinician reads the chart and needs to decide whether to escalate imaging or go straight to surgery. Bottom line: memorize the signs but don't stop at the definitions. Go do the exam on real patients. Let your hands learn the difference between voluntary and involuntary guarding. See how aging, pregnancy, obesity, and immunosuppression change the presentation. The textbook version is a starting point. The real skill is in the repetition.
Get the Full Details