What Supportive Therapy Actually Means for a Peritonsillar Abscess
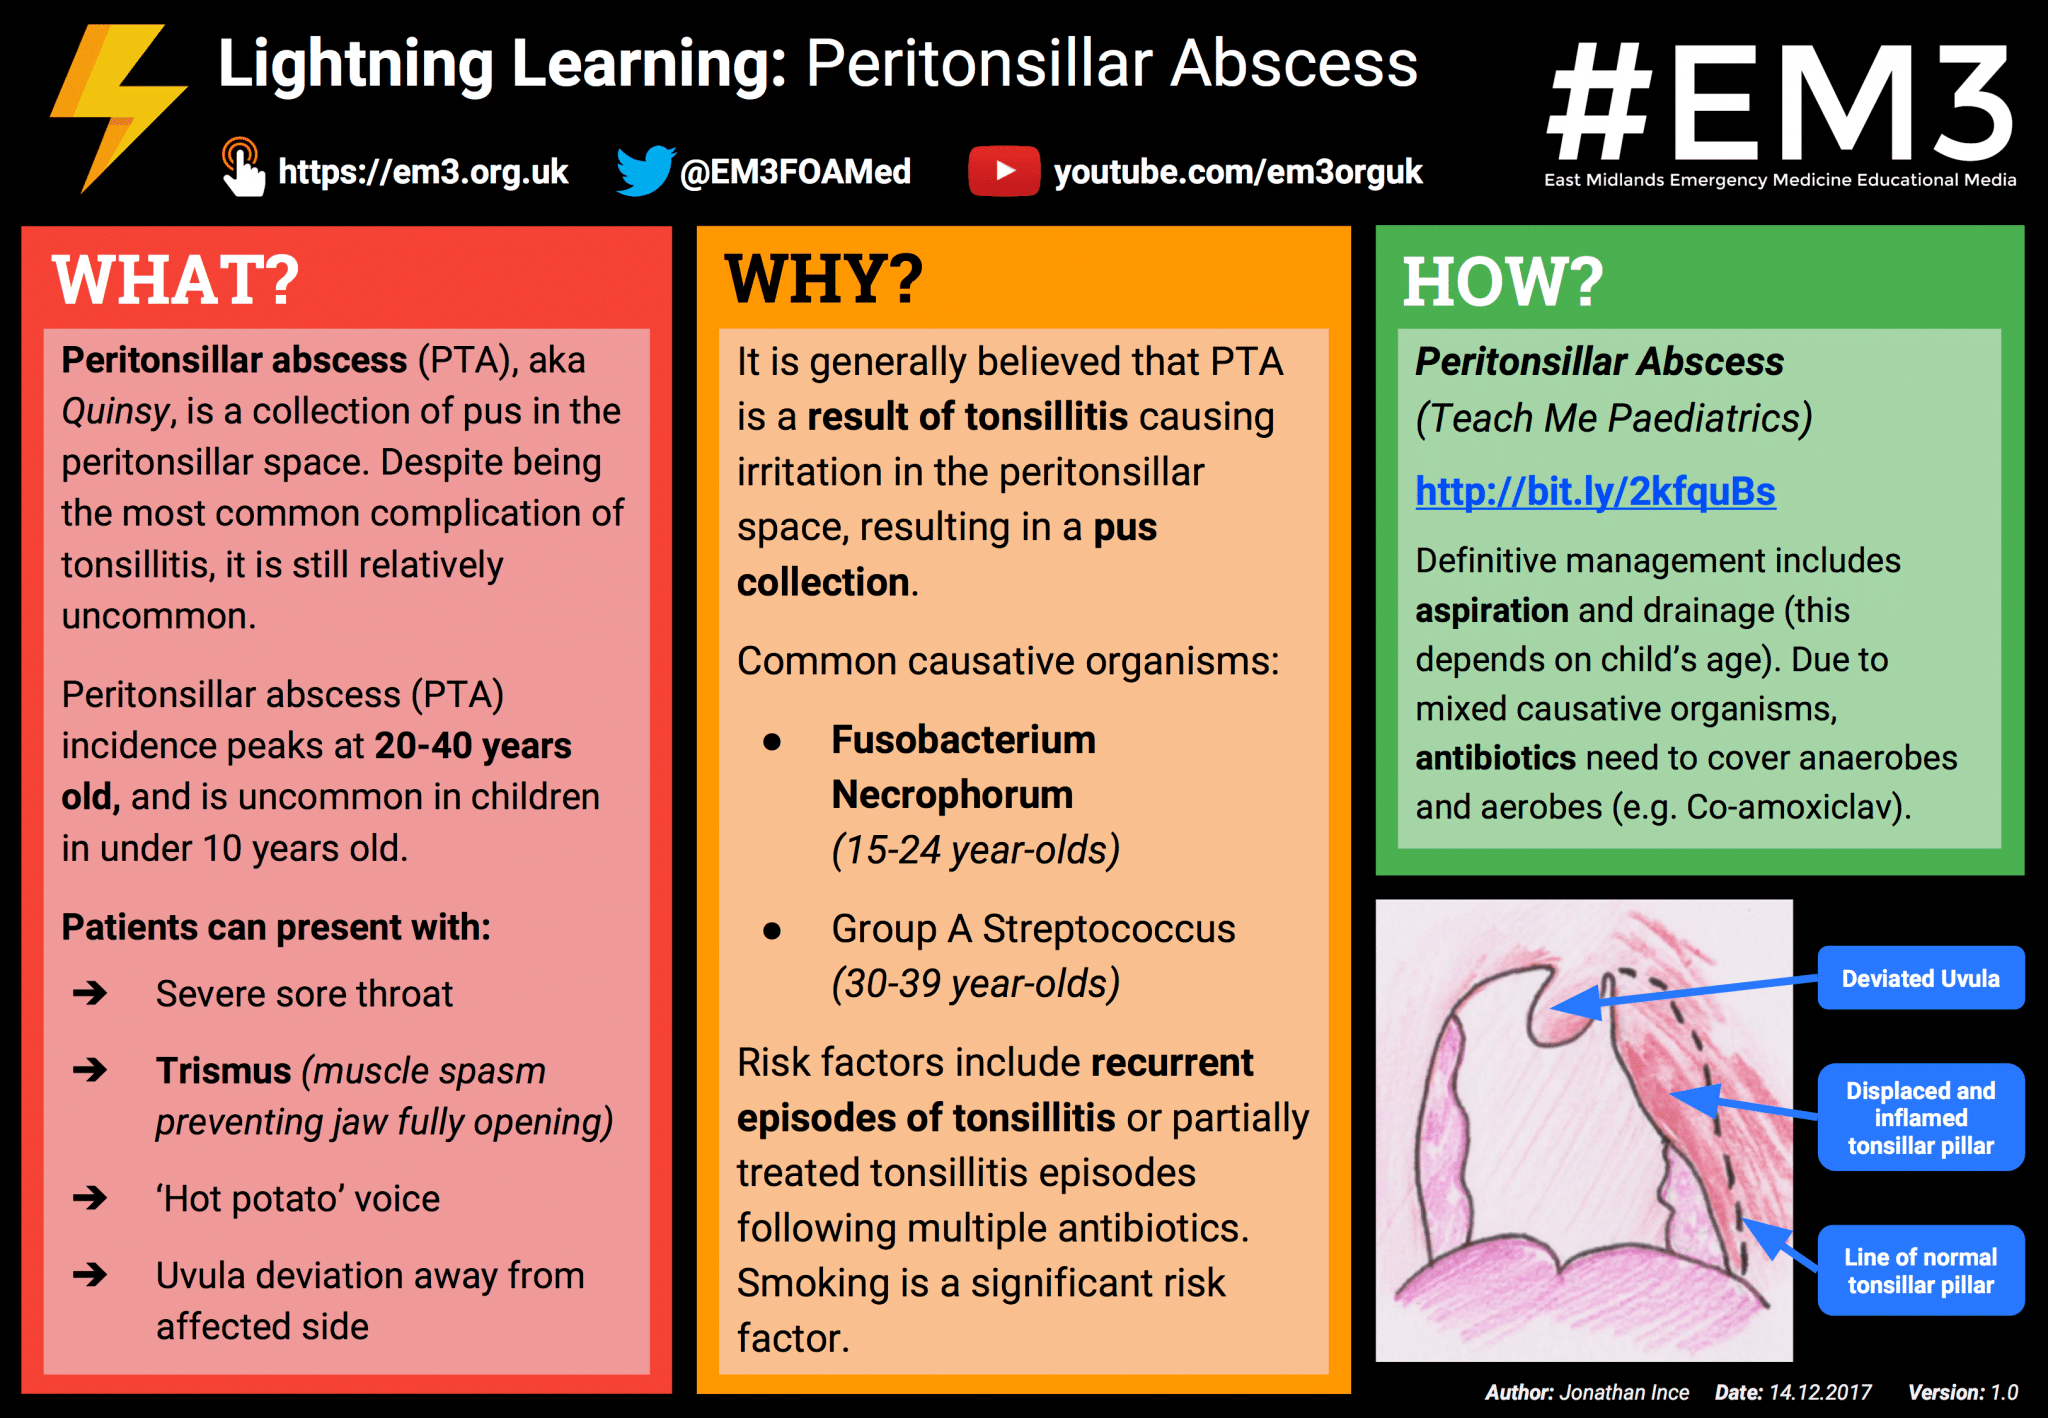
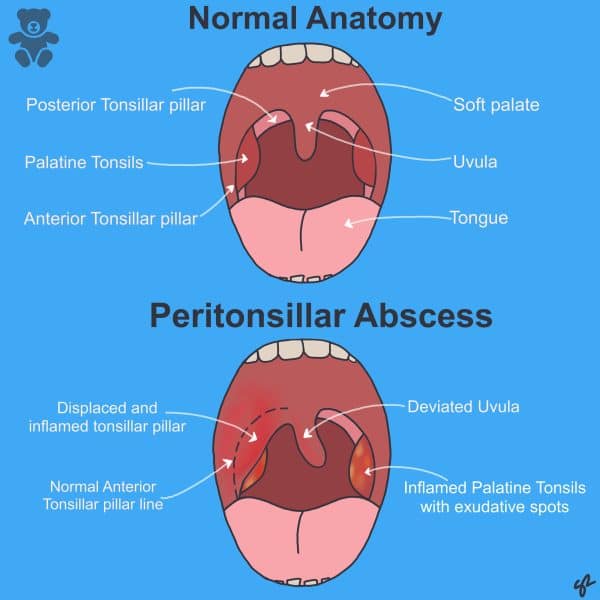
A peritonsillar abscess is a pocket of pus that forms between the tonsil capsule and the superior constrictor muscle. It typically follows an episode of acute tonsillitis that never quite resolves. The patient presents with severe unilateral throat pain, trismus, a muffled "hot potato" voice, and a swollen uvula deviated to the opposite side. Most of these cases show up in the ER at 2 AM after the urgent care office sent them away with a prescription for strep throat that didn't help. Supportive therapy for a peritonsillar abscess means everything that isn't drainage or antibiotics. It's the adjunctive care you provide while the definitive procedure is being arranged or while the abscess is small enough that conservative management might be attempted in select cases. I've seen this approach fail repeatedly when there's a mature, fluctuant collection. Don't confuse supportive therapy with definitive treatment. It only buys time. The cornerstone is adequate hydration. These patients are drinking barely anything because swallowing is excruciating. They dehydrate fast. A quinsy patient can go from mildly mouth-breathing to clinically dehydrated in under 12 hours. I've had patients arrive with a BUN-to-creatinine ratio of 35:1 and dry mucous membranes who hadn't taken more than three sips of water in two days. IV fluids are usually necessary unless the patient can tolerate oral intake, which they almost never can at presentation. Normal saline at 125 to 150 mL per hour keeps most adults going until drainage is performed.
Pain management runs on a schedule, not PRN. The standard approach is a combination of acetaminophen and an NSAID like ibuprofen. I typically use 1000 mg acetaminophen and 600 mg ibuprofen together, dosed every 6 to 8 hours. This dual mechanism hits both the inflammatory and nociceptive pathways, and the data supports the combination as more effective than either agent alone for deep tissue infection pain. If the pain is truly severe and trismus prevents oral intake, IV ketorolac 30 mg is a reasonable alternative. Opioids have a role but they muddy the clinical picture. Sedation from pain medication makes it harder to assess whether the airway is actually compromised or just painful. Use them sparingly and only when the benefit clearly outweighs that cost. Antipyretics are straightforward. Acetaminophen for fever over 38.5 C. Fever is the body's response to the infection but it's also increasing metabolic demand in a patient who can't eat or drink. Bringing the temperature down helps with comfort and fluid preservation. Antibiotics are part of the overall management but they're not supportive therapy. They're definitive adjunctive treatment. The standard regimen covers streptococci, staphylococci, and anaerobes. Ampicillin-sulbactam 3 g IV every 6 hours or clindamycin 600 mg IV every 8 hours if penicillin-allergic. Transition to oral amoxicillin-clavulanate or clindamycin once drainage is complete and the patient is tolerating oral intake. Typical duration is 10 to 14 days.
Here's a specific problem I ran into that nobody warns you about. I was managing a 42-year-old male with a confirmed peritonsillar abscess on CT. Drainage was scheduled but he was sitting in the observation bed for a three-hour wait because the ENT resident was in the OR. His trismus was worsening. His mouth opened less than 1 cm. I had him on IV fluids, ketorolac, and dexamethasone 10 mg IV for the inflammation. At hour two, he started drooling again and couldn't handle his own secretions. The dexamethasone had worn off and the swelling was progressing faster than the drainage schedule. I called the attending directly instead of waiting for the resident. We got him into the OR within 45 minutes. The moral here is simple: supportive therapy doesn't stop progression. If trismus is worsening or drooling returns after initial improvement, the abscess is expanding. No amount of steroids or fluids changes that. Escalate immediately. Steroids deserve a paragraph on their own. Dexamethasone 0.1 to 0.25 mg per kg IV, typically 10 mg for an average adult, is commonly used. It reduces peritonsillar edema and may improve trismus enough to make drainage easier or, in very early cases, theoretically allow the abscess to resolve without intervention. The evidence for steroids reducing the need for drainage is weak. Multiple studies show no statistically significant difference in drainage rates. What steroids do reliably do is improve pain scores within 2 to 4 hours and reduce the time until the patient can tolerate oral fluids. That's valuable even if it doesn't change the ultimate need for drainage. Nutrition is another area that gets overlooked. These patients will lose weight. Not significantly in the short term but the psychological impact of not being able to swallow is real. Once drainage is performed and pain improves, which usually happens within hours, start with cold liquids and soft foods. Ice chips, yogurt, applesauce, broth. Avoid acidic foods like orange juice because they sting raw tissue. The swallowing mechanism recovers quickly after the pressure is relieved. Most patients are eating normally within 48 hours post-drainage.
Get the Full Details

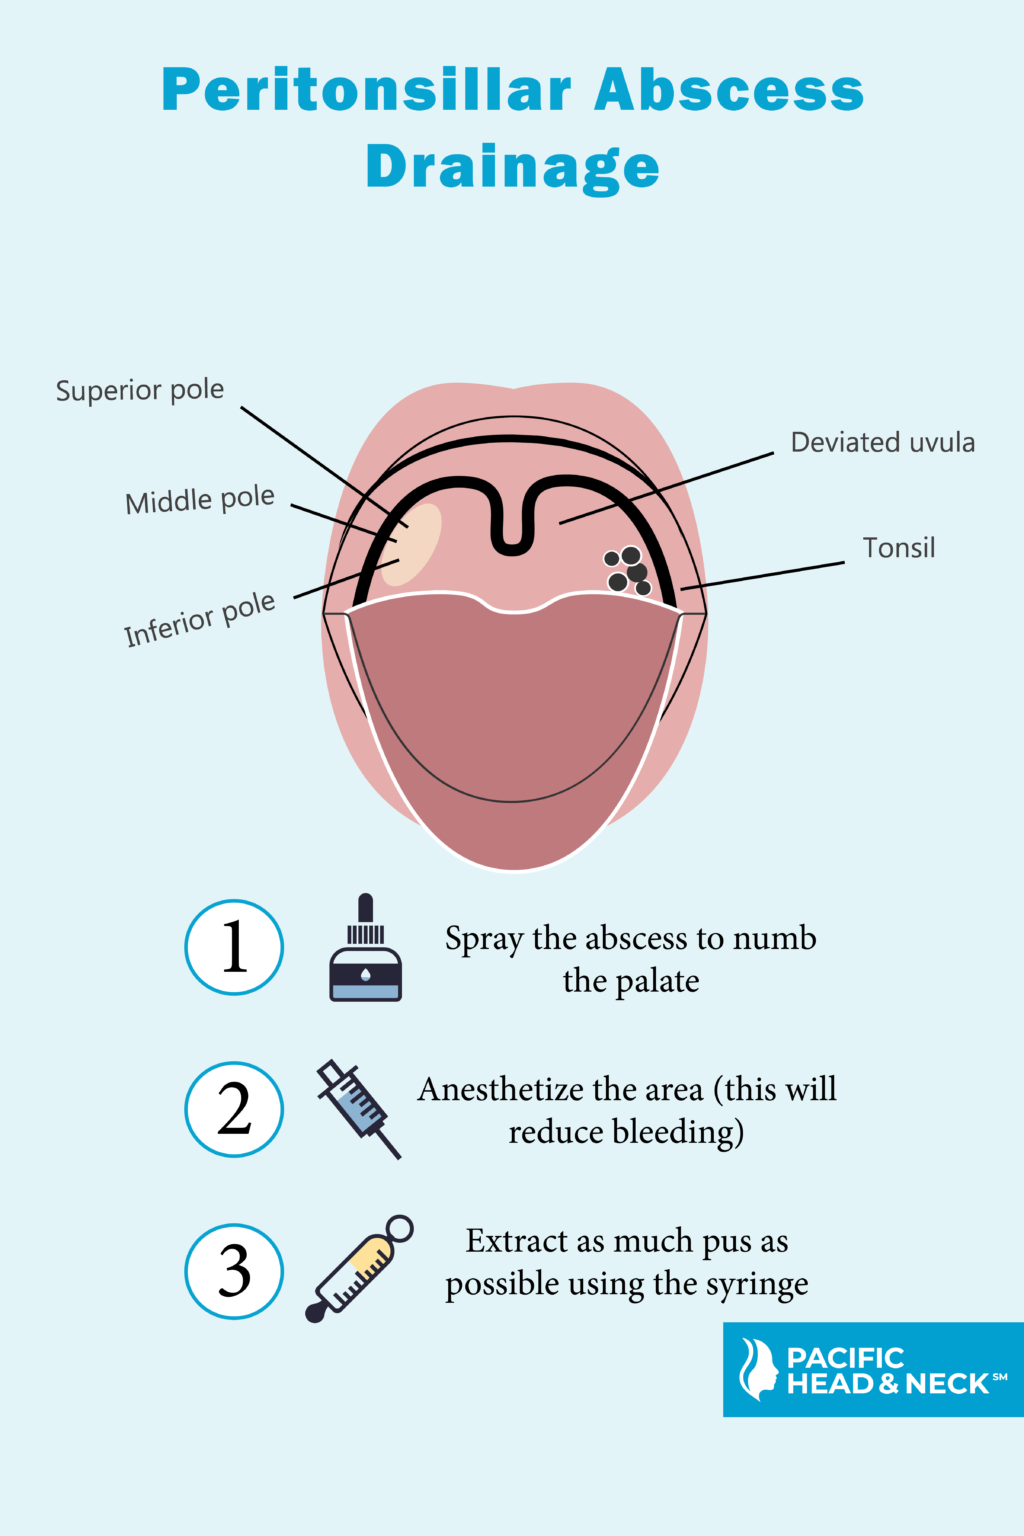
The biggest pitfall I see in practice is assuming supportive therapy can replace drainage in a mature abscess. A peritonsillar abscess that has coalesced into a discrete pocket will not resolve with IV antibiotics and fluids alone. The capsule of the abscess prevents antibiotic penetration. The pus needs a physical exit route. Needle aspiration or incision and drainage reduces hospital stay by approximately one day compared to antibiotics alone and provides immediate symptom relief. Waiting too long on supportive therapy while monitoring for improvement is the most common mistake. Each hour of delay increases the risk of airway compromise and spread to deeper neck spaces. Airway assessment is not supportive therapy but it's the critical context for everything else. Before you start any treatment, check the airway. Look for stridor, drooling, inability to handle secretions, tripod positioning, or respiratory rate above 24. If any of these are present, involve anesthesia early. A difficult airway with a peritonsillar abscess is a nightmare scenario because the swelling distorts normal landmarks. Fiberoptic intubation is the preferred technique if intubation becomes necessary. RSI with direct laryngoscopy can fail because the abscess mass effect narrows the pharynx unpredictably. I've watched this happen. Don't let it happen on your watch. Follow-up after discharge matters. Patients should be re-evaluated within 24 to 48 hours after drainage to confirm resolution. Recurrence happens in approximately 10 percent of cases, usually because drainage was incomplete or the abscess reformatted before the cavity closed. Repeat imaging is indicated if symptoms persist or worsen after 72 hours of appropriate antibiotic therapy following drainage. A recurrent or persistent abscess may require operative drainage under general anesthesia with a more complete exploration of the peritonsillar space.
Tonsillectomy during the acute phase, sometimes called a "quinsy tonsillectomy," is an option in recurrent cases or when drainage fails. The timing is individual. Elective tonsillectomy is the standard recommendation after a single episode in patients who meet criteria for recurrent tonsillitis. But in the acute setting with an active abscess, surgery is technically more difficult due to tissue edema and increased bleeding risk. Most surgeons prefer to complete the antibiotic course and return for elective tonsillectomy four to six weeks later if indicated. The bottom line is that supportive therapy is necessary but insufficient. Hydration, pain control, antipyretics, and sometimes steroids keep the patient stable. Drainage and antibiotics fix the problem. Know the difference.