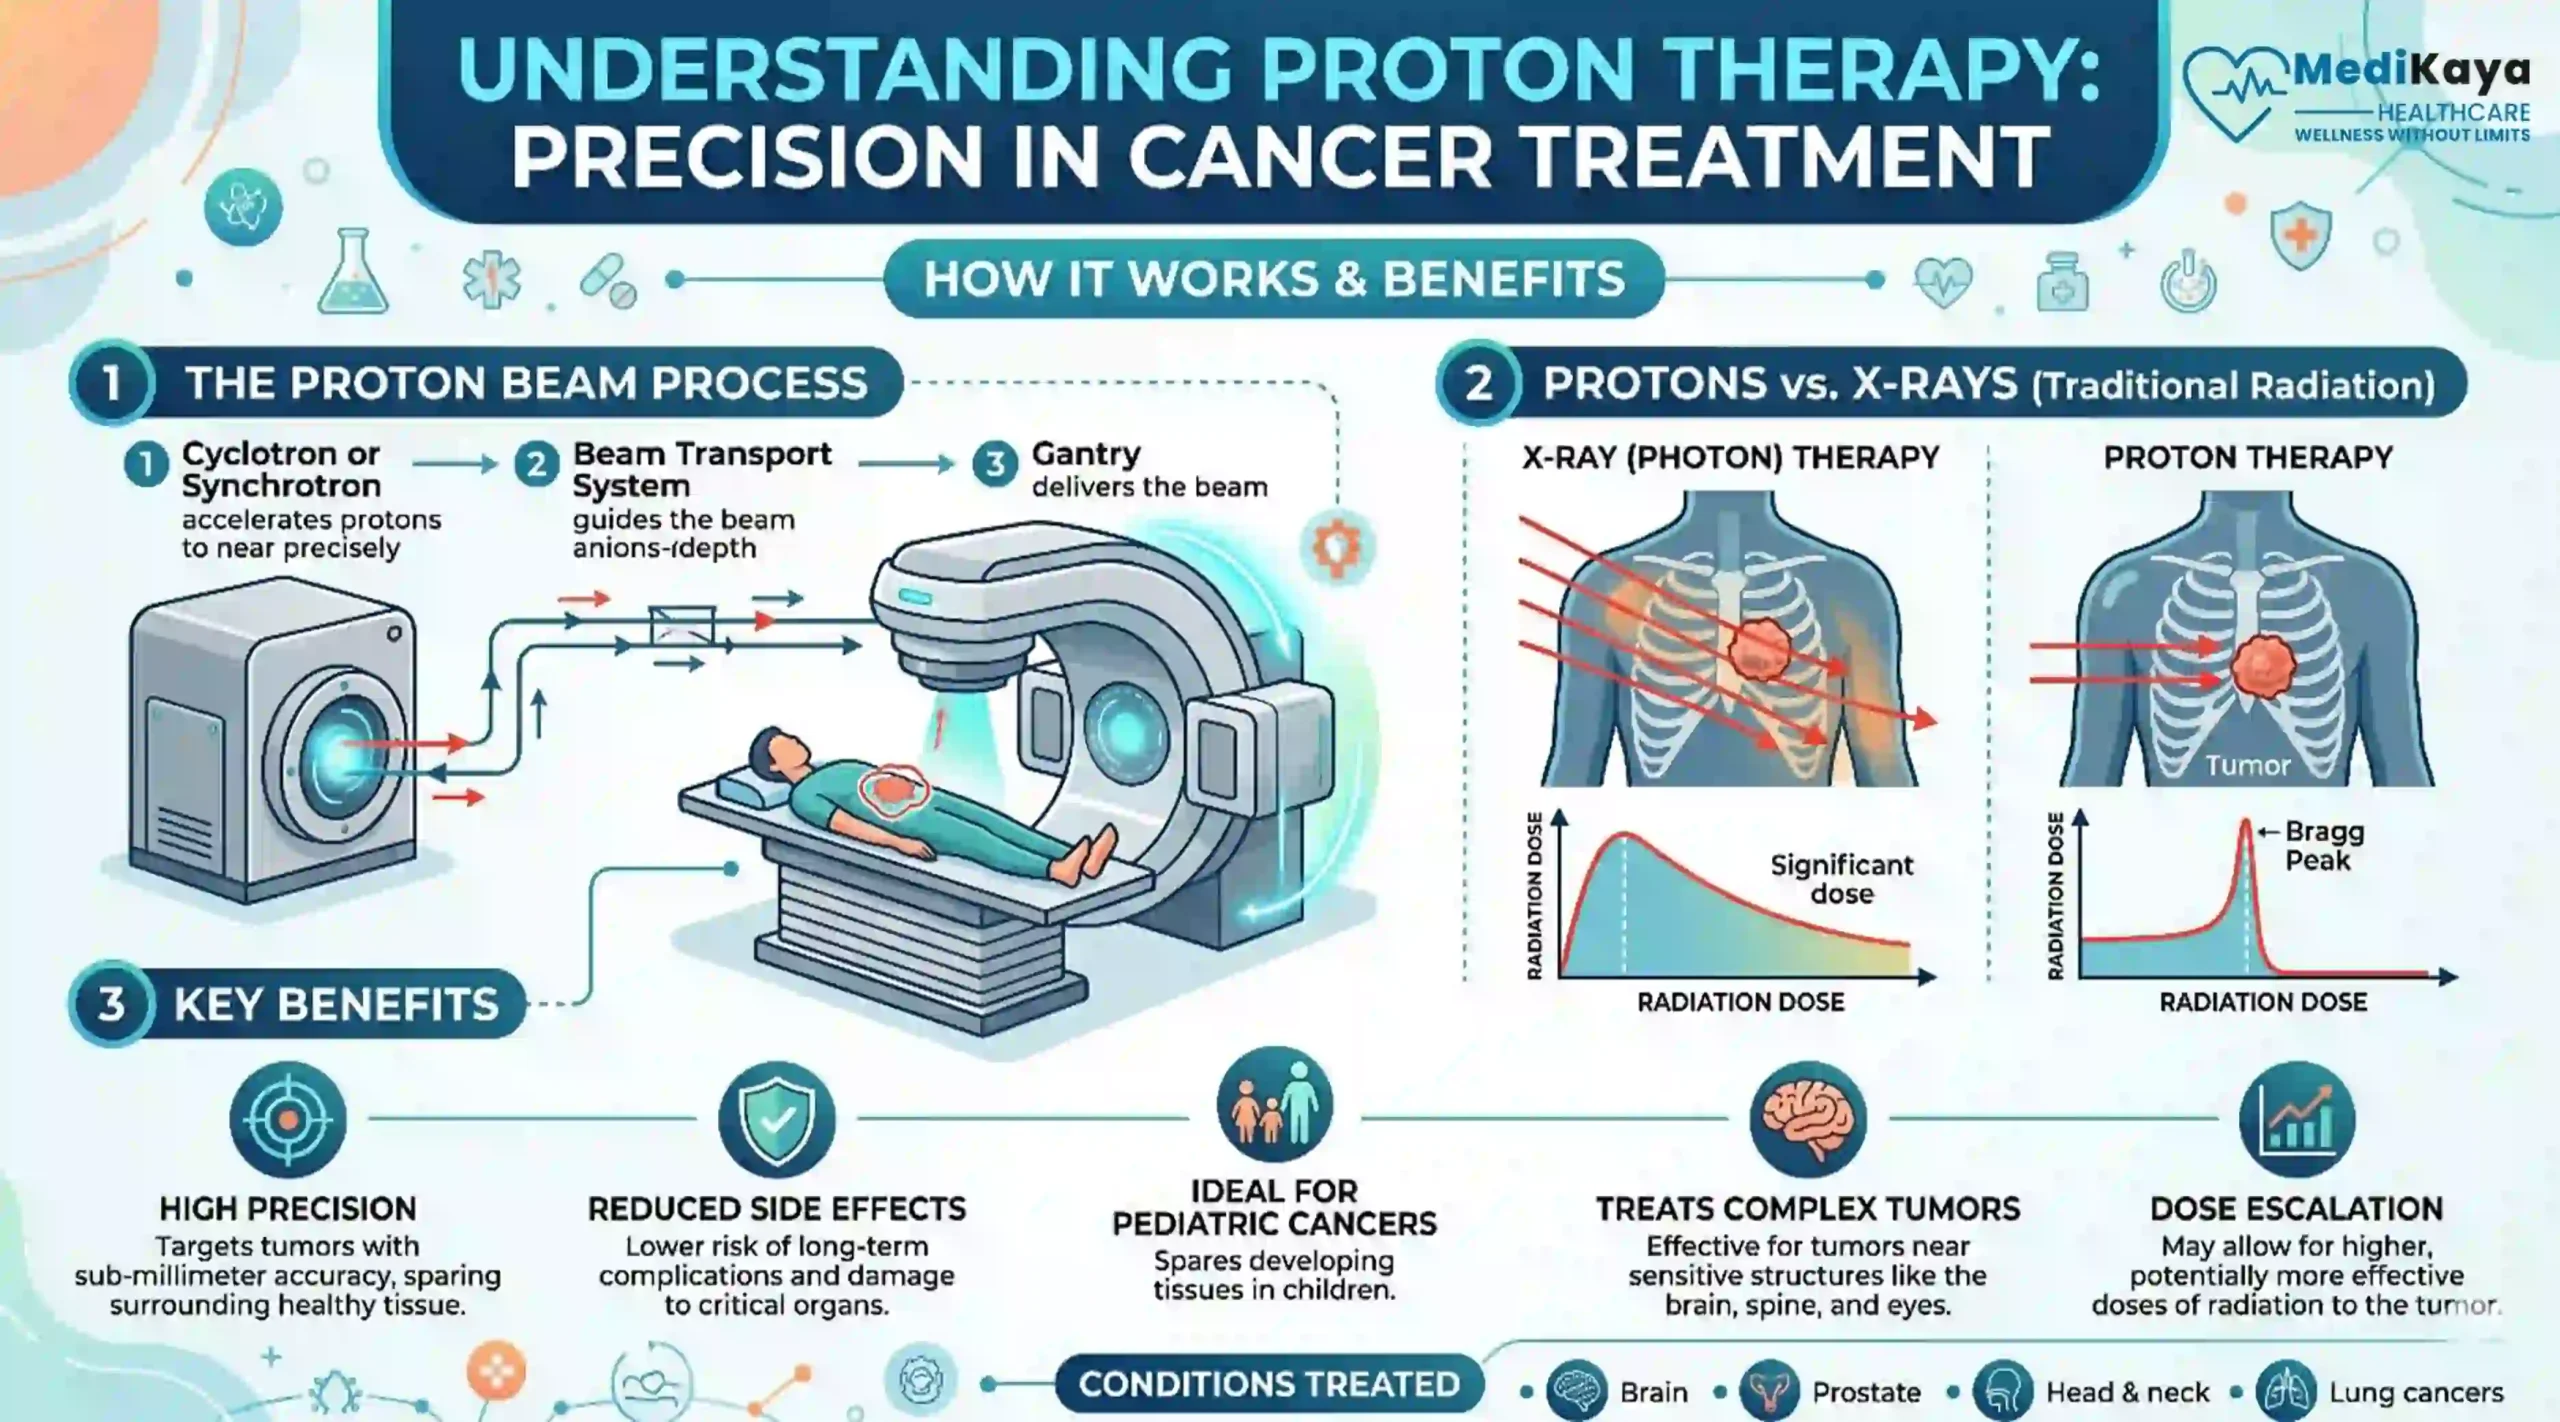
Proton therapy uses a beam of protons — hydrogen atoms stripped of their electrons — to deliver radiation directly to a tumor. Unlike traditional X-ray photon therapy, which deposits radiation along its entire path through the body and exits the other side, protons release most of their energy at a precise depth called the Bragg peak. You can tune that depth by adjusting the beam energy. This means less radiation to healthy tissue surrounding the cancer. That is the entire technical advantage. The trade-offs are significant, though.
I have been working with radiation oncology departments for over a decade, mostly on the planning and logistics side. The thing about proton therapy that nobody puts in the brochure is how finicky the case selection is. Not every tumor that looks like a good candidate actually benefits from protons over photons. There are scenarios where intensity-modulated radiation therapy (IMRT) with modern linacs performs virtually identically in terms of normal tissue sparing, particularly for larger, more diffuse targets. The dosimetric curve advantage of protons narrows dramatically when the tumor volume is greater than roughly 8 to 10 cubic centimeters with irregular margins.
Permanente Proton Therapy Access
Kaiser Permanente has operated proton therapy centers in a few locations, primarily in Colorado, Georgia, Hawaii, and Northern California. Access depends entirely on your plan tier, geographic region, and whether the treating physician obtains prior authorization. The referral pathway usually goes through your oncologist, who submits a coverage determination request to Kaiser's utilization management team. For members, the wait time for an initial consult at a proton center tends to run anywhere from three to eight weeks depending on regional capacity. Emergency or rapid-progression cases get prioritized, but elective re-irradiation cases sometimes sit in a lower queue.
The referral process itself is straightforward on paper. Your oncologist sends imaging and pathology records, the proton center's physics team reviews the treatment plan feasibility, and then a radiation oncologist schedules a consultation. What nobody tells you is that the consultation often includes a dedicated session with a medical physicist who will walk through the dose-volume histograms with you. Bring a notebook. Write down the numbers. Vagal nerve tolerance, spinal cord constraints, renal dose limits — these are not abstract concepts once you are in the chair.
The Treatment Workflow in Practice
A typical proton therapy course involves daily fractions over two to nine weeks. Each fraction lasts between fifteen and thirty minutes depending on the number of beam angles and whether you are using pencil-beam scanning or passive scattering. Pencil-beam scanning, which is the standard at most modern centers including Kaiser's, allows the beam to be magnetically steered point by point through the target volume. It produces sharper dose fall-off but requires more rigorous motion management.
Motion management is where things get interesting clinically. If your tumor moves with respiration — lung, liver, pancreatic — the center will typically use respiratory gating or breath-hold techniques. A common pitfall I see repeatedly is patients who do not practice the breath-hold properly before treatment begins. You will be asked to hold your breath for twenty to thirty seconds at a time, multiple times per session. If you cannot sustain that reliably, the delivery time doubles and the targeting accuracy drops. I had one patient, a man in his sixties with a hepatic lesion, who consistently broke his breath-hold mid-delivery. We switched him to a real-time tumor tracking system with fiducial markers, and that resolved the issue, but it added about forty-five minutes to each session and required a separate implant procedure.
The immobilization setup is usually a custom-molded thermoplastic mask or a vac-lok body cast. It feels clinical and impersonal, which it is. The mask is cut so you can breathe comfortably, but it does restrict head movement to within a millimeter. You will be positioned with laser alignment systems and verified with cone-beam CT before every single fraction. This is non-negotiable. Some centers skip the pre-treatment imaging on later fractions to save time, but I consider that a compromise I would not make for anything other than palliative cases.
Cost and Insurance Realities
The list price for a full proton therapy course in the United States typically ranges from eighty thousand to one hundred fifty thousand dollars. Insurance negotiated rates are substantially lower, but out-of-pocket exposure still exists in the form of co-insurance, deductibles, and non-covered ancillary services like daily parking or imaging performed at the proton center rather than your local hospital. Kaiser members on comprehensive plans generally face minimal direct costs, but those on limited-tier plans should verify coverage before committing.
A frequent misunderstanding is that proton therapy is automatically covered for any cancer diagnosis. It is not. Coverage is indication-specific. Pediatric solid tumors, certain skull base cancers, ocular melanomas, and re-irradiation scenarios have the strongest evidence base and the highest approval rates. For prostate cancer, coverage is more contested because multiple large randomized trials have shown comparable outcomes between proton therapy and modern photon IMRT. Your oncologist will need to articulate the clinical rationale during the prior authorization process. Documentation that addresses normal tissue sparing relative to your specific anatomy goes a long way.
Where Proton Therapy Falls Short
I want to be blunt about the limitations because the marketing material rarely is. Proton therapy is not superior for every cancer. The clinical evidence supporting protons over photons is strongest for pediatric malignancies, central nervous system tumors near critical structures, and re-irradiation cases where cumulative dose to normal tissue is the limiting factor. For many adult solid tumors — breast, prostate, early-stage lung — high-quality data does not demonstrate a meaningful overall survival advantage. The dosimetric benefit exists on paper, but translating that into clinical outcome is a different question.
There is also the geographic constraint. Proton centers are expensive to build and operate, so there are roughly eighty active facilities across the United States. If you live more than two hours from the nearest center, the daily commute over multiple weeks becomes a real burden. Family logistics, time off work, and sleep disruption are not trivial factors. I worked with a family in rural Arizona who drove three hours each way for six weeks. They ultimately switched to a photon-based SBRT protocol that achieved equivalent local control for their specific tumor type, and the total treatment span dropped from six weeks to five days.
Another limitation that gets overlooked is the availability of adaptive planning. Tumor shrinkage during a multi-week course can change the dose distribution significantly. Photon systems with online imaging adaptation can adjust on the fly. Proton systems can do this too, but it requires additional CT simulation sessions and physics recalibration that not all centers perform routinely. If your tumor is expected to shrink rapidly — lymphomas, germ cell tumors, some head and neck cancers — ask whether the center offers mid-course plan adaptation. If they do not, you may be delivering a suboptimal dose distribution for the second half of your treatment.
What to Ask Before You Commit
Get specific answers, not general reassurances. Ask about the treatment technique — pencil-beam scanning versus passive scattering. Ask about motion management protocols for your specific tumor site. Ask whether mid-treatment plan adaptation is available and under what circumstances it is triggered. Ask about the center's experience volume with your particular diagnosis. A center that treats fifty prostate cases per year is not the same as one that treats five hundred. Technique matters, and volume correlates with complication rates.
Also ask about the physics verification process. Every treatment plan undergoes independent dose calculation and pre-treatment quality assurance. Request to see the QA report. It will show measured versus calculated dose agreement, typically within a two percent tolerance. If the center cannot provide this documentation, that is a red flag regardless of how advanced their equipment appears.
Gallery Permanente Proton Therapy
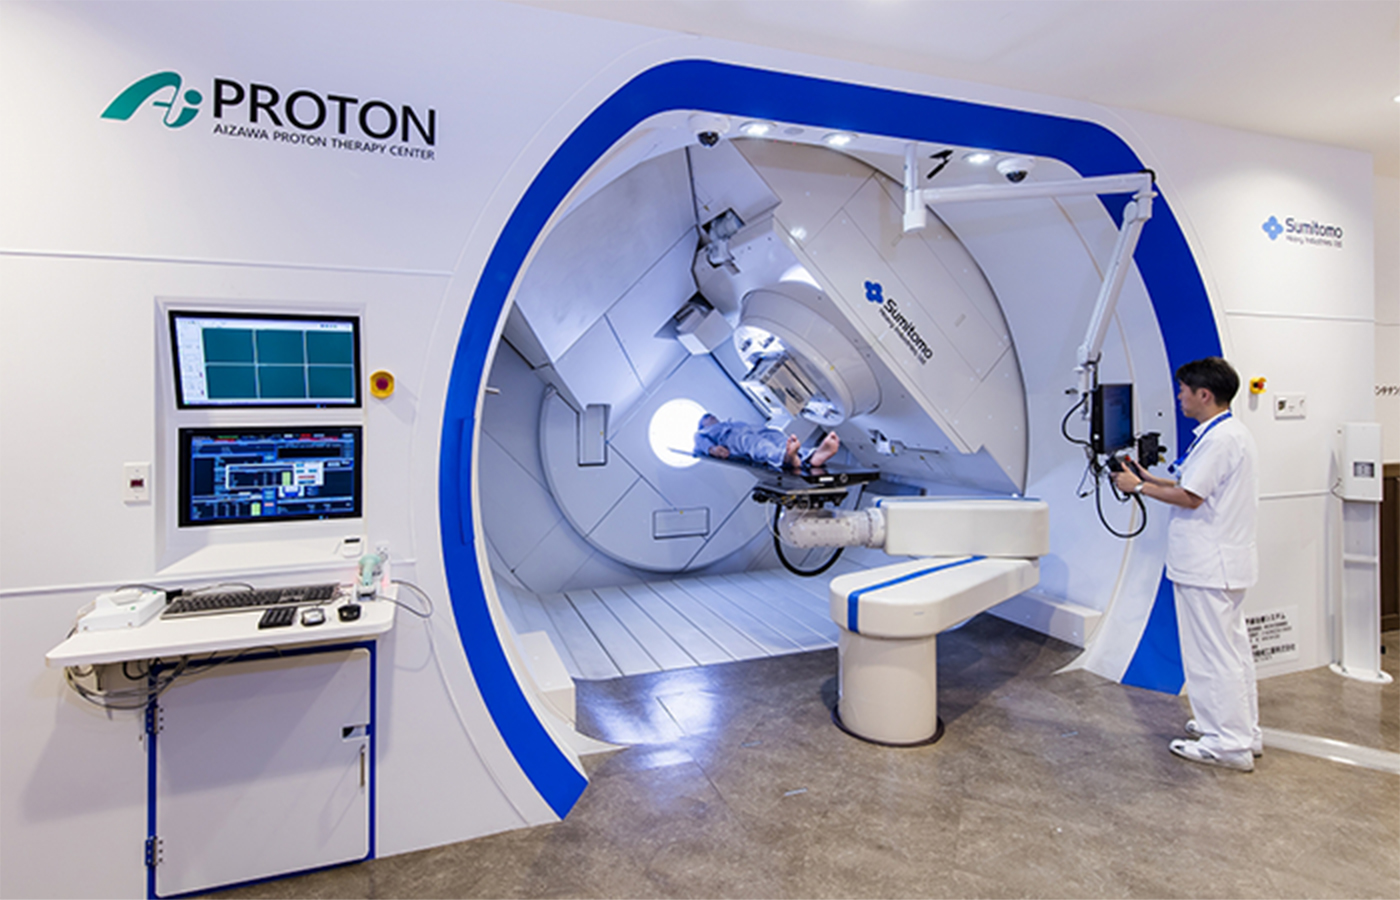
What is Proton Therapy? | MEDICAL | Sumitomo Heavy Industries, Ltd. Industrial Equipment Division
Proton Therapy in India | Cost, Hospitals and Outcomes
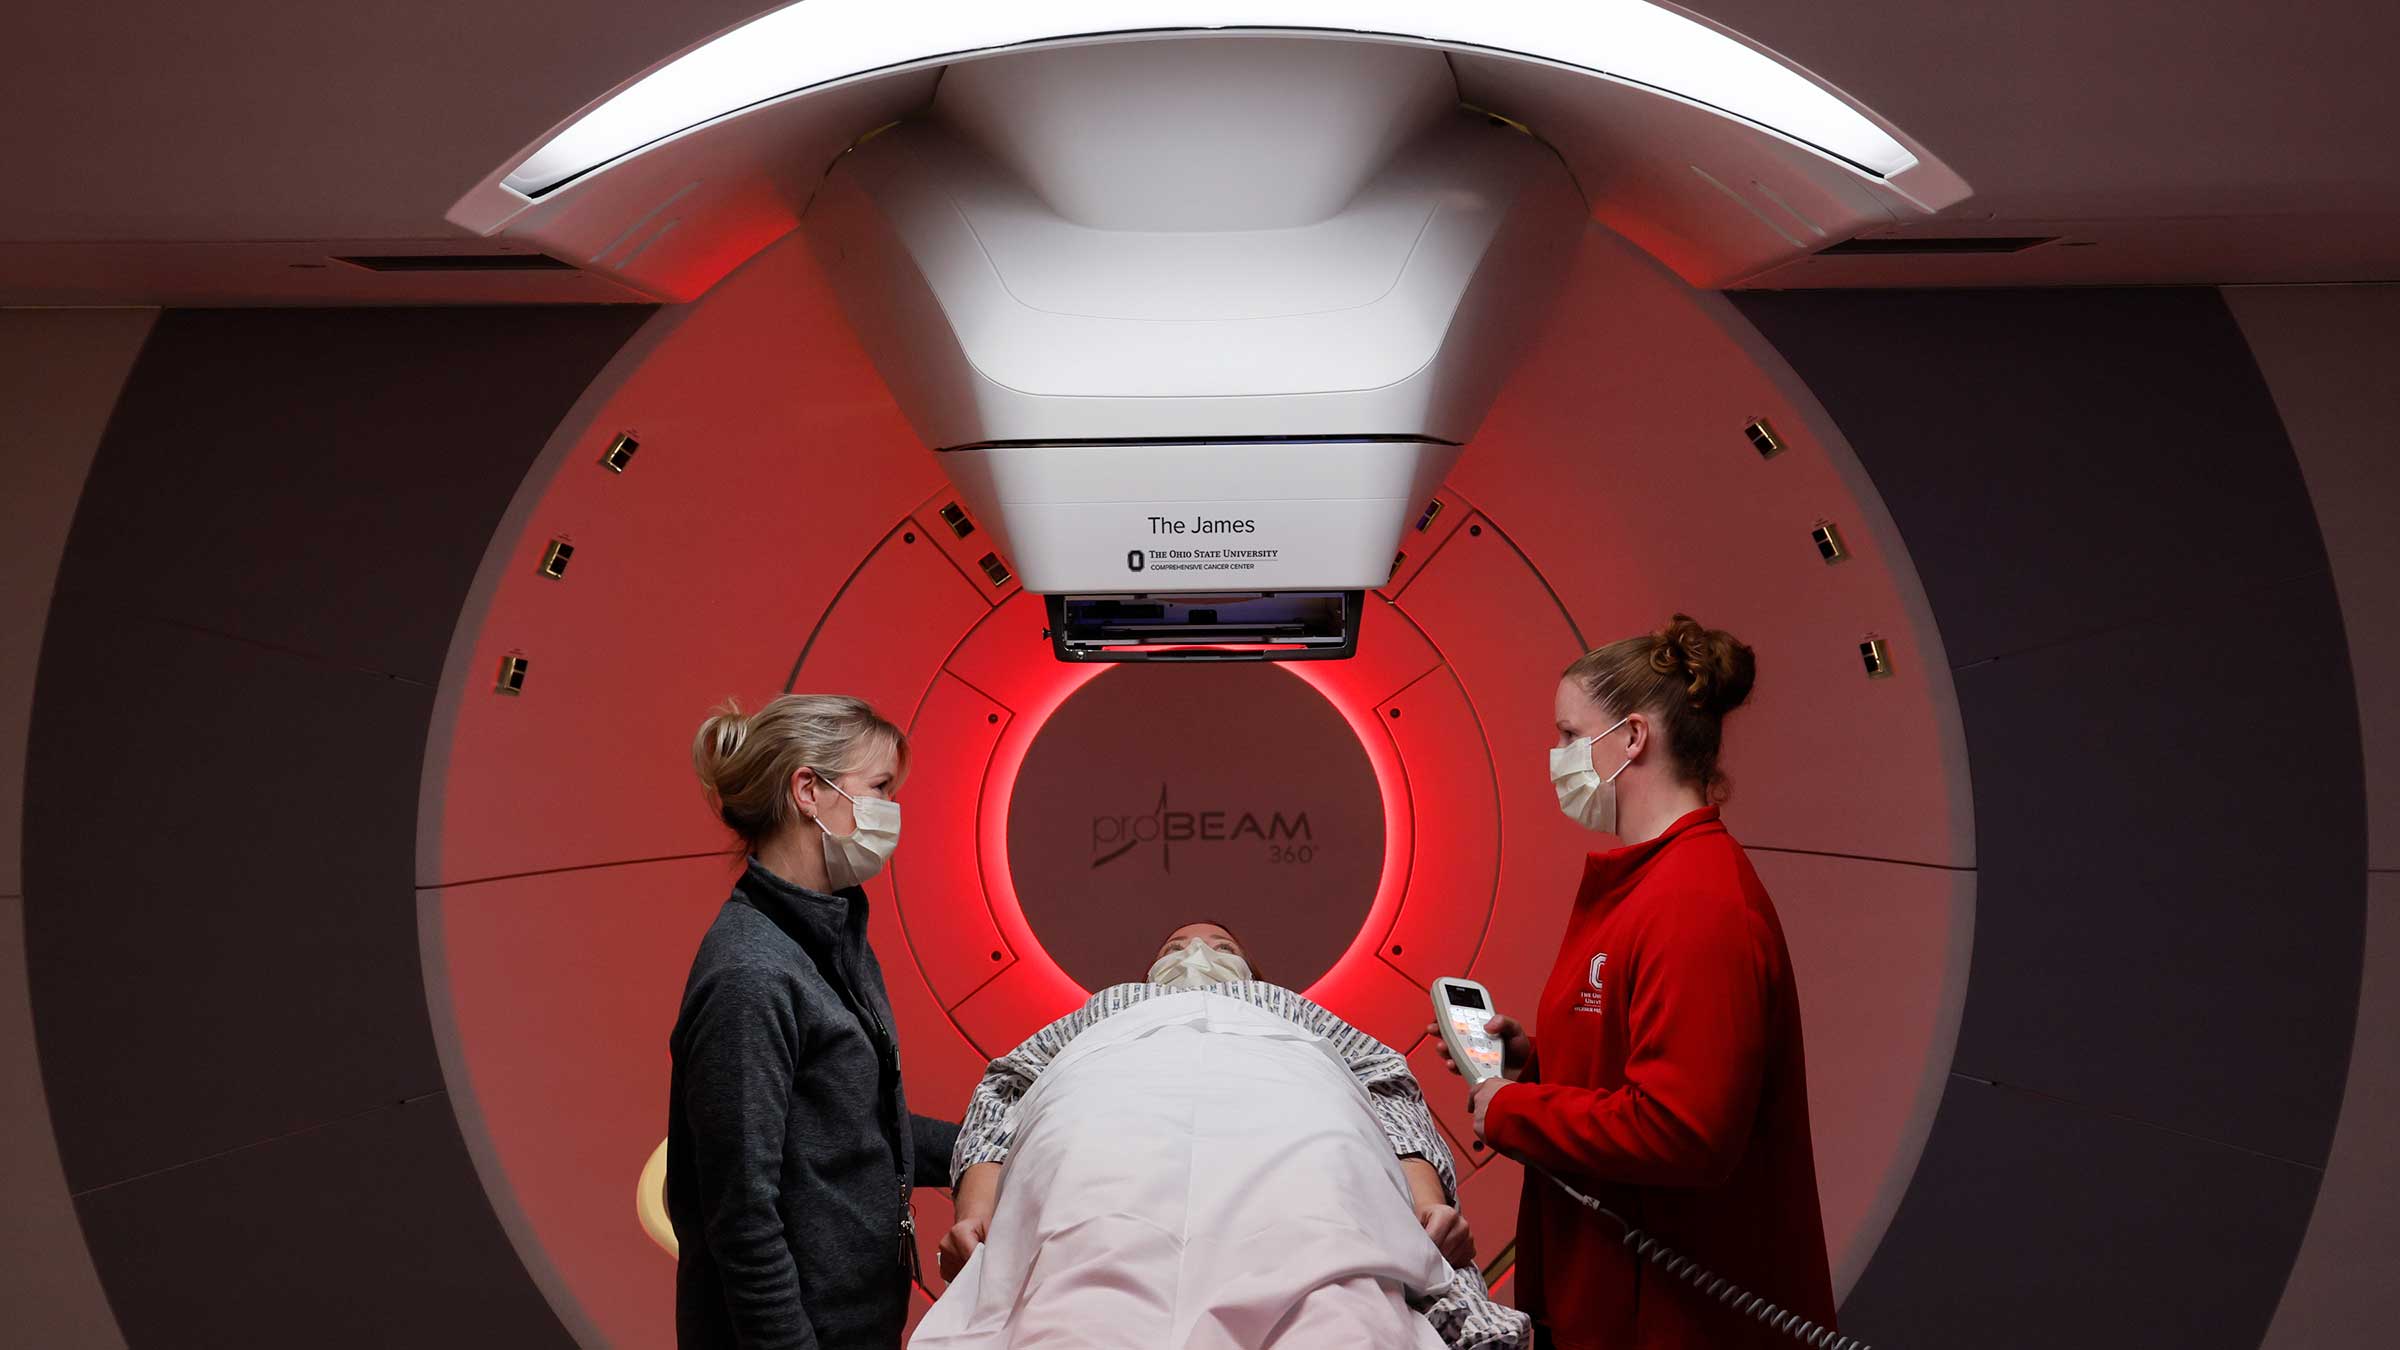
Proton radiation therapy fights thymic cancer | Ohio State Health & Discovery
Proton therapy accelerator: Patient on table surrounded by large medical device emitting bright ...
Proton Therapy | OSF HealthCare