
The Reality of Peroneal Tendonitis Recovery
Peroneal tendonitis doesn't heal on a schedule anyone can predict. The tendons run along the outside of your ankle, behind the lateral malleolus, and they take a beating from every step, every uneven surface, every time you roll your ankle slightly going down stairs. I've watched patients come in for months convinced that a specific stretch would fix it, only to find out the problem was load management, not flexibility. The tissue itself is often fine after a few weeks of relative rest. What isn't fine is its capacity to handle stress. There's a reason why so many people recover partially and then relapse. They feel better, they return to their normal routine, and the tendon flares up again within a week because they haven't rebuilt the structural tolerance. The exercises matter, but timing matters more. Doing eccentric work too early can set you back two to three weeks. Doing it too late just prolongs the whole process unnecessarily.
Peroneal Tendonitis Physical Therapy Exercises
Phase One: Isometric Holds (Days 1–7 roughly)
Start with isometrics because they provide pain relief through the gate control mechanism without demanding much from the tendon tissue itself. Sit down with your leg extended. Use your hand or a therapy band to resist inversion — that's moving your foot inward against resistance. Hold for thirty seconds at about seventy percent effort. Not maximum, not gentle. Solid, sustained tension. Do four reps, twice daily. Most patients report noticeable reduction in baseline ache within forty-eight hours of starting this. The tendon stays loaded enough to maintain some collagen alignment without being pushed into the painful range where microtears accumulate. I had a patient — marathon runner, late thirties — who came in convinced his issue was caused by tight calves. We did the full assessment and found his peroneals were barely firing at all. His posterior tibial tendon was doing all the stabilizing work. When we introduced the isometric inversion holds, his pain dropped significantly by day four. But the real breakthrough came when we added peroneal activation drills before any loading work, because his brain had essentially stopped recruiting those muscles. That disconnect between pain and dysfunction is something you see way more often than you'd think.
Phase Two: Controlled Eccentrics (Weeks 2–4)
Once the pain at rest drops below a three out of ten, you can introduce eccentrics. This is the phase most people rush through or skip entirely. Eccentric loading is what actually drives collagen realignment in the tendon. The classic exercise: sit with your leg extended, use your good foot to push the affected foot into inversion, then slowly — and I mean slowly, four to five seconds — let the affected foot evert back to neutral using only the peroneal muscles. Twelve reps, three sets, once daily. Progress to twice daily as tolerated. The mistake people make is going too fast on the lowering phase. A two-second descent doesn't create the same mechanical stress on the tendon collagen as a four-to-five-second one. You're essentially cheating the adaptation process. I also recommend doing this seated initially rather than standing, because standing introduces balance demands that shift load away from the peroneals and onto the smaller stabilizers. You want the peroneals doing the work, not your ankle's proprioceptive system compensating. Another thing nobody warns you about: the pain during eccentrics should stay at or below your baseline level. If it spikes above that during the set, you're already overloaded. Back off the resistance. A resistance band is fine, but don't default to weight until you can do the movement cleanly with body resistance alone. I've seen multiple patients add a dumbbell too early, push through a five out of ten pain spike, and then spend another three weeks starting over from phase one.
Get the Full Details

Phase Three: Load Progression (Weeks 4–8)
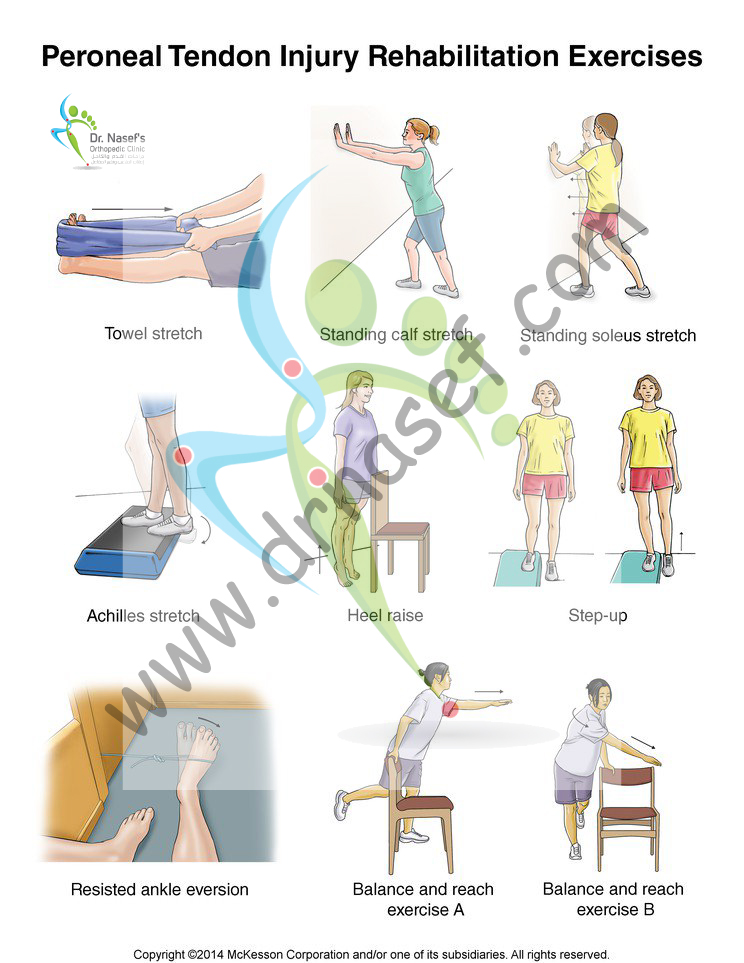
When you can complete the eccentric protocol with minimal discomfort, you move into progressive loading. Heel raises are the standard here, but the peroneal-specific version is what actually transfers to real-world function. Stand on the edge of a step with your feet parallel. Raise up on both feet, then shift your weight onto the affected side and lower slowly through a single-leg heel raise. The key detail most people miss: keep your big toe pressed down into the ground throughout the movement. This activates the peroneus longus, which runs under the foot, not just the peroneus brevis which is more superficial. Twelve to fifteen reps, three sets, every other day. Baltering surfaces matter here too. Start on flat ground. After about ten days of pain-free single-leg heel raises, move to a slight incline — a slant board or even a thick book under the front of your foot. The increased range of motion adds meaningful tension through a longer tendon stretch. Do not progress to uneven surfaces like foam pads or balance boards until you can do twenty clean single-leg heel raises on flat ground without next-day soreness. Uneven surface work too early reintroduces the instability that caused the tendonitis in the first place. There's a practical shortcut that saves a lot of frustration: ice the area for ten minutes after each session during the first two weeks of this phase. Not because inflammation is the primary problem — it's not — but because the mild analgesic effect lets you train more consistently. Missing two days of exercises because of a flare-up resets your adaptation clock more than people realize.
Phase Four: Sport-Specific Integration (Weeks 6–12)
This is where most rehab programs fail because they don't transition properly. Single-leg heel raises on flat ground won't prepare you for cutting, jumping, or running on irregular terrain. You need directional loading that mimics the actual stress patterns your sport or activity creates. For runners: start with straight-line jogging on a track or treadmill, three times per week, alternating with walking. Twenty minutes total, maximum. If there's no increase in next-day symptoms, add five minutes per session weekly. Side-to-side shuffling on a court surface comes after you can handle forty minutes of continuous jogging. Cutting and agility drills are the last thing you add, usually around week eight to ten for a straightforward case. Cutters and lateral-movement athletes get a different timeline. Sidestepping drills, carioca, lateral bounds — these load the peroneals differently than running does. Introduce them earlier, around week six, but at reduced intensity. A light resistance band around the thighs during lateral walks is a reasonable way to load the peroneals in the eversion plane without the impact forces that aggravate the tendon.
Common Pitfalls That Derail Recovery
Stretching the calf aggressively is one. Tight calves contribute to the problem indirectly by altering foot mechanics, but aggressive stretching of the peroneals themselves — especially the ball-of-the-foot stretch where you pull your toes toward your shin — can compress the tendon against the fibula and make things worse. Gentle calf stretching is fine. Peroneal stretching should be minimal and controlled. Another pitfall is ignoring the hip. The peroneals don't operate in isolation. Weak gluteus medius means your knee and ankle collapse inward during weight-bearing, which increases the load on the lateral ankle structures dramatically. A single set of banded side-lying hip abduction exercises at the start of your routine — twenty reps — takes thirty seconds and addresses a root cause that many people overlook for months. Footwear matters more than patients expect. A shoe with excessive rearfoot motion — anything with a soft, compressed midsole or a worn-out outsole on the lateral edge — removes the stability the peroneals are supposed to provide. During rehabilitation, you want a firm, stable base. After recovery, you can gradually reintroduce more flexible footwear, but doing so while the tendon is still adapting is a reliable way to prolong the process.
When the Standard Protocol Doesn't Work
Sometimes the exercises don't produce the expected results, and that's worth acknowledging plainly. About fifteen to twenty percent of chronic peroneal tendonitis cases don't respond to conservative management within twelve to sixteen weeks. In those cases, the issue is often a tendon tear that wasn't detected on initial imaging, a sinus tarsi syndrome masquerading as tendonitis, or nerve entrapment — the superficial peroneal nerve can refer pain to the same region and mimic tendon symptoms almost exactly. If you've been consistent with the protocol for six weeks and see absolutely no improvement in pain or function, get an MRI or a dynamic ultrasound. It's not a failure of the exercises. It's a signal that the diagnosis needs refinement. I had a patient who completed the full program three times over six months with no lasting improvement. The fourth visit included imaging that revealed a longitudinal tear in the peroneus brevis. Surgery and a modified rehab protocol resolved it in another four months. He'd have saved about three months of frustration with an earlier scan. The timeline I've outlined assumes a straightforward tendinopathy without tears, tenosynovitis, or subluxation. If you have any of those conditions, the protocol changes significantly and you should be working with a physical therapist or sports medicine physician rather than following a general guide. These exercises are a framework, not a substitute for a proper clinical assessment.


