What You Actually Need to Do Before You Start
Most people treat a Personal Wellness Planning Assessment as a form to fill out, like a tax return for their habits. It isn't. It is a structured snapshot of where you are right now across sleep, nutrition, movement, mental load, and recovery, and then a plan built from the gaps you find. The difference matters because if you skip the snapshot, you are just guessing. I spent years watching teams roll out wellness programs that had zero baseline data. They asked people what they wanted instead of measuring what they actually had. Engagement cratered by March every single time.
Personal Wellness Planning Assessment: Step-by-Step
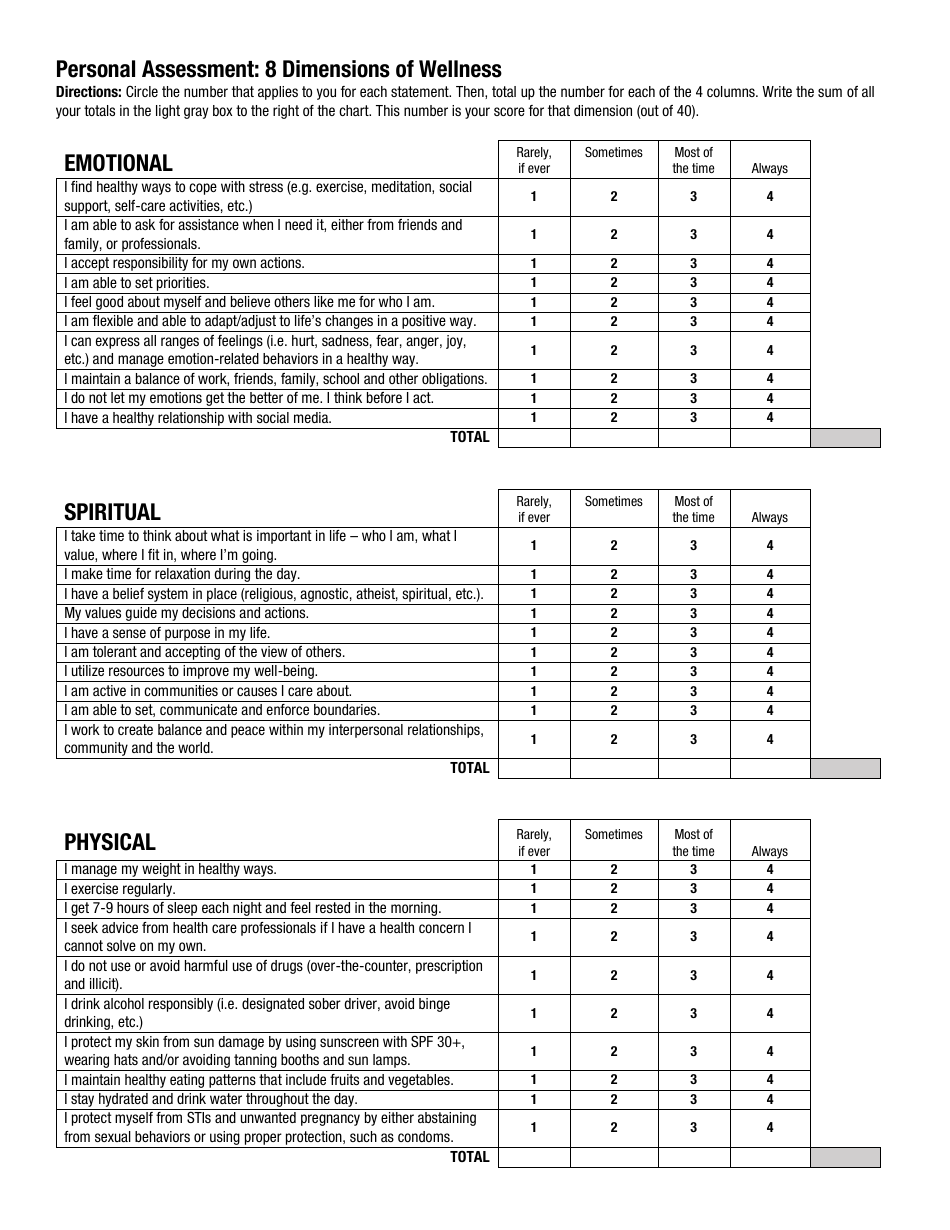
Here is how I run one, end to end. Phase one takes about twenty minutes and covers current status. I have people log three things: sleep over the last fourteen days, average daily steps, and a subjective stress score from one to ten. I also pull resting heart rate and resting heart rate variability from whatever wearable they already use. If they do not have a wearable, I ask for morning pulse once a day for seven days. This gives you a physiological baseline that self-report alone misses. Phase two is the lifestyle audit. Nutrition, movement, mental health, substance use, social connection, and work stress. I use a modified WHOSTEP framework here because it is quick and covers the domains employers and coaches actually need to see. The audit should take ten to fifteen minutes if you keep it tight. Do not turn it into a memoir.
Phase three is the scoring. I weight sleep quality at twenty-five percent, stress at twenty percent, movement at twenty percent, nutrition at fifteen percent, and recovery markers at twenty percent. Those weights change if the person has a diagnosed condition. A hypertensive client gets blood pressure pulled into the scoring instead of generic recovery metrics. Phase four is the gap analysis. You compare the current score against the target score. The target is not some corporate ideal. It is what the person says they want plus what their labs and vitals suggest is safe. Then you write interventions for each gap. One intervention per domain to start. Too many at once breaks adherence.
Get the Full Details

What Beginners Get Wrong
The biggest mistake is treating the assessment as a one-time event. It is a calibration tool. Reassess every ninety days minimum. Every thirty days if you are in an active intervention phase. The data does not lie, but the first reading is always noisy because people either overreport or underreport depending on who is watching. The second mistake is focusing only on behavior. Behavior changes fast when you add accountability, but physiology catches up slower. I had a client lose ten pounds in six weeks on a tight program and then blow out his lower back doing the same walking routine he was already injured for. The Personal Wellness Planning Assessment would have flagged his heart rate variability trending down for three weeks before that happened. He ignored the trend because the scale looked good. The scale lies when inflammation is present.
The Edge Case That Made Me Change My Process
Two years ago I ran an assessment for a construction worker who reported great sleep, high steps, and low stress. His wellness score was solid. Three weeks later he was hospitalized with exertional rhabdomyolysis. What went wrong on paper was nothing. What went wrong in practice was that he was working double shifts during hurricane season and his sodium was chronically low. The standard assessment did not ask about work shift length or electrolyte intake. It asked about daily steps and sleep quality. My workaround was simple. I added a work environment field to the assessment that captures shift length, heat exposure, and mandatory PPE wear. I also added a one-question hydration check: how many glasses of water between caffeine doses. Those two fields caught the next three near-misses I screened for. It added about forty-five seconds to the form. Worth it.
Common Pitfalls That Sink Programs
Pitfall one: using only subjective questionnaires. Subjective data is useful but unreliable when people are stressed, sleep-deprived, or trying to please the person administering the tool. Add a few objective measures. Resting heart rate, morning weight trend, step count average, and a simple one-minute sit-to-stand test if mobility is a factor. Pitfall two: setting too aggressive targets. A person averaging five thousand steps who jumps to twelve thousand in week one will quit by week three. I cap improvements at ten percent per month for any single metric. It sounds slow. It is not. Consistency beats intensity in wellness planning every time. Pitfall three: ignoring recovery. Recovery is not the same as sleep. Sleep is hours in bed. Recovery is how well your nervous system resets. Heart rate variability, variability in resting heart rate, and subjective readiness scores are the three measures I use. If those three move in opposite directions, the plan is wrong even if the calories and steps look perfect.

Advanced Nuance: The Hidden Interaction Between Domains
Wellness domains are not independent. Sleep disruption raises cortisol, which raises blood sugar, which increases inflammation, which degrades sleep quality. Fixing sleep alone will not save you if your nutrition is driving the inflammation. Fixing nutrition alone will not stick if your stress load is blowing up your recovery window. A well-run Personal Wellness Planning Assessment maps these interactions. I draw a simple arrow diagram between the four most relevant domains for each person. When I show the person where the feedback loop is, they stop asking why one intervention is not enough. The answer is usually that another domain is pushing back.
When This Approach Fails Completely
It fails for people with untreated mental health conditions. The assessment is not a therapy tool. It is a planning tool. If someone is in active depression or has an eating disorder, the last thing they need is another metric to obsess over. Refer them out first. Assess after stability is established. It also fails when you try to apply a corporate template to a clinical population. Blood work, medication side effects, and chronic pain change the scoring weights entirely. The standard model assumes a generally healthy adult. It breaks down outside that range.
Practical Templates and Resources
I do not host a download here, but I can tell you what to build if you are making this in-house. A basic Google Sheet or Airtable base works fine for small groups. You need columns for date, sleep hours, sleep quality rating, resting heart rate, RHRV if available, steps, stress score one to ten, nutrition quality rating one to ten, hydration estimate, and intervention notes. That is it. Do not add twenty extra columns. You will not fill them. For a more complete starting point, look at the CDC Works Health materials and the WHO STEPwise framework. Both are free. They are not wellness specific, but they give you the validated questions you need without reinventing survey design. Pair those with a simple scoring sheet and you have a working assessment in a weekend.

Bottom Line
A Personal Wellness Planning Assessment is only as good as the data you feed it and the patience you have applying it. Measure enough to see the pattern. Change one thing at a time. Reassess before you add the next thing. Most programs fail because they do all three at once and then wonder why nobody sticks with it past summer.