How the PAI Actually Works in Practice
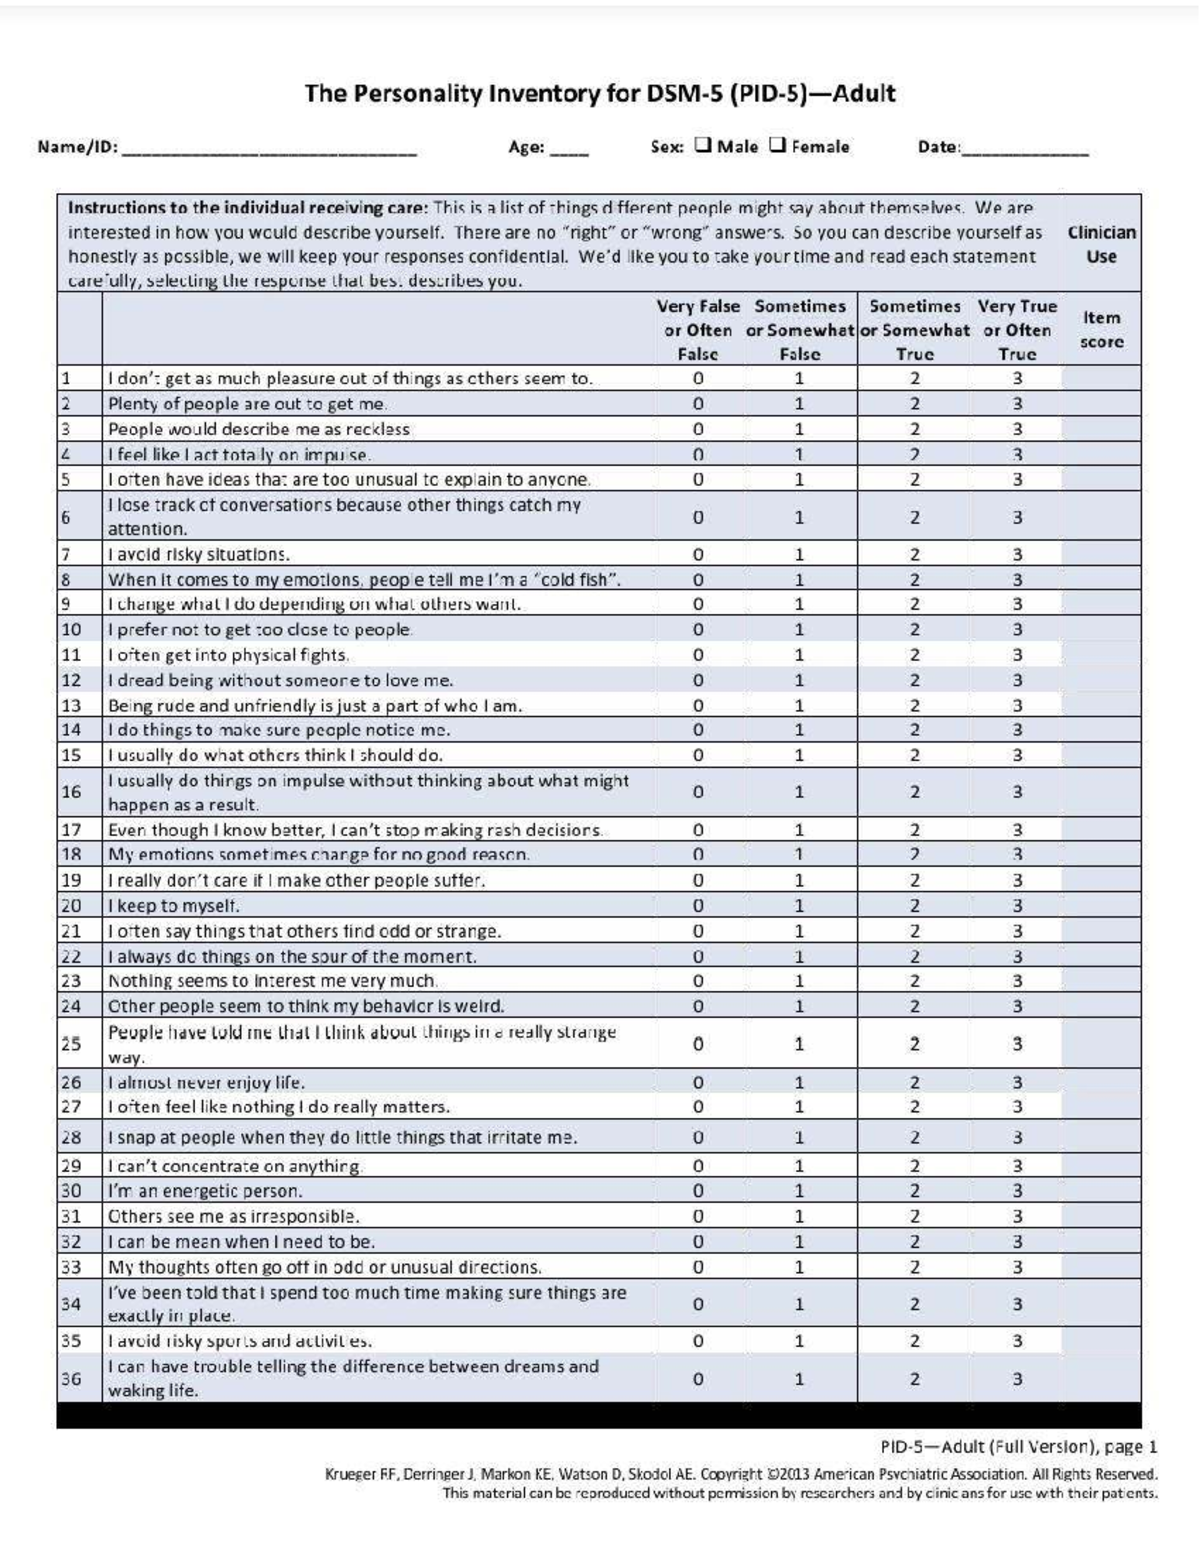
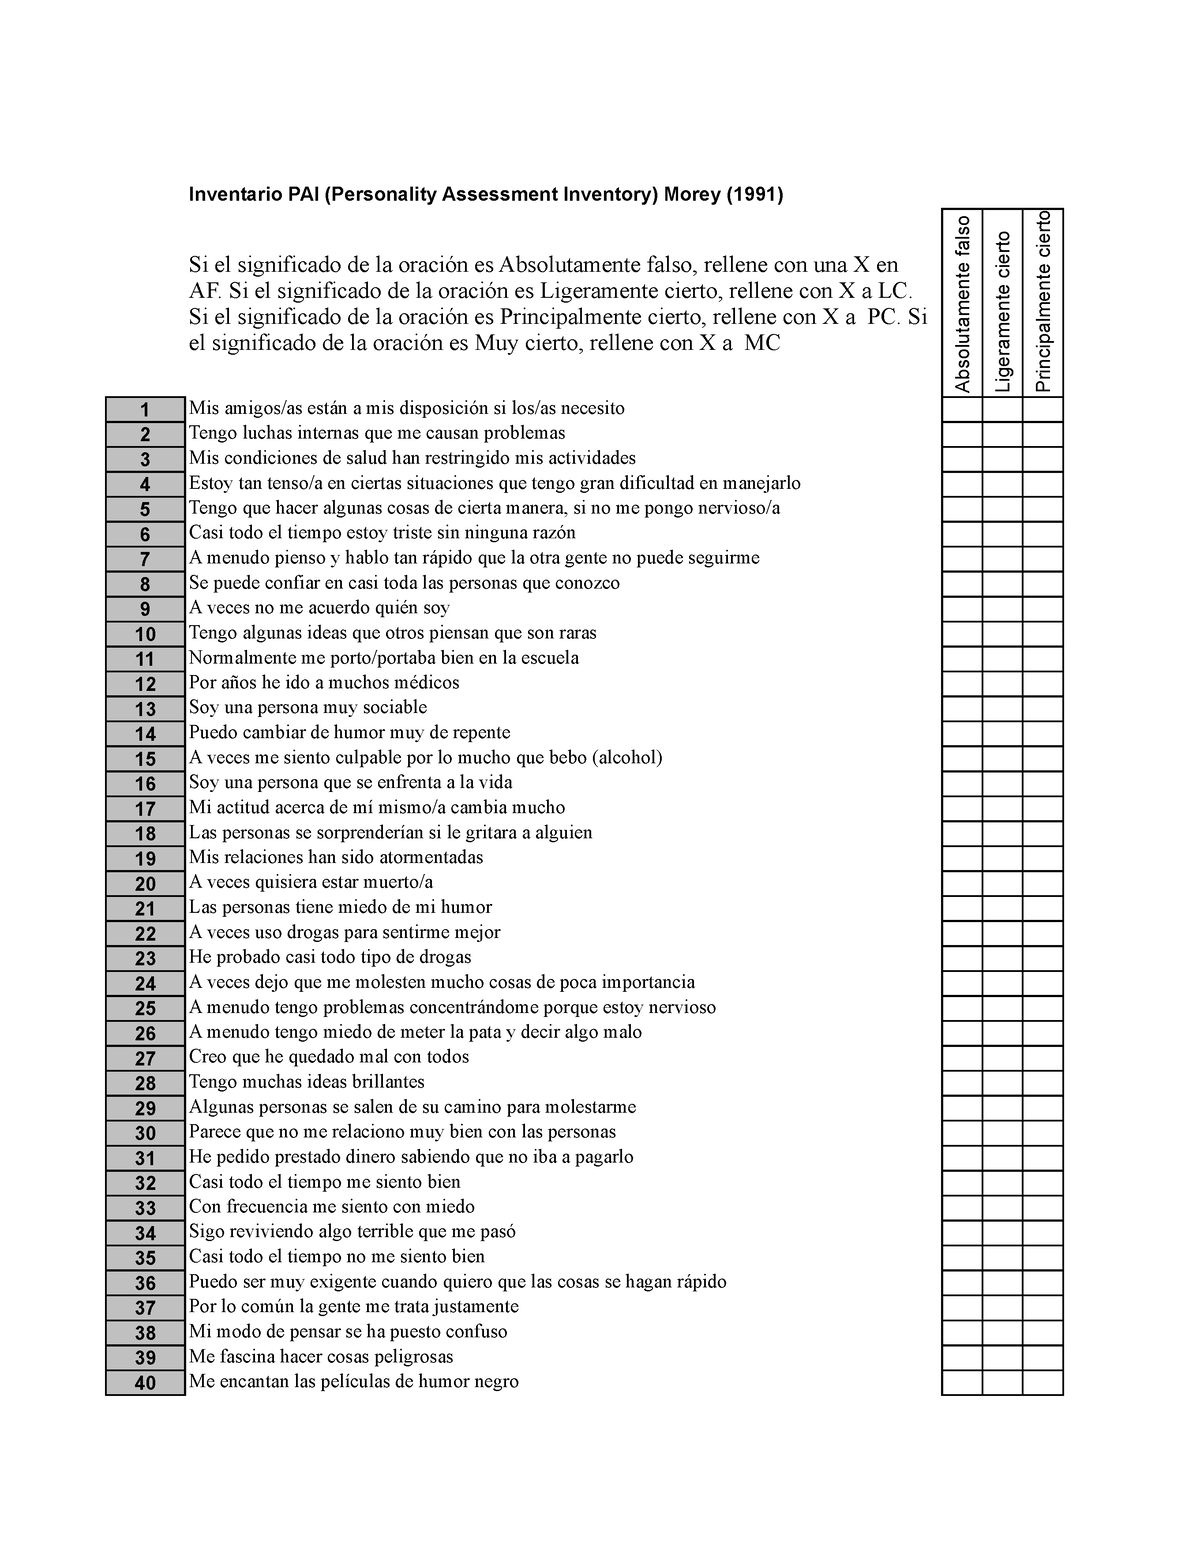
The Personality Assessment Inventory is a 344-item true/false questionnaire designed to assess psychopathology and personality characteristics. It was developed by Leslie Morey and published by Psychological Assessment Resources. Unlike many personality tests you see floating around, the PAI is strictly a clinical instrument. You need a qualifying degree in psychology or a related field to purchase it, and you definitely cannot just download free copies and start using them with clients. That said, understanding how it's structured and what the questions actually measure is useful for anyone working in mental health settings. The PAI breaks down into several domains. There are four infrequency scales, eight clinical scales, seven treatment orientation scales, and interpersonal scales, plus validity indicators. The clinical scales cover things like somatic concerns, anxiety, elevated excitement, dysphoria, paranoia, psychosis, mania, and antisocial features. Each scale has a set number of items mapped to it. For example, the NAE (Narcissism) scale has 16 items, while the ANX (Anxiety) scale pulls from 24 items across the inventory. A typical item looks like this: "I often feel worthless." You mark true or false. The scoring algorithm converts raw scores to T-scores with a mean of 50 and a standard deviation of 10. Scores above 70 are generally considered clinically significant, though the manual recommends interpreting profiles holistically rather than chasing cutoff scores in isolation.
Here is one practical issue I ran into. I was reviewing a PAI profile for a client who scored in the elevated range on nearly every clinical scale. On paper, this looked like severe multifaceted pathology. But the validity indices told a different story. The SVR (Variable Inconsistency) scale was elevated at 82, and the VRx (Random Responding) index was also flagged. This person was essentially clicking randomly or alternating between true and false in a patterned way. I had the test administrator re-administer the PAI with a strict instruction set, including a short practice block and explicit directions to answer honestly but thoughtfully. The second administration produced a clean validity profile and a clinically interpretable result. Random responding is far more common in forced-compliance settings, such as forensic evaluations, than most clinicians admit.
Understanding the Validity Scales First
Most beginners skip straight to the clinical scales and that is a mistake. The PAI has a built-in response style index called the IRI (Invalid Response Profile), which flags excessive infrequent responses. There is also the RX (Infrequent Self-Contradictory Items) scale, which detects inconsistent answering. These two are your first checkpoint. If the IRI is above 65, treat the entire profile with skepticism until you can confirm valid administration. I have seen cases where clients with legitimate conditions score high on IRI because they misread the instructions or genuinely struggle with the reading level of certain items. The PAI was normed on a broad population, but items like "I frequently experience inner tension" assume a certain vocabulary baseline. Another counter-intuitive thing about the PAI is how the positive impression scale, or POS, behaves. A low POS score does not automatically mean someone is trying to look bad. It means they endorsed relatively few positive self-descriptors, which can be entirely normal for depressed or dysphoric individuals. I once worked with a therapist who flagged a client for faking bad purely because POS was below 35, ignoring the fact that the client's dysphoria scale was also elevated, which is consistent with genuine depression. The scale exists to detect negative impression management, but you have to read it in context with the clinical data, not as a standalone red flag.
Get the Full Details

Where the PAI Falls Short
For all its utility, the PAI has real limitations. It takes about 45 to 60 minutes to complete, which is long for someone with attention difficulties or cognitive slowing. The reading level sits around a seventh-grade baseline, but some clinical populations still struggle with the abstract phrasing. There is no strong cultural adaptation beyond the original U.S. norming sample, so cross-cultural interpretations need caution. The manual itself notes that norms may not generalize well to non-English speaking populations or certain minority groups without supplementary clinical judgment. Another bottleneck is the cost. A full PAI kit with scoring software, manual, and record forms runs several hundred dollars, and you need to repurchase as needed. For solo practitioners or small clinics, this is a real barrier. Some people try to use older pirated versions of the test, which is both illegal and unethical. You risk invalid results and serious professional consequences. If budget is a constraint, consider the MCMI-IV for personality pathology screening or the MMPI-3 if you need broader psychopathology coverage, though both have their own trade-offs.
What the Scores Actually Mean
When you get a valid PAI back, the clinical scales give you a framework, not a diagnosis. The SCL (Scariness) and PAS (Parasuicide) scales are useful for risk assessment, particularly around self-harm history. The ALC (Alcohol Problems) and DRG (Drug Problems) scales pick up substance use patterns but cannot distinguish between misuse and dependence without additional clinical data. The APR (Antisocial Problems) scale flags conduct issues but has a known false-positive rate in justice-involved populations where some endorsement of rule-breaking attitudes is normative. The treatment orientation scales are where the PAI tends to shine. The THR (Treatment Readiness) scale predicts engagement likelihood, and the SUI (Suicidal Ideation) scale, despite sometimes being overlooked, has decent sensitivity for current suicidal thinking when combined with clinical interview data. I use the PAI primarily to supplement therapy intake, not to diagnose. It gives me a faster picture of comorbidity than a bare intake interview usually would, especially when a client minimizes symptoms or lacks insight into their own patterns.
Getting Legitimate Access to the PAI
If you are a qualified professional, you can purchase the PAI directly from PAR at pari.parinc.com. You will need to verify your credentials before the order goes through. The standard package includes the test booklets, record forms, and scoring software. There is no official free download. Any site offering a PDF of the actual items is distributing copyrighted material illegally, and the scores from unauthorized administrations are not defensible in clinical or legal contexts. If you are a student or researcher, contact PAR for academic pricing and check whether your institution already has a license that covers your needs.