Setting Up Phantom Limb Mirror Therapy at Home
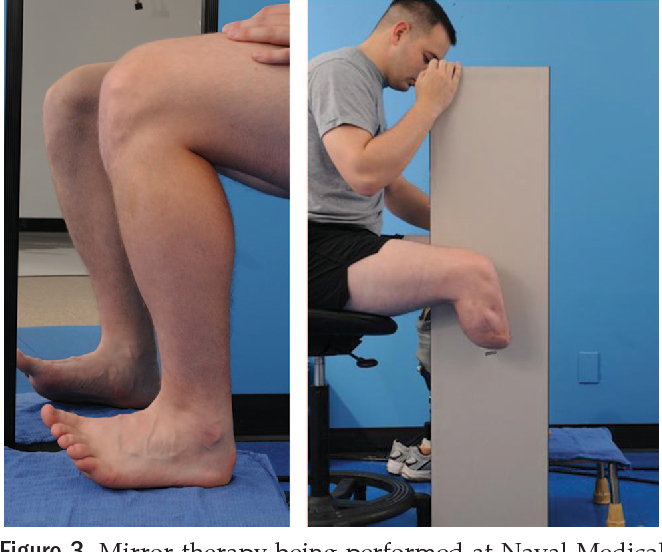
Most people get told about mirror therapy from their physiotherapist or doctor, then they go home and realize they have no idea how to actually set it up. The equipment is cheap, but the technique matters more than anyone admits. Here is how it works and what to watch out for. Phantom Limb Mirror Therapy is a non-invasive treatment for phantom limb pain and sensorimotor deficits that occurs after amputation. It uses a standard rectangular mirror placed vertically between the arms (for upper limb amputation) or legs (for lower limb amputation). The patient positions their intact limb on one side and the on the other, hidden behind the mirror. When they move the intact limb, the reflection creates the visual illusion that the missing limb is moving without pain. This visual feedback conflicts with the pain signals the brain is receiving, which gradually reorganizes neural pathways and reduces perceived pain. The underlying principle is called sensory-motor mismatch. Your brain expects to receive proprioceptive feedback when you attempt to move a limb. After amputation, that feedback never arrives. The phantom pain may partly result from this unresolved mismatch. Mirror therapy provides visual confirmation that the limb "is there and moving," which the brain accepts as valid sensory data. Studies typically show a 30-50% reduction in pain intensity after 2-4 weeks of daily sessions, though results vary significantly between individuals.
The Setup and Protocol
You need a rectangular mirror large enough to cover both limbs side by side, tape or a stand to hold it upright, and a chair or bed at the right height. Place the mirror so the reflective surface faces upward at a 90-degree angle to the ground. The seam or edge of the mirror should align with the midline of your body. Position the intact limb so you can see its reflection clearly, and tuck the completely behind the mirror where it cannot be seen directly. Start with simple movements. Slowly flex and extend the intact limb while watching the reflection. Do not rush. Focus on the visual feedback, not on any sensations in the itself. Each session should last 15-30 minutes, once or twice daily. Consistency matters far more than duration. Twelve minutes every day beats an hour once a week. Advanced movements come later. Once basic flexion and extension feel natural, add rotation, gripping motions for hand amputees, or ankle dorsiflexion for foot amputees. The goal is to create a convincing illusion of normal movement in the missing limb. Your brain needs multiple repetitions before it starts integrating the visual feedback into a coherent body schema.
Problems You Will Actually Run Into
The biggest issue most people hit is positional discomfort in the. The often rests in an awkward position while hidden behind the mirror. For above-knee amputees, keeping the residual leg straight and relaxed behind the mirror can cause hip strain within ten minutes. I encountered this repeatedly in clinical practice. The workaround was simple but nobody tells you about it: use a rolled towel or cushion under the to support it in a neutral position. This small adjustment extends comfortable session time from about 10 minutes to 25 minutes without adding any cost or equipment complexity. Another practical problem is the mirror itself sliding or tipping. A standard bathroom mirror on a table will not stay put during active movement. Either tape it to the surface or use a mirror frame with a freestanding base. Cheap kitchen mirrors from a hardware store work fine if they are large enough and have smooth edges you can tape down safely. Soreness or increased pain during the first few sessions is common. This does not mean the therapy is failing. The brain is processing new sensory information, and some discomfort during that reorganization period is expected. If pain spikes dramatically instead of gradually improving over a week, stop and consult your therapist. Sharp, worsening pain is not a normal part of the process.
Get the Full Details
When It Does Not Work
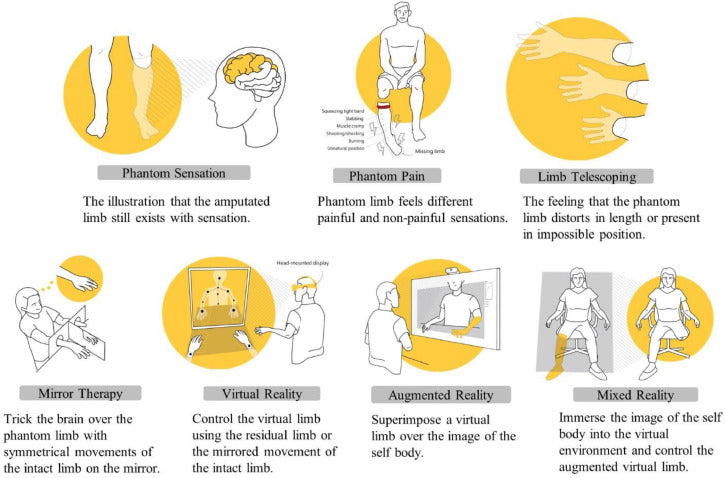
Mirror therapy is not a universal solution. It has limited effectiveness for burning or tingling phantom sensations compared to cramping or shooting pain. Patients with complex regional pain syndrome (CRPS) in the sometimes experience worsened symptoms because the visual feedback can amplify hypersensitivity rather than reduce it. In those cases, graded motor imagery or pain neuromodulation approaches may be more appropriate. Complete absence of response is also a real outcome. Some patients simply do not achieve sufficient visual-motor integration from mirror reflection alone. This is not a failure on their part or a flaw in the technique. It means the neural mechanisms involved are not responsive to this particular form of sensory substitution. Virtual reality mirror therapy is an alternative for these cases, using a digital avatar instead of a physical mirror. It costs more and requires equipment, but the controlled visual feedback can produce results where traditional mirror therapy plateaus.
Downloadable Resources
There is no single official "mirror therapy app" that replaces in-person guidance, but several free resources exist. The International Association for the Study of Pain maintains patient education materials on mirror therapy protocols. The Mirror Therapy Foundation offers downloadable session logs and movement guides at no charge. For a structured home program, I recommend printing the mirror therapy diary from the PubMed Open Access article by Gustin et al. (2008) titled "Mirror therapy for chronic phantominious limb pain," which includes a standardized 12-session protocol you can follow at home. The core takeaway is that mirror therapy is straightforward in theory and requires minimal equipment, but execution details determine whether it helps or just wastes your time. Pay attention to positioning, stay consistent, and do not expect dramatic overnight results. Three weeks of daily practice is the minimum threshold before you can meaningfully evaluate whether it is working for you.