
The Problem With Teaching Dosage Math
Most programs teach it backwards. They hand you a dimensional analysis worksheet, drill you through ten clean problems where everything cancels perfectly, and then you go to your first clinical shift where nothing is clean. A pediatric dose needs to be drawn up from a concentration that comes in a brown glass vial because it's light-sensitive. The order says "titrate to effect" and you are supposed to figure out what that means in mL/hr when the pump won't accept decimals smaller than 0.1. The worksheet never covered that. I learned the hard way on a med-surg floor about three months into my first job. We had a order for dopamine at 5 mcg/kg/min for a post-op patient who was 82 kilograms. The pharmacy sent down an admixed bag: 400 mg in 250 mL D5W. Straightforward enough until the attending asked me to change the rate to 8 mcg/kg/min and then asked again two minutes later when the patient's blood pressure didn't move. I had recalculated twice and gotten different numbers. Turns out I used 80 kg instead of 82 on the second pass. You can see how easy it is to make that error when you're working through it in your head while watching an infusion pump.
Pharmacology Dosage Calculations For Nurses
At its core, this is the practice of converting a physician's ordered dose into the volume or count you actually administer, while accounting for patient-specific factors like weight, renal function, and concentration. The math itself is usually basic algebra and ratios. The difficulty comes from the layering of real-world constraints on top of it. There are three main methods you will encounter in training and on the job, and they each have trade-offs that nobody really discusses openly.
Method One: Dimensional Analysis
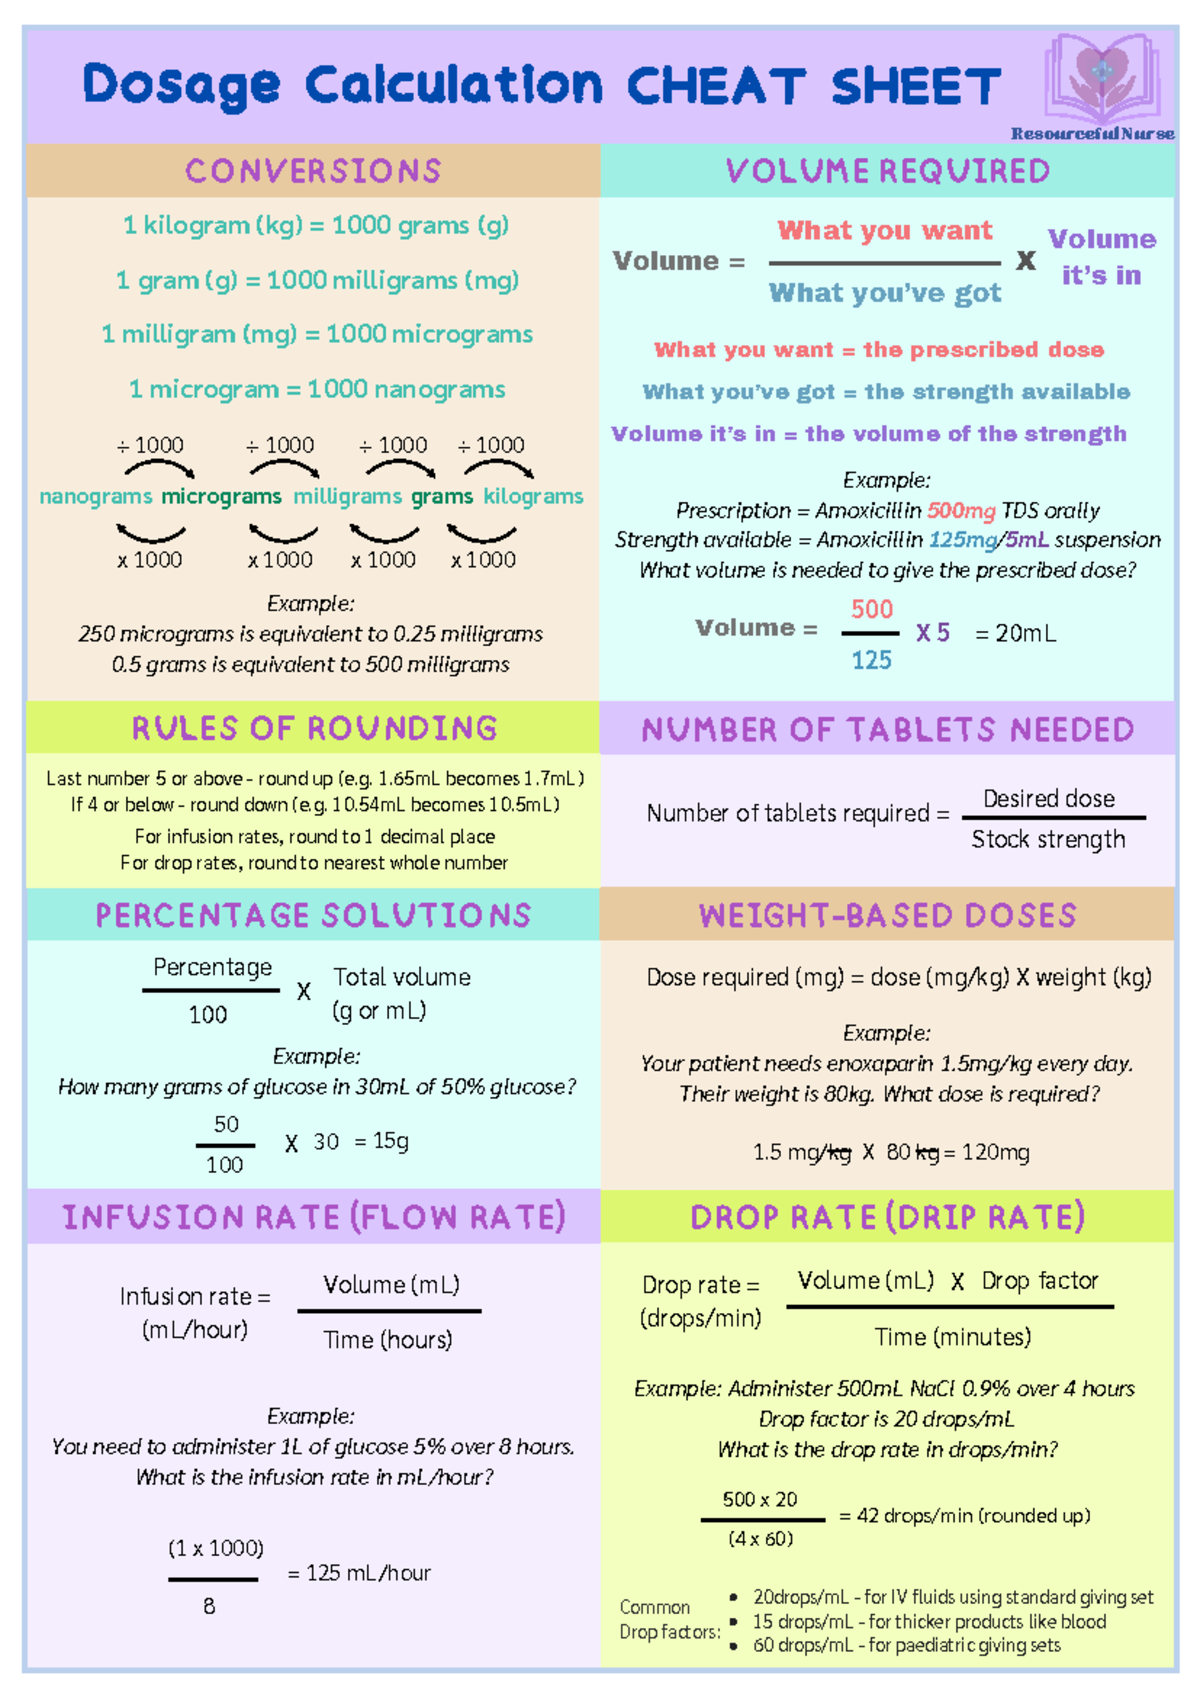
This is the most widely taught method in nursing programs right now. You set up a chain of fractions so that every unwanted unit cancels out, leaving only the unit you need — typically mL, tabs, or drops per minute. The setup looks like this for a basic oral dose: Order: Amoxicillin 500 mg PO every 8 hours.
Supply: Amoxicillin suspension 250 mg per 5 mL. Set it up as: (5 mL / 250 mg) × (500 mg / 1 dose) = 10 mL per dose.
The mg cancels. You are left with mL. It works cleanly when the numbers cooperate. Where dimensional analysis gets ugly is with continuous infusions involving weight-based dosing. Take that dopamine example again. You need to get from mcg/kg/min to mL/hr. That requires three conversion steps in one chain: mcg/kg/min × kg × min/hr × mL/mcg = mL/hr
Write it out fully: (50 mcg / kg / min) × (82 kg) × (60 min / 1 hr) × (250 mL / 400,000 mcg) = 15.375 mL/hr Round to 15.4 mL/hr on your pump. The kg cancels. The min cancels. You are left with mL/hr. If any of those conversions are wrong — and 400 mg equals 400,000 mcg, not 40,000 — your patient gets ten times the intended dose. I have seen that exact error happen. Not by a stranger. By a nurse who was pulled off the line to cover a bedside that wasn't theirs.
Get the Full Details
Method Two: The Formula Method
This is the classic D over H times Q approach. D is the desired dose. H is what you have on hand. Q is the quantity that contains H. The formula is (D / H) × Q = X, where X is what you administer. Using the same amoxicillin order: (500 mg / 250 mg) × 5 mL = 10 mL. It is faster to write and faster to think through than dimensional analysis once it is internalized. But it breaks down completely when you hit multi-step problems like IV drips, and that is exactly the point where nurses are expected to perform. Formula method will not get you from mcg/kg/min to mL/hr in one shot. You have to know when to abandon it and switch tools. Most programs don't emphasize that transition.
Method Three: Ratio and Proportion
This is the oldest method and the one that hospital math review courses tend to fall back on. You set up two ratios and solve for the unknown. The supply ratio goes on one side, the order ratio on the other: 250 mg / 5 mL = 500 mg / X mL Cross multiply: 250X = 2500. X = 10 mL.
It works fine for single-step oral and IM calculations. For titratable IV drips, you end up doing the same intermediate conversions either way, so ratio and proportion just adds an extra step without giving you anything dimensional analysis doesn't already do.
What Nobody Tells You About Concentration Conversions
Here is a counter-intuitive thing that catches people every single rotation: percentage concentrations are not a separate category. They are just a different way of writing a ratio. A 1% solution means 1 gram per 100 mL. A 0.9% sodium chloride solution is 0.9 grams per 100 mL, which is 9 grams per liter, which is 9,000 mg per liter. When you are calculating a drip and the order gives you a percentage concentration rather than a straight mg/mL label, you need to convert that percentage yourself before you can set up any of the three methods above. Epinephrine 1:1000 is another classic trap. That notation means 1 gram of epinephrine in 1000 mL of solution. That equals 1 mg per mL. Epinephrine 1:10,000 means 1 gram in 10,000 mL, or 0.1 mg per mL. Cardiac arrest code crews mix these up routinely because they look similar and the math is trivial if you take thirty seconds to write it out. It is not trivial if you do not write it out.
Insulin and Heparin Are in a League Of Their Own
Units are not milligrams. You cannot convert between them without a specific product's conversion factor, and that factor varies by manufacturer and by concentration. Insulin U-100 means 100 units per mL. Insulin U-500 means 500 units per mL. They look identical in a syringe until you read the label. Using a U-500 vial with a U-100 calculation gives you five times the intended dose. Heparin comes in 1,000 units/mL, 5,000 units/mL, and 10,000 units/mL vials. The math for a weight-based heparin bolus is simple — it is the concentration identification that kills people. My workaround for this on the floor was to keep a small reference card in my pocket with the common insulin and heparin concentrations and their mg-equivalents where applicable. Not because the math is hard. Because the cognitive load of a busy shift makes it too easy to assume a vial is one thing when it is another. The card costs me nothing and it has prevented three near-misses in five years.

Pediatric Calculations Add a Layer Most People Underestimate
Pediatric dosing is almost always weight-based, and the margin for error shrinks dramatically as the patient's weight drops. A 0.5 mL error on a 70 kg adult is negligible. A 0.5 mL error on a 5 kg infant is a meaningful fraction of the dose. This is why pediatric pumps often require double verification by a second nurse and why many institutions mandate that all pediatric IV medications be prepared by pharmacy rather than at the bedside. When I was covering a pediatric float shift, I ran into a vancomycin order calculated by weight at 15 mg/kg for a 7.2 kg neonate. The pharmacy supplied vancomycin 50 mg/mL in 2 mL vials. The math said 2.16 mL. The smallest gradation on a 3 mL syringe is 0.1 mL. I could not draw up 2.16 with any accuracy using standard equipment. I had to go back to the attending, explain the measurement limitation, and we adjusted the order to 2.2 mL and split the infusion over a longer dwell time. The dosage was technically approximate, but it was the most accurate I could deliver with the tools available. This is the kind of edge case that exists constantly in pediatrics and never appears on the exam.
Renal Dosing and Why Your Math Changes
Pharmacology Dosage Calculations For Nurses is not purely mathematical when the patient has impaired renal or hepatic function. Some drug orders include a built-in adjustment factor based on creatinine clearance. The order might say "reduce dose by 50% if CrCl
30." You do not calculate the CrCl yourself in most cases — the pharmacy does that and prints it on the label. But you need to recognize when an order has been adjusted and verify that the adjusted dose matches what the pharmacy prepared. I caught one instance where the pharmacy adjusted a gentamicin dose for renal function but the physician's original order and the pharmacy's adjusted order were filed separately and the nurse who picked up the med ran both through the pump. The patient received a full dose on top of the reduced dose. The double-ordering happened because the two documents looked independent. Flagging adjusted doses with a colored sticker on the med sheet would have made the duplication obvious in three seconds.
IV Pump Limitations You Need To Plan Around
Most modern infusion pumps accept rates to one decimal place in mL/hr. Some accept two. None accept three. This means your calculated rate sometimes needs to be rounded to what the pump can actually display, and you need to know when that rounding is clinically acceptable and when it is not. For most medications, rounding a rate within 5 percent of the calculated value is considered acceptable practice. A rate of 15.4 mL/hr rounded to 15 mL/hr is a 2.6 percent difference. That is fine. A rate of 4.6 mL/hr rounded to 5 mL/hr is a 8.7 percent difference. That crosses the typical acceptability threshold for narrow-therapeutic-index drugs like vasopressors and insulin drips. In those cases, you recalculate the concentration — dilute or concentrate the bag so that the desired mL/hr lands on a number the pump can display accurately. This is called rate optimization and it is something every nurse should know how to do. It usually takes about five minutes to work through and it eliminates a whole class of rounding errors. I teach it to new grad hires during orientation and I wish I had known to ask for it when I was one.
Drop Factor Calculations Are Mostly Historical Now
You will still see them on exams and occasionally on older unit formularies. Manual IV sets use drop factors measured in drops per mL. Macrodrop sets are typically 10, 15, or 20 gtt/mL. Microdrop or administration tubing is 60 gtt/mL. To convert mL/hr to gtt/min, you divide the drop factor by 60 and multiply by the mL/hr rate. With a 10 gtt/mL set, that divisor is 0.167. With a 60 gtt/mL set, it is exactly 1, which is why microdrop sets are easier to calculate by hand. The practical reality is that almost no unit uses gravity-driven IVs anymore. If you are calculating drop factors, it is for an exam or for a situation where pump tubing is unavailable. Know the math for the test. Do not let it distract you from mastering the concentration conversion and rate optimization skills that matter on the floor.
A Practical Workflow That Actually Works
Here is the process I use every single shift, and it has not failed me in twelve years: Read the order. Identify the drug, the dose, the route, and any special instructions like titration or renal adjustment. Check the label. Confirm the concentration, the total volume, and the expiration. If the concentration is unusual — like a high-alert medication in a non-standard strength — flag it immediately.
Do the calculation on paper or in a notes app, not in your head. Write out every step. Show your units cancelling. This takes roughly forty-five seconds for a standard oral dose and two to three minutes for a weight-based IV drip. Verify. Use a second method or a calculator app to cross-check. Many hospitals have an IV app or a dedicated med math tool approved by the formulary committee. Using one is not cheating. It is standard practice. Round appropriately based on pump capability and clinical acceptability. Document the final rate.
Set the pump and verify the programmed rate against your calculation one more time before you hang the bag.
Where These Methods Completely Fail
Dimensional analysis, formula method, and ratio-proportion all assume that the order and the supply use compatible units. They fail when the order is written in a unit system that the label does not reflect directly. This happens frequently with compounded medications, extemporaneously prepared doses, and hospital-specific admixtures that do not follow commercial labeling conventions. In those situations, the only reliable method is to request a pharmacy verification before administering. No amount of personal calculation competence substitutes for a certified pharmacist confirming a non-standard concentration. I have seen nurses attempt to reverse-engineer a compounded suspension's concentration from partial information on a label and come up with a number that was close but wrong. The patient received approximately eighty percent of the intended dose. The order was for a narrow-margin antibiotic and the subtherapeutic dosing contributed to treatment failure that required a second-line agent with more side effects. The fix was to call pharmacy and ask them to re-label the container with an explicit mg/mL statement.
Bonus: Reference Charts You Should Keep Handy
Common conversions that appear in dosage calculations repeatedly and that you should memorize rather than look up under pressure: 1 gram = 1,000 milligrams = 1,000,000 micrograms 1 kilogram = 2.2 pounds
1 teaspoon = 5 mL 1 tablespoon = 15 mL 1 ounce = 30 mL
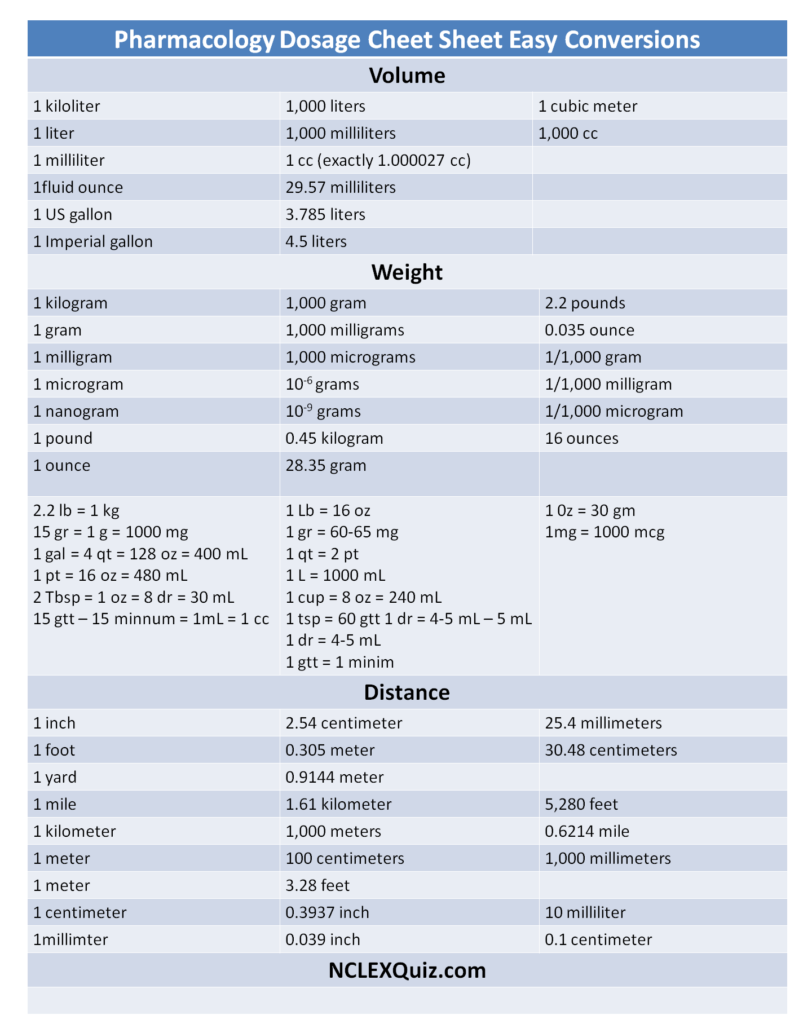
Normal saline is 0.9% = 9 mg/mL = 9,000 mcg/mL D5W is 5% dextrose = 50 mg/mL Lidocaine 1% = 10 mg/mL
Lidocaine 2% = 20 mg/mL Epinephrine 1:1,000 = 1 mg/mL Epinephrine 1:10,000 = 0.1 mg/mL
Atropine 0.4 mg/mL is the standard adult dose vial. Atropine 0.1 mg/mL exists for pediatric use and they are not interchangeable. Memorizing these cuts your calculation time down significantly because you are not stopping to convert units mid-problem. A typical weight-based drip calculation goes from three minutes to about forty-five seconds once the conversions are automatic. That sounds small. On a shift with twenty med passes and three titratable drips, it adds up to twenty minutes of saved time and far fewer errors from rushed last-step conversions.
Final Note on Practice Resources
If you want problem sets that match what you actually encounter, skip the generic math worksheets and look for resources from the ANA or your state nurse association's continuing education portals. Some hospital systems also publish internal dosage calculation guides that include their approved rounding policies and pump-compatible rate ranges. Those documents are more practically useful than any textbook chapter because they reflect the actual equipment and protocols you will be using on the unit.

