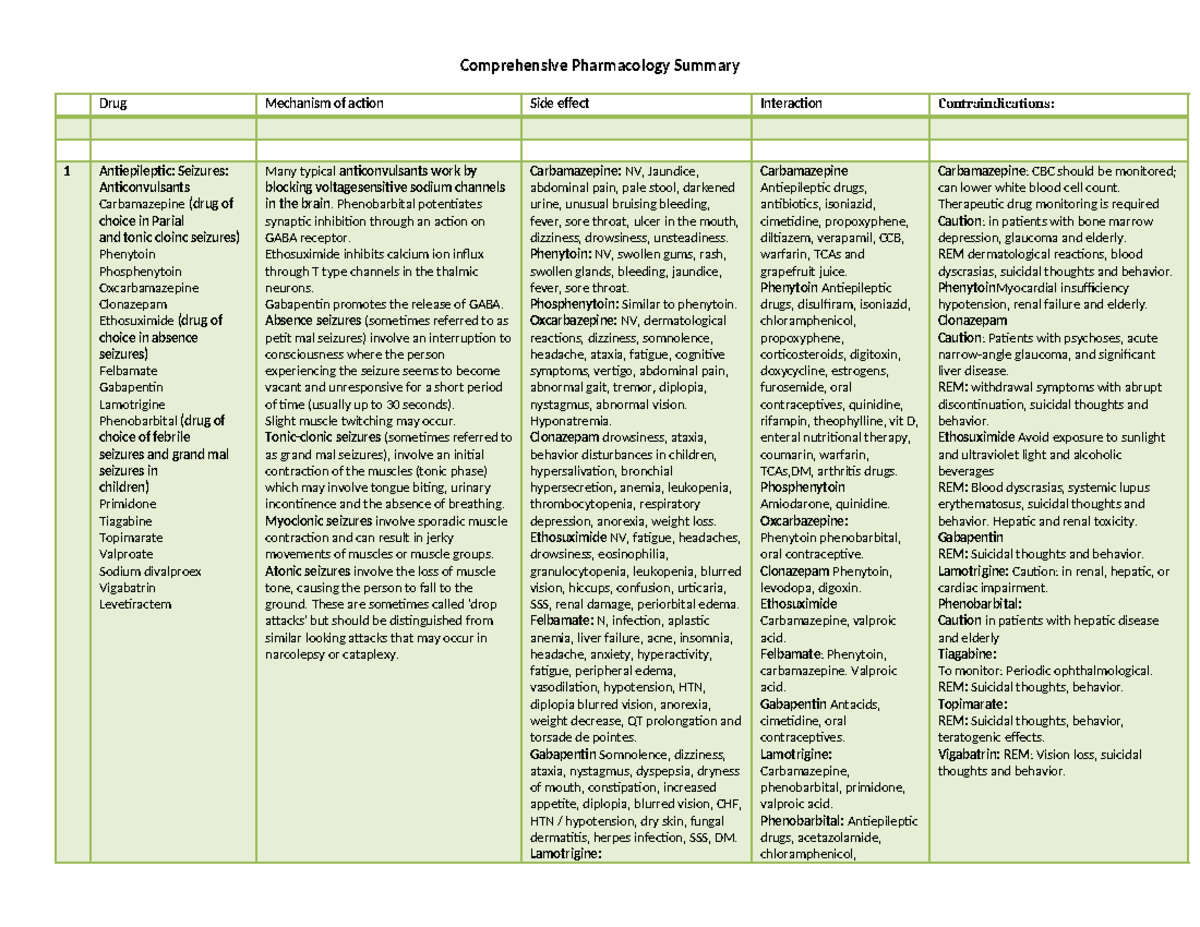
How to Actually Use Pharmacology Examples Comprehensive for Studying
Most students waste weeks going through pharmacology decks without retaining anything because they're studying the wrong layer of information. A Pharmacology Examples Comprehensive resource is only useful if you understand how to mine it for clinical reasoning patterns rather than just memorizing drug names and doses. I spent three years building and refining pharmacology teaching materials across multiple rotations before I stopped seeing students crash and burn on the same questions every exam cycle. The pattern was always the same: they knew the mechanisms but couldn't apply them to a patient scenario. That gap is exactly what a well-structured comprehensive examples document is supposed to close.
What a Pharmacology Examples Comprehensive Actually Covers
A proper comprehensive pharmacology examples set isn't just a list of drugs. It organizes information by clinical presentation first, then maps mechanisms and interventions onto that framework. You'll find sections covering cardiovascular drugs, CNS medications, antimicrobials, endocrine agents, and the usual suspects, but the value comes from how each drug is contextualized within a case vignette. The format typically looks like this: patient case, presenting symptoms, first-line treatment, alternative regimens for special populations, mechanism explanation, adverse effect profile, and monitoring parameters. That structure forces your brain to practice retrieval in the same context you'll need it during clinical rotations and board exams. I've seen people download these resources and immediately start highlighting everything. That's the fastest way to make the material useless. Highlighting is passive. You need to cover the answer side and force yourself to generate the management plan from the case alone before checking what the document says.
How to Use It Without Wasting Your Time
Start with the section most relevant to your upcoming material. If you're grinding through a cardiology block, pull the cardiovascular section and work through five cases blind. Write down your differential and chosen medication with rationale. Then compare against the document. The part most people skip is the mismatch analysis. When your answer differs from the comprehensive examples set, don't just note the correct answer and move on. Write out exactly why you chose what you chose, then trace where your reasoning diverged. Was it a mechanism misunderstanding? Did you overlook a drug interaction? That divergence point is where actual learning happens. Here's something I learned the hard way during my second year of clinical work. A patient came in with heart failure and atrial fibrillation. The standard comprehensive example would suggest a beta-blocker plus diuretic. But this patient had borderline bradycardia at 52 bpm and a history of reactive airway disease. The textbook algorithm doesn't cover that. I ended up using digoxin as the rate control agent instead, which isn't first-line in any general reference but made sense here. That's the limitation of these documents: they teach the rules, but real patients break them constantly. You need to internalize the baseline before you know when to deviate.
Get the Full Details

The Mechanism-to-Clinical Bridge
The deeper you go with a Pharmacology Examples Comprehensive resource, the more you'll notice the documents that actually work all follow the same internal logic. Every drug entry connects four things: molecular target, physiologic consequence, clinical indication, and toxicity pattern. If any one of those links is missing from your understanding, you'll struggle with application questions. Take warfarin for example. Most study guides will tell you it's an anticoagulant that inhibits vitamin K epoxide reductase. That's accurate and completely insufficient for board exams. You need to understand that the half-life of existing clotting factors determines why warfarin has a delayed onset despite immediate anticoagulant activity at the molecular level. You need to know that the INR doesn't stabilize for five to seven days because factors II, VII, IX, and X all have different half-lives. And you need to recognize that starting heparin simultaneously isn't optional, it's mandatory, because the initial protein C depletion creates a transient hypercoagulable state before the full anticoagulant effect kicks in. When the comprehensive examples document shows all four connections for each major drug class, you stop memorizing and start understanding drug behavior patterns. That's when pharmacology becomes manageable rather than exhausting.
Common Pitfalls That Derail Students
The biggest mistake I see is studying pharmacology in isolation from pathophysiology. You cannot reliably remember which antihypertensive to choose in a patient with diabetes if you don't already understand why those patients are damaged by renin-angiotensin system overactivity. The drug facts become arbitrary and fade within weeks. Build the disease framework first, then layer medications on top. Another trap is conflating drug classes. CCBs and beta-blockers both lower blood pressure and heart rate, but their mechanisms are fundamentally different and the adverse effect profiles don't overlap. Students who group them together in their heads will pick the wrong drug for a patient with reactive airway disease or peripheral vascular disease. Keep classes separate in your notes. There's also the dosing obsession. Yes, know the standard doses for critical medications like vancomycin, heparin, and insulin. But memorizing every dose for every drug is a losing proposition. Focus on the narrow therapeutic index drugs and the ones you'll actually be prescribing. For everything else, understand the dosing principles and look up the specifics when you need them.
Structuring Your Own Practice Sessions
Work through a comprehensive examples document in timed blocks. Twenty cases in forty minutes simulates exam pressure and reveals which drug categories you actually know versus which ones you only recognize when you see them in print. Most students can identify amiodarone's side effects when reading a list but freeze when asked to choose between amiodarone, sotalol, and dofetilide for a specific arrhythmia case without prompting. After each block, spend ten minutes reviewing only the cases you got wrong. Don't rewrite everything. Just explain out loud why the correct answer is correct and why your answer was wrong. Speaking it forces a different neural pathway than silent reading and catches gaps you'd otherwise miss. I used a slightly modified approach during my own exam prep that I still recommend. I took the comprehensive examples and recreated them from memory first, without looking at anything. The version I produced was terrible and full of errors. Then I compared it to the original document and marked everything I'd missed or gotten wrong. That comparison list became my personal high-yield review sheet for the final week. The effort of trying and failing was worth more than any number of passive readings.

When a Comprehensive Resource Falls Short
These documents aren't perfect. They tend to present idealized clinical scenarios that don't reflect the messiness of real practice. Drug interactions are often simplified. Special population dosing, especially in renal impairment and the elderly, is frequently underrepresented because it requires too much nuance for a single reference page. You'll also find that newer drugs get less coverage than established ones, which matters if your curriculum includes recent FDA approvals. If you're relying on a single comprehensive examples document, supplement it with the latest prescribing information for drugs you're encountering clinically. The package insert will have interaction data and dosing adjustments that a general review document won't include. It adds time but prevents dangerous gaps in your knowledge. For board exam preparation specifically, a comprehensive examples resource should be paired with a question bank. The examples teach you the framework. The questions test whether you can use it under time pressure. Using only one or the other leaves you unprepared for the actual testing environment.
The bottom line is that a Pharmacology Examples Comprehensive document is a tool, not a solution. It works if you use it actively, compare your answers honestly, and recognize its limitations. It fails if you treat it like a textbook to be read from cover to cover. Pick the sections you need, drill them until the patterns stick, and move on.



