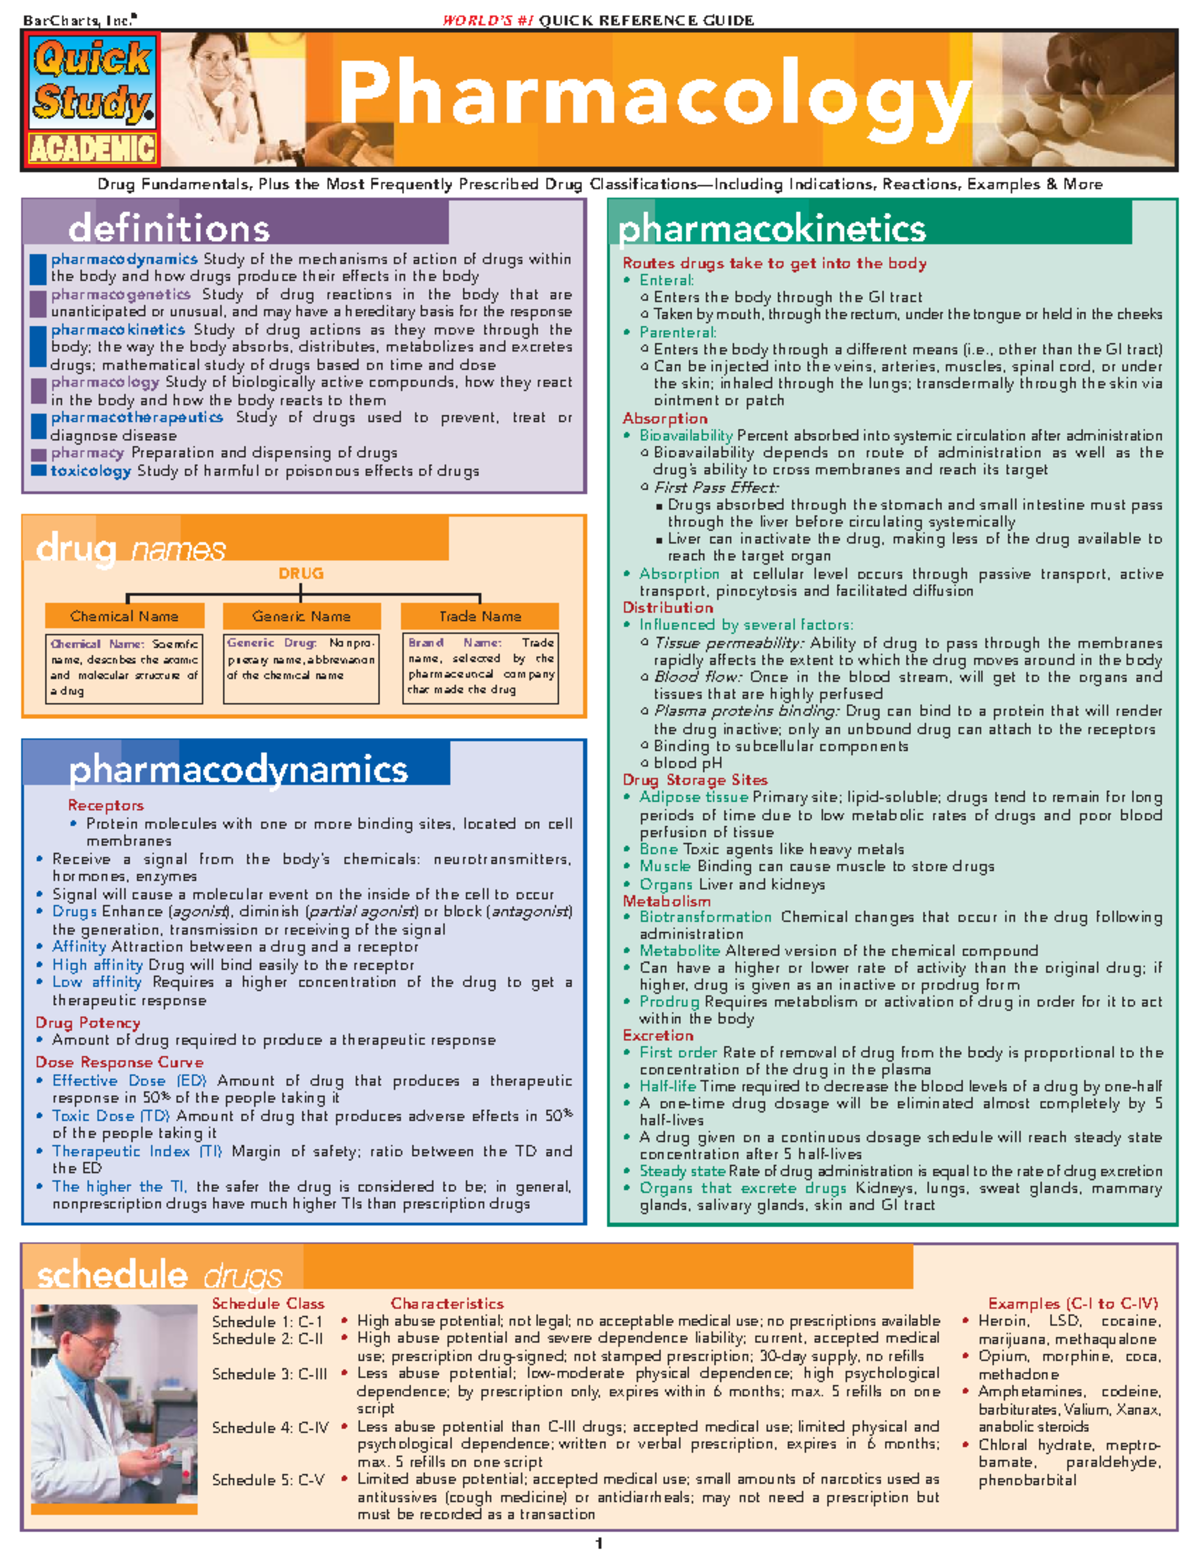
Pharmacology basics are straightforward until you try to make them stick.
The field is massive, and beginners usually drown in terminology before they understand how anything connects. I watched students memorize receptor types for weeks without being able to look at a prescription and figure out what was actually happening inside the body. Pharmacology For Beginners Quick doesn't solve that overnight, but it gives you a framework fast enough to stop flailing and start making actual progress. The method is simple: you start with mechanisms of action instead of drug names. Pick a single pathway — say, the renin-angiotensin-aldosterone system — and trace every medication that touches it. You learn one drug thoroughly, then add the rest as variations on a theme. This beats flashcard decks any day because you're building a mental map rather than collecting isolated facts.
Pharmacology For Beginners Quick: The Mechanism-First Approach
Here's how you actually run it. Take ACE inhibitors as your first circuit. Losartan blocks the AT1 receptor directly. Lisinopril stops angiotensin II from forming. Both drop blood pressure through related but distinct mechanisms. Write that down in a two-column table. Mechanism on the left, clinical consequences on the right. You'll notice patterns like potassium retention, cough side effects, and angioedema risk without being told each one individually. I hit a wall doing this with anticoagulants once. Warfarin versus the DOACs seemed completely unrelated despite both targeting the clotting cascade. My workaround was drawing out the extrinsic and intrinsic pathways by hand on a whiteboard. Connecting factor VII to tissue factor made warfarin's vitamin K antagonism click, and seeing exactly where rivaroxaban and apixaban sit in that same diagram explained their faster onset and fewer dietary interactions. It took about forty minutes and solved a problem that had been bugging me for three weeks. The real advantage here is what most textbooks skip. Drugs are grouped by chemical structure in most courses, but structure rarely predicts clinical behavior the way mechanism does. A beta-blocker like metoprolol and a calcium channel blocker like amlodipine can both lower blood pressure, but their side effect profiles diverge sharply because the pathways they touch are different. Understanding that divergence early saves you from confusing drugs that belong to the same therapeutic class but behave nothing alike in practice.
There's a bottleneck with this approach though. It works well for systems with clear pharmacology, but some drug classes don't fit clean mechanistic boxes. SSRIs, for instance, all block serotonin reuptake, but their clinical differences come down to off-target effects and half-lives rather than primary mechanism. If you push the mechanism-first model too hard into those areas, you'll miss the details that actually matter for prescribing. I learned that the hard way when I could explain fluoxetine's mechanism but couldn't answer why its six-week washout period matters clinically. For those messier areas, flip to a side-effect-first review. Group drugs by what they cause rather than how they work. Anticholinergic burden is one example — first-generation antihistamines, tricyclic antidepressants, and some antipsychotics all share that profile despite belonging to totally different classes. Learning them together is faster and more useful than trying to force a mechanism narrative. Another thing people get wrong is assuming memorization comes after understanding. In pharmacology, the two happen simultaneously. You won't truly grasp pharmacokinetics until you've drilled elimination half-lives enough that they feel intuitive. Same with volume of distribution. These aren't abstract concepts you read about and move on from. They're calculations you'll reach for constantly, and they stick through repetition, not through elegant explanations.
Get the Full Details

If you want a concrete schedule, two hours a day splits cleanly: thirty minutes reviewing yesterday's drugs, sixty minutes learning new ones using the mechanism-first tables, and thirty minutes doing practice questions that force you to apply what you just studied. Questions matter more than reading. I consistently underestimated how much retrieval practice shaped retention. Answering questions revealed gaps I thought I'd closed. The method isn't fast in the sense that you'll finish a full course in a week. But it cuts study time meaningfully compared to traditional approaches. Where students might spend twelve hours per week passively reading chapters, this framework typically gets you through the same material in six to eight hours with better recall. The trade-off is that the first week feels slower because you're building structure instead of accumulating isolated facts. Push through that initial friction and the pace picks up noticeably. One final note about limitations. This approach assumes you have access to a coherent curriculum or a good reference text. Jumping in cold with random drug lists will confuse you more than help. Start with whatever standard resource your program or region uses — Goodman and Gilman, Katzung, whatever — and apply the mechanism-first lens on top of it. Don't try to build your own framework from scratch while also learning the content. That doubles your workload for no real benefit.




