Why You're Building a Pharmacology Guide from Scratch
Most people who end up making their own pharmacology reference materials do it because the available resources don't match how they actually study or work. Commercial drug databases are built for clinicians who need quick lookups at the bedside. Students and researchers often need something structured differently - more about mechanisms, pathways, and relationships between compounds rather than just dosing tables. I spent about three months building my own system after getting frustrated with how Anki cards for pharmacology were scattered across different spaced repetition decks with inconsistent formatting and outdated half-life values. The result ended up being a personal wiki-style reference that I could search by receptor subtype, organ system, or adverse effect profile depending on what I was working on.Pharmacology Guide Diy Approach
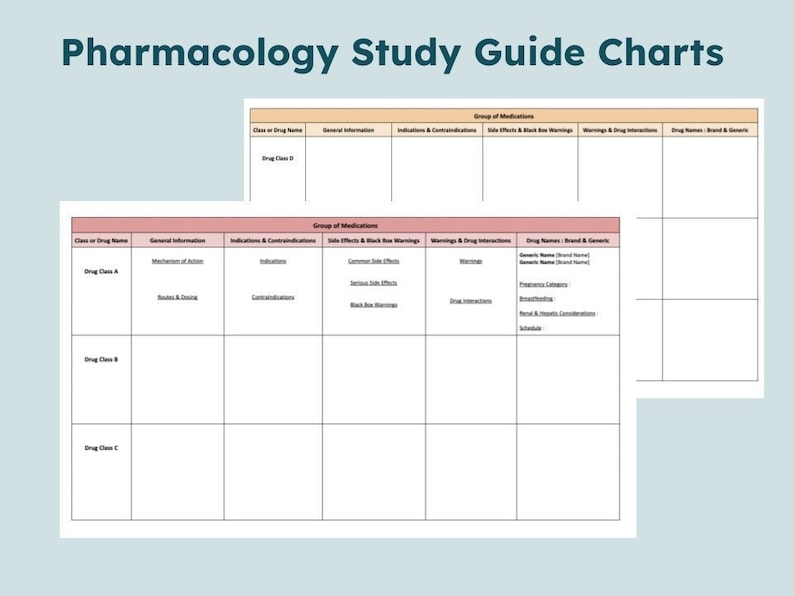
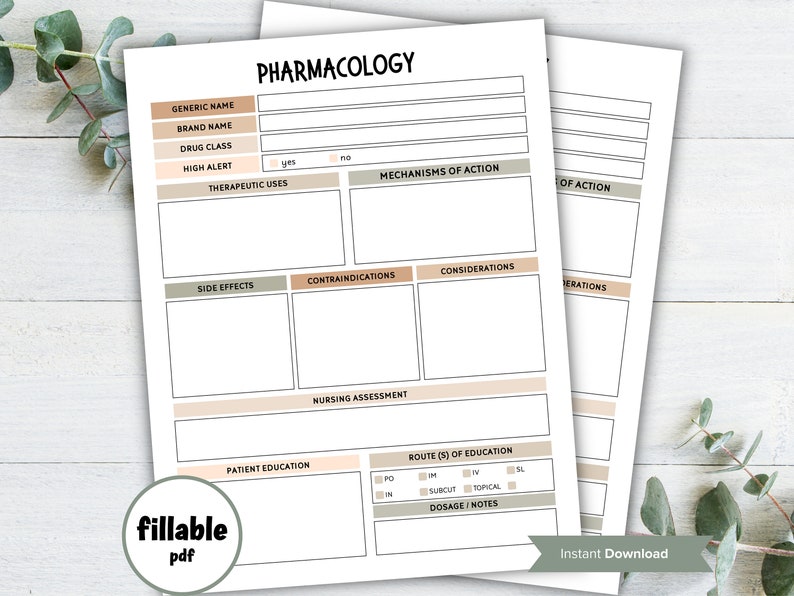
The core structure most people find useful breaks into four layers. First is the drug entry itself - generic name, trade names if relevant, class, route of administration, bioavailability numbers, protein binding percentage, metabolism pathway, and elimination half-life. Second is the mechanism section covering the primary target, downstream signaling effects, and any off-target interactions at therapeutic doses. Third is the clinical correlation - indications, contraindications, major drug interactions, and adverse effects with incidence rates where available. The fourth layer is the comparative notes, which is where you paste in brief comparisons to drugs in the same class so you aren't memorizing each one in isolation. The practical workflow starts with picking a reference source. I used Katzung's Basic and Clinical Pharmacology as the base, cross-referenced with the FDA label database for any drug-specific data points that looked stale. The FDA database is free and updated whenever there's a new safety communication. For mechanism and pathway details, I pulled from Goodman & Gilman when the information wasn't clear elsewhere.One thing that catches people off guard is the half-life variability. A drug listed with a 6-hour half-life in your textbook might show 2 to 8 hours across different patient populations. I started noting the range rather than a single number, and flagged which populations had extended clearance - renal impairment, hepatic dysfunction, elderly. That distinction mattered more than I expected when I was actually using this guide for case discussions.
Building the System
I used Obsidian for this because it handles backlinking and graph view natively, which turns out to be useful when you're trying to see connections between drug classes. You could absolutely use a Google Sheet or Notion database if you prefer structured tables over freeform notes. The choice affects how easily you can search and cross-reference later. Each drug gets its own page with a consistent template. The front matter includes tags for class, mechanism type, and organ system. The body follows the four-layer structure I outlined above. I made it a habit to include the exact source citation at the bottom of each entry because pharmacology references drift and you will need to verify things later.The actual time investment was roughly 12 to 18 minutes per drug for a complete entry the first time through. After I had about fifty entries built, the template became muscle memory and it dropped to around 8 minutes per drug. I covered maybe sixty-five drugs total across cardiovascular, central nervous system, endocrine, and antimicrobial categories before I felt the guide was usable for exam preparation.
A Problem I Ran Into
About halfway through building this, I hit a wall with CYP450 interaction data. Most sources list the major inhibitors and inducers, but they rarely tell you the clinical significance of each interaction. I spent an afternoon cross-referencing the FDA drug interaction labeling sections against clinical pharmacology databases to build a severity rating - contraindicated, major, moderate, minor. That took me about four hours for maybe thirty drugs, but it made the guide actually useful for clinical reasoning instead of just memorization. Another issue was that my initial entries were too dense. I was pasting entire paragraphs from textbooks without distilling them down. After I rewrote about twenty entries to be more concise, the guide became something I could actually scan quickly during study sessions instead of re-reading everything every time.What This Method Does Not Do Well
The main limitation is maintenance. Drug information changes. New black box warnings get added. Guidelines shift. If you built this system and then stopped updating it for six months, portions of it would already be slightly stale. I found myself going back every few months to verify half-lives and interaction data against current prescribing information. A second limitation is scope. This approach works well for a focused set of drug classes. It becomes unwieldy if you try to cover every drug in the pharmacopeia. I stopped adding new entries once I had solid coverage of the drugs that actually appeared on my exams and in my clinical rotations. Everything else was noise at that point.If you need something broader or more clinically oriented than a study guide, commercial databases like UpToDate or Micromedex are worth the subscription cost. They are continuously updated and designed for real-time clinical decision making. This DIY method is better suited for learning and retention than for point-of-care reference.
Get the Full Details