
Pharmacology Nursing Study Guide
Most students treat pharmacology like a memorization contest. That approach breaks down the moment you're standing at a med cart with a full assignment and a patient who just had surgery. The subject requires something different. It requires understanding mechanisms well enough to predict what happens when you miss a dose, and knowing the assessment parameters before you walk into a room. Here is how to actually study this material without losing your mind by midterm.
What a Pharmacology Nursing Study Guide Should Actually Cover
A proper guide goes beyond drug names and doses. The real structure breaks into four areas: mechanisms of action, indications, adverse effects, and nursing considerations. Mechanisms come first because everything else hangs off them. If you understand why a beta-blocker slows the heart through sympathetic inhibition, you do not need to separately memorize that its side effect list includes fatigue and hypotension. The side effects follow from the mechanism. I spent years grading nursing pharmacology exams and the pattern was always the same. Students who grouped drugs by mechanism scored significantly higher than those who grouped by brand name. Brand names are marketing. Mechanisms are physiology. They do not change when a company rebrands. A complete Pharmacology Nursing Study Guide should include therapeutic classifications, the nursing process applied to drug therapy, and priority assessments for high-alert medications. It should also flag contraindications and key drug interactions. Not every drug needs that level of detail. Antibiotics, anticoagulants, and cardiac drugs do, though. Those are the medications where mistakes carry the heaviest consequences.
The hardest part for most students is connecting the pharmacokinetics chapter to actual practice. Absorption, distribution, metabolism, and excretion matter most when patients have conditions that alter any of those steps. A patient with end-stage liver disease metabolizes benzodiazepines differently than someone with normal hepatic function. Studying pharmacokinetics in isolation gives you a textbook answer. Applying it to clinical scenarios is what the NCLEX and real practice actually test.
Get the Full Details
How to Organize Your Study Sessions
Spend more time on the top 100 drugs than on the full formulary. The top 100 cover the vast majority of what you will encounter in clinical rotations and on standardized exams. Focus on drug classes in this order: cardiovascular, endocrine, central nervous system, antimicrobials, and respiratory. Those five categories account for most prescribed medications in acute care settings. Use active recall instead of passive review. Close your notes and write out the mechanism, indication, major side effects, and nursing considerations for a drug class from memory. Then check your work. You will quickly identify which systems you actually understand versus which ones you have only half-memorized. Passive rereading creates a false sense of competence. You recognize the material when you see it and mistake recognition for retention. Spaced repetition helps with the volume. Review a drug class today, again in two days, then in one week. Most programs use flashcard apps or Anki decks for this. The technology is not the point. The point is that forgetting is normal and revisiting material after a delay strengthens long-term retention far more than cramming it all into one session.
The Dosing Calculation Problem Most Students Ignore
Dosage calculations show up in every pharmacology course and on every licensing exam. They also show up during clinicals when you realize you estimated wrong and the pump is set incorrectly. Practice them early and repeatedly. Do not wait until the night before the skills check. The standard methods include dimensional analysis, ratio and proportion, and formula-based calculation. Dimensional analysis tends to be the most reliable under pressure because it tracks units throughout the entire problem. When unit cancellation errors happen, they happen visually. With ratio and proportion, the same error can hide because the setup looks clean even when it is wrong. Here is a scenario I encountered repeatedly. A student calculated a heparin bolus correctly but then converted the infusion rate to mL per hour without checking the concentration on the bag label. The math was right. The assumption was wrong. The bag was 25,000 units in 250 mL, not 500 mL. That single oversight changes the delivered dose by half. In the simulation lab that is a red flag on your skills sheet. In practice it is a preventable adverse event. Always verify the concentration before calculating. The math is the easy part.
High-Alert Medications and What Makes Them Different
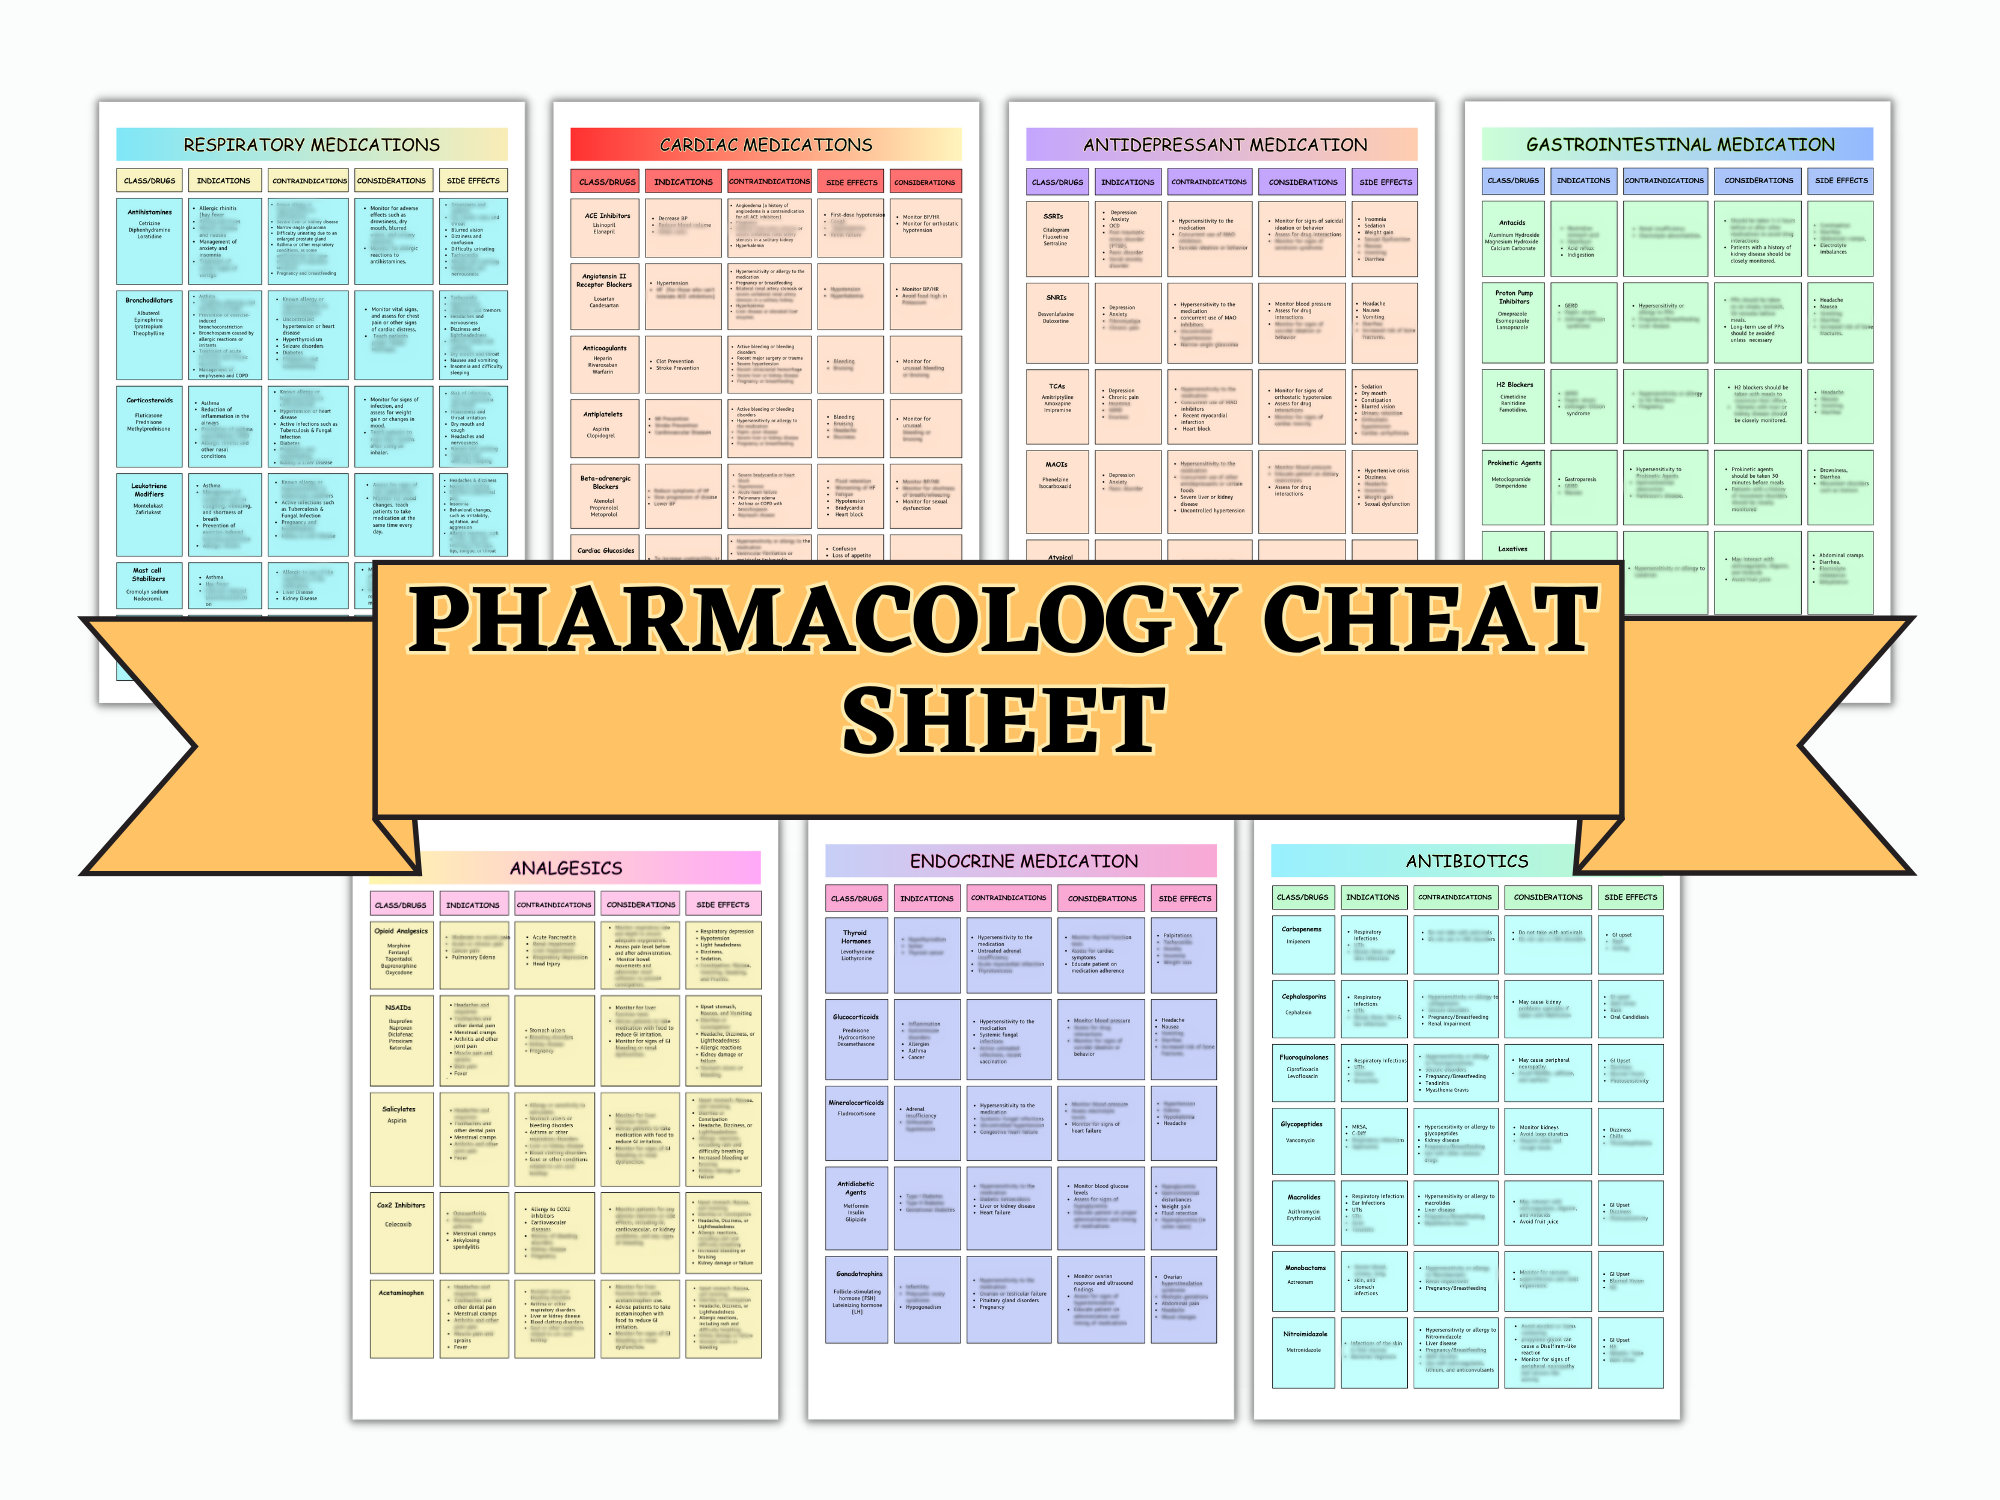
High-alert medications require double-checks, independent verification, and specific assessment parameters before administration. Insulin, heparin, opioids, chemotherapy agents, and neuromuscular blockers fall into this category. Knowing that list is table stakes. The deeper knowledge is knowing the baseline assessments and reversal agents. Insulin requires blood glucose checks and monitoring for hypoglycemia signs. Heparin requires a baseline aPTT and platelet count. Opioids require respiratory assessment. Chemotherapy agents require oncology-specific protocols and spill management. Neuromuscular blockers require availability of reversal agents and ventilator support. These are not optional additions. They are the difference between safe practice and patient harm. When building a study guide, flag each high-alert drug with its monitoring requirements and emergency interventions. Keep that information accessible. Reference tables work better than dense paragraphs when you need a quick lookup during a skills rotation or an exam.

Adverse Effects, Side Effects, and Toxicity
Students confuse these terms constantly. A side effect is an unintended but predictable response to a drug. An adverse effect is any harmful or unpleasant reaction. Toxicity occurs when drug levels reach a range where organ damage becomes likely. The distinction matters for prioritization questions on exams and for clinical judgment in practice. Consider digoxin. The therapeutic range is narrow. Side effects include nausea and visual disturbances. Toxicity presents with arrhythmias and requires serum level checks. Teaching a patient about side effects is different from teaching them about toxicity signs. One is management. The other is escalation. Confusing the two leads to poor patient education and delayed intervention. A strong Pharmacology Nursing Study Guide includes toxicity thresholds, monitoring parameters, and nursing actions for each high-risk drug. Table format works best here. Columns for drug class, therapeutic level, signs of toxicity, and priority nursing intervention compress a lot of information into something you can actually scan under time pressure.
Drug Interactions and How to Approach Them
Drug interactions do not need to be memorized as a complete list. They need a framework. Inhibitors and inducers of cytochrome P450 enzymes affect metabolism. Additive effects occur when two drugs produce the same physiological response. Pharmacodynamic interactions involve receptor-level competition or synergy. Pharmacokinetic interactions involve absorption, distribution, metabolism, or excretion changes. The most clinically significant interactions in nursing practice involve anticoagulants and antiplatelets combined with NSAIDs, SSRIs combined with MAOIs, and digoxin combined with diuretics that cause hypokalemia. Hypokalemia increases digoxin toxicity risk. That is the kind of chain connection that exam questions target and that patients suffer from when it is missed on the floor. Teach yourself to think in chains. Drug A causes electrolyte shift. Electrolyte shift changes Drug B's toxicity profile. Toxicity profile determines what assessments you perform before administration. That chain thinking replaces isolated memorization with a workable mental model.
Using a Pharmacology Nursing Study Guide Effectively
The guide itself is only useful if you interact with it. Reading it passively will not prepare you for application questions. The NCLEX uses modified essay and alternate-format questions that require clinical reasoning. Textbook summaries do not train that skill. Practice questions do. Pair each study session with application questions. After reviewing a drug class, answer five to ten questions that require you to prioritize assessments, identify contraindications, or select the appropriate nursing intervention. Wrong answers are more valuable than right ones if you understand why you got them wrong. The correction process builds the judgment the exams measure. One limitation worth noting: study guides vary widely in quality. Some focus too heavily on brand names and outdated classifications. Others omit the nursing process entirely and present pharmacology as pure biochemistry. Check the publication date and cross-reference with your course objectives. A guide that does not align with your curriculum wastes time. The current FDA labeling updates and revised clinical guidelines mean that anything older than three to five years may already be behind practice standards.
The Role of Clinical Pharmacy Resources
Textbooks and study guides provide the foundation. Clinical references fill the gaps. Drug monographs from sources like Lexicomp or Micromedex include pregnancy categories, renal dosing adjustments, and administration techniques that study guides often summarize or skip entirely. Using these resources during clinical rotations trains you to look up information efficiently rather than trying to carry everything in your head. Memorization has a ceiling. Knowing how to find accurate information quickly has not. Clinical practice changes faster than any printed guide. The habit of verifying details at the point of care is more valuable than perfect recall of information you will look up anyway.
Building Your Own Reference Sheet
Create a one-page summary for each major drug class as you study them. Include mechanism, indication, key side effects, monitoring parameters, and patient teaching points. The act of creating the sheet forces you to make decisions about what matters. That decision-making process is where learning actually happens. A completed sheet you never create teaches you nothing. Start with cardiovascular drugs. Antihypertensives, diuretics, antiarrhythmics, and lipid-lowering agents form a dense cluster that appears frequently on exams and in clinical practice. Once you can differentiate ACE inhibitors from ARBs by mechanism and side effect profile, the rest of that category becomes easier. The same applies to beta-blockers versus calcium channel blockers. The patterns emerge once you stop treating each drug as an isolated fact. The material is extensive. The subject is not unfathomable. Focus on mechanisms, practice application questions, verify calculations independently, and build reference sheets that force you to prioritize. That approach turns a massive volume of information into something manageable without relying on shortcuts that collapse under exam pressure or real clinical demands.


