Understanding the Pharmacology Behind Substance Use
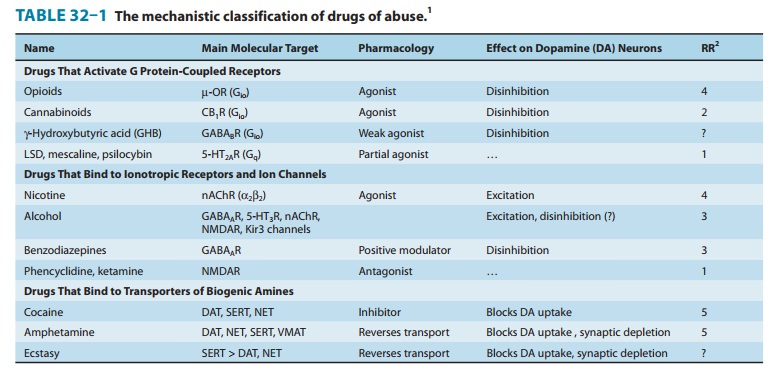
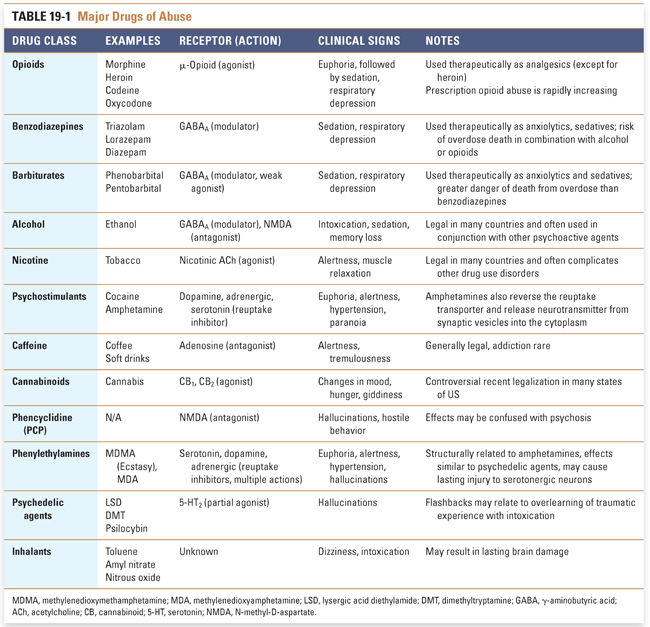
The pharmacology of drugs of abuse covers how addictive substances interact with the central nervous system, peripheral receptors, and neurotransmitter pathways to produce tolerance, dependence, and addiction. This isn't a clean field with clear boundaries. The mechanisms overlap in messy ways that don't always match what textbooks claim, and anyone who has actually worked with these compounds in a clinical or research setting knows the real world is far more complicated than the diagram on page 342 of a pharmacology textbook. Most addictive drugs converge on the mesolimbic dopamine pathway, specifically the ventral tegmental area projecting to the nucleus accumbens. That's the basic pathway. The details matter far more than the headline. Opioids like heroin and fentanyl act as agonists at mu-opioid receptors, which indirectly disinhibit dopamine neurons by suppressing GABA interneurons. That's a double-negative mechanism. The dopamine surge is indirect, mediated through GABA reduction rather than direct dopaminergic action. Cocaine and amphetamines are more direct. Cocaine blocks the dopamine transporter (DAT), preventing reuptake, while amphetamines reverse the transporter, forcing dopamine out into the synapse. Different molecular mechanisms, similar behavioral outcomes. Cannabis compounds act primarily through CB1 receptors in the brain, modulating GABA and glutamate release. The resulting dopamine increase is also indirect, via disinhibition of GABAergic control on dopamine neurons in the VTA. Benzodiazepines enhance GABA-A receptor function, increasing chloride influx and producing sedation, anxiolysis, and muscle relaxation. They don't directly activate the receptor. They increase the frequency of chloride channel opening when GABA is already present, which is why they have a ceiling effect for respiratory depression compared to barbiturates. Barbiturates can directly open the chloride channel even without GABA, which is why overdose is far more lethal.
I spent considerable time in a clinical toxicology unit dealing with polysubstance presentations. One case that stands out involved a patient who had used synthetic cathinones, commonly called bath salts, alongside benzodiazepines. Standard reversal protocols didn't apply cleanly here. Flumazenil is the benzodiazepine antagonist, but using it in a mixed overdose with certain compounds can precipitate seizures, especially when the benzodiazepine was taken chronically for self-medicating stimulant crashes. The cathinones themselves don't have a reversal agent. Supportive care with benzodiazepines is the standard approach, but if you're also reversing the benzodiazepine with flumazenil, you lose your only tool for controlling the stimulant toxicity. The workaround was staying on a continuous benzodiazepine infusion and keeping flumazenil strictly reserved for cases with life-threatening respiratory depression, which it was in only about one in fifteen of these mixed presentations.
Serotonin Syndrome and Overlooked Interactions
One thing beginners consistently miss is the serotonin syndrome risk with drugs like MDMA, Tramadol, and dextromethorphan. These compounds inhibit serotonin reuptake through different mechanisms but the effect is additive. MDMA blocks SERT and also displaces serotonin from vesicles. Tramadol has weak serotonergic activity alongside its opioid mechanism. Taking them together can push serotonin levels into a dangerous range even at doses that wouldn't cause problems alone. The classic presentation includes autonomic instability, neuromuscular hyperactivity, and altered mental status. Cyproheptadine is the treatment, but it's not something most emergency departments stock in readily available quantities, and recognition is the real bottleneck here. Another counter-intuitive point involves nicotine. People treat it as a mild recreational drug, but its pharmacology is remarkably complex. Nicotine acts on nicotinic acetylcholine receptors throughout the brain and periphery. It increases dopamine release in the nucleus accumbens through activation of nicotinic receptors on VTA neurons. It also stimulates release of norepinephrine, serotonin, endorphins, and cortisol. The half-life is about two hours, which is why withdrawal symptoms appear quickly and hit hard for heavy users. The tolerance development is rapid, often within weeks of regular use, and the dependence profile, while milder than opioids or alcohol, is still clinically significant. Withdrawal symptoms include irritability, anxiety, difficulty concentrating, increased appetite, and insomnia, typically peaking in the first week and lasting several weeks.
Get the Full Details
Tolerance and Cross-Tolerance Patterns
Tolerance develops at different rates across drug classes. Opioid tolerance to analgesia and euphoria develops relatively quickly, often within days to weeks of repeated use. Tolerance to constipation and miosis develops much slower, which is why patients on long-term opioid therapy still suffer severe constipation even after pain control improves. This differential tolerance is clinically important and frequently ignored. Cross-tolerance between opioids is well established. Someone with high tolerance to heroin will also show tolerance to morphine and oxycodone because they act on the same receptor subtype. But cross-tolerance between different classes is limited. A benzodiazepine-tolerant person won't show tolerance to opioids, and vice versa. The exception is alcohol and benzodiazepines, which both act on GABA-A receptors and show significant cross-tolerance. This matters enormously in overdose situations where someone using benzodiazepines chronically presents with alcohol in their system. The combined respiratory depressant effect is synergistic, not merely additive, and the margin between a sedative dose and a lethal dose narrows dramatically.
Individual Variability in Drug Response
Genetic polymorphisms explain a lot of the variability in how people respond to these substances. The CYP2D6 enzyme metabolizes codeine to morphine. Poor metabolizers get little to no analgesic effect from codeine because they can't convert it. Ultra-rapid metabolizers, on the other hand, can convert codeine to morphine so efficiently that standard doses produce opioid toxicity, including respiratory depression. This isn't theoretical. There are documented cases of infants dying from morphine exposure through breast milk when the mother was an ultra-rapid metabolizer taking codeine for postpartum pain. The COMT gene variant affects how dopamine is broken down in the prefrontal cortex. People with the Val158Met polymorphism have different baseline dopamine tone, which influences both their risk of developing substance use disorder and their response to certain medications. The OPRM1 gene codes for the mu-opioid receptor, and the A118G polymorphism affects receptor binding affinity. These genetic differences mean that population-level dosing guidelines are always approximations, and individual response can vary significantly from the expected pattern.
Pharmacokinetics in Real-World Use
The route of administration dramatically changes pharmacokinetics and therefore the risk profile. Intravenous injection produces the fastest onset and highest peak concentration, which is why it carries the highest addiction potential and the greatest risk of acute overdose. Smoking or vaping also produces rapid onset, though slightly slower than injection. Oral administration has the slowest onset due to first-pass metabolism, but the duration of effect is longer. This matters for harm reduction purposes because the delay between ingestion and peak effect with oral use means people sometimes redose prematurely, not feeling the full effect yet and accidentally consuming a lethal amount. Purity and adulteration are persistent problems in the illicit drug supply. Fentanyl and its analogs have contaminated the cocaine and methamphetamine supply across North America and Europe since around 2013. People who use cocaine expecting cocaine are getting fentanyl exposure without knowing it. The dose-response relationship for fentanyl is extremely steep. A difference of one microgram can be the difference between a desired effect and respiratory arrest. Test strips exist for fentanyl detection, but they have limitations. They can detect fentanyl at certain thresholds but miss some analogs, and they don't quantify the amount present. Even with test strips, the user community's understanding of how to properly use them is inconsistent.

Withdrawal Pharmacology
Withdrawal from different drug classes produces fundamentally different physiological states. Alcohol and benzodiazepine withdrawal can be fatal due to unopposed neuronal excitation, manifesting as seizures and delirium. Opioid withdrawal is extremely distressing but rarely life-threatening in healthy adults. The sympathetic overdrive, GI hypermotility, and yawning are miserable but don't typically cause death unless complications like aspiration or severe dehydration occur. Stimulant withdrawal, particularly from methamphetamine and cocaine, produces a crash phase characterized by severe depression, fatigue, and increased appetite, followed by anhedonia that can persist for weeks or months. This protracted anhedonia is partly due to dopamine system downregulation and is a major factor in relapse. The concept of kindling is important here. Repeated cycles of withdrawal and reinstatement can sensitize the nervous system, making each subsequent withdrawal episode more severe. This is most documented with alcohol and benzodiazepines but appears to occur with other depressants as well. Someone who has been through multiple detox cycles may face progressively worse withdrawal symptoms even if the amount used hasn't increased. This means that medical supervision for withdrawal should be maintained longer and approached more conservatively in people with a history of multiple detox attempts.
Limitations of Current Pharmacological Approaches
Naltrexone is effective for alcohol use disorder and opioid use disorder, but it has significant limitations. For opioid dependence, it requires complete detoxification before initiation, which means the patient must be opioid-free for seven to ten days. Starting naltrexone too early precipitates immediate withdrawal. Compliance is another issue because the medication blocks the rewarding effects of opioids, which means if someone relapses, their tolerance has decreased but their dosing hasn't, creating a high overdose risk. The extended-release injectable formulation improves compliance but is expensive and not universally available. Buprenorphine has become the preferred medication for opioid use disorder in many settings because it has a ceiling effect on respiratory depression, making it safer than full agonists in terms of overdose potential. However, it's still a partial agonist at mu-opioid receptors, and patients with high tolerance who switch from full agonists can experience precipitated withdrawal if buprenorphine is started too soon. The induction protocol matters enormously here. Starting on the same day as last opioid use can be dangerous. Waiting too long increases the risk of the patient dropping out of treatment due to withdrawal discomfort. The standard recommendation of 12 to 24 hours for short-acting opioids and 72 hours or more for methadone is a rough guideline, and individual variation means some people need longer waiting periods regardless of the textbook recommendation. For stimulants like methamphetamine and cocaine, there are no FDA-approved pharmacological treatments with strong evidence. Behavior therapy remains the primary intervention, and while research into vaccines and monoclonal antibodies is ongoing, nothing with robust clinical efficacy has reached practice yet. This is a genuine gap in the field, and it's worth stating plainly rather than padding the discussion with hopeful speculation about pipeline drugs.