Learning pharmacology doesn't require memorizing everything at once
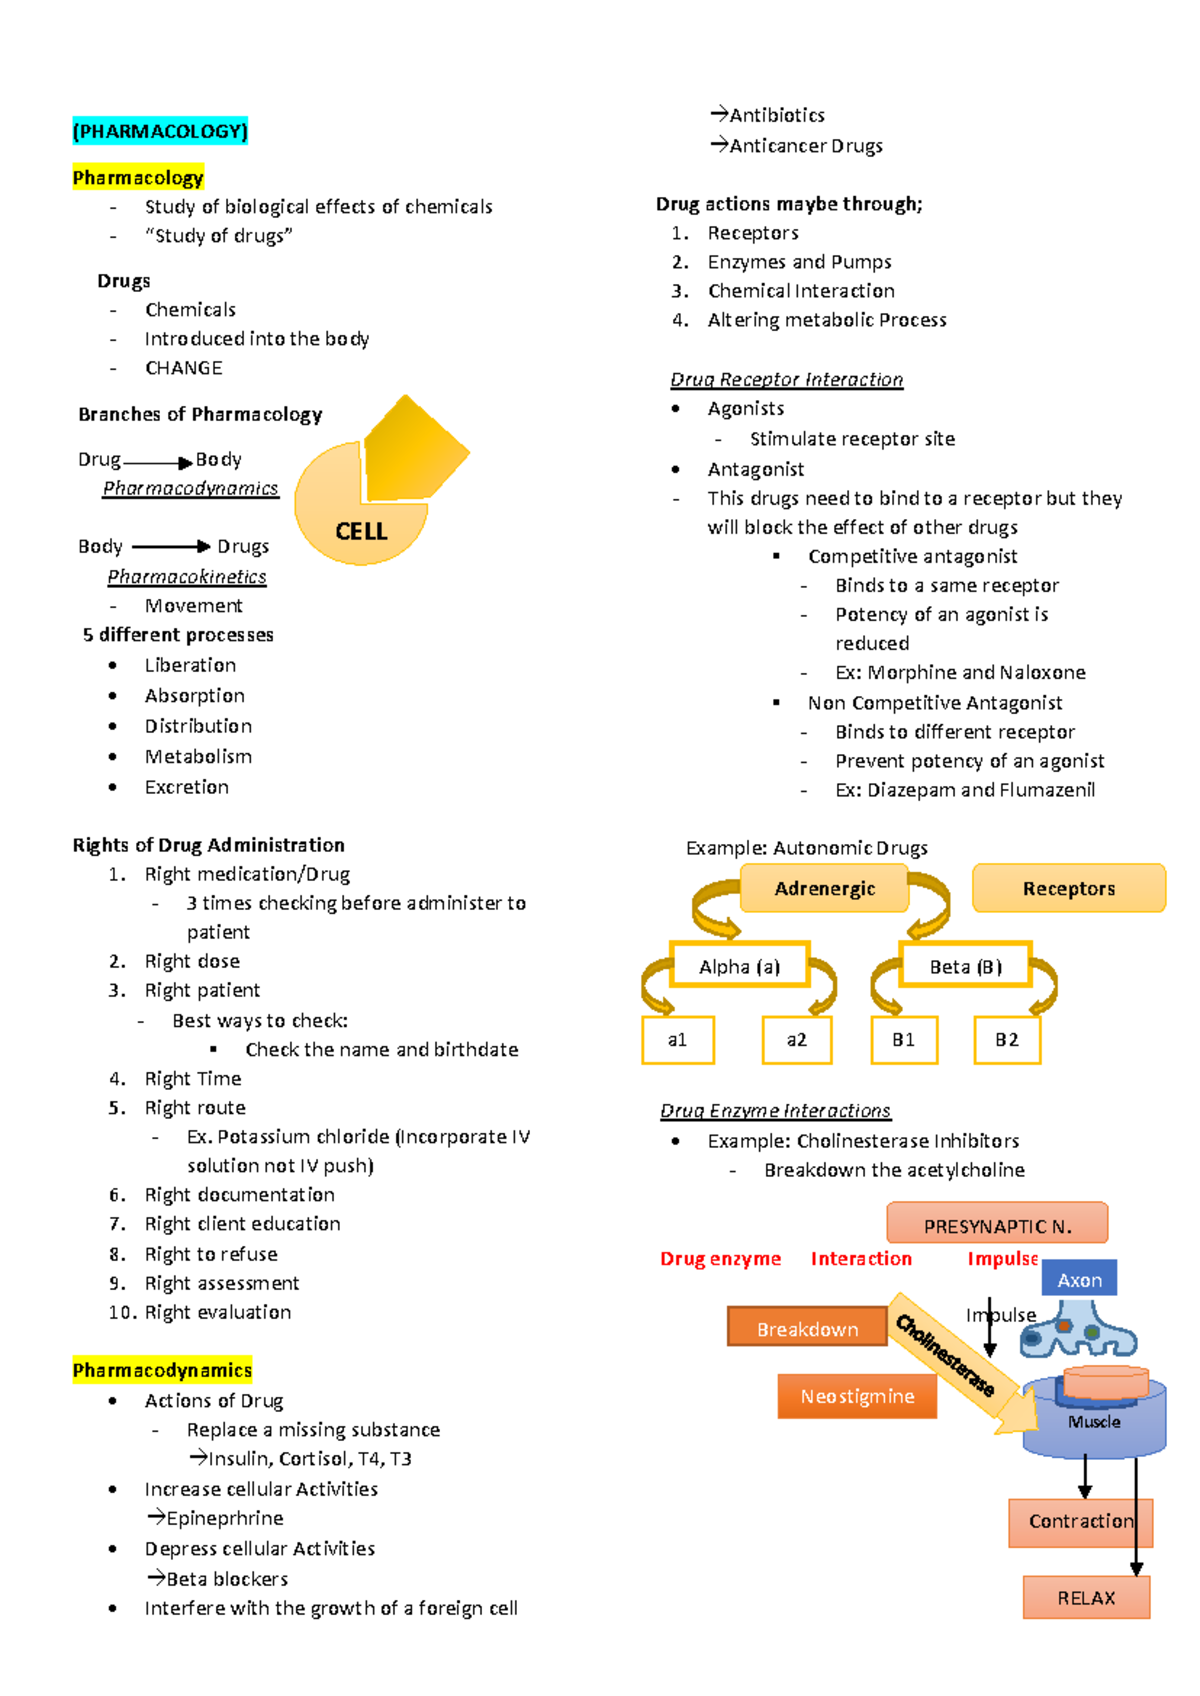
When I first started studying pharmacology, I tried to learn every drug class by rote. That approach failed quickly because the volume of information overwhelms working memory. Instead, I shifted to a sequential method that builds on what you already understand. This is what people sometimes call Pharmacology Step By Step Simple, though I never use that phrase out loud. Start with pharmacokinetics. Absorption, distribution, metabolism, excretion. These four pillars explain how drugs move through the body. Without understanding half-life and clearance rates, memorizing drug names becomes pointless exercise. I spent three weeks on basic PK before touching any drug classes. This foundation makes the rest significantly easier. Pharmacodynamics follows naturally. Receptor binding, signal transduction, dose-response curves. The key insight most students miss is that most drugs don't work the way textbooks describe. They hit multiple receptors, trigger cascading effects, and produce side effects that seem random until you map the mechanism.
Once you grasp the mechanism, drug classification becomes logical rather than arbitrary. Beta-blockers aren't just a list to memorize. They share a common endpoint: blocking beta-adrenergic receptors. Understanding this principle lets you predict the properties of drugs you've never seen before.
Practical application requires pattern recognition
I encountered a specific problem during my clinical rotations. A patient was prescribed propranolol for hypertension but developed severe bronchospasm. The textbook explanation was straightforward: non-selective beta-blockade affecting both beta-1 and beta-2 receptors. However, the real learning came from understanding why this happened in that particular patient and how to prevent it next time. The workaround involved checking the patient's pulmonary history before prescribing any non-selective agent. This seems obvious now, but during exams, this edge-case rarely appears explicitly. You need to recognize the pattern and apply caution even when the question doesn't spell it out. Dosing calculations represent another area where theory diverges from practice. The formula is simple: dose equals concentration times volume. But volume of distribution varies dramatically between patients. Obesity, age, renal function all alter this parameter. I once calculated a phenytoin dose using population averages and missed the actual therapeutic range by 40 percent. This mistake taught me to always adjust for individual patient factors.
Get the Full Details

Drug interactions demand systematic thinking
CYP450 enzyme induction and inhibition form the backbone of clinically significant drug interactions. Most introductory courses gloss over this topic. The reality is more complex. Enzyme inducers like rifampin can reduce drug concentrations by 50 to 80 percent within days. Enzyme inhibitors like ketoconazole can raise levels enough to cause toxicity in the same timeframe. The counter-intuitive point: not all interactions are dangerous. Some produce therapeutic benefits. Combining lisinopril with hydrochlorothiazide exemplifies this principle. Both drugs lower blood pressure through different mechanisms. Together they achieve better control than either alone. Learning to distinguish beneficial combinations from harmful ones requires understanding mechanism, not just memorizing lists. Adverse drug reactions follow predictable patterns based on mechanism. Anticholinergic effects appear with drugs affecting muscarinic receptors. Sedation occurs with agents crossing the blood-brain barrier. Understanding these connections allows prediction of side effects before encountering them clinically.
Common pitfalls that waste study time
Students frequently confuse pharmacokinetics with pharmacodynamics. These concepts overlap but remain distinct. PK describes what the body does to the drug. PD describes what the drug does to the body. Mixing these up causes errors on examinations and in practice. Another frequent mistake involves memorizing drug names without understanding classes. Knowing that metoprolol is a beta-blocker matters more than memorizing its chemical structure. Classification provides the framework for predicting properties, interactions, and adverse effects. The limitation of this approach: it doesn't cover every drug exception. Medicine contains numerous outliers that defy simple classification. Some drugs work through unexpected mechanisms. Understanding the general principles helps, but clinical practice requires consulting references when encountering unfamiliar agents.
Alternative methods exist for different learning styles
Some students prefer visual mapping over sequential learning. Creating mind maps connecting mechanism to clinical application proves effective for certain individuals. Others benefit from clinical case studies that contextualize pharmacological principles. Neither approach eliminates the need for understanding basic mechanisms. The step-by-step method I described works best for students who need structural clarity. It provides a scaffold for organizing information. However, this structure can become rigid if followed too literally. Adapt the method to your own cognitive style while maintaining focus on mechanism understanding. Pharmacology remains one of the most clinically relevant subjects in medical education. Drugs affect nearly every physiological system. Understanding how they work enables safer prescribing, better patient outcomes, and more effective treatment strategies. The investment in learning mechanism pays dividends throughout clinical practice.