Why Everyone Is Rushing Into This Field Right Now
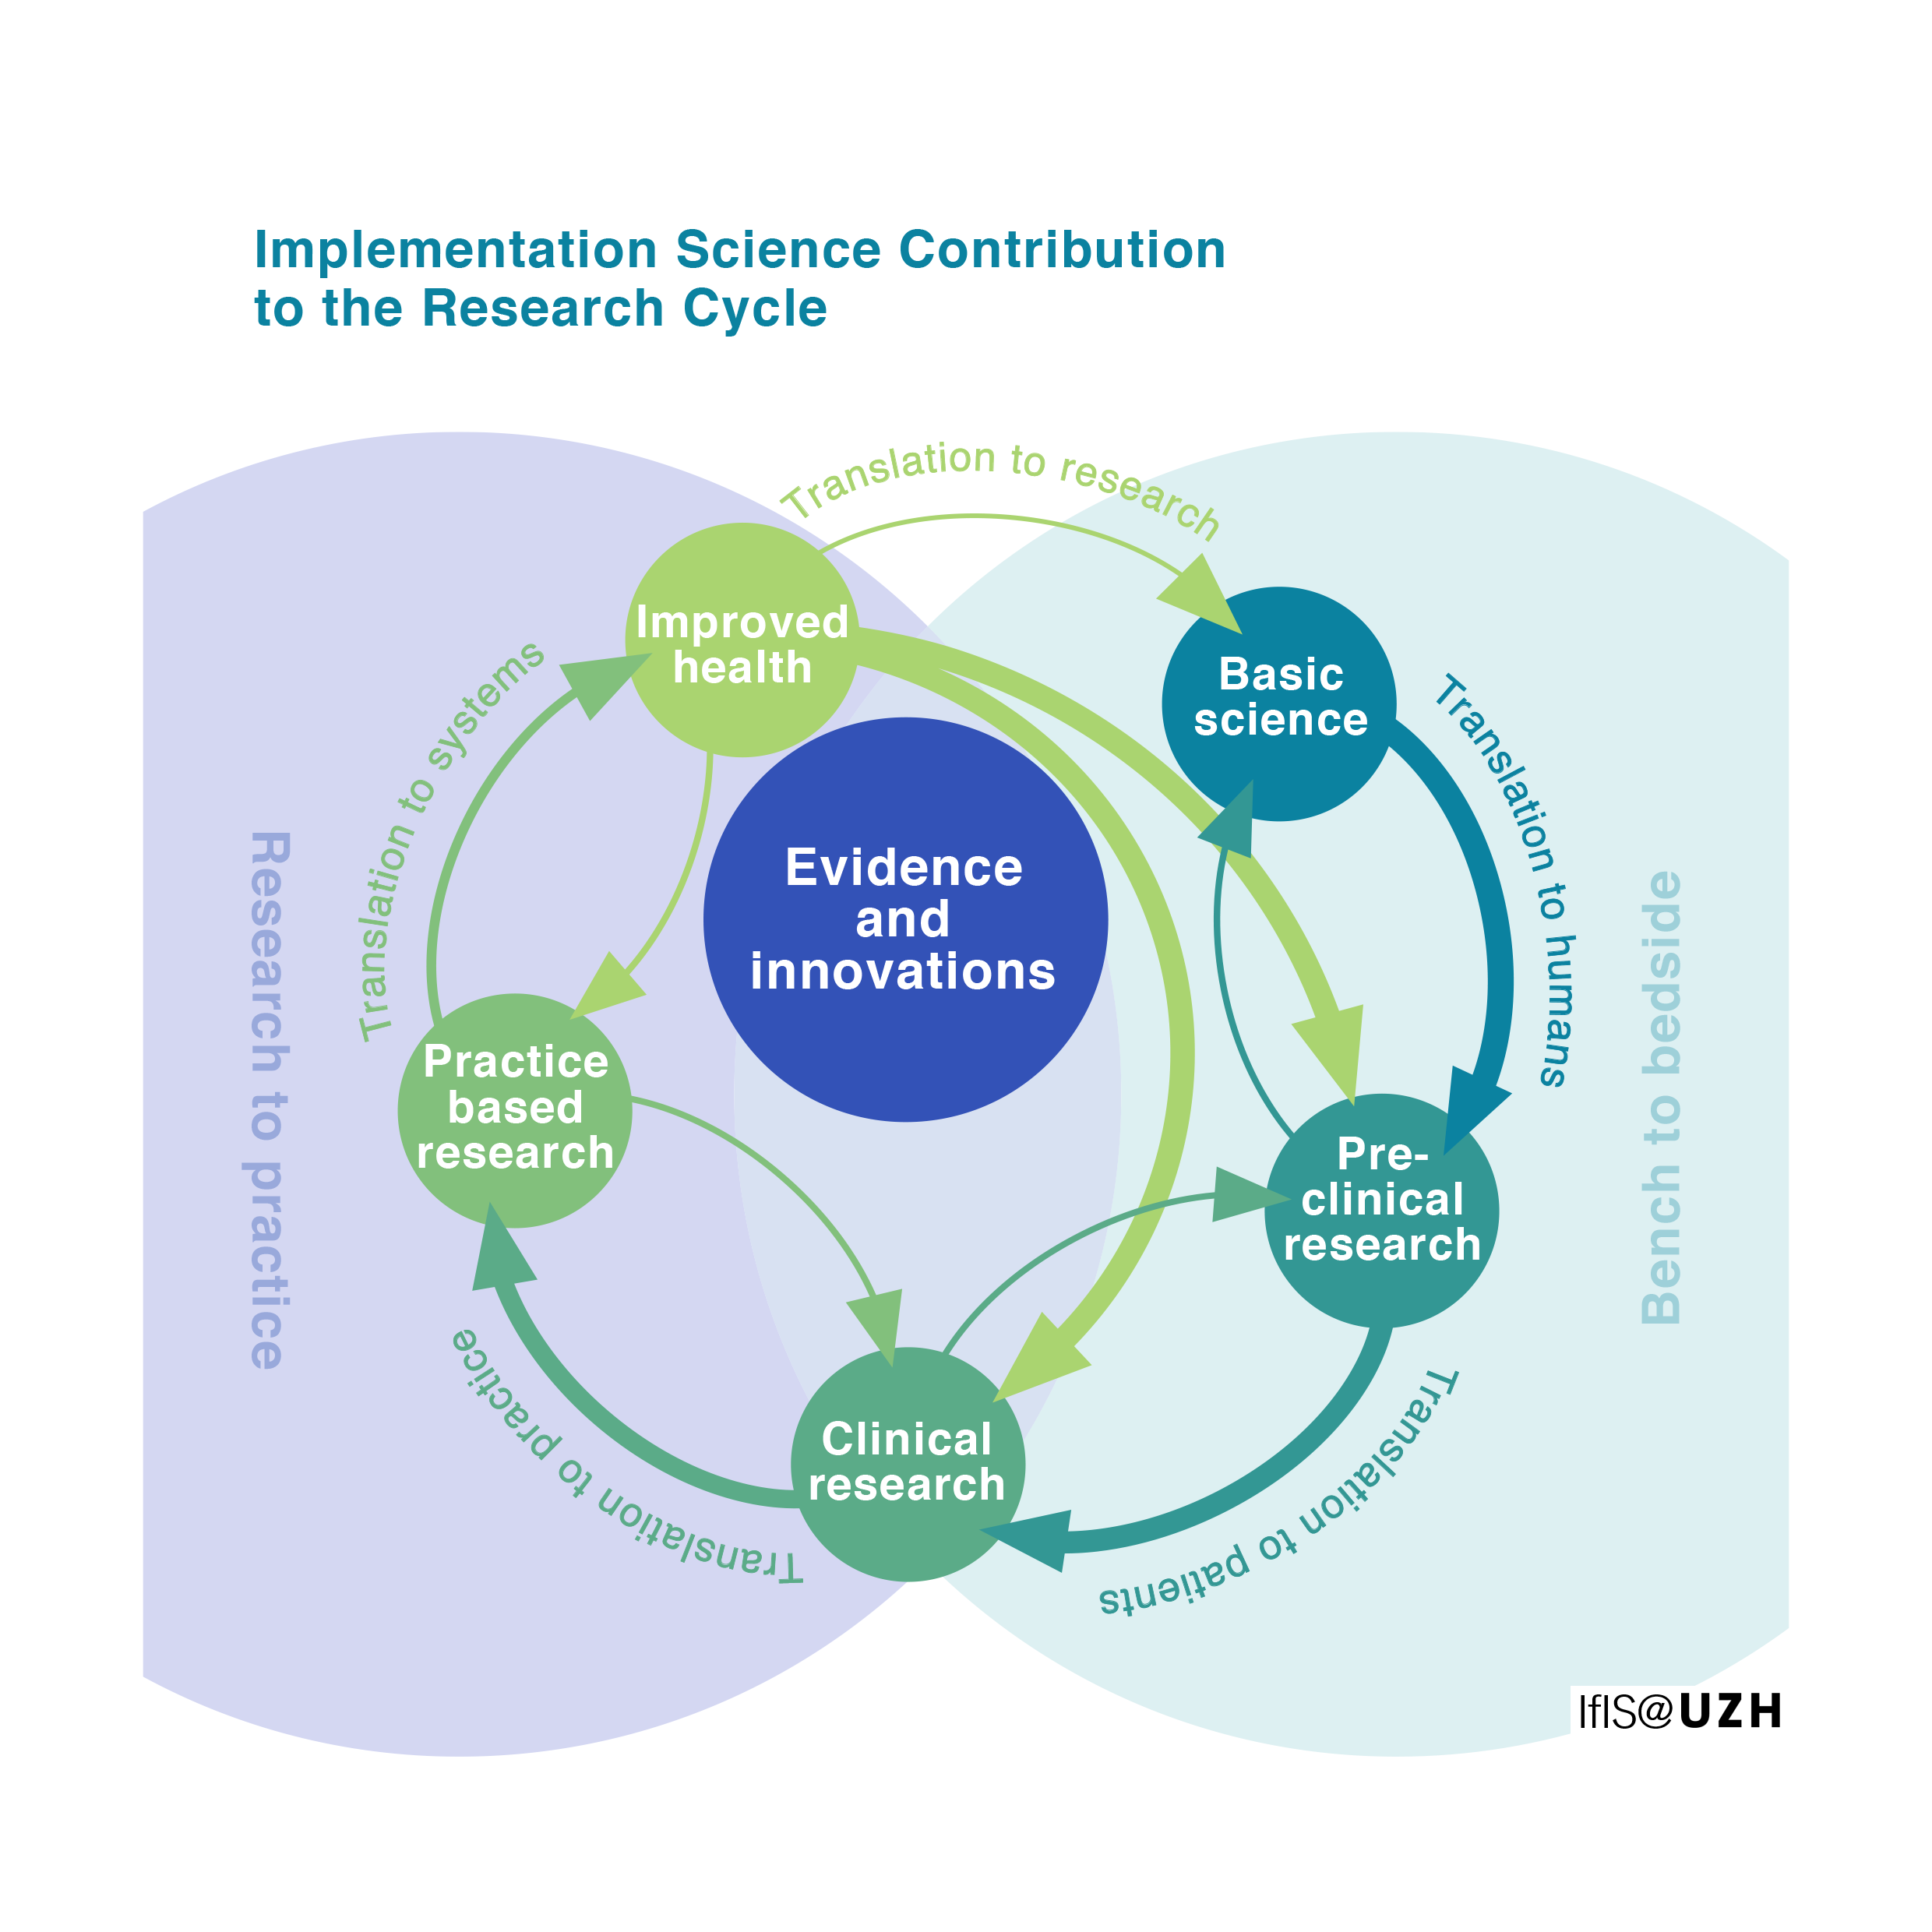
The job market for health services researchers has shifted hard over the past few years. Hospitals, public health departments, and even some pharma companies now have dedicated implementation science budgets. Funding from NIH and AHRQ has poured into the area. This means PhD programs in implementation science have popped up at more universities, and applications are way up. If you are thinking about it, here is what you actually need to know before committing four to six years. Implementation science is the study of methods to promote the adoption of research findings into routine practice. It is not clinical research. It is not basic science. It is the "how do we get evidence-based interventions actually used at scale" discipline. Programs vary by school but most sit somewhere between public health, psychology, and health services research departments. The core curriculum usually covers frameworks like the Consolidated Framework for Implementation Research (CFIR), the RE-AIM framework, and normalization process theory. You will take methods courses in mixed-methods design, qualitative interview analysis, and implementation outcome measurement. Some programs require a practicum or consulting project where you work with an actual health system. That part matters more than the classes.
The Methods You Actually Need To Know
Mixed methods is the bread and butter. You will run focus groups with frontline clinicians while simultaneously collecting fidelity data from electronic health records. The trick is integration. Most students fail here because they treat qual and quant as separate projects instead of weaving them together through joint displays or convergence sampling designs. Learning QualCoder or ATLAS.ti early saves months of headaches. I spent two weeks wrestling with NVivo in my first year when a colleague showed me that QualCoder handles code hierarchy far more efficiently and runs on macOS without complaining. For quantitative work, R with the mixedmod or lavaan packages handles the nested data structures you will encounter. Don't rely on SPSS. It cannot do multi-level modeling well enough for implementation data where patients are nested within clinics nested within regions.
A Real Problem I Ran Into And How I Fixed It
During my dissertation work, I was evaluating a suicide risk assessment protocol rollout across ten community health centers. The implementation outcome measure was supposed to capture adoption fidelity. The problem was that half the sites were using the new protocol but documenting it differently depending on their EHR vendor. One site had a dedicated smart form. Another had a free-text note. A third site didn't document it at all and just told me verbally they were doing it. The workaround was to build a three-pronged data collection approach. I used chart audit abstractions for the sites with structured data. For the free-text sites, I built a Python script with regex patterns to extract mentions of the protocol from clinical notes. For the sites that refused or couldn't document, I did structured provider interviews triangulated against patient encounter timestamps. It took extra time upfront but prevented the whole dataset from being thrown out. You learn pretty fast that implementation data is messy and you need backup collection methods for every site.
Get the Full Details
Counter-Intuitive Things No One Tells You
Framework selection is more important than method selection. I have seen students use sophisticated statistical models on poorly defined implementation problems because they picked a framework that didn't match their research question. If you are studying sustainability, CFIR is fine. If you are studying how an intervention becomes routinized, normalization process theory gives you better constructs to measure. The framework drives your measures, not the other way around. Another thing: publishing in implementation science is harder than you think. The top journals in the field have limited capacity and favor theory-driven papers over straightforward evaluations. This means a clean but shallow evaluation might get rejected while a messier paper with strong theoretical contribution gets accepted. Focus on building a conceptual model early. Your committee will thank you.
Program Selection Checklist
Look at where recent graduates land. If they are going into academia, the program has a research track. If they are going into health systems or consulting, it has an applied track. Both are valid. Check whether the program has funded projects with actual health system partners. Implementation science without real-world partners is just theory writing. Also verify that your potential advisor has active AHRQ or NIH R01s in implementation. Funding follows people, and people who can't secure grants will struggle to support you. The field suffers from a credibility problem in some traditional epidemiology circles. Implementation science is sometimes dismissed as "soft" because it deals with process rather than disease outcomes. You will hear this from certain faculty members. It is unfair but real. If you want a career in pure biostatistics or clinical trials, this might not be the path. Budget constraints are another issue. Some programs offer partial funding that covers tuition but not a living wage. Teaching assistantships pay around 18 to 22 thousand dollars a year depending on the state. In coastal cities, that barely covers rent. Look for programs with guaranteed fellowships or industry partnerships that provide better stipends.
The work can also be emotionally draining. You are often trying to change systems that are already failing patients. Watching a well-designed intervention fail because of broken workflows or unmotivated staff takes a toll. This isn't a field for people who need quick wins. Projects routinely take three to five years from launch to published results.

Alternatives Worth Considering
If a full PhD feels too long, some universities offer a Master's in Implementation Science or Health Services Research with a thesis option. This takes two years and can still lead to jobs in health systems. Another path is a clinical PhD like a DDS or PharmD combined with an implementation science fellowship. Clinicians with implementation training are rare and highly sought after. If you are already working in a health system, look into employer-sponsored part-time programs. Some hospital networks will fund your tuition if you commit to staying after graduation. It limits your options but removes the debt burden entirely. There is no single right answer. The field needs people who understand both the science and the systems. If you can tolerate the slow pace and the institutional friction, it is one of the more impactful areas in public health right now. Just go in with your eyes open.