Why Your Patients Seizure Threshold Drops Anyway
I spent six months chasing breakthrough seizures in a unit patient on phenytoin that I couldn't explain at first. Her loading dose was perfect, her trough level came back therapeutic at 12 mcg/mL, yet she kept having absence-like absences that weren't on the EEG. Turns out phenytoin has this weird dual effect — at higher concentrations it actually can worsen certain seizure types instead of suppressing them. That patient ended up on levetiracetam instead and went home seizure-free the next day. Understanding how phenytoin actually works at the molecular level isn't just textbook trivia. It changed how I approached dosing and monitoring for about a year until it became second nature.
The Core Phenytoin Mechanism Of Action
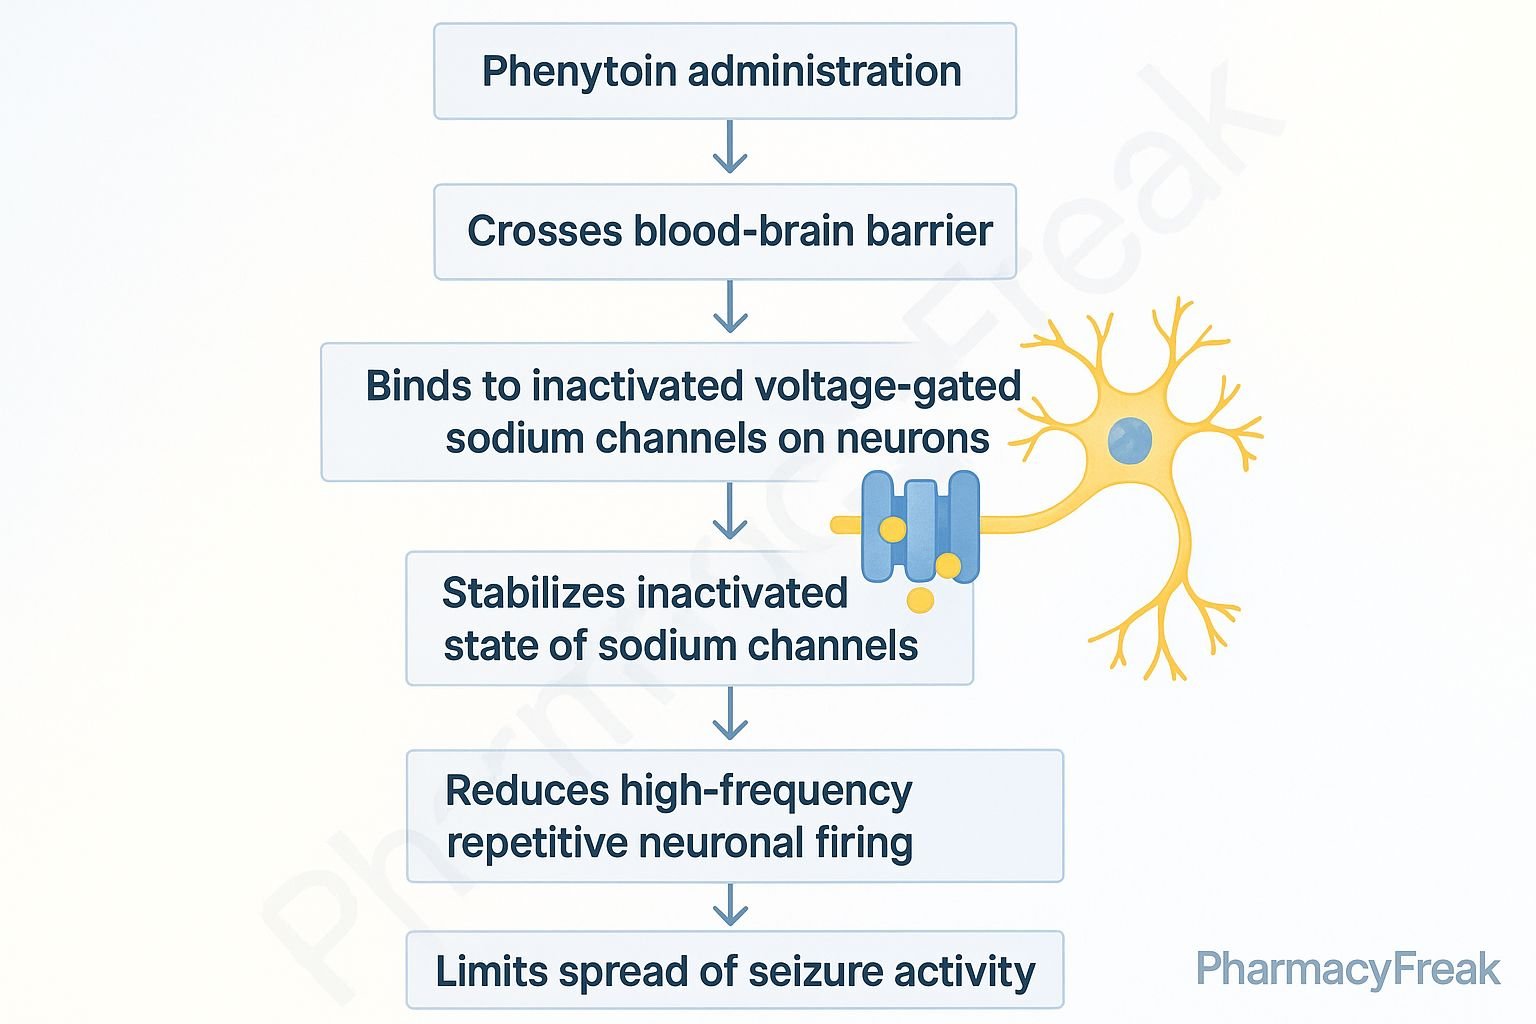
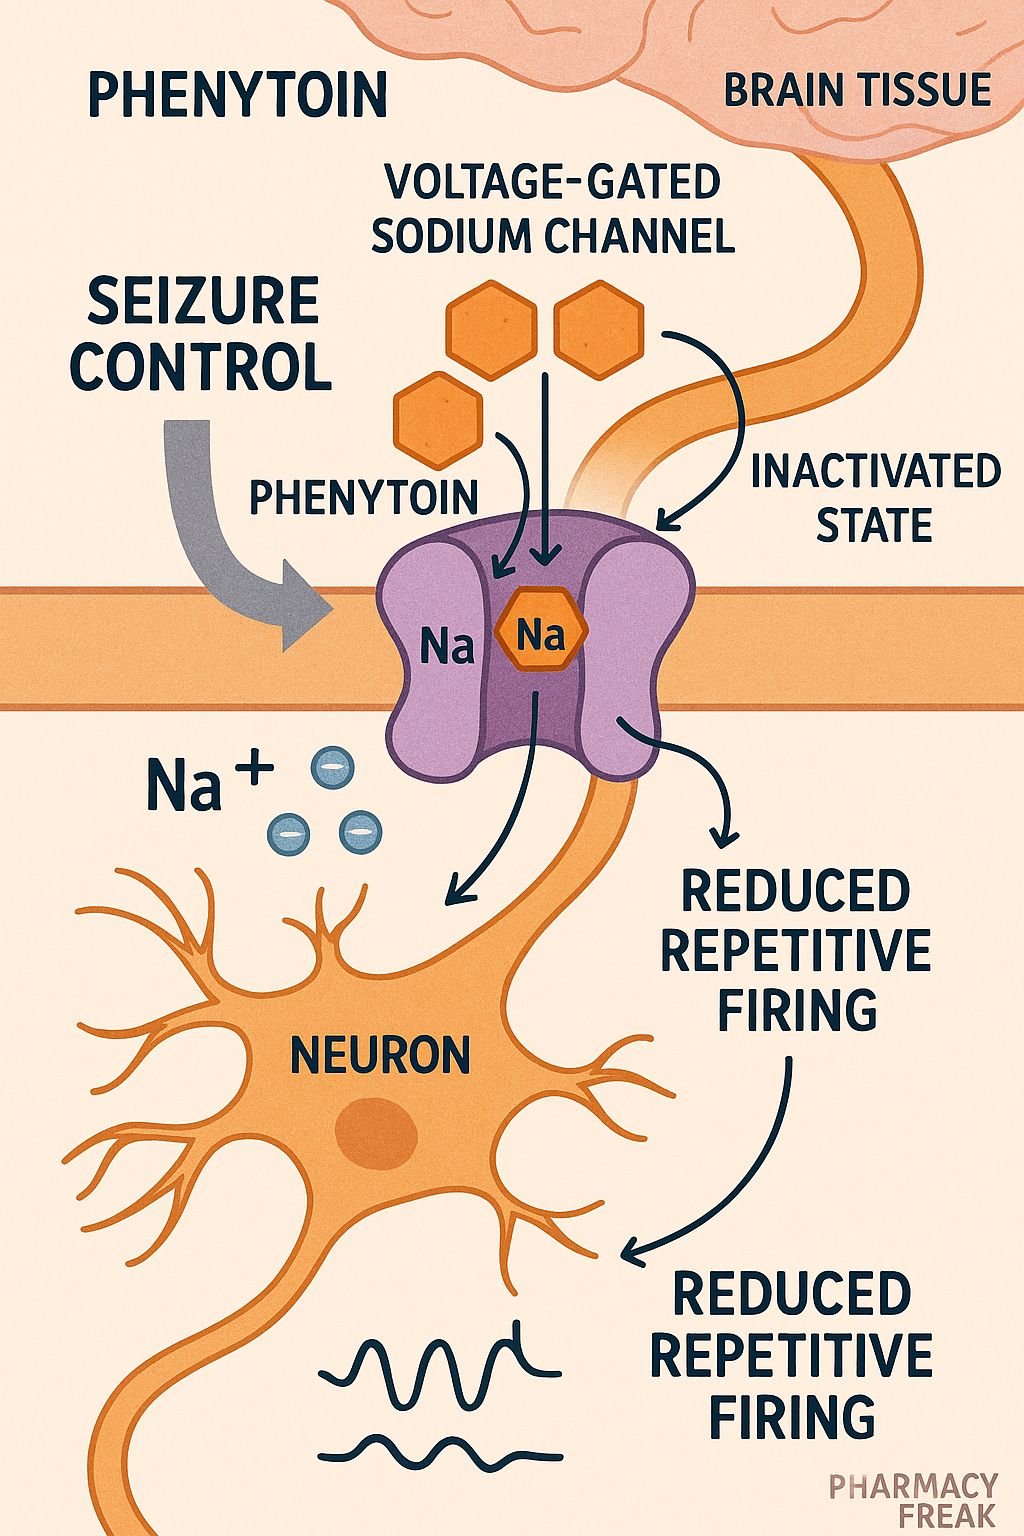
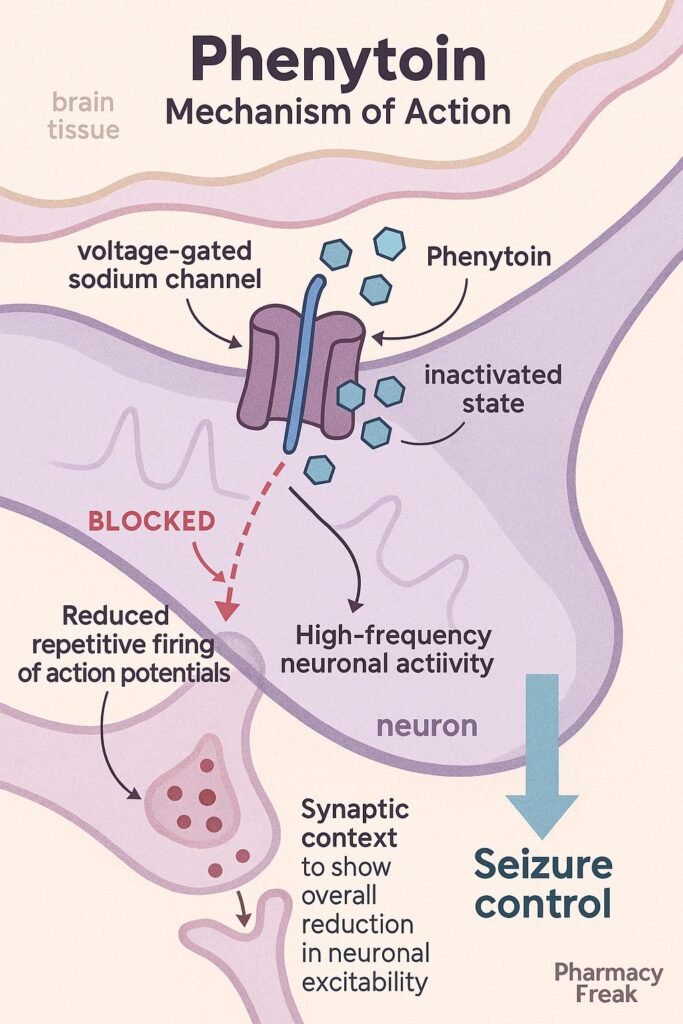
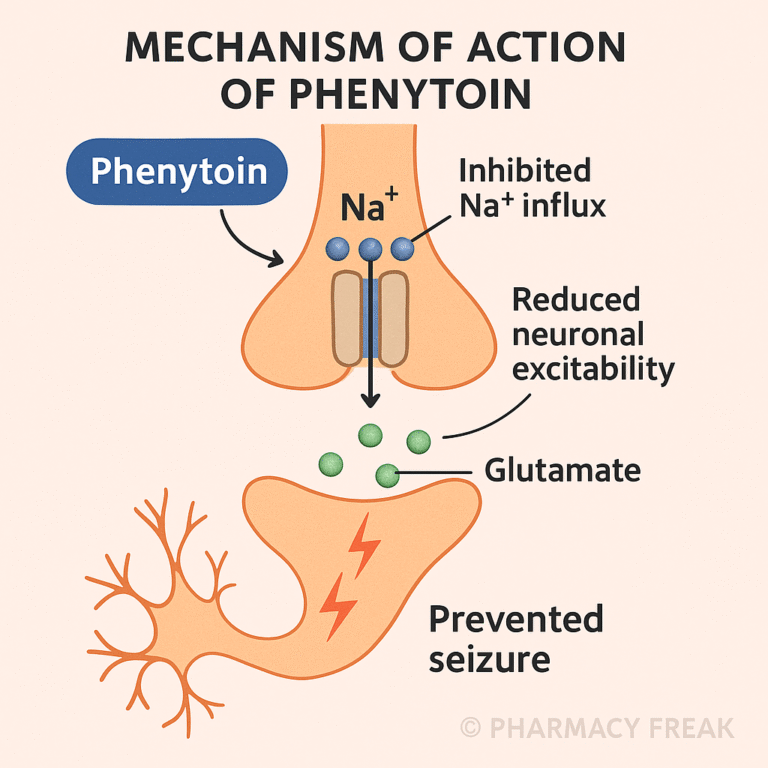
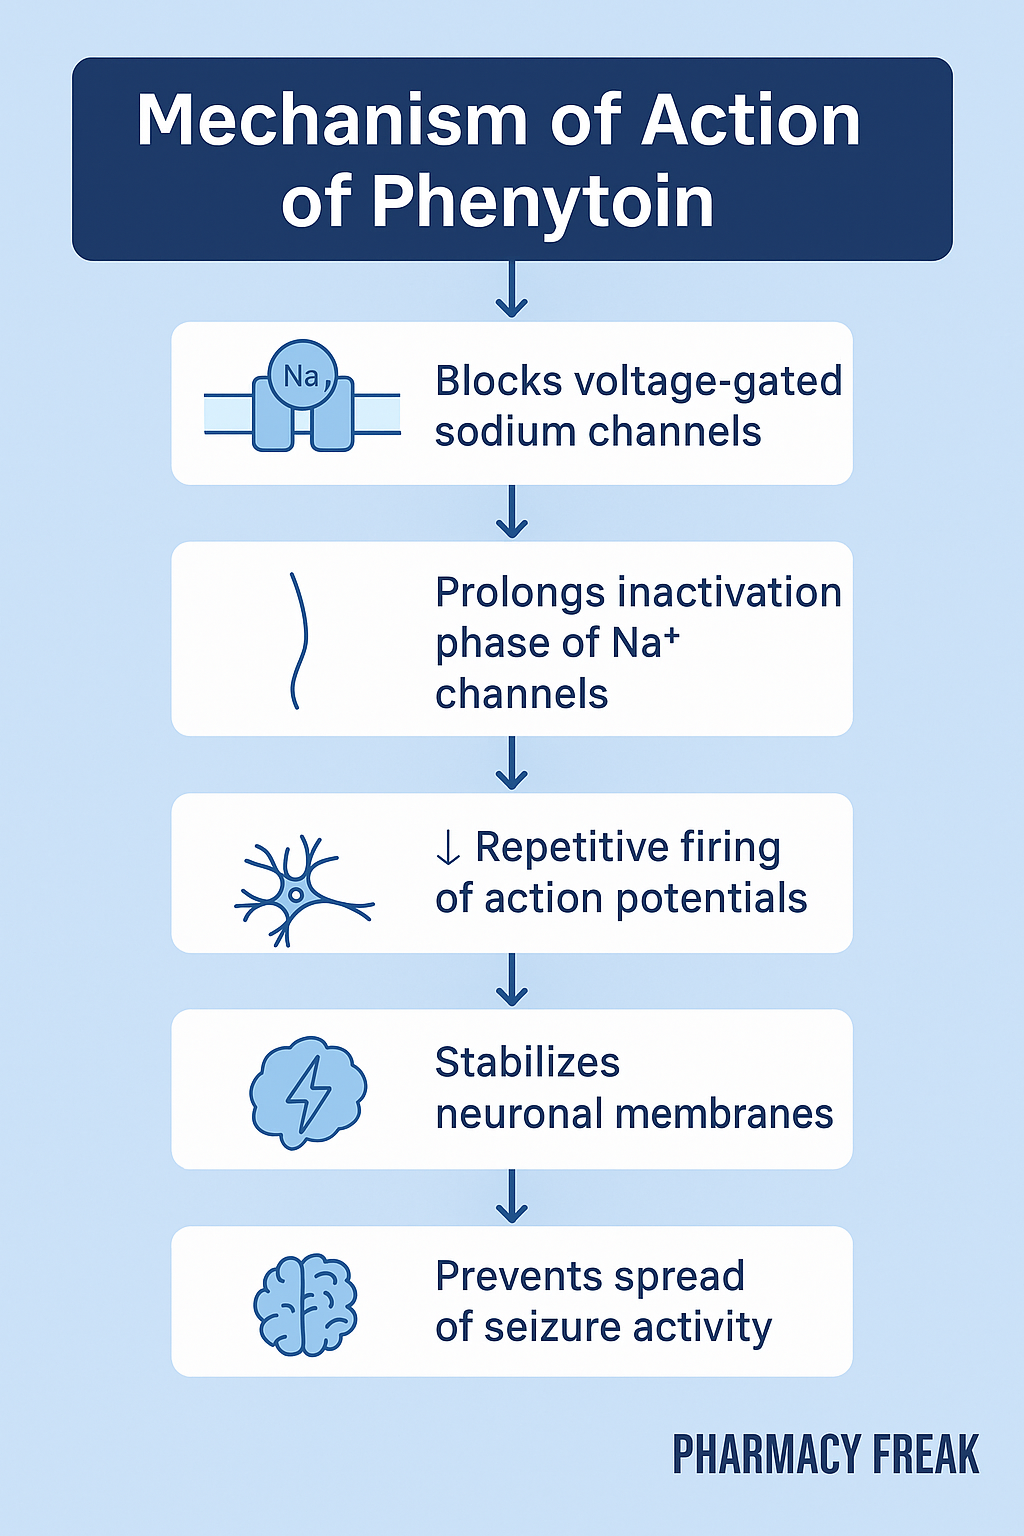
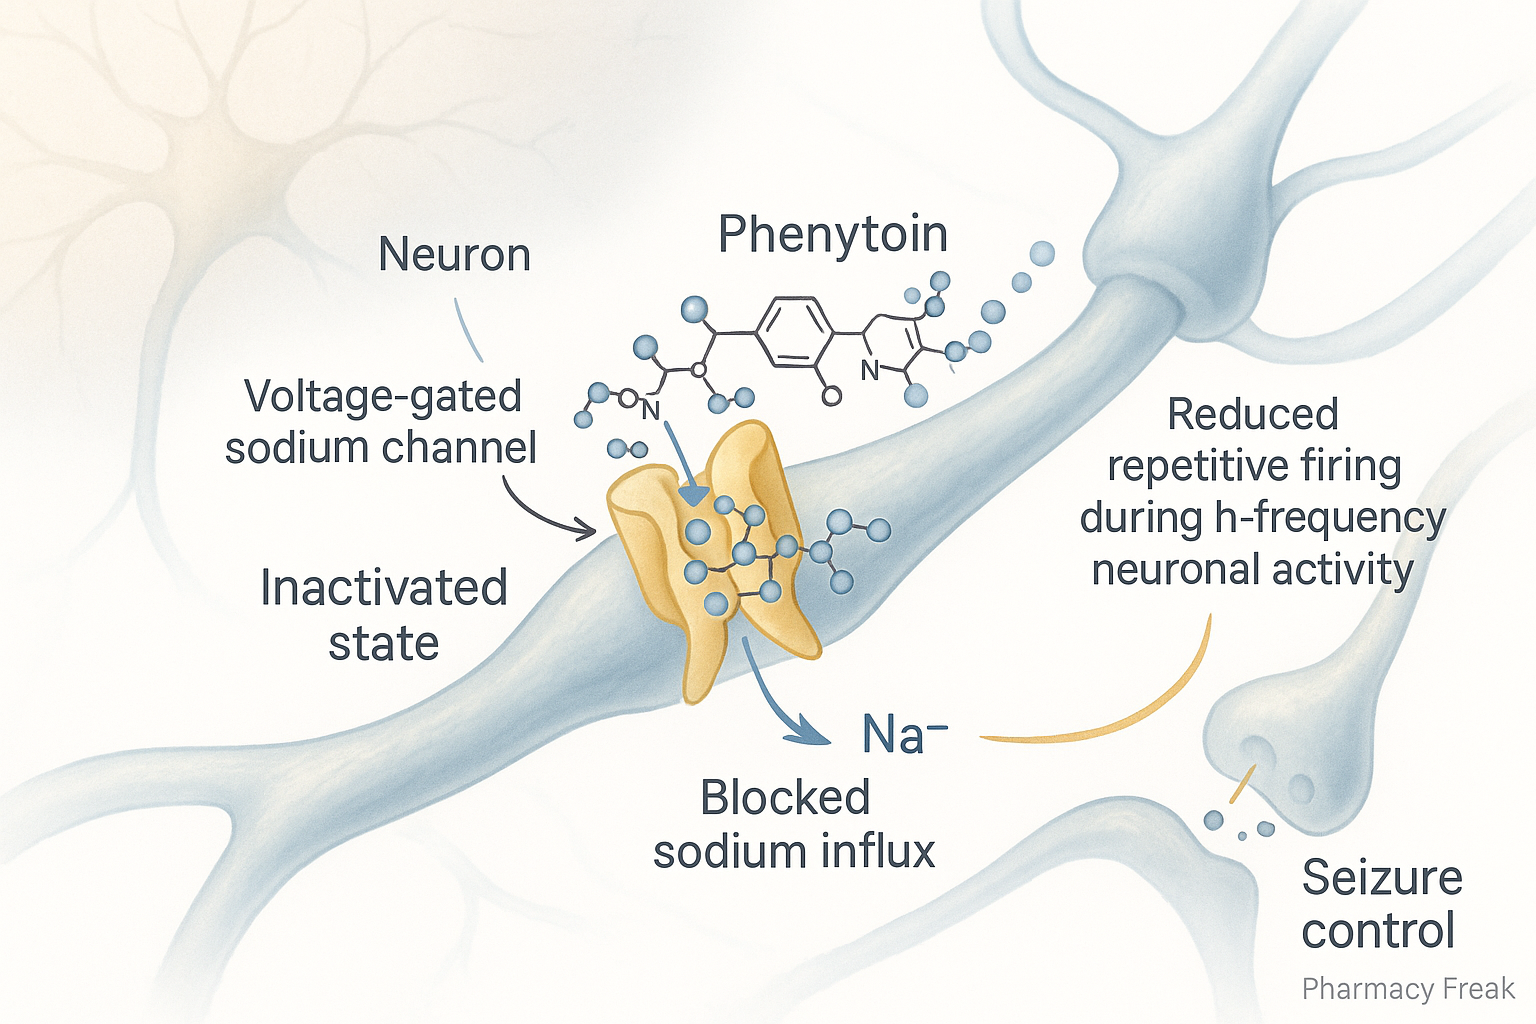
Phenytoin blocks voltage-gated sodium channels in their inactivated state. Most anticonvulsants do something similar, but phenytoin is picky about timing. It only binds when neurons are firing rapidly — the faster the firing, the more drug gets trapped in the channel. This is called use-dependence or frequency-dependent blockade. Here's what that means practically. When a seizure starts spreading through cortex, the neurons fire in abnormally rapid sequences. Phenytoin locks onto those overactive channels and prevents the sodium influx needed to regenerate the action potential. Normal neurons firing at regular rates stay mostly unaffected because the drug dissociates fast enough between spikes. The binding site is on the intracellular portion of the sodium channel alpha subunit. Phenytoin doesn't block the pore itself — it stabilizes the inactivated conformation so the channel can't reset quickly. Recovery from inactivation gets delayed, sometimes by hundreds of milliseconds depending on concentration.
This mechanism explains why phenytoin works well for focal seizures and tonic-clonic seizures but fails completely for absence seizures. Absence seizures involve thalamocortical oscillations at 3 Hz that don't depend on the same sodium channel dynamics in the same way. Actually giving phenytoin to someone with absence epilepsy can make things worse — which brings me back to that patient I mentioned.
Get the Full Details
What Nobody Tells You About The Kinetics
Phenytoin follows zero-order kinetics at therapeutic doses. That's the practical implication of its nonlinear pharmacokinetics. Once you exceed the metabolic capacity of hepatic enzymes — mainly CYP2C9 and to a lesser extent CYP2C19 — small dose increases produce disproportionately large concentration jumps. I learned this the hard way after a patient went from 300 mg daily to 350 mg daily. The dose increase looked reasonable on paper — about 17 percent more. Two weeks later her level was 28 mcg/mL instead of the target 10-20. She had nystagmus, ataxia, and mild confusion. We dropped back to 300 mg and waited ten days for steady state again. The Michaelis-Menten parameters vary wildly between individuals. Vmax — the maximum metabolic rate — can range from about 4 to 15 mg/kg/day across different patients. Km, the concentration at half-maximal velocity, sits around 4-5 mcg/mL typically. A patient with low Vmax needs dramatically less drug than someone with high Vmax, even at identical body weight.
This is why I always calculate using the Michaelis-Menten equation before adjusting doses. The standard approach is to measure two steady-state levels at different doses, then solve for Vmax and Km individually. Once you have those numbers, you can predict the exact dose needed for any target concentration. It usually takes about fifteen minutes of calculation instead of weeks of trial and error. The formula is straightforward: Dose = (Vmax × Target Concentration) / (Km + Target Concentration). Plug in your patient-specific Vmax and Km, solve for the required daily dose. Worked for me every time after I stopped guessing.
Drug Interactions Worth Remembering
Enzyme inducers like carbamazepine, rifampin, and chronic alcohol use increase phenytoin metabolism. These patients often need 50 to 100 percent more drug than the standard dose to maintain therapeutic levels. I once saw a patient on rifampin for tuberculosis who required 600 mg daily just to stay in range. Conversely, valproic acid displaces phenytoin from protein binding sites and inhibits its metabolism simultaneously. Total phenytoin levels might look normal or even low, but the free fraction doubles. Always check free phenytoin levels when valproate is involved, especially if albumin is low. Fluconazole, isoniazid, and metronidazole inhibit CYP2C9 and can push phenytoin levels up dangerously. I've seen cases where adding fluconazole for a fungal infection spiked phenytoin to toxic ranges within a week. Dose reduction by 25 to 50 percent is usually necessary when starting these agents.
Monitoring Realities
Total phenytoin levels assume normal albumin and normal renal function. Both assumptions fail frequently in the populations that actually receive this drug. Critically ill patients, elderly patients, and those with renal failure all have altered protein binding and altered clearance. The Sawchuk-Zaske method adjusts total phenytoin for albumin and creatinine clearance. It gives you an estimated corrected level that's closer to reality. I use it routinely now instead of relying on uncorrected values. Free phenytoin measurement is the gold standard when binding is uncertain. It costs more and takes longer, but it prevents dosing errors that total levels would miss. In practice, I order free levels whenever albumin is below 3.5 g/dL or creatinine clearance is below 30 mL/min.
Timing matters too. Steady state requires about five half-lives, which translates to roughly seven to fourteen days at therapeutic doses. Drawing a level too early gives you false reassurance. I always wait at least ten days after any dose change before checking levels.
When Phenytoin Fails Completely
Newer anticonvulsants have largely replaced phenytoin for chronic seizure management in many settings. Levetiracetam, lamotrigine, and lacosamide all have cleaner pharmacokinetic profiles, fewer drug interactions, and linear dosing. Phenytoin still has places — acute seizure control, certain structural epilepsies, and resource-limited settings where cost matters. The cosmetic side effects are real too. Gingival hyperplasia affects up to 50 percent of patients on long-term phenytoin. Hirsutism, coarsening of facial features, and osteomalacia round out the list. Young patients and women tend to notice these changes first and drop the medication. Peripheral neuropathy develops insidiously with chronic use. I've lost track of the number of patients who blamed their numbness on diabetes or aging without considering the phenytoin they'd been on for years. Checking B12 and folate helps, but stopping the drug is what actually reverses the symptoms — if caught early enough.
Cerebellar atrophy on MRI has been documented in long-term phenytoin users. It's rare but serious, and usually irreversible. I screen for this in patients on the drug for more than five years who complain of balance issues or fine motor deterioration.
A Practical Loading Protocol
For acute seizure control, the standard loading dose is 15 to 20 mg/kg IV at no faster than 50 mg/min in adults. Cardiac monitoring is essential because rapid infusion causes hypotension and arrhythmias — mostly QT prolongation and bradycardia. I slow the rate to 25 mg/min in anyone with known conduction disease or on beta-blockers. Oral loading is an option for patients who can't tolerate IV access, but absorption is erratic and unpredictable. The bioavailability ranges from 80 to 100 percent depending on the formulation and gastric emptying. I prefer IV loading whenever possible and switch to oral maintenance once levels are therapeutic. Renal and hepatic impairment don't dramatically change the initial loading dose because loading depends on volume of distribution, not clearance. But maintenance dosing requires careful adjustment. I typically start at 50 percent of the standard maintenance dose and titrate based on levels and clinical response.
Folate supplementation is standard practice for patients on chronic phenytoin. The drug interferes with folate metabolism and can cause megaloblastic anemia over time. I prescribe 1 mg daily and check CBC with differential every six months. Vitamin D and calcium supplementation address the bone loss risk. Phenytoin induces CYP3A4, which accelerates vitamin D catabolism. Baseline DEXA scans and annual monitoring make sense for patients on the drug long-term, especially postmenopausal women and elderly men.