Reading the Pheochromocytoma Endocrine Society Guidelines Without Losing Your Mind
The 2014 Endocrine Society Clinical Practice Guidelines on Pheochromocytoma and Paraganglioma are still the most referenced document in the field, even though they are over a decade old at this point. The 2022 ENETS consensus and the 2024 ACC/AHA updates have added nuance, but most clinicians still reach for the Endocrine Society doc first when a patient walks in with a suspicious adrenal mass and a headache that won't quit. The core recommendation is straightforward: measure plasma free metanephrines or 24-hour urinary fractionated metanephrines before you touch any imaging. This is step one, not step two. I see too many people scan first and biochemically confirm after, which flips the entire algorithm on its head and wastes money. The guidelines specify that plasma free metanephrines have a sensitivity of about 97 percent and specificity around 90 percent when measured under supine resting conditions. Urinary fractionated metanephrines run slightly lower on sensitivity but are more practical for outpatient follow-up because patients don't have to sit upright for 30 minutes before the draw. The guidelines say plasma is preferred if you can actually get the collection conditions right. In practice, they rarely are right.
Here's the thing nobody tells you during residency. If you draw plasma metanephrines with the patient sitting upright, your false positive rate climbs dramatically. I had a patient last year whose plasma free metanephrines came back at 2.5 times the upper limit of normal. Sitting position, anxious phlebotomy, caffeine that morning. We repeated it supine after 30 minutes of rest and it dropped to 1.1 times the ULN. Borderline. She didn't have a pheo. That single repeat saved her from an unnecessary MRI and months of anxiety.
Imaging Strategy After Biochemical Confirmation
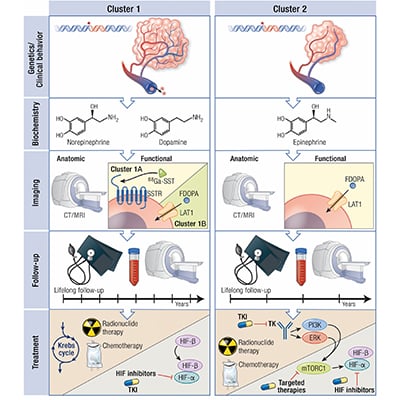
Once you've confirmed elevated metanephrines, the guidelines recommend CT or MRI of the abdomen and pelvis as first-line localization. 123I-MIBG scintigraphy is recommended when there is metastatic disease, extra-adrenal location, or familial syndrome. PET imaging with 18F-FDOPA, 18F-FDG, or 68Ga-DOTATATE has largely replaced MIBG in many centers for metastatic workup, even though the original guidelines predate this shift. The guidelines do mention genetic testing for all patients diagnosed with pheochromocytoma or paraganglioma. This is non-negotiable and it's one of the most underimplemented recommendations I see in clinical practice. About 40 percent of these tumors are hereditary. If you're not sending germline testing, you're missing something significant. The recommended panel includes VHL, RET, NF1, SDHD, SDHC, SDHB, SDHAF2, TMEM127, MAX, and FH. SDHB mutations in particular carry a higher risk of malignancy and extra-adrenal recurrence, so knowing that status changes your surveillance cadence. I ran into a case recently where a patient had a sporadic-appearing left adrenal pheo. Standard resection, pathology confirmed, everything seemed closed. But the genetic panel came back with an SDHB mutation. That changed the entire follow-up plan. Instead of annual imaging, we moved to biannual whole-body MRI for at least 15 years because SDHB-related recurrences can happen decades later. The guidelines support this, but the original text doesn't emphasize the timeframe strongly enough for most clinicians to internalize it.
Get the Full Details

Preoperative Preparation That Actually Matters
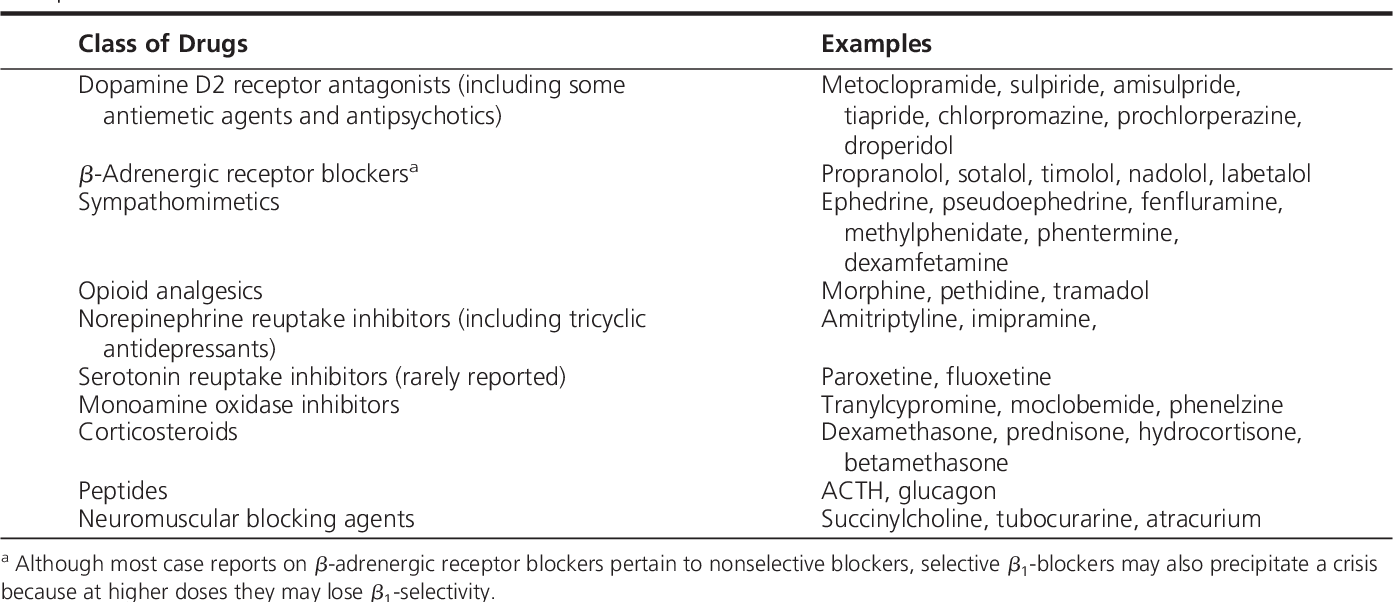
Alpha-blockade before surgery is the single most important preoperative step. The guidelines recommend phenoxybenzamine starting 7 to 14 days before surgery at doses that control blood pressure and prevent intraoperative hypertensive crises. The typical target is systolic blood pressure below 120 millimeters mercury in the sitting position and above 100 millimeters mercury when standing, with a mild orthostatic drop being acceptable and expected. Volume expansion follows alpha-blockade naturally because these patients are chronically vasoconstricted and volume-depleted. The guidelines suggest a liberal salt intake and fluid consumption once alpha-blockade begins. This isn't optional. I've seen surgeons skip the volume expansion discussion and then deal with refractory hypotension immediately after tumor venous sacrifice. That's a predictable and preventable complication. Calcium channel blockers like amlodipine can be added if alpha-blockade alone doesn't control blood pressure. Beta-blockers should never be started before adequate alpha-blockade. Starting a beta-blocker first causes unopposed alpha stimulation and can trigger a hypertensive crisis. This is classic board question material and also classic real-world mistake material. I read a case report where a patient was started on metoprolol for incidental tachycardia before pheochromocytoma was suspected, and they went into crisis. The sequence matters and the guidelines state it clearly, but clinicians still get it wrong.
When the Guidelines Fall Short
The original 2014 guidelines don't adequately address the management of incidentally discovered adrenal lesions that turn out to be non-functioning on metaB workup but show mild catecholamine elevation. These "gray zone" patients are increasingly common as CT scanning becomes more sensitive. The guidelines suggest repeating testing in 6 to 12 months for equivocal results, but they don't give clear thresholds for when to escalate to imaging versus when to watch. There's also no clear guidance on the use of minimally invasive adrenalectomy for large tumors greater than 6 centimeters. The guidelines lean toward open adrenalectomy for large or suspicious masses, but laparoscopic approaches are now widely performed for tumors up to 10 centimeters in experienced hands with good outcomes data. If you're following the guidelines strictly, you might recommend open surgery for a 7-centimeter tumor that a skilled surgeon could safely remove laparoscopically. The guidelines lag behind surgical practice here. Another gap is the management of pregnant patients with pheochromocytoma. The guidelines acknowledge this population exists and recommend alpha-blockade followed by surgical resection in the second trimester when feasible, but the evidence base is thin. Most recommendations here are based on case series and expert opinion rather than robust trials. If you're managing a pregnant pheo patient, you're essentially making decisions outside the guideline framework.
Practical Takeaways
The Pheochromocytoma Endocrine Society Guidelines remain the foundational reference for this condition. They cover biochemical diagnosis, imaging localization, genetic testing, preoperative preparation, and surgical management in a structured way. The document is freely available on the Endocrine Society's website at endocrine.org. You don't need a subscription to read it. The key practical points are: draw metanephrines under proper conditions before imaging, confirm with repeat testing if borderline, order germline genetic testing for every patient, start alpha-blockade well before any surgery, never give beta-blockers before alpha-blockade, and plan for long-term surveillance in SDHB carriers. Everything else in the guidelines is useful context, but those five items are the ones that change patient outcomes most directly. If you want the full text with all the grading and recommendation strength annotations, go straight to the source document. Third-party summaries always trim the nuance that matters when you're actually making clinical decisions.