So you need to figure out physical exam forms. Good luck.
I have been through enough clinic implementations to know that most people treat a Physical Exam Form like it is a simple document you download and fill out. It is not. It is a data structure that becomes the backbone of every billing cycle, every quality metric pull, and every time a provider claims they never saw a particular finding documented. I learned that the hard way in 2019 when we tried rolling out a custom form across three satellite clinics using a template we found on a hospital vendor site. The template assumed a standard adult wellness visit. Our patients were mostly pediatric and geriatric. The form had no branching logic, no conditional fields, and no way to handle multiple complaints in a single encounter. Within two weeks, half our providers were circumventing the form entirely and typing everything into free-text notes because the form made them click through twelve irrelevant sections just to document a sore throat. That is not a technology problem. That is a workflow problem that manifests as a technology problem.
What a Physical Exam Form Actually Is
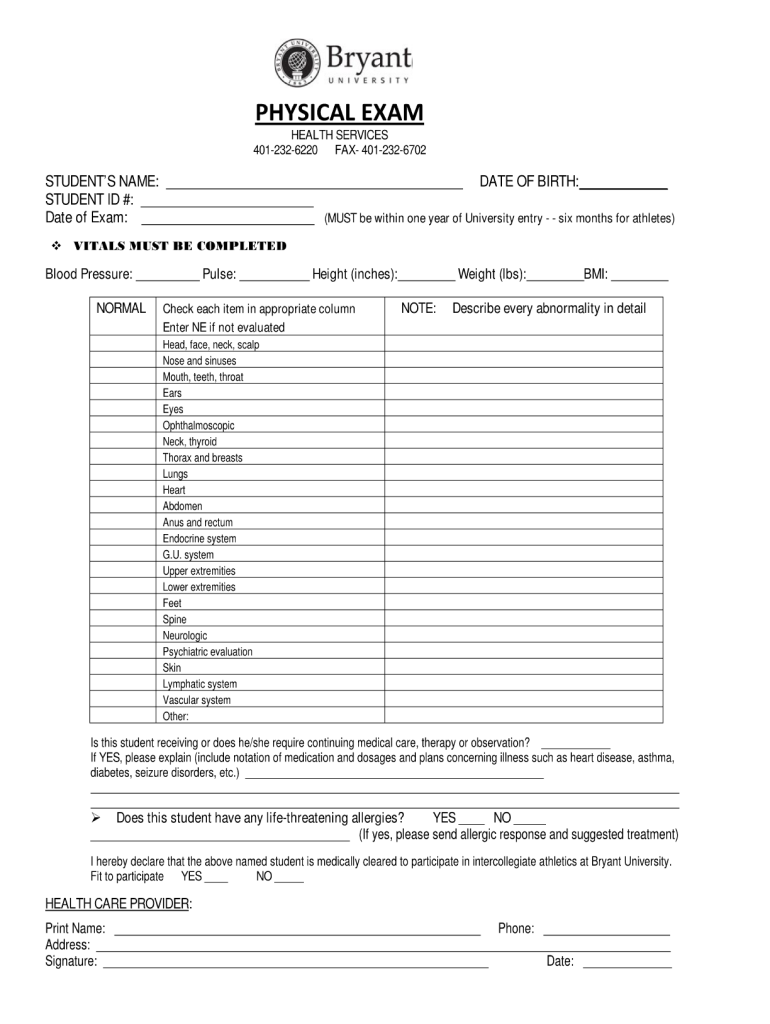
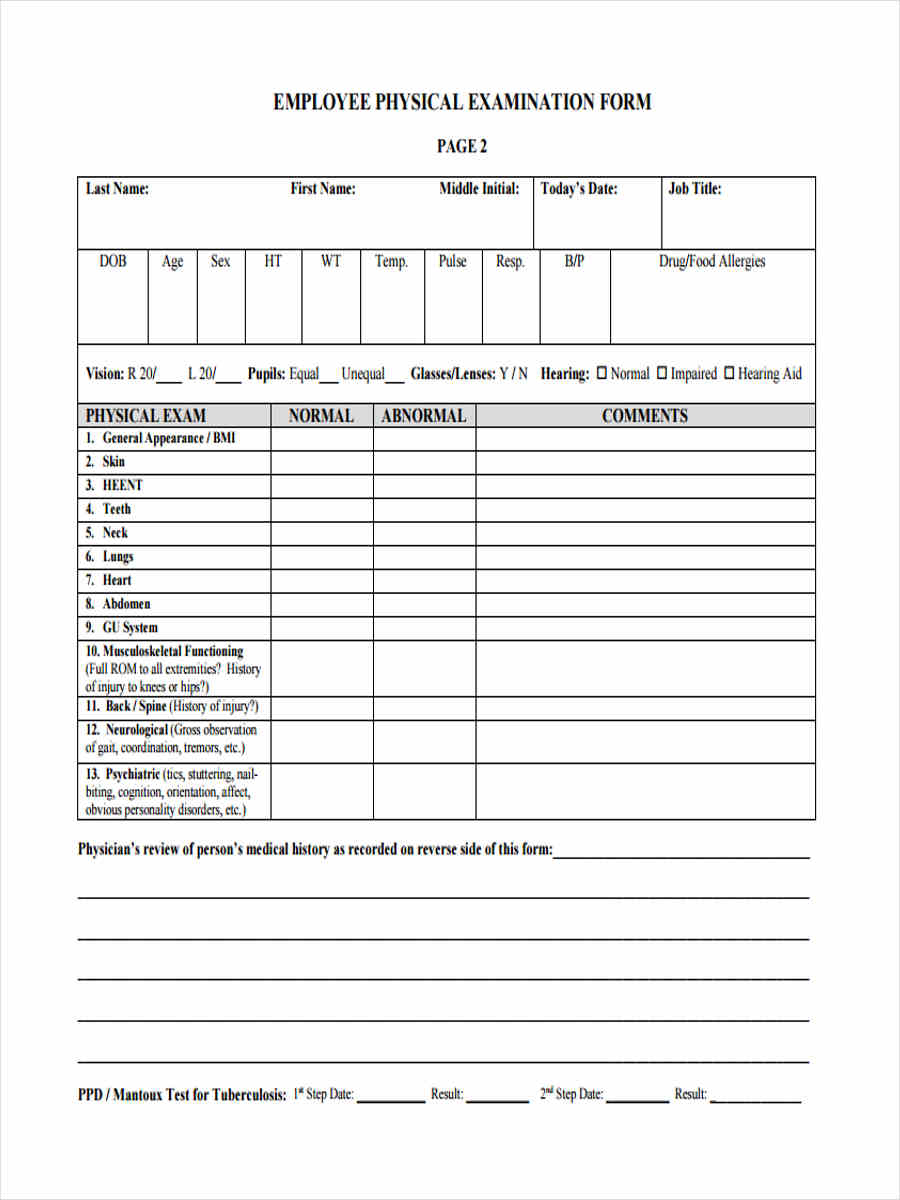
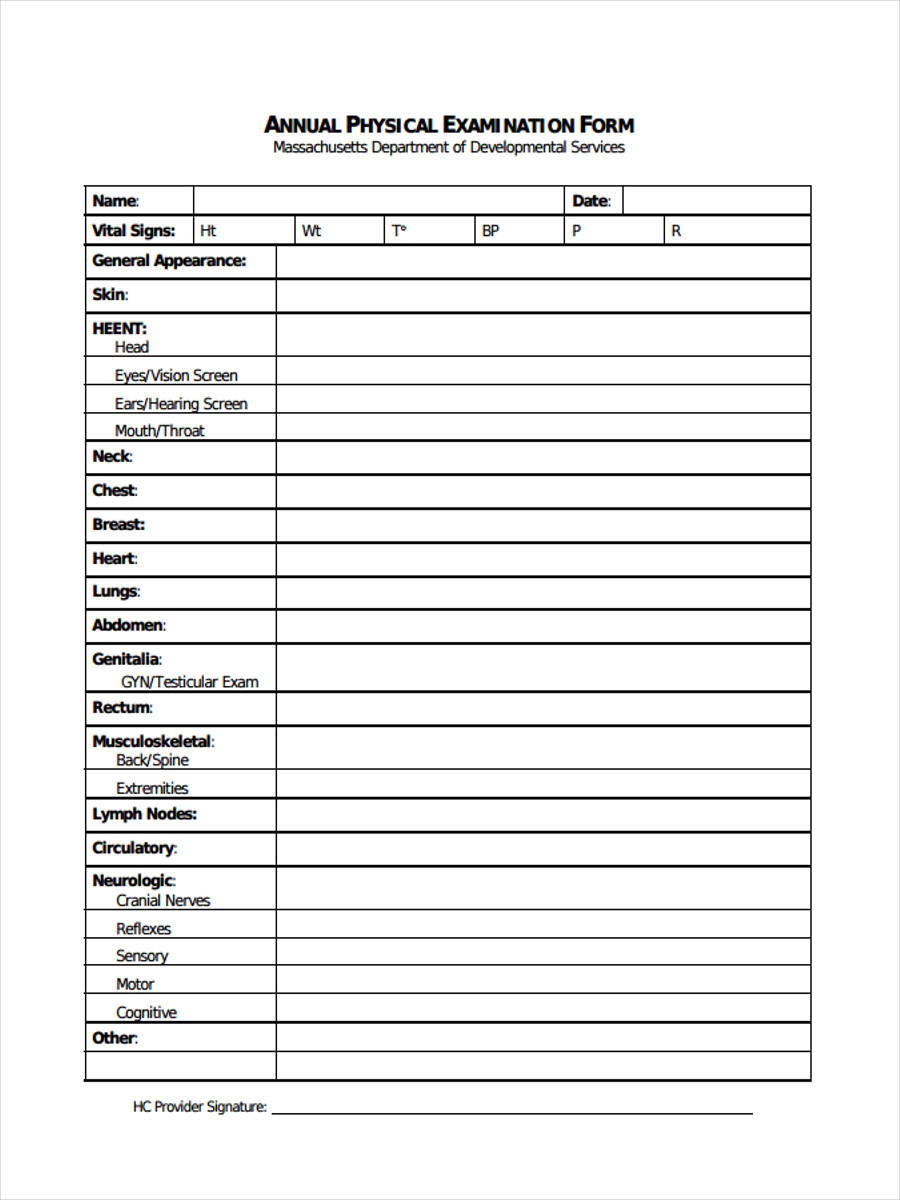
A Physical Exam Form is a structured data-capture interface that records objective clinical findings organized by body system or anatomical region. It translates what a clinician observes, palpates, percussion-tests, or auscultates into discrete, searchable fields. The output feeds into the electronic health record, supports billing coding requirements, enables population health queries, and sometimes gets pulled into quality reporting dashboards that nobody asks about until an auditor does. The form itself is usually built inside an EHR system, a practice management platform, or a standalone clinical documentation tool. It consists of sections like general appearance, vital signs, head and neck, cardiovascular, respiratory, abdominal, neurological, musculoskeletal, skin, and psychiatric or mental status depending on the visit type. Each section contains checkboxes, dropdowns, free-text boxes, and sometimes structured fields for severity grading like the Glasgow Coma Scale or Richmond Agitation-Sedation Scale. Here is something most people miss. The most important part of a Physical Exam Form is not the layout. It is the downstream dependency chain. Every field on that form has a purpose beyond what the provider sees. A checkbox for decreased breath sounds gets parsed into an ICD-10 code mapping. A negative finding in one system can trigger a prior authorization denial if it contradicts a symptom entered elsewhere in the encounter. The form is not just documentation. It is a transactional object.
How to Build or Configure One That Actually Works
Start by mapping the encounter types your clinic handles before you design a single field. If you do ten different visit types and only design for one, you will spend the next six months patching it. I had a client who designed a comprehensive Physical Exam Form for routine adult exams and then tried to force it into urgent care visits. The form had forty-eight fields. An urgent care visit typically takes four to six minutes. Providers were spending eleven minutes just clicking through the form, which meant they were either finishing late or skipping sections entirely. We ended up building three separate forms instead and reduced average documentation time from eleven minutes to four minutes and twelve seconds. Use conditional logic. If a provider selects abdominal pain as a chief complaint, the form should surface relevant abdominal exam fields and suppress unrelated sections like breast exam or prostate exam. If you are using an EHR like Epic or Cerner, this is built-in. If you are using something lighter or building your own, you need to either integrate a conditional rendering layer or accept that your form will always feel bloated. Group fields by clinical workflow, not by textbook anatomy. A physical exam in real life follows a sequence: inspection, palpation, percussion, auscultation. But the way a provider actually works is they think in terms of systems they need to address before the patient gets dressed. Structure the form to match that rhythm. When we reorganized a form from textbook order to workflow order for a cardiology practice, their documentation compliance rate jumped from sixty-three percent to eighty-nine percent in the first month. Not because the form was better. Because it was faster to use.
Get the Full Details

Include a macros or templates section. Every provider has phrases they repeat. Breathe symmetrically, clear to auscultation, normocephalic, atraumatic. A good Physical Exam Form lets you save custom snippets and insert them with a single click. I recommend limiting this to pre-approved language that your compliance team reviews quarterly. Otherwise you end up with three doctors each using five different versions of the same phrase and your data becomes impossible to query reliably.
Common Pitfalls Nobody Warns You About
The first pitfall is over-documentation. More fields does not mean better documentation. It means more clicks, more fatigue, and more missed fields because the form is exhausting. I once audited a practice where the Physical Exam Form had twenty-two fields under cardiovascular alone. Most of those fields were checked negative every single time. The other ten providers at the same practice used a five-field cardiovascular section and caught every clinically significant finding. The difference was not skill. The difference was cognitive load. The second pitfall is static forms in a dynamic environment. Your form needs version control and a review cycle. I watched a clinic use the same Physical Exam Form for eight years without updating it. In year six, their payer mix shifted significantly toward Medicare Advantage plans that required specific documented elements for risk-adjusted payment. The form never captured those elements. They lost approximately forty-seven thousand dollars in supplemental payments that year because a field they never added could have generated it automatically. The third pitfall is ignoring the copy-paste problem. Electronic forms make it trivially easy to copy a previous encounter's exam findings into the current one. This happens constantly. I found a case where a provider had documented bilateral crackles for six consecutive monthly visits spanning eighteen months. The patient was not hospitalized during that period. The cramps were not worsening. The provider had simply copy-pasted the same text for half a year. This is a documentation liability that can look like fraud if an auditor notices it. Build in alerts for identical findings repeated across encounters. Even a simple flag that says this section matches a prior encounter within thirty days is enough to make providers pause and verify.
Practical Considerations When Choosing or Building
If you are embedded in Epic, use the SmartPhrase and SmartText ecosystem. It is imperfect but it is what everyone already knows. If you are on a smaller platform like AdvancedMD or aabbott, check whether they support custom form builders natively before you buy a third-party add-on. Third-party add-ons create sync issues and support tickets that multiply when your EHR updates. If you are building from scratch, use a database-first approach. Design your data model before you design the interface. I have seen teams build beautiful UIs first and then realize the underlying schema could not store the data they needed in a queryable format. That means rewriting both the UI and the backend. It happens more often than you would think. Test with actual providers before rolling out. Not IT staff. Not nurses. The people who will click through this form at two in the afternoon after their seventh patient. Give them five real encounter scenarios and time them. If any scenario takes longer than eight minutes, simplify it.

One last thing. Document your form logic somewhere. Not in a separate manual. Just a comment block in the configuration or a one-page diagram showing which fields trigger which downstream calculations. Six months from now, when the person who built it leaves, someone will need to understand why a specific field exists and what it feeds into. If that knowledge lives only in one person's head, it dies with them.