How I Track And Manage Adolescent Growth - A Practical Guide
I spent about six years running a pediatric growth clinic before moving into private consulting, and honestly the hardest part wasn't the science. It was helping parents understand that growth charts are reference tools, not verdicts. Kids don't grow in straight lines. They grow in spurts, plateaus, and weird temporary deviations that look alarming but mean absolutely nothing. If you are trying to understand Physical Growth In Adolescence for your own kid, or for work, start with the basics of what is actually happening biologically and then worry less about the noise in the data.
Understanding Physical Growth In Adolescence
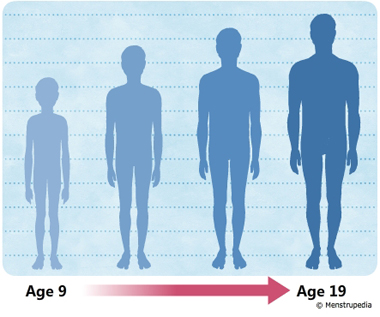
Adolescent growth is driven by the hypothalamic-pituitary-gonadal axis kicking into gear. Estrogen and testosterone both play roles here, and the interesting part most people miss is that estrogen is actually the primary driver of epiphyseal closure in both sexes. Testosterone converts to estrogen through aromatase. That is why boys often have a slightly later growth spurt than girls but continue growing longer before their growth plates seal. The average girl hits her peak height velocity around 11 to 12 years old, gaining about 8 to 10 centimeters in a single year at the peak. Boys hit theirs around 13 to 14, peaking at roughly 9 to 11 centimeters per year. These numbers come from population averages. Any individual kid can fall outside them by a wide margin and still be perfectly healthy. Here is where it gets messy in practice. I had a case about three years ago where a boy came in at the 3rd percentile for height, flagged for possible growth hormone deficiency. His bone age was slightly delayed by about six months, his IGF-1 was borderline low, and his parents were convinced something was wrong because his uncle was tall. We did the full workup anyway. Turns out the kid was a constitutional delay of growth and puberty. He was healthy. His growth velocity was normal for his stage. He just started his spurt later. Reassurance was the treatment. He ended up hitting a reasonable adult height for his family pattern. The whole episode cost the family about four thousand dollars in tests and caused real anxiety for no clinical reason.
This happens constantly. Parents see a percentile drop and assume pathology. It is usually just normal variation.
Get the Full Details

What Actually Drives Growth During This Period
There are several factors pulling on a growing teenager. Nutrition is the biggest one that people actually have control over. Protein intake, calories, and micronutrients like zinc and vitamin D matter more than most parents realize. A kid eating consistently below their energy needs will not grow at their genetic potential regardless of how much they sleep or exercise. Sleep is non-negotiable for growth hormone secretion. Most of the daily GH pulse happens during deep slow-wave sleep, which peaks in the first half of the night. Teenagers who stay up until midnight and wake at seven are structurally missing the best GH window. This is not speculation. It is measured. Chronic stress also suppresses growth. I do not mean everyday school stress. I mean sustained physiological stress from bullying, family instability, or eating disorders. There is a condition called psychosocial short stature where kids literally stop growing due to emotional deprivation. It reverses when the environment improves. That is not metaphorical. I saw it happen.
Body composition matters too. Both ends of the spectrum cause problems. Significant underweight status delays puberty and slows growth velocity. Conversely, excess adipose tissue increases aromatase activity, which accelerates bone age advancement and can actually shorten final adult height in girls by causing earlier growth plate fusion.
How To Actually Measure And Monitor Growth At Home
You do not need a clinic to track growth. You need a proper stadiometer or a flat wall with a rigid measuring tape and a right angle. The kitchen doorframe trick works fine if you are consistent. Mark the hairline with a pencil, measure from the floor to the mark, and record the date along with the measurement. Here is the practical method I tell parents to use. Measure every three months, same time of day, same conditions. Shoes off. Shoulders straight. Heels, buttocks, and back of head against the wall. Record to the nearest millimeter. Plot it on a standard growth chart. CDC charts are fine for US populations. WHO charts work better for younger children. Use the same chart consistently so you can see trends. The most important number is not the percentile. It is the velocity. How many centimeters per year is this kid actually growing? A kid who stays at the 10th percentile but grows at a normal velocity is fine. A kid who drops from the 50th to the 25th percentile over a year needs investigation regardless of where they land. Velocity tells you what is happening. Percentile tells you where they sit relative to other kids.
I keep a simple spreadsheet for tracking. Columns for date, height in centimeters, weight in kilograms, and a notes field for things like illness, stress events, or medications. The notes field catches context that pure numbers hide. That timeline last year showed me a growth deceleration that coincided exactly with my daughter starting high school and developing anxiety. The pediatrician caught it because I had the data.
When To Actually Worry
Most kids who come into my office worried about growth are fine. But there are red flags worth knowing. Start puberty before age 8 in girls or before age 9 in boys is precocious and needs evaluation. No sign of puberty by age 13 in girls or 14 in boys is delayed and deserves workup. A growth velocity below 5 centimeters per year outside of infancy is abnormally slow. Crossing two or more major percentile lines downward on a growth chart is concerning. Family history of autoimmune disease, thyroid issues, or untreated celiac disease should raise your threshold for getting checked. A child with known chronic illness like inflammatory bowel disease or cystic fibrosis needs regular growth monitoring regardless of how they feel. These conditions silently throttle growth before any other symptoms become obvious. Here is something people get wrong about growth. Tall parents do not guarantee tall kids. Genetics set a range, not a point. The mid-parental height calculation gives you an estimate with a range of about plus or minus 10 centimeters for boys and 8.5 centimeters for girls. A kid can end up at either end of that range. Nutrition and health determine where in that range they land.
Supplements And Growth
I will be blunt about this. Growth supplements marketed to teenagers are almost entirely unproven. The few studies that exist on products containing arginine, ornithine, or special herbal blends show minimal to no effect on final height. Some of these products even contain undisclosed ingredients that can affect hormone levels. The risk is real and the benefit is not. Vitamin D supplementation makes sense if a kid is deficient, and deficiency is common in northern latitudes and among darker-skinned teens who spend most of their time indoors. Zinc deficiency can impair growth, but that is also mostly a concern in populations with genuinely poor nutrition. If you are wondering whether to give supplements, get a blood test first. Empirical supplementation without a diagnosed deficiency is wasted money and potentially harmful. Prescription growth hormone is only appropriate for specific diagnosed conditions like growth hormone deficiency, Turner syndrome, chronic kidney disease, or children who are small for gestational age and fail to catch up by age 2 to 4. It is not a treatment for short stature caused by normal variation or late puberty. Using it outside those indications is expensive, requires daily injections for years, and has real side effects including increased intracranial pressure, insulin resistance, and slip capital femoral epiphysis. The average height gain from GH therapy in approved indications is about 5 to 10 centimeters over untreated expectations. That is meaningful for some kids and marginal for others.
The Bottom Line On Monitoring
Track height regularly. Pay attention to velocity more than percentile. Address nutrition, sleep, and stress before reaching for supplements or tests. Get medical evaluation for the red flags I listed above. Most growth concerns resolve with time and basic health optimization. The kids who actually need intervention are a small minority, and they benefit enormously from early recognition. One thing I wish more parents understood is that adolescent growth is highly variable and most variation is normal. The kids who grow the earliest often end up average height. The kids who grow the latest frequently surpass their early-maturing peers. Timing matters more than speed during adolescence. Patience and basic monitoring is usually the correct approach.


