What happens when you try to move your foot after bunion surgery
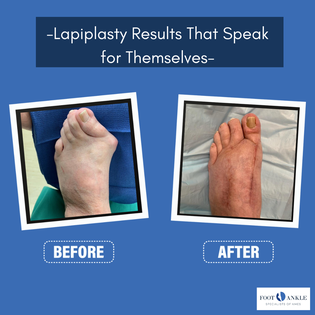
Most people think lapiplasty is the end of the road for their bunions. It isn't. The surgery fixes the bone alignment by locking the first metatarsal in place with a 3D correction, but that doesn't mean the rest of your foot stops being a problem. What most surgeons don't spend enough time on is what happens in the weeks after the incision closes. The joint capsule stiffens. The tendons adapt to the new position or fail to, depending on how aggressive your rehab is. I've seen patients who came out of surgery with perfect X-rays and still ended up with a stiff, painful first MTP joint because nobody told them about dorsiflexion losses during the early healing phase. The timeline generally breaks into three phases. Phase one runs from surgery through about week six, sometimes eight depending on your surgeon's protocol. During this window you're not doing much more than ankle pumps, toe wiggles if you're cleared for it, and gentle range of motion once the initial swelling drops enough that the therapist can work without causing tissue trauma. The big risk here is skipping mobilization entirely and ending up with adhesive capsulitis of the first MTP joint, which is a completely separate problem from the bunion itself. Phase two kicks in around week six or so when your surgeon gives you the all-clear for more active movement. This is where formal PT becomes critical. You're working on dorsiflexion, plantarflexion, inversion, eversion, and subtalar joint mobility. The first metatarsophalangeal joint needs to regain at least fifty to sixty degrees of dorsiflexion for normal gait. Anything less and you're compensating, which means your second toe takes overload, your knee starts tracking differently, and your hip follows shortly after. I had a patient last year who was at forty degrees of MTP dorsiflexion at twelve weeks post-op. We spent six weeks just on passive stretching and joint mobilizations before we saw meaningful improvement. She'd stopped PT at week eight because she felt fine and thought she was done. Feeling fine and being functionally normal are two different things after this kind of surgery.
Phase three is the return to activity phase, usually starting around week twelve. By this point you should be working on balance, proprioception, calf strength, and progressive weight-bearing activities. Gait training is non-negotiable if you haven't been walking normally since surgery. Most people develop an antalgic pattern within the first two weeks and never correct it without guidance. I always have my patients do a simple observation test: watch them walk on a flat surface barefoot. If the first toe doesn't bear weight during push-off, they're not ready to progress to jogging or agility work. One thing that catches people off guard is the swelling timeline. You can expect significant edema for six to twelve weeks, sometimes longer. Swelling directly limits range of motion. If you're fighting to get dorsiflexion and your foot is still puffy, part of that restriction is mechanical compression from fluid, not just scar tissue. Elevation and compression garments aren't optional accessories at this stage. They're part of the rehab protocol. I use a simple measurement approach: compare the circumference of the operative foot to the non-operative foot at the widest point of the forefoot. When those measurements are within ten millimeters of each other, I consider swelling to be sufficiently resolved for more aggressive joint mobilization. Another counter-intuitive point that people miss is that early motion doesn't compromise the surgical fix. The lapiplasty fixation system is designed to hold the metatarsal in place immediately. You're not going to disrupt the osteotomy by doing gentle toe bends or ankle circles. The hardware is what keeps it stable. The restriction comes from pain and swelling, not from the bones moving. That's why passive range of motion exercises starting in the first one to two weeks, even before formal PT begins, are actually protective. They prevent the joint capsule from adhering to itself while it's healing in a shortened position.
There are limitations to this approach that need to be stated plainly. Not everyone responds to PT the same way. Patients with pre-existing hallux rigidus, those who have had multiple prior foot surgeries, or people with connective tissue disorders like Ehlers-Danlos syndrome will have a harder time regaining full range of motion. In my experience, about fifteen to twenty percent of post-lapiplasty patients plateau at around forty-five to fifty degrees of dorsiflexion despite consistent therapy. That's functional for daily activities but insufficient for high-impact sports. If you're an athlete or someone who needs full range for work, you need to know this upfront so you can set realistic expectations and plan accordingly. The most common mistake I see is patients who stop PT too early because they're pain-free. Pain disappearing doesn't mean the tissues have remodeled. Collagen alignment in the joint capsule and surrounding soft tissues continues for up to eighteen months after surgery. The fact that you can walk without pain at week ten doesn't mean the first MTP joint has the mobility or strength it needs for the demands you're about to place on it. I always tell patients to continue their home exercise program for at least six months post-op, even after formal sessions end. Here's a practical routine that works for the early phase, assuming your surgeon has cleared you for it. Sit with your leg elevated and do ankle pumps — twenty repetitions every hour while awake. Then move to seated towel stretches, pulling your toes toward your shin gently without forcing through pain. Hold for thirty seconds, repeat three times. Once you're past the six-week mark and cleared for active motion, add seated MTP joint mobilizations. Use your thumb to gently glide the proximal phalanx dorsally relative to the metatarsal head. Small amplitude movements first, gradually increasing as tolerance allows. Never force a stretch that produces sharp pain. Dull pressure is acceptable. Sharp pain means you're irritating the healing tissues.
Get the Full Details

For the strength component, which becomes relevant around week eight to ten, start with short foot exercises. Have the patient try to shorten their foot by drawing the ball of the foot toward the heel without curling the toes. This activates the intrinsic foot muscles that atrophy rapidly after surgery. Progress to resistance band work for evertors and invertors by week ten to twelve. Calf raises come later, usually around week twelve, and should start double-leg before single-leg. Going single-leg too early puts excessive load on the first ray before the soft tissues have adapted. If you're looking for a structured program to follow between sessions, there are various printable guides available online from orthopedic associations and physical therapy boards. Just make sure any protocol you download has been reviewed or approved by a licensed physical therapist who understands post-surgical foot rehab. Generic ankle rehab sheets won't address the specific demands of first ray mechanics after lapiplasty. The bottom line is that lapiplasty corrects the deformity but doesn't rehab the foot. That's the patient and therapist's job after the surgeon's part is done. Skipping or rushing through any phase of the process creates compensatory problems that can be just as debilitating as the original bunion.