What Actually Happens in the First Few Weeks
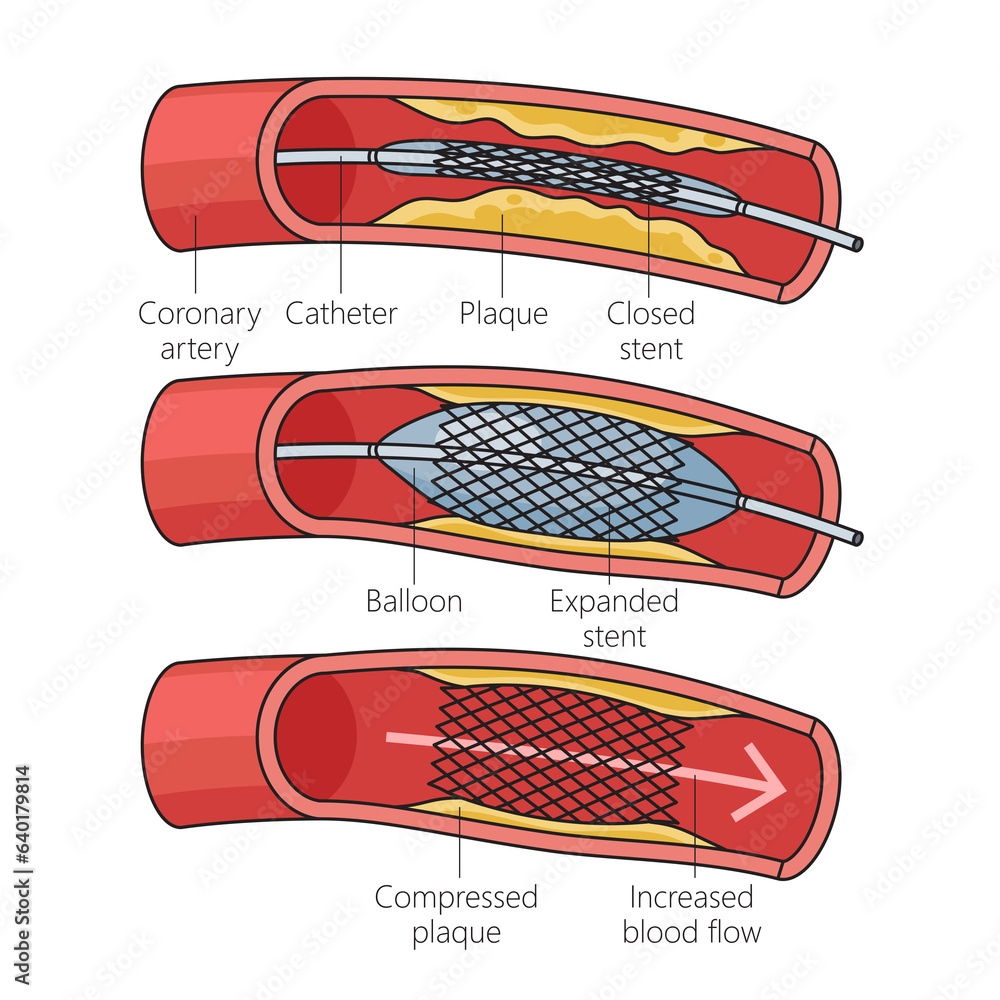
You get a stent put in. A catheter goes through your artery, they balloon out the blockage, they drop a metal tube in there, and then they pull the catheter back out. That's it. The procedure itself is relatively minor compared to open-heart surgery. But the recovery isn't just sitting around doing nothing, and it's not suddenly going back to the gym either. There's a specific window where you have to be careful about the access site and the blood thinners you'll be on for the rest of your life. I've worked with enough cardiac patients to know that the biggest mistake people make is swinging too far in either direction. They either baby themselves to the point of deconditioning, or they ignore the access site and blow out their groin or wrist within a week. Both happen constantly. The middle ground is narrower than patients expect.
Physical Therapy After Stent Placement: Getting It Right
The formal term for what you'll likely be referred to is Cardiac Rehabilitation, Phase II. It's a supervised program, usually starting about one to three weeks after your procedure, depending on how things went. Most programs run three times per week for about eight to twelve weeks. You'll be monitoring your heart rate, blood pressure, and symptoms while doing aerobic exercise on a treadmill or bike. They also throw in some light resistance work. The whole thing is designed to rebuild the cardiovascular fitness you lost during the hospital stay and the weeks after. Here's the thing nobody tells you upfront: you don't just walk into a cardiac rehab program and start exercising. There's an access site to consider first. If they came in through your femoral artery in the groin — and a lot of them still do, especially for more complex cases — that puncture site needs time to seal. You'll typically be lying flat for a few hours after the procedure, sometimes longer if they used a closure device. Then over the next several days to a week, you're gradually increasing walking distance. No bending at the waist past ninety degrees. No lifting anything heavier than ten pounds. This isn't arbitrary fear-mongering; a hematoma at the femoral access site can be a serious complication that sometimes requires a blood transfusion or even surgical repair. If they went through your radial artery in the wrist, which is increasingly common, the restrictions are different but real. You can start moving that arm sooner, but you're still looking at avoiding heavy gripping or lifting for about a week. I had a patient recently who was a landscape architect and went back to using hedge trimmers five days after his stent because the wrist felt fine. Developed a pulsating mass in his forearm by day eight. Had to come back for a repair. The artery wall was still healing underneath the skin. It doesn't always present with obvious bleeding.
Before you even think about structured exercise, there's the medication piece. You'll be on dual antiplatelet therapy — usually aspirin plus clopidogrel, ticagrelor, or prasugrel — for at least six to twelve months. This prevents clot formation inside the stent. It also means any bruise or bleed takes longer to stop. You'll notice this in physical therapy immediately. Patients who were previously fearless about trying new exercises become suddenly cautious because they're bruising from light contact or even from blood pressure cuff inflation. That's normal. It's also why the therapists in these programs are very methodical about progression. They're not being timid. They're working around the pharmacology. The actual exercise progression, assuming everything went smoothly, typically looks like this. Week one is mostly walking. Ten minutes, two or three times a day. The goal is just to get the blood flowing and prevent deconditioning without stressing the access site. By week two, you can usually handle twenty to thirty minutes of continuous walking or stationary cycling. Heart rate target is generally set at your baseline plus twenty beats per minute, or roughly sixty to seventy percent of your maximum. You should be able to hold a conversation while exercising. If you can't, you're going too hard. Weeks three through four is where formal cardiac rehab usually kicks in. That's the supervised part. You'll do twenty to forty minutes of aerobic exercise per session, three times a week, with continuous ECG monitoring. They'll also introduce light resistance bands or very light weights, typically starting at two to three pounds. The resistance work is progressive but slow. Most programs don't push beyond five to ten pounds for the first eight weeks. This is deliberate. The sternum isn't involved, but the blood vessels are still healing internally, and sudden increases in blood pressure from heavy lifting aren't helpful.
Get the Full Details
After that, months two through four, you can gradually increase intensity and resistance. By month three, many patients are back to moderate-intensity activities like brisk walking, swimming, or recreational cycling. The six-minute walk test is a common benchmark — if you can cover about 400 meters without significant symptoms, you're in a reasonable range for independent exercise. There are edge cases where this timeline gets stretched. Patients who had a large amount of blockage removed, those who experienced complications during the procedure, or people with other conditions like diabetes or peripheral artery disease will move more slowly. I worked with a patient who had a stent placed after a spontaneous coronary artery dissection rather than typical atherosclerosis. His vascular wall was structurally compromised in a different way. We held off on any upper-body resistance work for six weeks instead of the usual four, and we kept his heart rate targets fifteen beats lower than the standard protocol. The textbook doesn't cover every anatomical variation, and the therapists who only follow the standard pathway sometimes miss these nuances. Another thing worth noting: the psychological component is real and often underestimated. After a stent procedure, a significant number of patients develop exercise aversion. They've just been through a scary medical event. Their heart did something wrong. The idea of pushing their heart rate up feels risky, even when their doctor has cleared them. I've seen patients in rehab programs who were technically physically ready to progress but refused to go above a certain heart rate because they associated that sensation with the day of their procedure. The therapists handle this by using a lot of reassurance and education, and by showing patients their actual heart rate data in real time. It helps a lot when you can see that your numbers are perfectly safe.
Longer-term, the goal is maintenance. Cardiac rehab graduates typically transition to unsupervised exercise programs. The evidence is strong that continuing exercise after discharge reduces repeat cardiac events and improves survival. But compliance drops off sharply after the formal program ends. Most people stop going to the gym or the pool within three months. That's a separate problem, but it's the reason the lifestyle counseling in cardiac rehab is as important as the exercise itself. The practical takeaway is straightforward. You don't need to rush back to your normal routine, but you also shouldn't treat a stent placement like a major surgical recovery. Most people are walking normally within days and doing light exercise within two weeks. Formal supervised rehabilitation starts around week two and runs for about three months. The restrictions are mostly about the access site in the first week and the blood thinners throughout. Listen to your care team, report any swelling or unusual pain at the access site immediately, and don't let anxiety about exercise become a self-fulfilling prophecy. Your heart is stronger after this procedure than it was before, generally speaking. The stent did its job. Now you just need to support it.