What Actually Happens When Your Neck Is Unstable
Cervical instability means the ligaments and joints in your neck aren't holding things together the way they should. The vertebrae move more than they're supposed to, especially when you bend forward or turn your head. This isn't theoretical. People live with it daily and the symptoms range from nagging headaches to genuine neurological concerns. Physical therapy is usually the first line of treatment because surgery is reserved for severe structural failure. The goal isn't to stretch the neck more. It's the opposite. You build endurance in the deep stabilizers so the ligaments stop doing all the work. The superficial muscles like the trapezius and sternocleidomastoid tend to overfire in these patients because the deeper system is sluggish. When you see someone whose shoulder shrugs every time they look up, that's a compensation pattern. Your job is to retrain the system before it reinforces bad habits. Start with isometric holds. Not because they're easy but because they load the joint without moving it through the risky arc. Chin tucks against light resistance, lateral holds, gentle extension against your palm. Hold for 10 to 15 seconds. Eight reps. That's it. Going heavier or longer too early just recruits the wrong muscles and reinforces the wrong patterns.
I've worked with enough of these patients to know the typical progression. Week one is all about awareness and gentle activation. Week two and three introduce controlled range of motion with resistance bands or manual cues. By week four you're adding proprioceptive challenges like unstable surfaces or eyes-closed balance work. Most people need six to twelve weeks before they're doing functional strengthening. The timeline varies based on severity and compliance.
What Beginners Get Wrong
The biggest mistake I see is rushing into strengthening before the patient can isolate the deep flexors. I had a guy last year who came in after six weeks of what he called his own program. He was doing full range neck curls with a weight plate. Classic case. His SCM was so dominant that his deep flexors were completely offline. We spent three weeks just re-teaching him how to activate the longus colli without his neck creaking and popping every time he moved. He could have saved two months by not starting there. Another common error is treating all neck pain the same. Some patients with cervical instability actually have a hypermobile segment adjacent to a fused or arthritic one. That creates a pivot point and the surrounding tissues take enormous strain. If you throw standard stabilizing exercises at that pattern without identifying the mechanics first, you'll make it worse. Imaging and careful clinical testing matter here more than anywhere else in rehab. Stretching is also where people get burned. Tight suboccipitals feel like the enemy but aggressive stretching on an already loose joint destabilizes it further. You release the suboccipitals gently with pressure techniques or very light sustained holds, never bouncing or forcing range. The goal is tension reduction, not lengthening.
Get the Full Details

Advanced Nuances That Actually Matter
Scapular positioning changes everything. The cervical spine doesn't operate in isolation. If the scapula is winged or the thoracic spine is overly kyphotic, the cervical stabilizers are forced to compensate at a mechanical disadvantage. I'll spend as much time on shoulder blade stability and thoracic extension as I do on neck work. Patients often respond faster when you address the base rather than just the top of the chain. Vestibular involvement is another area people underestimate. Cervical instability can interfere with proprioceptive input from the neck into the vestibular system. That means dizziness and balance issues that have nothing to do with the inner ear. Cervicogenic dizziness is real and it responds to neck rehab differently than peripheral vestibular problems. If a patient reports lightheadedness with certain head positions, test it. Do a cervical provocation test before you assume it's BPPV or something else entirely.
Progressions and Exercise Examples
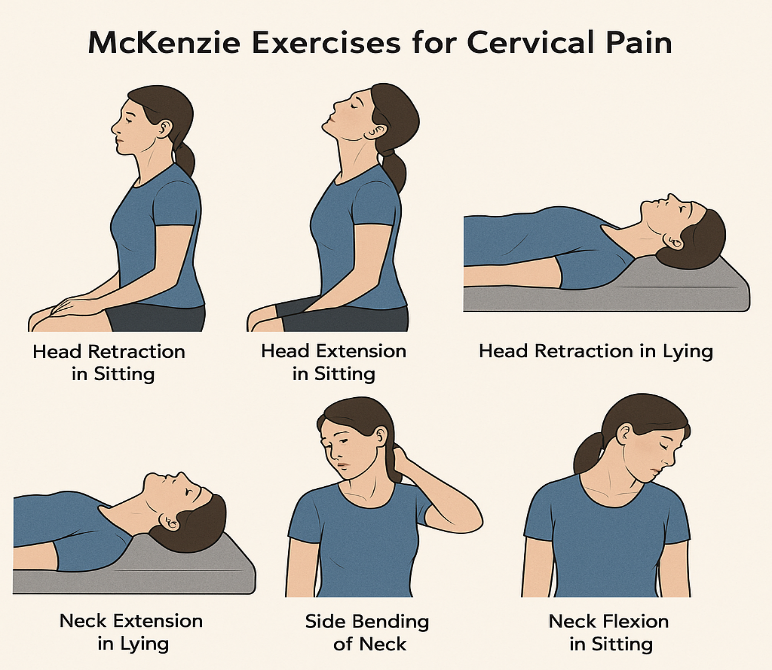
Isometric chin tuck: Sit or stand tall. Push your head straight back like you're making a double chin. Don't tilt up or down. Hold resistance with your hand. Ten seconds. Eight reps. Scapular retraction with cervical hold: Pull your shoulder blades together and slightly down while maintaining a neutral chin position. Hold five seconds. Ten reps. This links the thoracic and cervical systems intentionally. Prone Y raises: Lie face down on an incline bench or firm surface. Arms overhead in a Y position. Lift using lower trapezius and serratus anterior, not upper traps. Keep the neck long. This is harder than it looks and builds endurance in the exact muscles that support cervical alignment.
Resistance band rotation: Anchor a band at head height. Stand sideways and resist gentle rotation against the band. Five seconds on each side. This trains controlled rotation rather than free, unguarded movement through the unstable arc.

When Physical Therapy Isn't Enough
Sometimes the ligaments have degraded beyond what rehab can fix. Atlantoaxial instability from rheumatoid arthritis, Ehlers-Danlos syndrome with significant laxity, or post-traumatic instability with ligamentous rupture are situations where conservative care has limits. If imaging shows significant translation during flexion and extension views, or if neurological symptoms like hand clumsiness, gait changes, or bowel bladder dysfunction appear, surgery becomes a real consideration. Physical therapy alone won't rebuild torn or chronically stretched ligaments in those cases. Bracing is another tool worth discussing honestly. Soft collars provide some feedback and limit end-range motion but they also weaken muscles if worn too long. A rigid collar like a Philadelphia or Aspen collar offers more restriction but dramatically limits daily function. Most specialists use them short-term after acute events or post-surgery, not as a permanent solution. Relying on a collar for months without active rehab is usually a path to deconditioning and worse outcomes.
Practical Considerations for Physical Therapy For Cervical Instability
Find a therapist who understands cervical biomechanics beyond the standard protocol. Not every PT has experience with ligamentous laxity and hypermobility syndromes. Ask about their approach before committing. The right therapist will emphasize slow progression, careful assessment of scapular and thoracic contribution, and willingness to modify when symptoms flare. The wrong one will push aggressive mobilization or ignore the whole chain above and below the neck. Expect consistency over intensity. Daily gentle work beats three hard sessions per week. The stabilizers need frequent low-load exposure to adapt. Think of it like practicing a musical instrument rather than lifting weights. Volume and repetition with good form build the adaptation. Heavy loading too soon just reinforces compensation patterns and delays progress. Pain and fatigue management matters more than patients realize. Cervical instability often coexists with generalised pain sensitization, particularly in connective tissue disorders. Pushing through sharp or shooting pain is a bad strategy. A dull muscular ache is fine. Nerve symptoms, headaches that worsen with the exercise, or increased dizziness means you backed off too far and need to regress to an earlier step.
The evidence for this approach is solid enough. Studies on deep cervical flexor training show improved pressure tolerance and reduced symptom burden in chronic neck pain populations. The specific data on instability is thinner but the biomechanical logic holds and clinical outcomes generally support it. Surgery remains the alternative when structural compromise is significant and conservative care has been given a fair trial without success.