What Actually Happens When You Treat a Lumbar Compression Fracture
A compression fracture means one or more of the vertebral bodies in your lower back has collapsed slightly under load. Most of these are osteoporotic, meaning the bone quality was already compromised before the event that caused the break. The usual presentation is sudden midline back pain after something minor like a sneeze, a bump in the road while driving, or lifting a grocery bag. It hurts to stand. It often feels worse when you bend forward. Getting treated right matters because the wrong approach can delay healing or make things worse. Bracing too aggressively for too long causes deconditioning. Skipping movement entirely leads to stiffness and muscle atrophy. The balance is harder to strike than most patients realize.
The Real Work Of Physical Therapy For Compression Fracture Of Lumbar Spine
Early phase management focuses on pain control and protecting the healing vertebra while maintaining enough movement to prevent secondary complications. I typically see patients coming in during the first three to six weeks after diagnosis. At that point, the acute inflammatory response is still active and any flexion-heavy loading reproduces the pain quickly. The first sessions are almost entirely about education and gentle movement retraining. We avoid flexion. That means no toe touching, no traditional sit-ups, and no forward bending from the hips with a rounded spine. Instead, we focus on neutral spine positioning and pelvic tilts that keep the lumbar curve relatively maintained. Patient education alone accounts for a significant portion of early progress. Understanding why forward bending hurts so much changes how people move in daily life almost immediately. I had a patient last year, a woman in her late seventies with a L1 fracture who was terrified of any movement at all. She was basically spending most of the day lying down because she feared bending even slightly would worsen the fracture. She came to me unable to stand for more than thirty seconds without sharp pain. The workaround was breaking everything into micro-doses of movement. Ten seconds of standing, then sitting. Fifteen seconds of marching in place while holding the counter, then rest. We repeated this cycle throughout the session with no pressure to push through discomfort. Within four sessions she could stand for two minutes without escalating pain. It was not dramatic but it was sustainable.
Progression Timeline And What Each Phase Looks Like
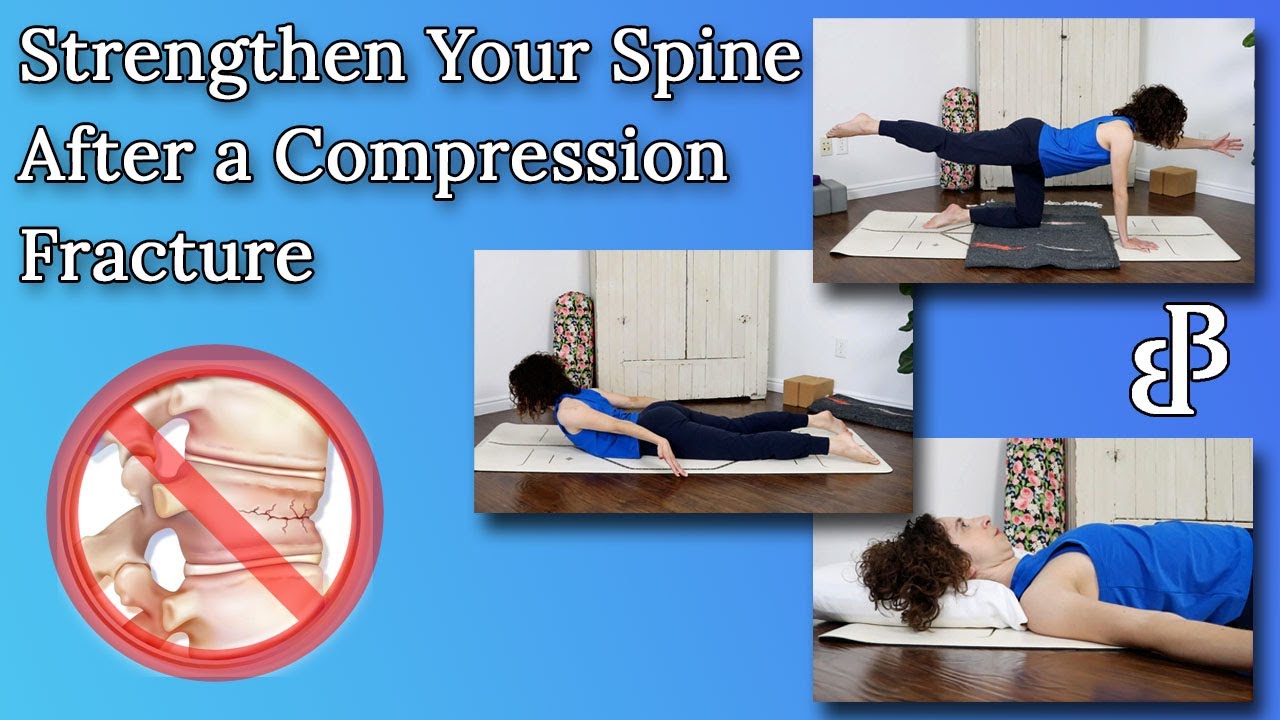
Phase two typically begins around week six or eight depending on imaging follow-up and pain response. By this point, the fracture is entering the callus formation and early remodeling stage. Pain at rest has usually decreased substantially but mechanical pain with certain movements remains. This is where we introduce extension-biased exercises based on the McKenzie method principles, though adapted for fracture cases. Prone lying, prone on elbows, and gentle prone press-ups are common starting points. The goal is not to force the spine into extension but to establish that extension-oriented movement is tolerable and often reduces pain compared to flexion. Core stabilization work comes next. Not the intense core work you see in fitness magazines. We are talking about gentle transverse abdominis activation, pelvic floor engagement, and breathing retraining. A lot of patients have been breathing shallowly due to pain guarding. Once that pattern shifts, core recruitment becomes easier to teach. Dead bugs with a reduced range of motion, bird dogs with limited limb elevation, and modified planks on the knees are reasonable progressions. The key is maintaining neutral spine throughout and stopping before form breaks down. By phase three, usually around twelve to sixteen weeks, most patients are cleared for more dynamic loading if imaging shows adequate healing. Balance training, gait re-education, and functional strengthening become the focus. Hip hinge patterns are critical here because learning to bend from the hips while keeping the spine neutral translates directly to safer daily activities. Sit-to-stand practice, step-ups, and light resistance band work are all appropriate. We avoid axial loading through the spine until the fracture is well consolidated, which generally means waiting at least four to six months for heavy lifting or high-impact activities.
Get the Full Details

Common Mistakes That Slow Recovery Down
The biggest mistake I see is patients rushing back into their pre-injury exercise routines too soon. A person who used to do heavy squats or yoga before the fracture should not resume those activities even at reduced weight during the early phases. The vertebral body needs time to regain structural integrity. Pushing through pain during strengthening is a reliable way to delay healing or risk further collapse. Another issue is over-bracing. Thoracolumbar orthoses like TLSO braces are useful in the acute phase for pain reduction and postural support. But wearing one for more than eight to twelve weeks without guidance leads to core muscle weakening that actually makes the spine less stable long term. The brace should be a temporary aid, not a permanent crutch. I typically recommend weaning off the brace gradually once the patient can maintain good posture without it during daily activities. Some patients skip the extension work entirely because it initially provokes pain. That is a mistake. The initial discomfort during extension exercises is often a sign that the movement is being done correctly, not incorrectly. The pain should be mild and central, not sharp or radiating. If the pain becomes severe or starts shooting down the leg, that is a different signal and the exercise needs to be modified or paused.
When Physical Therapy Alone Is Not Enough
Not every compression fracture responds well to conservative management. Patients with significant vertebral height loss, those who develop neurological symptoms, or people whose pain remains severe despite six to eight weeks of proper physical therapy may need procedural intervention. Vertebroplasty and kyphoplasty are options worth discussing with a spine specialist in those cases. These procedures involve injecting bone cement into the fractured vertebra to stabilize it. They are not without risks, including cement leakage and adjacent level fractures, but they can provide meaningful pain relief when conservative care fails. Osteoporosis management is equally important and often overlooked. Physical therapy addresses the mechanical aspects of recovery but does nothing to improve bone density. Without addressing the underlying bone health through medication, calcium, vitamin D, and lifestyle changes, the risk of another fracture increases substantially. A DEXA scan and appropriate medical workup should be part of the overall plan, not an afterthought. The timeline I described is a general framework. Individual recovery varies based on fracture severity, bone quality, age, activity level, and adherence to the program. Some patients progress faster. Others need more time in each phase. The guiding principle is watching the body's response and adjusting accordingly rather than following a rigid calendar. Pain is feedback, not failure. If an exercise consistently increases pain beyond a reasonable level, it is not working for that person at that time and the approach needs modification.
What To Expect In A Typical Session
A standard session runs about forty-five to sixty minutes. The first ten to fifteen minutes are usually dedicated to reviewing how the patient has been since the last visit, assessing current pain levels, and checking for any new symptoms. The middle portion involves hands-on manual therapy if needed, followed by guided exercise progression. The last ten minutes focus on teaching self-management strategies, home exercise review, and planning for the interval until the next appointment. Most patients I work with come in once or twice per week during the active rehabilitation phases, transitioning to less frequent visits as they become independent with their program. Home exercises are non-negotiable. Doing the clinic work without reinforcing it at home significantly slows progress. I usually prescribe fifteen to twenty minutes of home practice, five to six days per week. The exercises are simple and do not require equipment. The consistency matters more than intensity at this stage.