Spinal rehab is rarely about fixing the back itself.
Most people walk into a clinic expecting to be treated for their lumbar spine. They sit on the table and wait for the provider to find the source of their pain. That approach misses the reality of how the kinetic chain works. When you are dealing with Physical Therapy Of The Spine, you are usually managing compensation patterns. The low back is the victim, not the culprit, ninety percent of the time. You need to understand the difference between mobility and stability. A segment of the spine that is too mobile causes instability. One that is too stiff causes stress elsewhere. The goal is not to create more flexibility in the vertebrae themselves. It is to teach the surrounding musculature to manage load. I spent years trying to manipulate lumbar segments that were clearly fused by scar tissue. The results were always temporary. The breakthrough came when I stopped forcing movement into a restricted segment and started building global core stiffness. We used a method involving isometric holds and breath control to engage the deep stabilizers before introducing any dynamic load.
A realistic edge case involving hip flexor dominance
One patient presented with recurrent disc bulge symptoms at L4-L5. Every standard protocol failed. We worked on the spine for weeks with no improvement. The issue was not in the spine. It was a severely tight psoas from hours of sitting at a desk. The psoas pulls on the lumbar spine anteriorly, creating constant shear force. I stopped treating the back entirely. We focused on releasing the hip flexors and activating the glutes. The patient performed glute bridges three times a day. Within two weeks, the radiating leg pain vanished. The spine was finally getting a break from the abnormal pull of the hip flexors. This is why you must assess the entire body before focusing on the painful area.
Specific techniques for cervical and thoracic regions
Cervical issues often stem from forward head posture. The weight of the head increases exponentially as the neck flexes. For every inch the head moves forward, the effective weight on the neck muscles doubles. Corrective exercises must address this leverage problem. We use chin tucks to lengthen the suboccipital muscles. You do not push the head back. You draw the chin straight back as if making a double chin. Hold for five seconds. Repeat ten times. This retracts the cervical vertebrae into a neutral position. Thoracic stiffness contributes to both neck and low back pain. A stiff mid-back forces the segments above and below to move more than they should. We use thoracic extensions over a foam roller. Place the roller horizontally across the mid-back. Support the head with hands behind the ears. Extend gently over the roller. Move the roller up and down the thoracic spine in one-inch increments. Perform this daily for five minutes.
Get the Full Details

Pitfalls to avoid during recovery
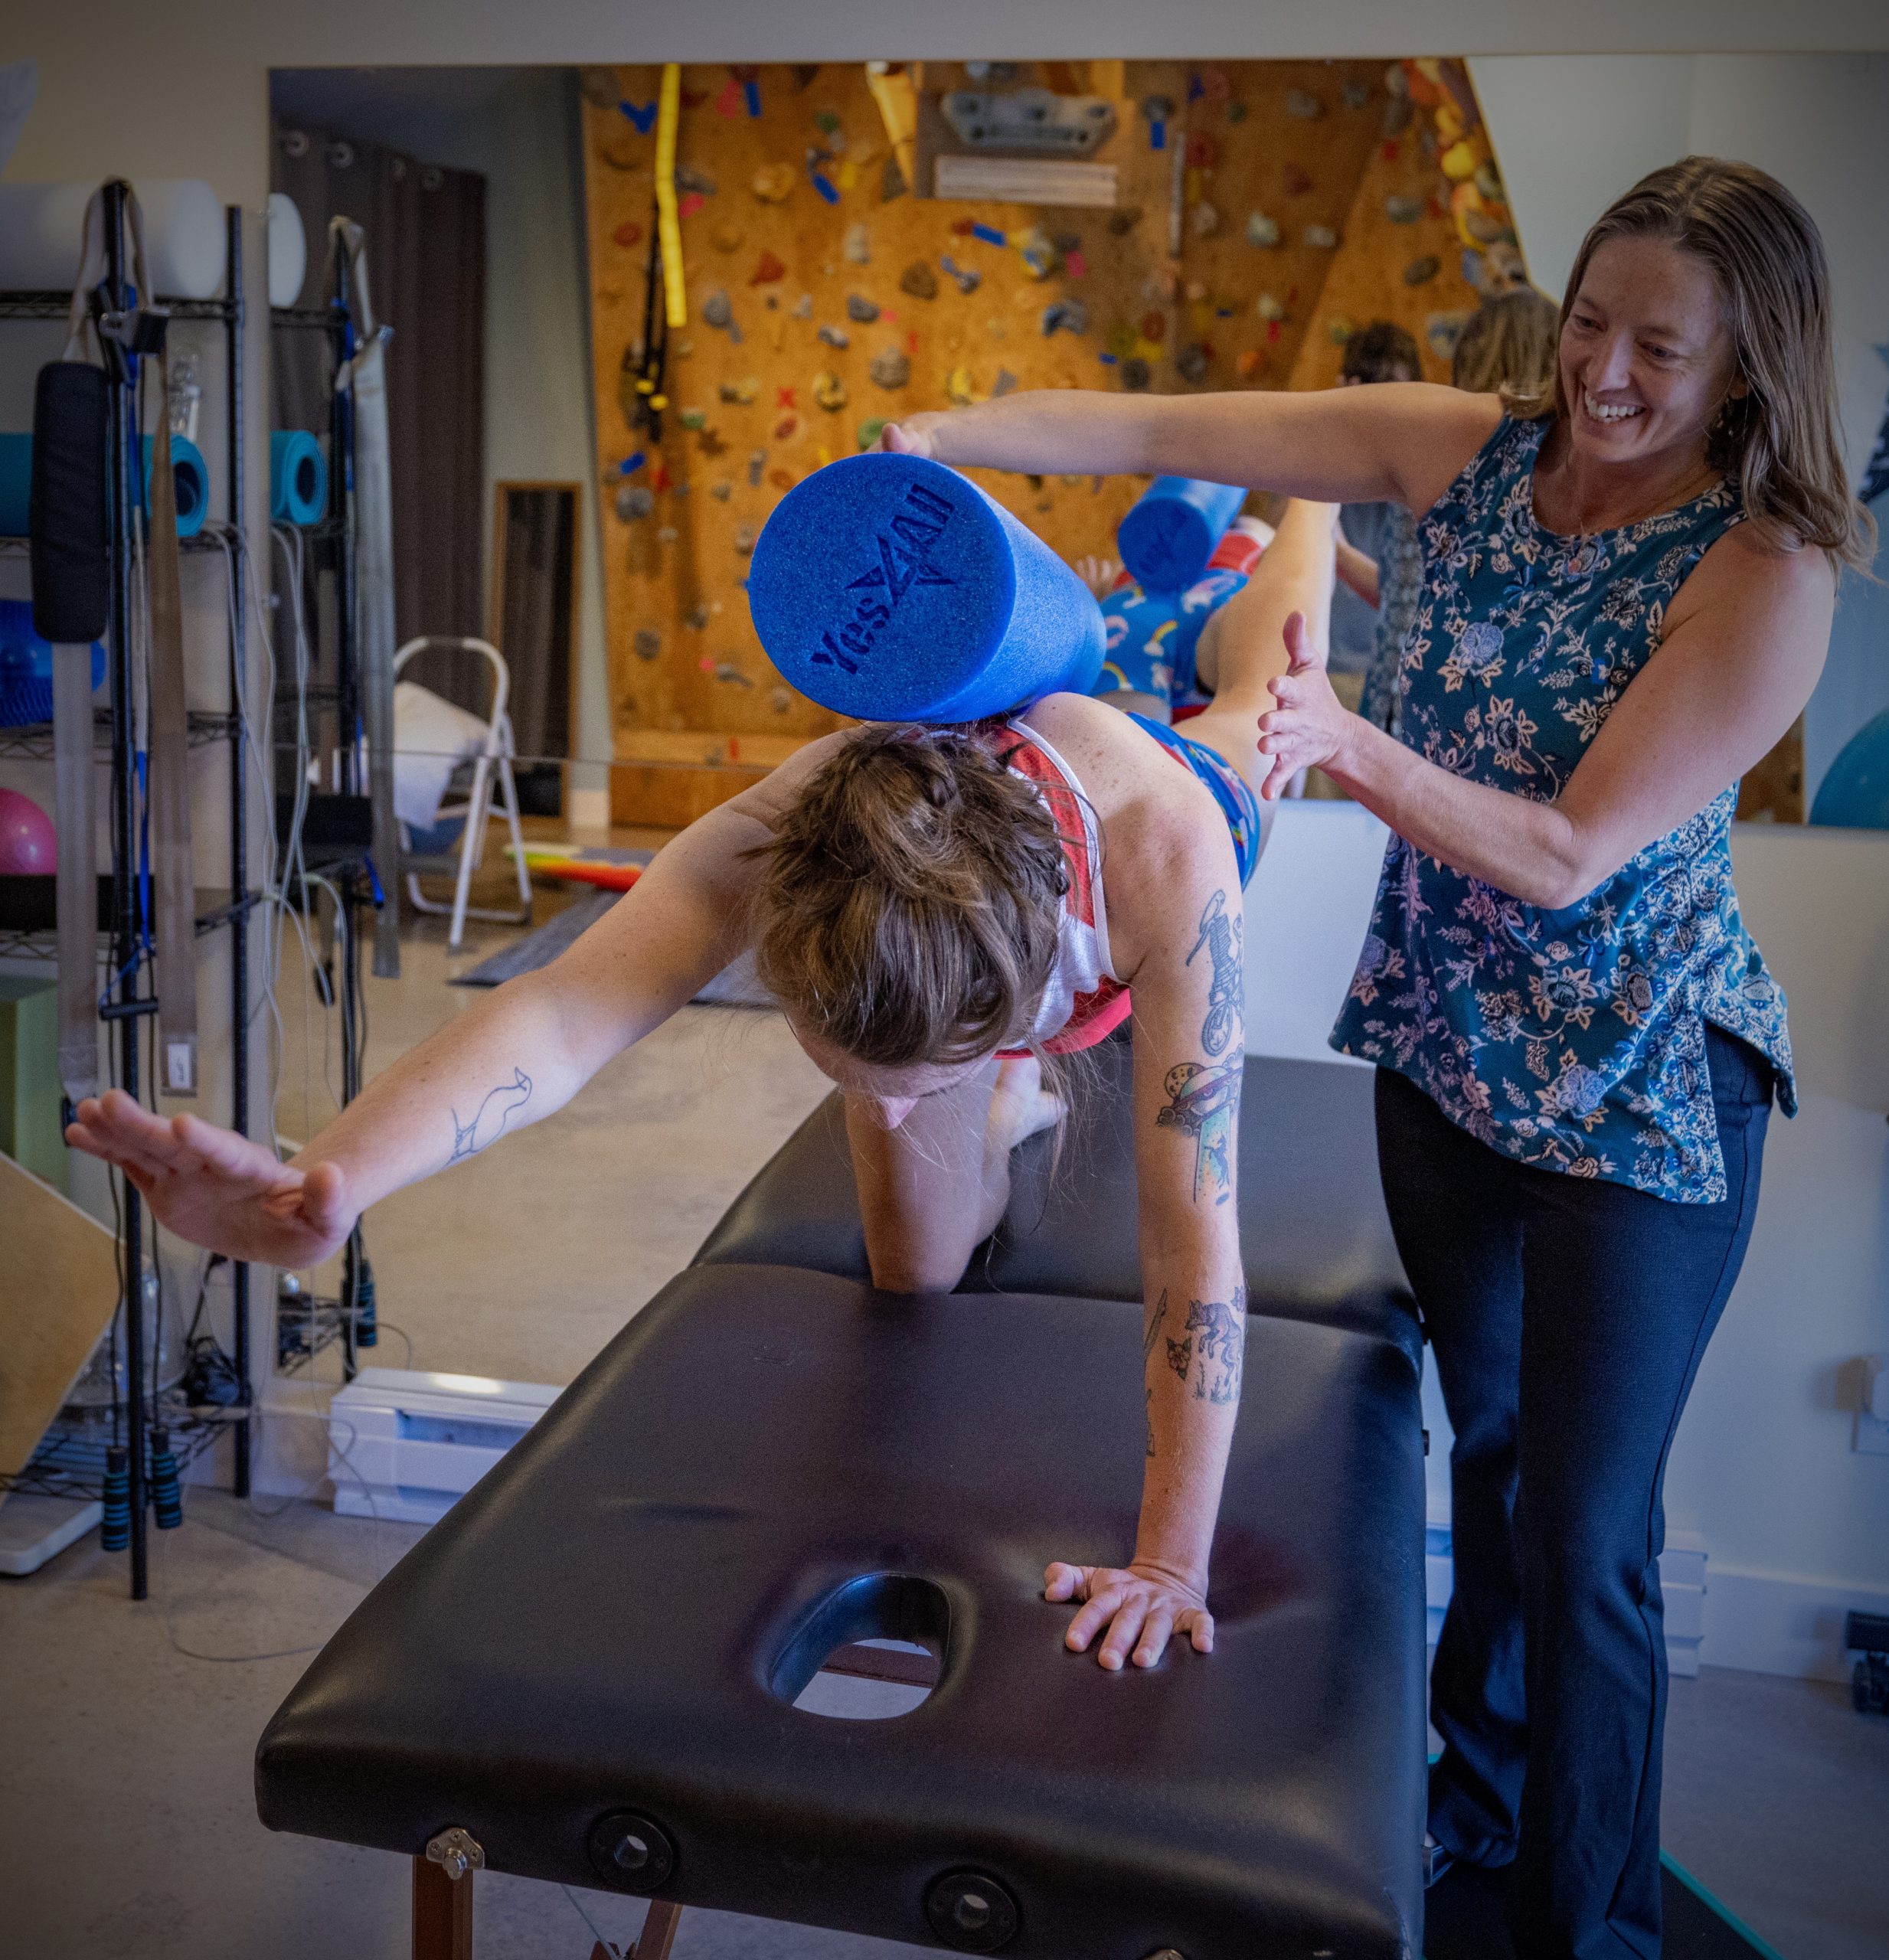
Stretching is often recommended for back pain, but aggressive stretching can worsen instability. If the ligaments are already loose, stretching them further reduces their ability to hold the spine in place. Focus on strengthening instead. Core exercises like the dead bug and the bird dog provide stability without excessive range of motion. Another common mistake is ignoring breathing. Shallow chest breathing keeps the accessory neck muscles active and the diaphragm weak. Proper diaphragmatic breathing engages the deep core and stabilizes the spine naturally. Inhale deeply through the nose, allowing the belly to expand. Exhale fully through pursed lips. This should be integrated into every exercise. The timeline for spinal recovery is slow. Discs have poor blood supply. Healing takes months, not days. Consistency matters more than intensity. Performing gentle exercises daily yields better long-term results than intense sessions twice a week. Load management is key. Avoid activities that increase pain during the acute phase. Gradually reintroduce movement as tolerance improves.
Not all back pain requires imaging. Red flags include loss of bowel or bladder control, fever, unexplained weight loss, or history of cancer. These require immediate medical attention. For mechanical back pain, manual therapy combined with exercise is the gold standard. Medications only mask symptoms and do not address the underlying cause. If conservative care fails after six to eight weeks, surgical consultation may be necessary. However, most cases resolve with proper rehabilitation. The focus should always be on restoring function and preventing recurrence. Building a resilient spine requires patience and a comprehensive approach that goes beyond the painful area.