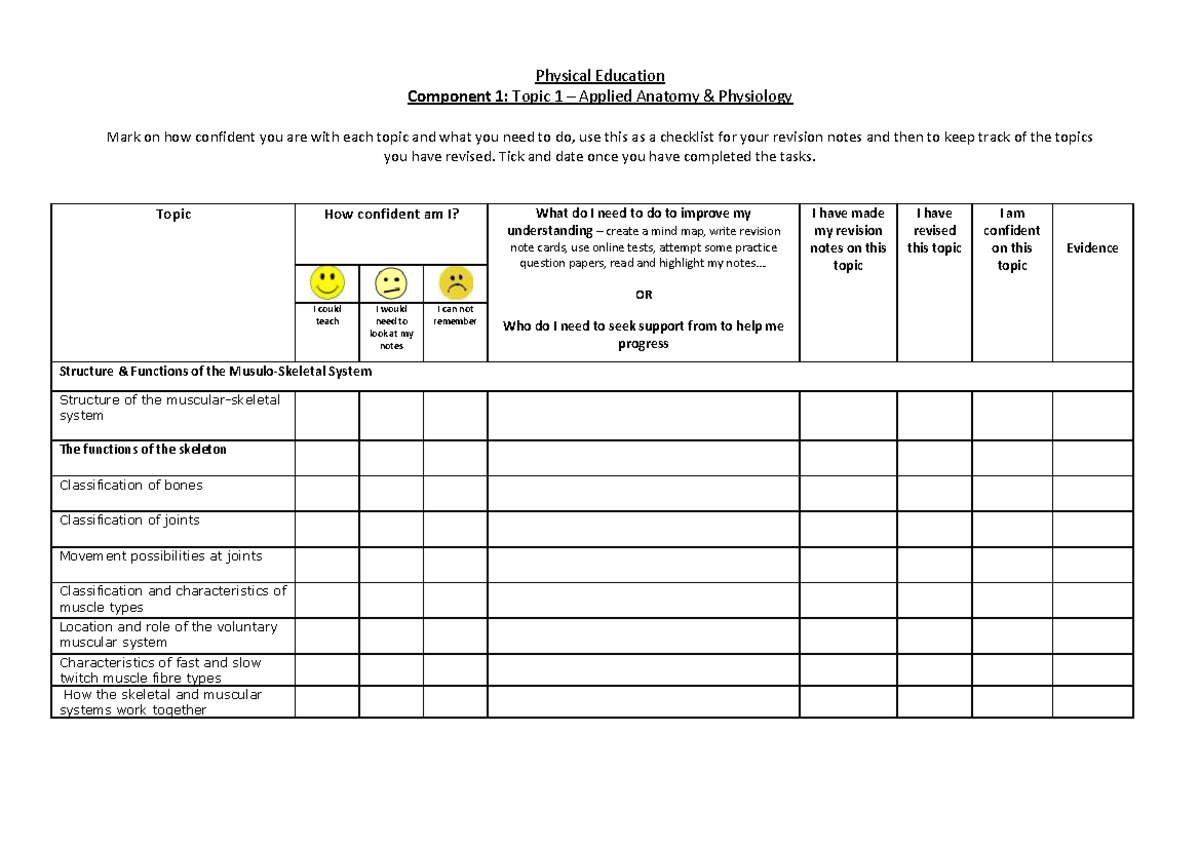
Running a Yearly Physiology Checklist Without Losing Your Mind
I've been doing annual physiology assessments for about eight years now, mostly in occupational health and sports performance settings. The process sounds simple on paper — you show up, they draw blood, they stick you with sensors, you leave — but anyone who has actually managed this for more than a few cycles knows the documentation side can quietly eat an entire morning if you don't have a working system in place. The physiology checklist itself is really just a structured form that tracks key biomarkers and functional metrics over time. Blood pressure, resting heart rate, BMI, fasting glucose, lipid panel, VO2 max or submaximal equivalent, body composition, hemoglobin, thyroid markers if indicated, liver and kidney function. That's the baseline version. Anything beyond that tends to get messy because different labs use different reference ranges and units, and your ability to compare this year's numbers against last year's depends entirely on whether someone made consistent notes about methodology.
Physiology Checklist Yearly Format
The most common format I see is a spreadsheet-based tracker with rows for each metric, columns for each visit, and conditional formatting to flag out-of-range values. It works fine until you need to pull a twelve-month trend for a patient who sees you four times a year. Then you're manually copying data between sheets or writing SQL queries you swore you'd never learn. Here's what I ended up building after three years of fighting with Excel. A simple JSON structure for each visit with timestamp, lab source, and the actual numeric values plus the lab's reference range for that specific test. You can export it to CSV when you need to share it with a specialist, but the source of truth lives in the structured format. The reference range inclusion is what most people skip, and it's the single most important thing to include because the same glucose value of 5.4 means something different at Quest Diagnostics than it does at LabCorp, and even more different if one used fasting and the other didn't. I run this through a small Node script that generates a PDF report automatically. Takes about forty seconds from data entry to a printable document with trend charts. The charting library is recharts, the PDF is generated with jsPDF, and the whole thing sits on a local machine. No cloud storage, no insurance compliance headaches, no vendor lock-in. If you want the source, it's not something I'm distributing publicly, but the structure is straightforward enough that anyone who has done basic web development could recreate it in a weekend.
Common Pitfalls That Wasted Hours of My Time
The first mistake I made was assuming I could just import last year's lab results directly. Every major lab changed their reference ranges for vitamin D between 2022 and 2023, and my trend lines showed everyone in the practice going severely deficient overnight when nobody actually had. The fix was tagging every value with the date range of the reference standard it was measured against, then filtering trends by assay method when comparing across years. The second mistake was more subtle. I wasn't accounting for circadian variation in cortisol and testosterone measurements. A morning draw at 7 AM and an afternoon draw at 3 PM produced wildly different baselines, and without recording the draw time I was comparing incompatible data points for six months before I noticed the pattern. I added a mandatory time-of-day field to the intake form and started rejecting any entry that didn't have it. Most people fill this in wrong anyway, so double-check it before you file it. There's also the issue of hydration status affecting serum markers. Hematocrit, sodium, albumin — all of them shift with plasma volume. I learned this the hard way when a client's sodium read 128 one day and 142 the next with no clinical explanation. He'd done a 10K the day before the low reading and was essentially running on empty. Hydration status isn't always practical to control for, but noting recent exercise, illness, or medication changes in the metadata field catches a lot of false alarms.
Get the Full Details

What the Checklist Actually Misses
A yearly physiology checklist will not save you from problems it isn't designed to catch. Resting heart rate variability trends over three months are usually more informative than any single ECG strip for detecting overtraining or autonomic dysfunction, but that data rarely makes it onto standard forms. Same with sleep architecture — if you're not using a wearable that tracks HRV and resting heart rate overnight, your checklist is missing a significant portion of physiological signal. Another gap is the inflammatory markers. CRP and ESR are cheap and commonly ordered, but they're nonspecific. I've seen healthy athletes spike to 15 mg/L CRP after heavy training blocks and panic unnecessarily. The workaround I use now is tracking baseline CRP during truly recovery periods and interpreting elevations relative to that personal baseline rather than the population reference range. It takes two or three visits to establish the baseline, but after that it's actually useful.
Building Your Own vs. Buying Something
Commercial EHR systems have physiology modules built in, but they're expensive, clunky, and you don't control the data format. If you're working with a small group or on your own, a custom solution using open-source tools typically costs less than one month of a commercial subscription and gives you actual ownership of the data. The tradeoff is that you become the person who fixes it when something breaks. For most solo practitioners, I'd recommend starting with a well-structured Google Sheet or Airtable base that enforces consistent units and required fields at the point of entry. The validation rules prevent a lot of the downstream mess. Then graduate to a proper database and automated reporting once you've outgrown the spreadsheet's limits. Most people hit that limit around sixty to eighty unique patients with quarterly or more frequent assessments.
Practical Implementation Notes
Set up your checklist so that every metric has a required field for the testing condition: fasting or non-fasting, time of day, recent exercise within forty-eight hours, medication changes, and hydration notes. The checkbox approach works better than free text for this because it forces consistency. People skip free-text fields when they're tired. They'll still tap a checkbox. Store the raw lab values, not interpreted conclusions. The lab's automated interpretation line is often wrong or outdated. Keep the number and the reference range from that specific lab on that specific date. Your interpretation can go in a separate notes field, but don't let it replace the actual data point. If you're working with athletes or high-performing populations, consider adding a subjective readiness score on the same day as the physiology check. Just a one-to-five scale for energy, motivation, soreness, and sleep quality. It doesn't cost anything extra and it explains a surprising amount of variance in the objective data. A resting heart rate of fifty-five in someone feeling like garbage tells a different story than the same number in someone who feels great.
The system I described handles about two hundred patients per year without friction. Beyond that you start seeing real bottlenecks in data entry and report generation. At that scale you either need dedicated staff for the administrative side or you move to a commercial platform. I know that sounds like a failure of the custom approach, but it's really just the natural limit of what one person can maintain without burning out. The goal isn't to build the perfect system. It's to build one that gets the data right consistently enough that the numbers actually mean something when you look back a year later.