What Calcific Tendonitis Actually Is
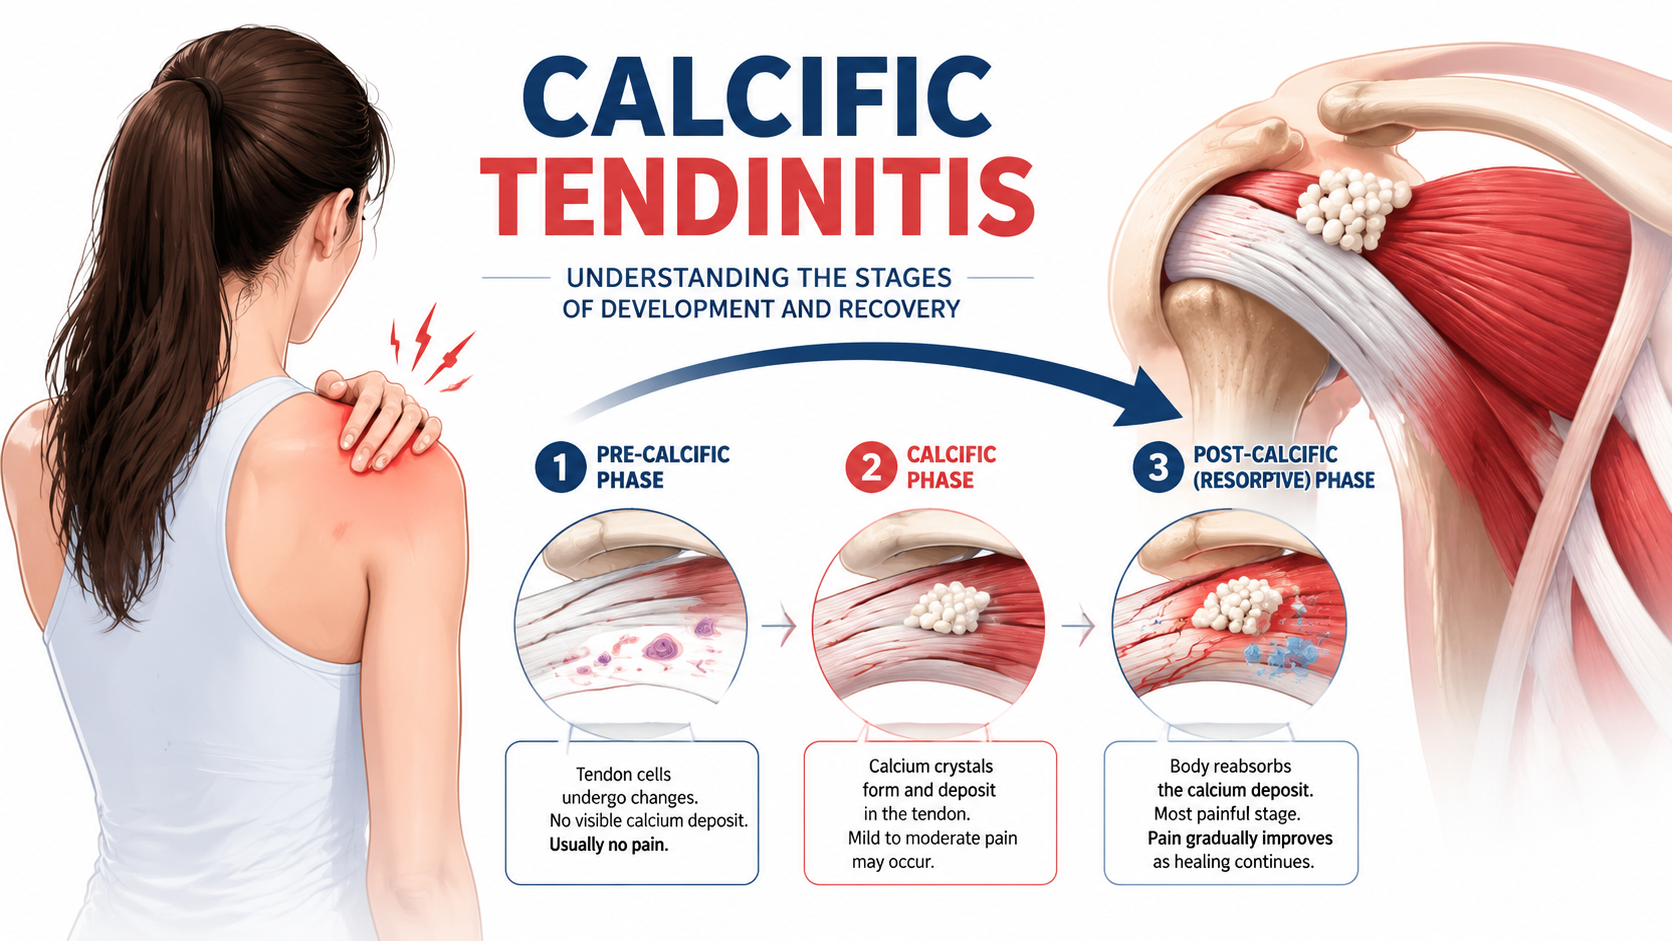
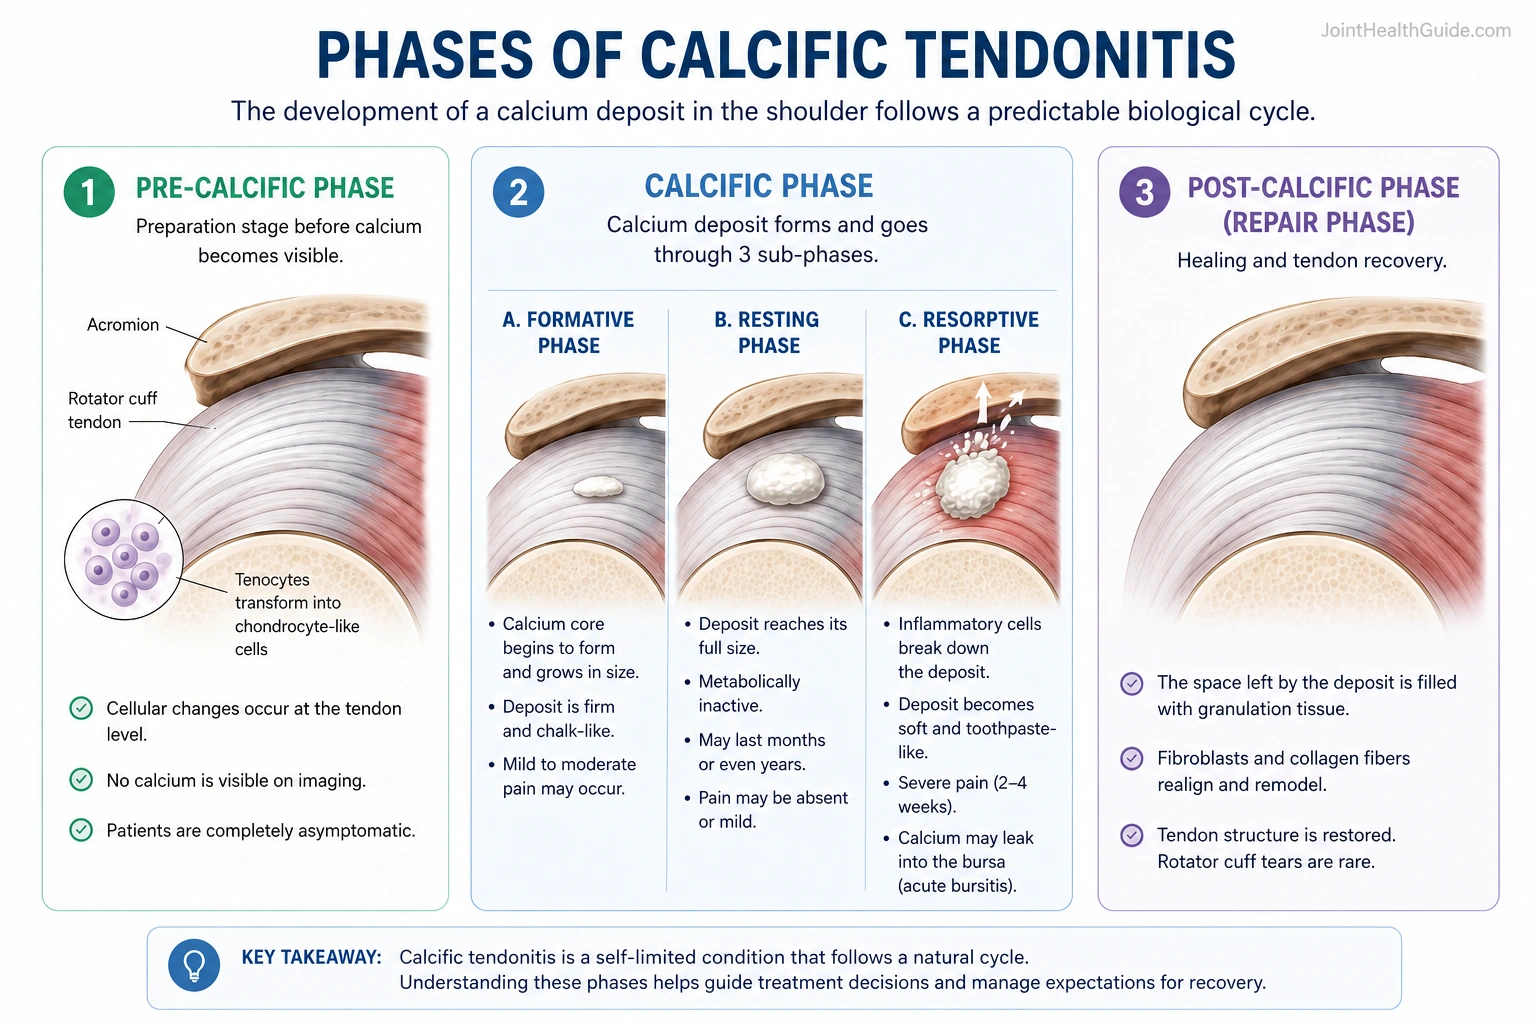
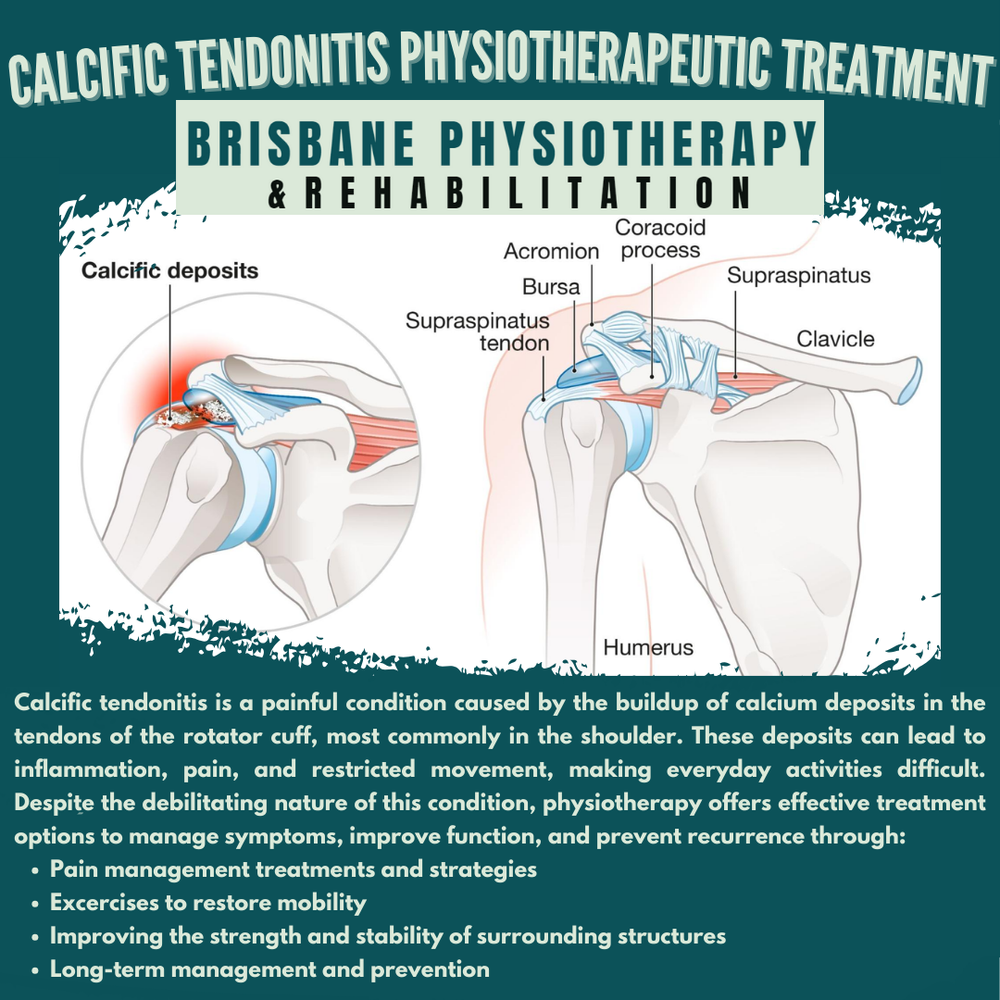
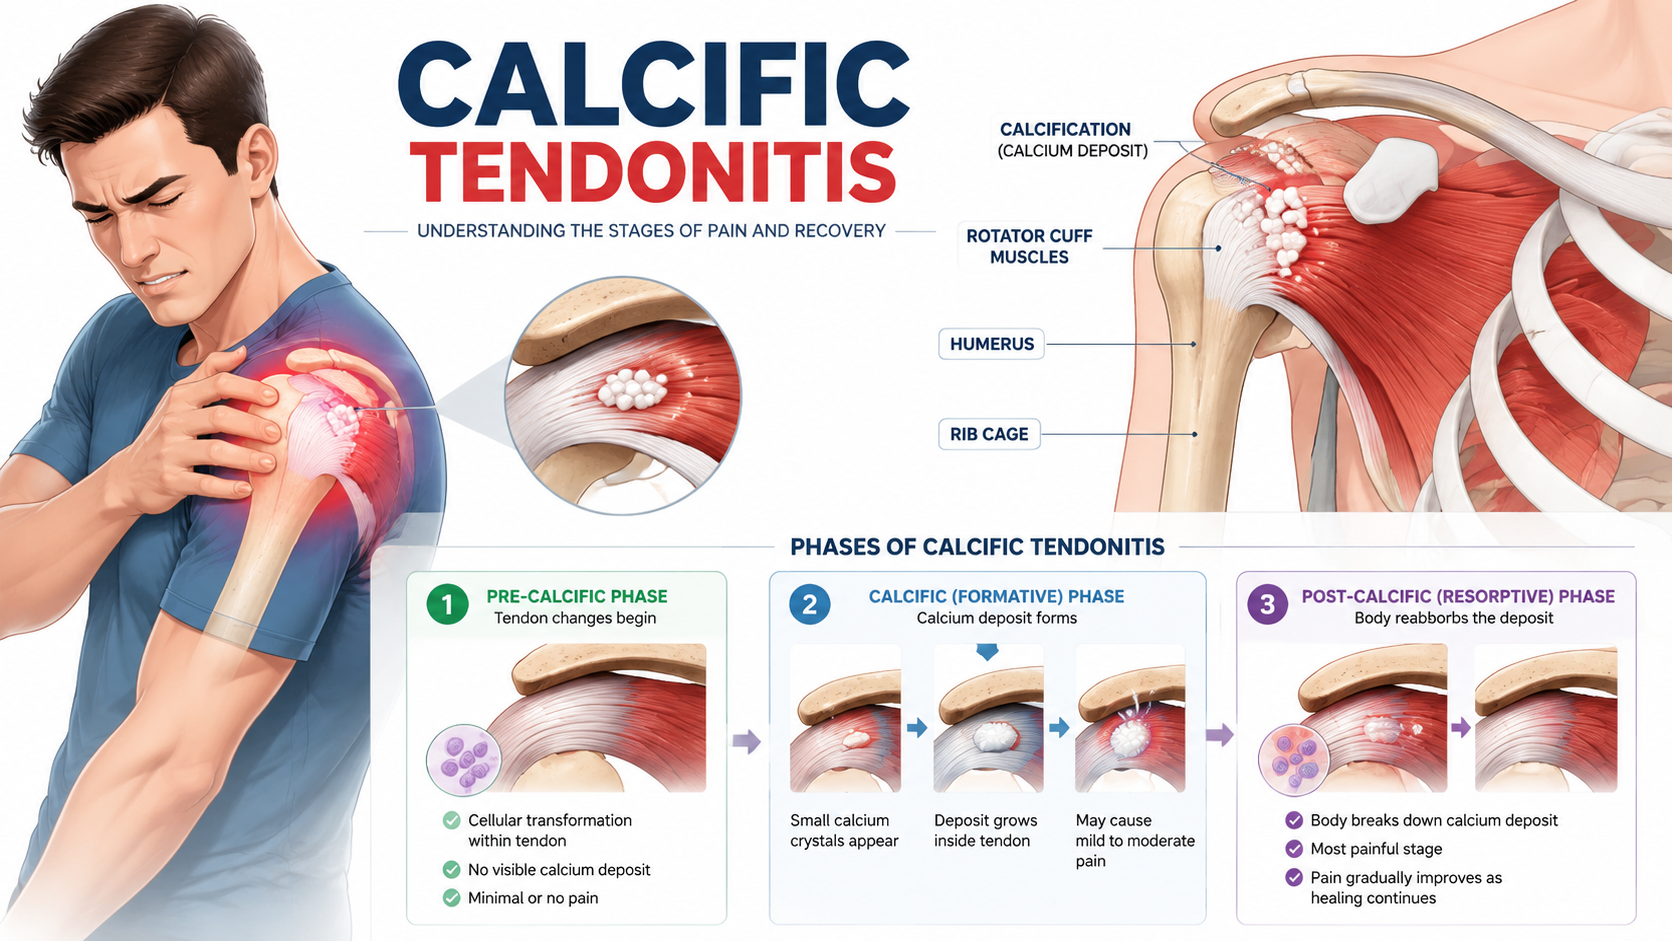
Calcific tendonitis is a condition where calcium hydroxyapatite crystals deposit within a tendon, most commonly the rotator cuff tendons of the shoulder. It is not a bone problem, despite the name suggesting otherwise. The deposits sit inside the soft tissue and trigger an inflammatory cascade that produces pain often described as severe, sometimes waking people at night. The condition passes through distinct phases: a forming phase where crystals accumulate, a resting phase that can be asymptomatic, and a resorptive phase where the body attempts to break down the deposit. The resorptive phase is typically the most painful. Physiotherapy For Calcific Tendonitis focuses on managing pain during the acute resorptive phase, preserving range of motion, and supporting the tendon through the later healing stages. It is not a cure in the sense of physically removing the calcium deposit, but it can significantly alter the clinical course and reduce the duration of disability. Here is how it works in practice. A standard session begins with an assessment of passive and active range of motion, palpation to locate the most tender area, and observation of scapulothoracic rhythm. Pain levels are recorded on a numerical scale before and after manual work so you have something concrete to track. Most of the hands-on work involves gentle mobilisation techniques rather than aggressive stretching. The tendon is inflamed and irritated during the resorptive phase. Forceful manipulation at this stage typically makes things worse and delays recovery.
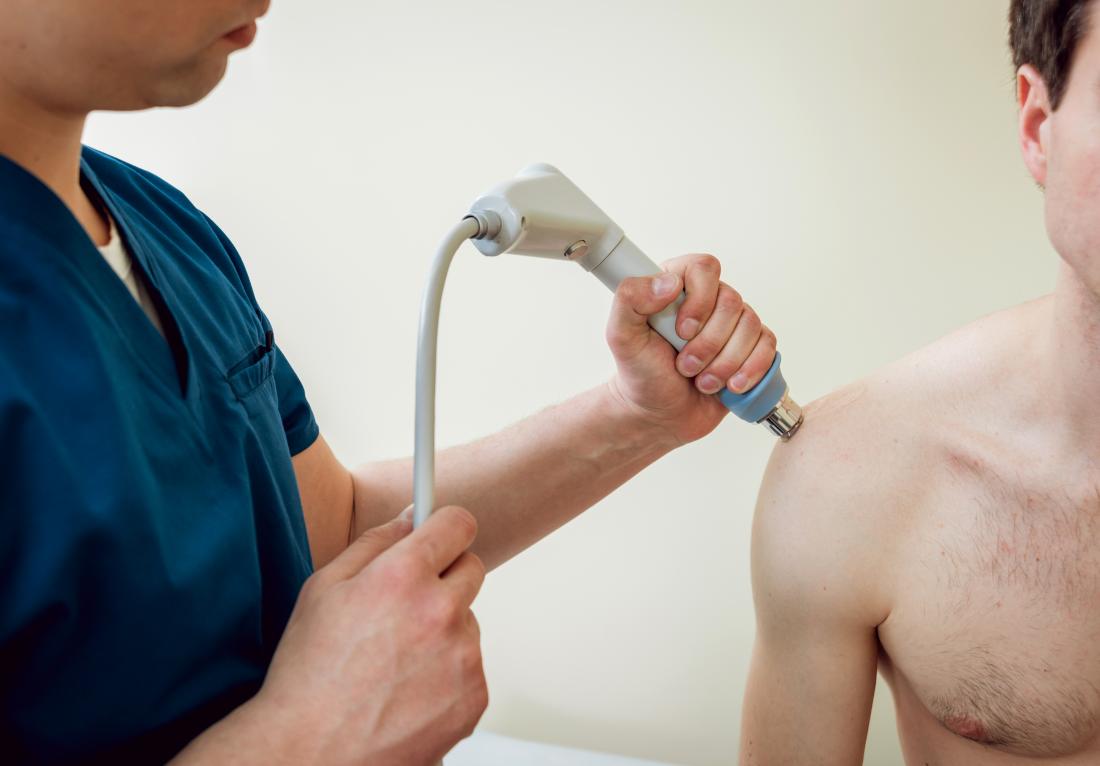
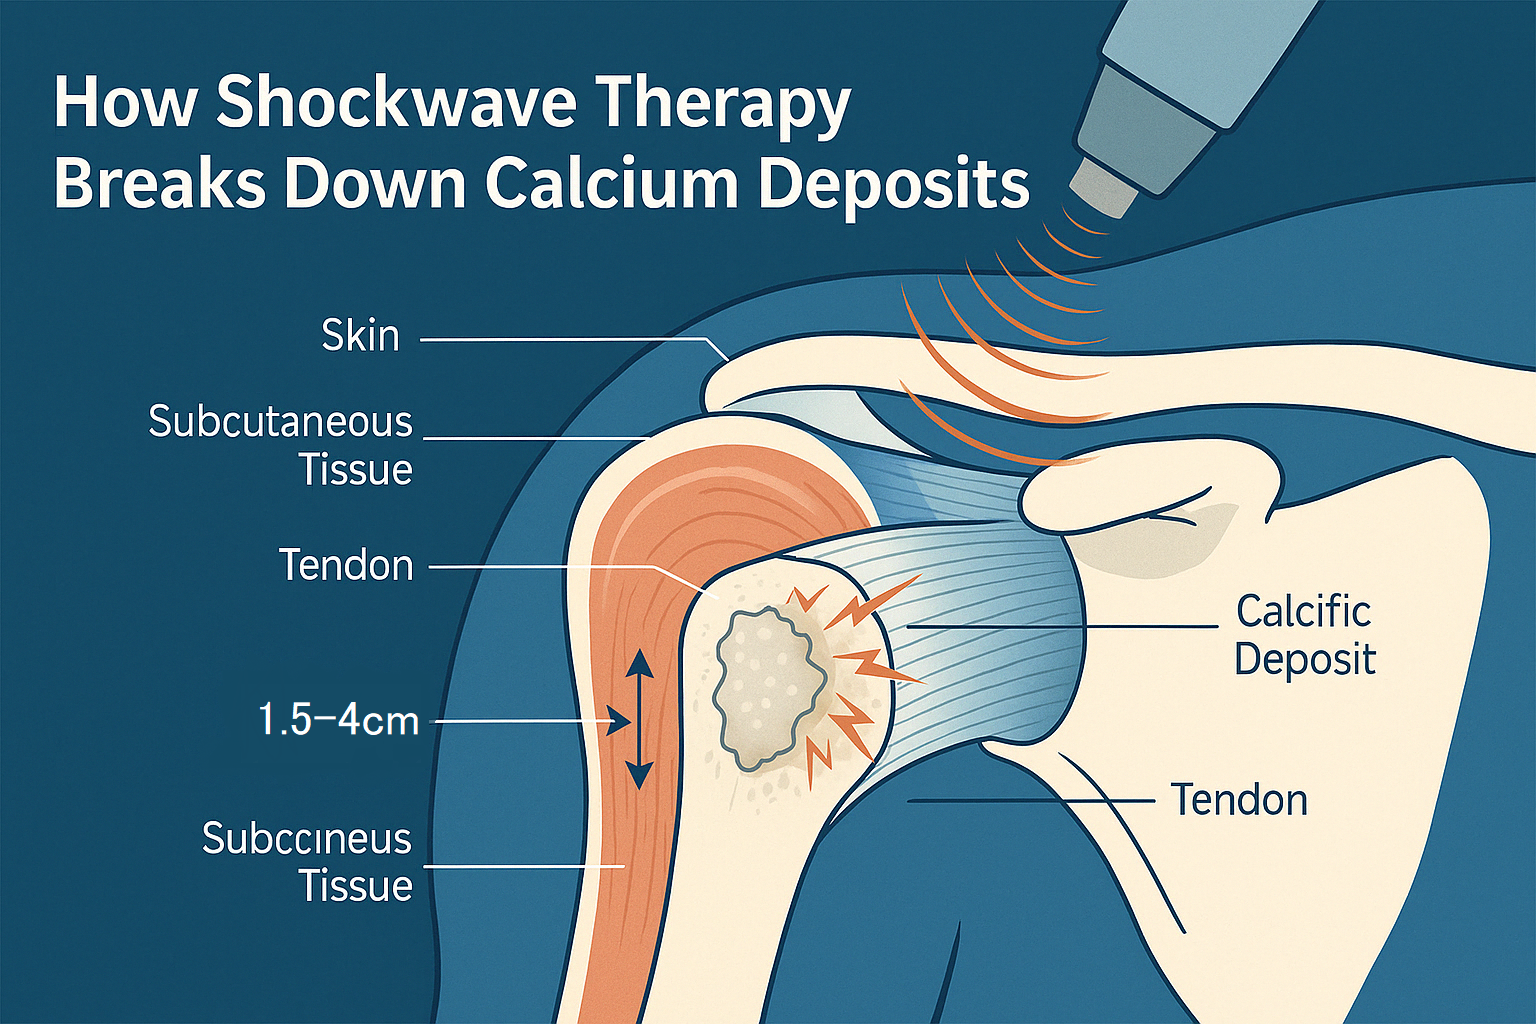
Soft tissue work targets the surrounding musculature — the deltoid, pectoralis major, latissimus dorsi, and the subscapularis when accessible. The goal is reducing compensatory tension in muscles that tighten up because the shoulder is being protected. Direct work over the calcific deposit itself is usually avoided during the painful phase because pressure on the inflamed area increases pain and can provoke further irritation. Modalities are used selectively. Ultrasound therapy has the most evidence specifically for calcific tendonitis. A study published in the Journal of Orthopaedic & Sports Physical Therapy found that extracorporeal shockwave therapy produced significant improvement in pain and function compared to placebo in patients with chronic calcific shoulder tendinopathy. I tend to recommend ESWT when available rather than conventional ultrasound alone. The mechanical energy from shockwave appears to stimulate neovascularisation and may help break down the deposit structure over time. Conventional therapeutic ultrasound has weaker evidence for this specific condition.
Exercise Progression
Exercise prescription depends entirely on which phase the condition is in. During the acute resorptive phase the priority is pain-free movement. Isometric contractions of the rotator cuff are useful because they maintain some muscular activation without creating significant joint shear or compression. A patient might perform isometric external rotation against a doorway at about 20 to 30 percent effort, holding for 30 seconds, three sets, once or twice daily. As pain settles into the healing phase, passive range of motion progresses to active-assisted movement. Pendulum exercises, pulley work, and stick-assisted elevation are standard tools. I generally avoid forcing the end range during early rehabilitation because impingement symptoms often accompany calcific tendonitis and pushing into pain simply reinforces protective muscle guarding. By the later stages, resistive exercises for the rotator cuff and periscapular muscles become the focus. Internal and external rotation with light resistance bands, scapular retraction drills, and serratus anterior work form the core of this phase. Loading is progressive but cautious. A common mistake is increasing resistance too quickly, which provokes a pain flare and sets the patient back by one to two weeks.
Get the Full Details
A Specific Problem And How I Worked Around It
I treated a patient in their late fifties with a large calcific deposit in the supraspinatus insertion. She had tried physiotherapy twice before with minimal improvement and was clearly frustrated. The issue was that her pain response was extremely sensitive to any load through the shoulder girdle. Standard strengthening exercises consistently triggered a significant flare within 24 hours, making progress nearly impossible. The workaround involved shifting the focus away from the shoulder entirely for about four weeks and concentrating on thoracic spine mobility and deep neck flexor endurance. Restricted thoracic extension and weak deep neck flexors change the mechanics of every shoulder movement. When I improved her thoracic extension by approximately 15 degrees and her neck flexor endurance by about 40 percent, her shoulder pain decreased noticeably even without direct shoulder treatment. She then tolerated rotator cuff strengthening much better. This approach is not instantaneous but it addresses a contributing factor that many clinicians overlook when focusing solely on the local deposit.
Expected Timeline And Limitations
Calcific tendonitis is often self-limiting, meaning the body may resorb the deposit naturally over six to eighteen months regardless of intervention. Physiotherapy does not necessarily shorten this timeline dramatically in every case. What it does is reduce pain severity, maintain function during the painful phases, and decrease the likelihood of chronic stiffness developing from prolonged immobilisation or avoidance behaviour. There are scenarios where physiotherapy alone will not be sufficient. Large deposits that cause persistent mechanical symptoms, deposits that do not respond to conservative management after six to twelve months, or cases where the diagnosis is uncertain and imaging has not been performed should be referred for orthopaedic review. Extracorporeal shockwave therapy, needle lavage, and arthroscopic removal are interventional options when conservative treatment fails. I have seen patients continue physiotherapy for extended periods without adequate imaging, which is not ideal. An ultrasound or X-ray confirmation of the deposit size and phase provides a more accurate prognosis and treatment direction.
What Patients Should Expect From Treatment
Treatment frequency during the acute phase is typically one to two sessions per week for four to six weeks. Home exercises are performed daily, though they should take no more than ten to fifteen minutes per session. Pain during exercise should remain below a three out of ten during the activity and should not cause a significant increase in baseline pain the following day. If it does, the exercise load or range needs to be reduced. Patient education is a substantial component. Understanding that the condition is self-limiting and that pain fluctuations are normal during the resorptive phase reduces anxiety and prevents premature cessation of movement, which leads to stiffness. Many patients stop all exercise when pain decreases slightly, only to experience a worse flare when they resume normal activities because the surrounding musculature has weakened and the joint has lost some mobility.
Red Flags That Require Medical Attention
Certain symptoms indicate that the problem may not be simple calcific tendonitis or that a complication has developed. These include significant weakness that prevents any active movement, night pain that is completely unresponsive to position changes and medication, fever or warmth over the shoulder, and a history of recent trauma preceding the onset of symptoms. In these cases, referral for medical evaluation and imaging is necessary before continuing with physiotherapy interventions.