What You Actually Need to Know Before Trying to Insert a PICC
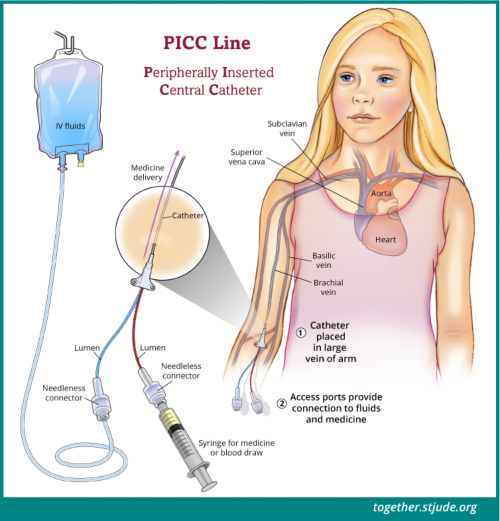
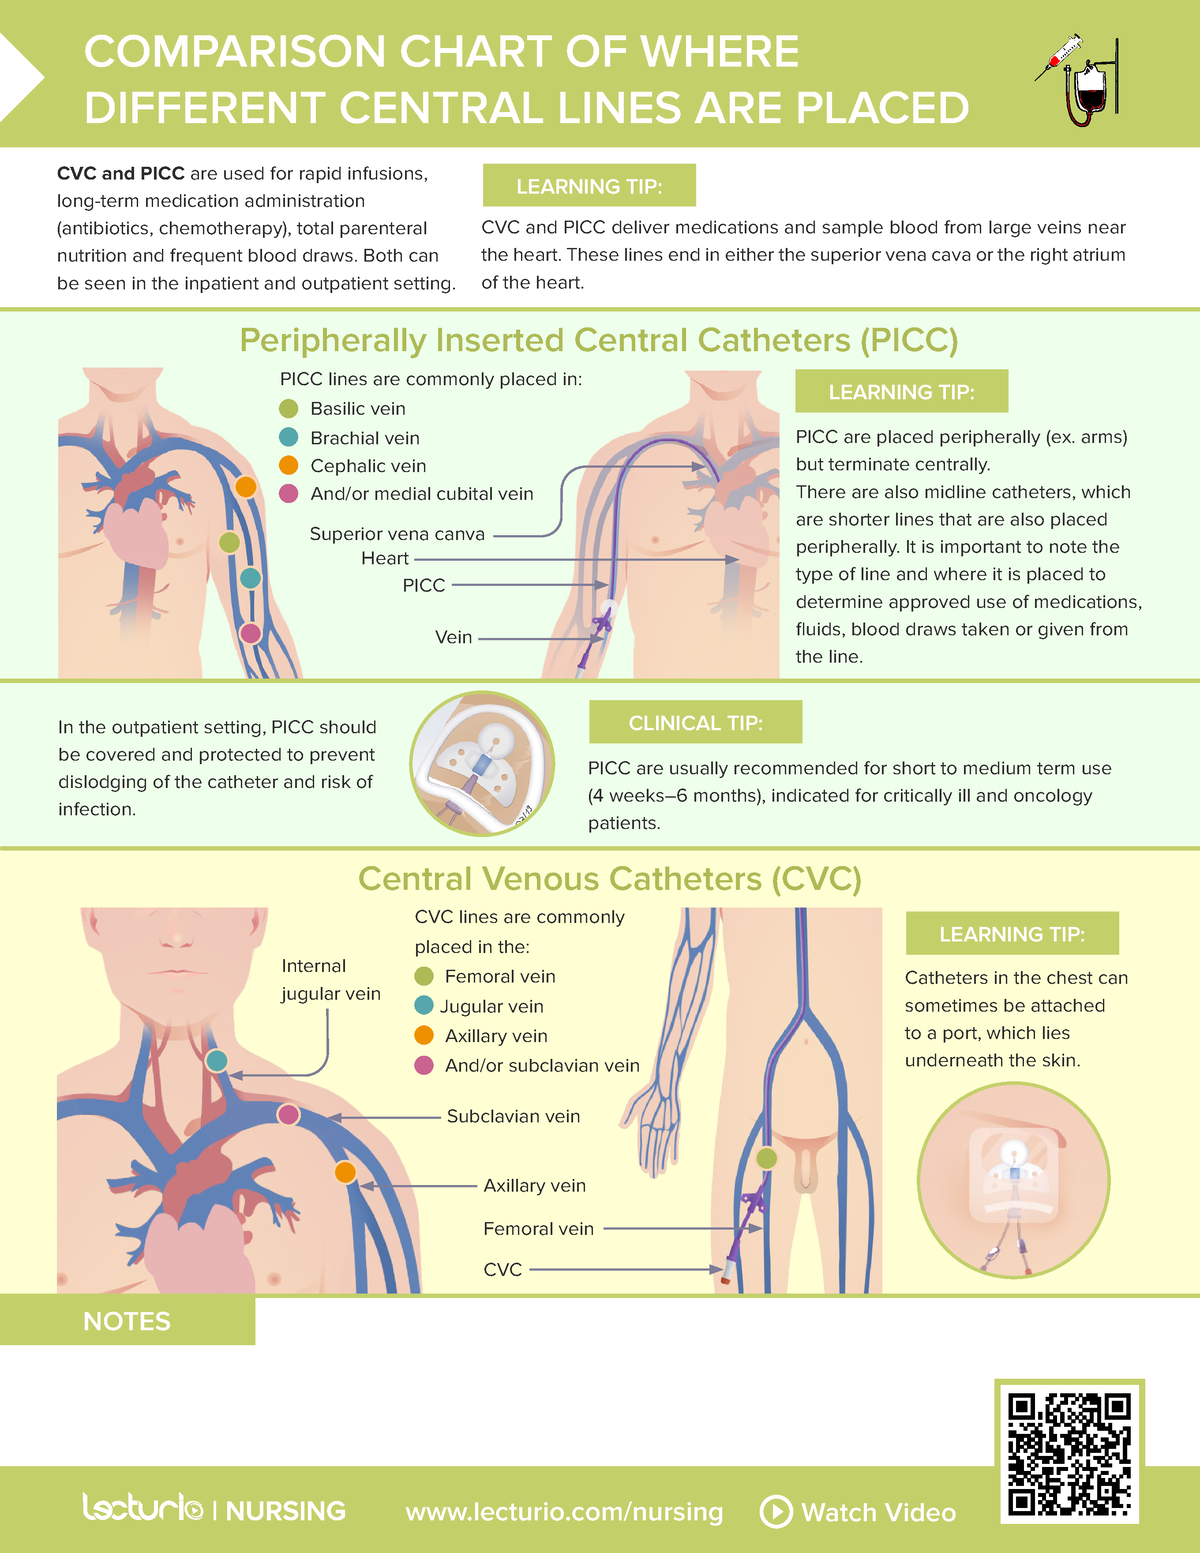
The whole certification process for PICC line education for nurses usually runs about 8 to 16 hours depending on whether your hospital includes bedside skills validation or keeps that separate. The classroom portion covers anatomy of the basilic and cephalic veins, ultrasound basics, sterile technique, and how to read a strip chart to confirm tip placement. That is the minimum. The real gap between what the course teaches and what happens on a Monday morning at 2 AM is where most problems show up. I ran into a case last year where the ultrasound course had us practicing exclusively on phantoms and one or two supervised bed partners who had nice, round, collapsible-free veins. Then I got assigned to a floor full of oncology patients with significant edema and chronic venous insufficiency. The first three attempts failed because the vein was there but the tissue compliance was wrong. The phantom never showed me that. I had to learn to use a higher frequency linear probe, apply less downward pressure than I was trained, and sometimes go for the brachial when the basilic just wouldn't cooperate. The course will tell you to aim for the mid-arm. It will not tell you that in practice, a mid-arm placement often ends up needing revision when the patient's arm position changes during transport. I learned to shoot for the lower third of the arm in patients who are going to be mobile. The tip location stays acceptable and you avoid migration issues down the line.
The Actual Workflow After You Complete the Didactic Course
You do not start placing lines the day you get the certificate. Your facility typically requires a supervised procedure log before they grant privileges. Most programs want between 10 and 25 insertions with competency sign-off from a trained preceptor. Some hospitals use a simulation to skills checklist. Others just watch you do the procedure and make a judgment call. Know which one yours is before you waste time on requirements that do not count. The insertion sequence goes like this. You measure the arm with the patient's arm abducted at 90 degrees. You mark the insertion site and the expected tip location based on the measurement. You prep the patient and yourself with full sterile barrier precautions. You use ultrasound to identify the vein, confirm it is compressible, and then proceed with the Seldinger technique. You advance the guidewire, thread the catheter, aspirate and flush, secure the dressing, and get a post-insertion chest X-ray to verify tip position. The part people rush is the measurement. A wrong measurement leads to malposition more often than any other single error. If you measure poorly, the tip can end up in the right atrium or too high in the superior vena cava. Both create complications. I use the anatomical landmark method as a backup when the external measurement seems unreliable due to body habitus. It is not as precise but it catches cases where the standard math fails.
Common Problems That Show Up During Training and Practice
Vasovagal reactions happen more frequently than the training videos suggest. A patient gets anxious, drops their blood pressure, and you are holding a needle over their vein. I keep a bag of ice and a cold pack nearby during insertions on nervous patients. Sometimes you just need to stop, lay them flat, and let the episode pass rather than pushing through it. Air embolism risk is real but manageable. The most common mistake during training is not clamping the catheter quickly enough when disconnecting the syringe or preparing to flush. I developed a habit of keeping my non-dominant hand on the catheter hub at all times during the procedure. It sounds minor but it has prevented at least one near-miss in my practice. Infection control during the insertion window is where the theory breaks down most often. The course will emphasize skin prep and draping. It will not prepare you for a patient who is diaphoretic, or whose skin needs extra preparation time due to residual antiseptic from a previous dressing change. I carry separate chlorhexidine prep sticks and allow a full three minutes of drying time even when the schedule is tight. The three minutes saves you from a line-associated bloodstream infection that will show up three days later and trace back to your insertion.
Get the Full Details
What Most Programs Leave Out
Complication management. The training covers insertion. It does not cover what to do when you suspect a thrombosis, when the catheter stops aspirating, or when you get a fever from an unknown source and need to determine if the PICC is involved. You need to understand how to order Doppler studies, when to consult vascular surgery, and how to decide between keeping the line in place with antibiotics versus removing it entirely. This comes from experience, not from a classroom module. Dressing selection is another area where the textbook answer and real-world constraints diverge. The guidelines say use a transparent semi-permeable dressing. They do not account for patients who sweat excessively, work in environments with heavy contamination risk, or have skin that reacts to the adhesive. I keep a range of dressing options available and choose based on the individual patient's situation rather than defaulting to the standard product every time. Documentation requirements also vary significantly between facilities. Some want you to record the exact vein used, the insertion depth in centimeters, the guidewire length, and the strip chart confirmation. Others are less stringent. Know your facility's expectations and document accordingly. Incomplete documentation is one of the most common findings during internal audits and it can compromise your privilege status more than a minor technique variation ever would.
How to Make the Most of Your Training
Find a preceptor who lets you observe multiple successful insertions before they touch you with a needle. Watch how they handle unexpected anatomy and how they talk to the patient during the procedure. Communication matters more than most courses admit. A calm patient has better veins. A cooperative patient gives you a clearer ultrasound image because they are not moving. Practice ultrasound identification outside of procedural training. Spend time scanning normal veins and abnormal veins separately. Learn what a thrombosed vein looks like so you can recognize it before you try to stick it. This skill separates competent inserters from the ones who end up causing complications because they could not tell the difference between a patent and a partially occluded vessel. Keep a personal log of every insertion attempt, successful or not. Note the vein chosen, the measurement technique, the difficulty level, and any complications. Review it quarterly. You will start seeing patterns in your own decision-making that the formal curriculum will not reveal to you.
The credentialing process itself is usually straightforward if you complete the required hours and procedures. Some hospitals require annual competency validation. Others do it every two years. Check your policy. The one thing nobody warns you about is that your privilege can be suspended if you go a certain number of months without placing a line, regardless of your annual training completion. Inactivity is a real risk for maintaining competence and institutional approval.