Understanding What You Can and Cannot Do With a PICC Line as an LPN
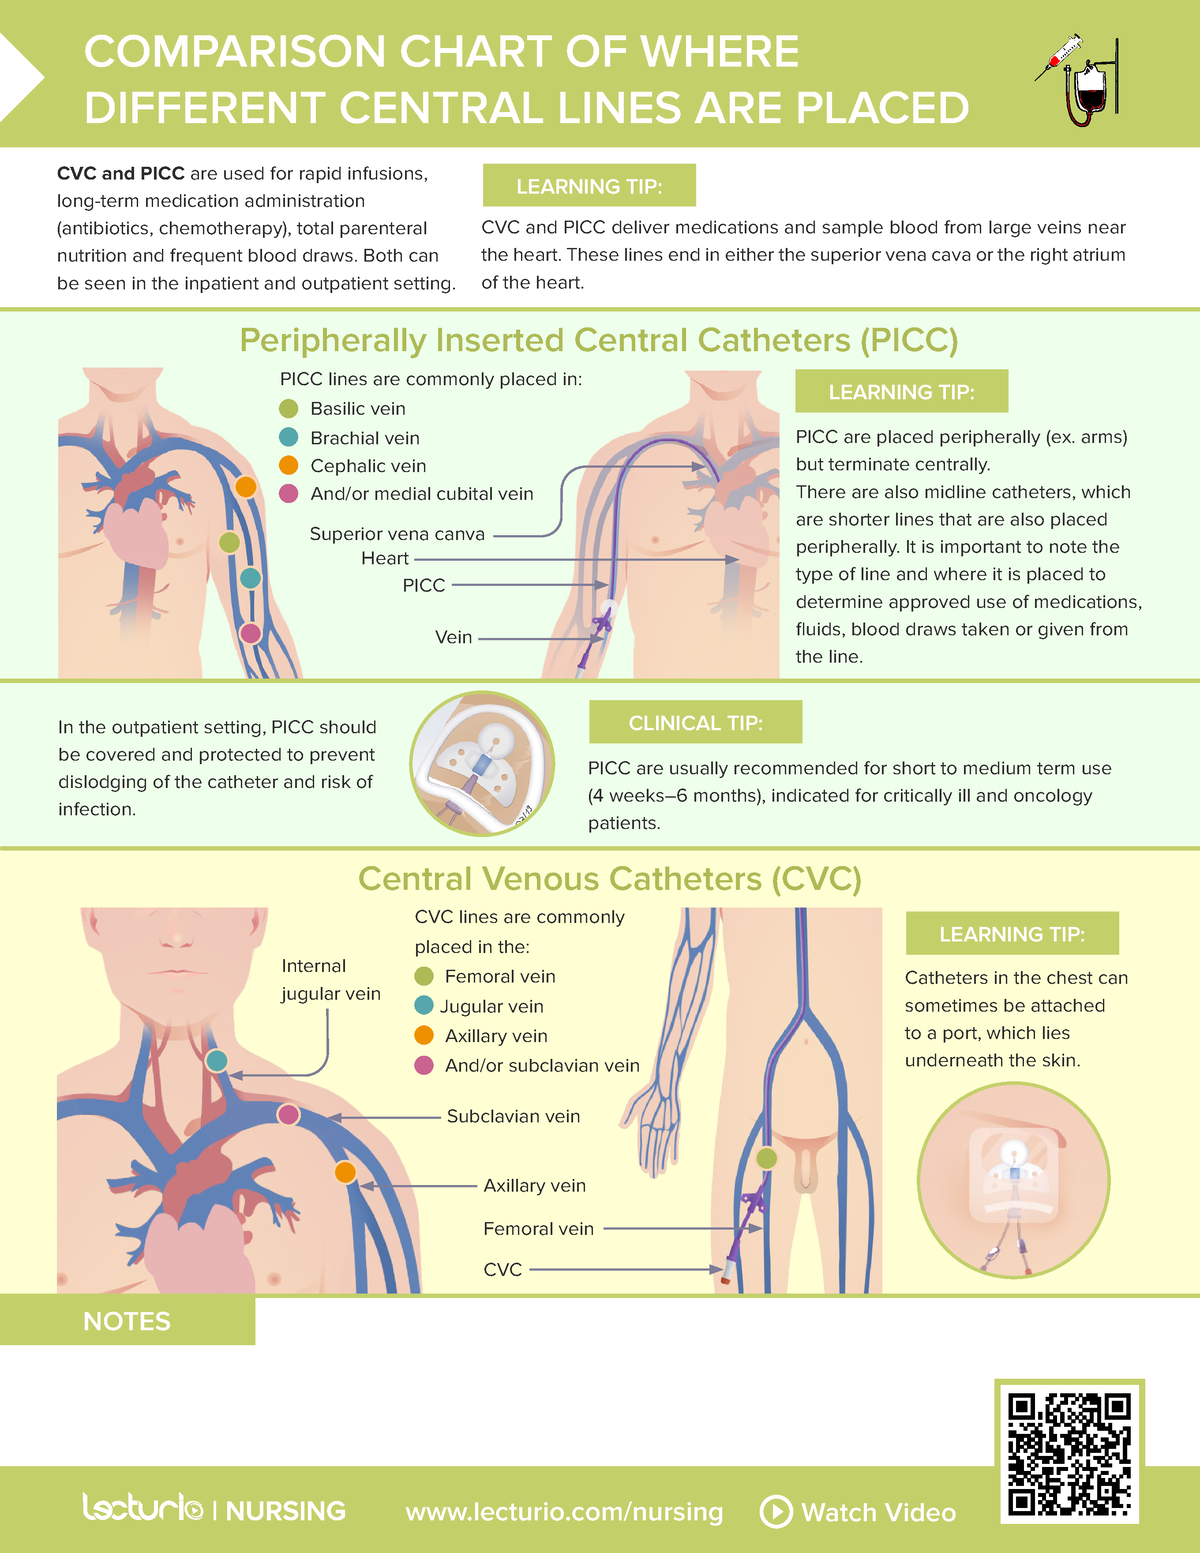
PICC line care is one of those things where the gap between textbook and real life is enormous. People think it's just a fancy IV. It isn't. It's a central line sitting with its tip in the SVC, and every task you do near it carries real risk if you cut corners. It depends entirely on your state board of nursing and your facility's policy. I've worked in three different states over the years, and the rules changed each time. In Texas, LPNs can do PICC line dressing changes and flushes after facility-based competency validation. In California, the scope is tighter — most facilities restrict PICC line management to RNs unless the LPN has completed a specific add-on certification. New York sits somewhere in between, allowing more IV therapy but still requiring explicit physician order and facility authorization. The baseline across nearly every jurisdiction: LPNs generally cannot insert PICC lines. They can maintain them. They can change dressings. They can flush and cap. They can draw blood from them in many states, though some facilities prohibit this without additional credentialing. What they absolutely should not do is attempt insertion, administer chemotherapy through a PICC without specialized training, or manage complications that require assessment-level decisions beyond their scope.
I learned this the hard way early in my career. I was working a med-surg floor in a rural hospital where staffing was thin. The charge nurse asked me to manage a new PICC line placement — dressings, flushes, everything. I said yes because I'd done peripheral IVs for years and figured it was the same concept. Wrong. The patient's arm was swollen by shift change. I hadn't caught the early sign of infiltration because nobody had properly oriented me to what I was actually looking for. An RN came in the next shift, saw the swelling, and confirmed the catheter had migrated. The patient needed a vascular surgery consult. I spent the next month going over my scope with the nurse educator, and we wrote up a quick-reference card that I keep on my locker to this day.
What LPNs Actually Do With PICC Lines Day to Day
Dressing changes are the bread and water. You'll be doing them every five to seven days for standard transparent dressings, or more often if the dressing gets damp, loose, or soiled. Use chlorhexidine prep if the facility protocol allows it — it's superior to povidone-iodine for reducing line-associated infections. Change the dressing in a way that minimizes catheter manipulation. Pull the old dressing off toward the insertion site, not away from it. That directional detail matters more than people realize because yanking the catheter back and forth can introduce bacteria into the tract. Flushes are straightforward if you follow the sequence. Saline flush before and after any medication administration. Heparin flush if your facility protocol requires it for locking — not all do anymore, and some use saline-only protocols for certain catheter types. Always use a 10 mL syringe. Smaller syringes create excessive pressure that can damage the catheter. I've seen cracked ports from people using 3 mL or 5 mL syringes out of habit. It happens more often than you'd think. Blood draws are where things get finicky. If your state and facility allow it, you'll need to discard the first few milliliters of blood before collecting your specimen. That priming volume in the catheter is saline or heparin, and it will contaminate your results if you don't clear it. A typical discard is 3 to 5 mL depending on catheter size and manufacturer guidelines. Don't skim this step. I once pulled a potassium level that read 8.2 from a PICC draw, panicked, and then realized we'd skipped the discard. The actual value was 4.1. False hyperkalemia from an undiscarded line is a classic preventable error.
Get the Full Details

Common Pitfalls and What Beginners Miss
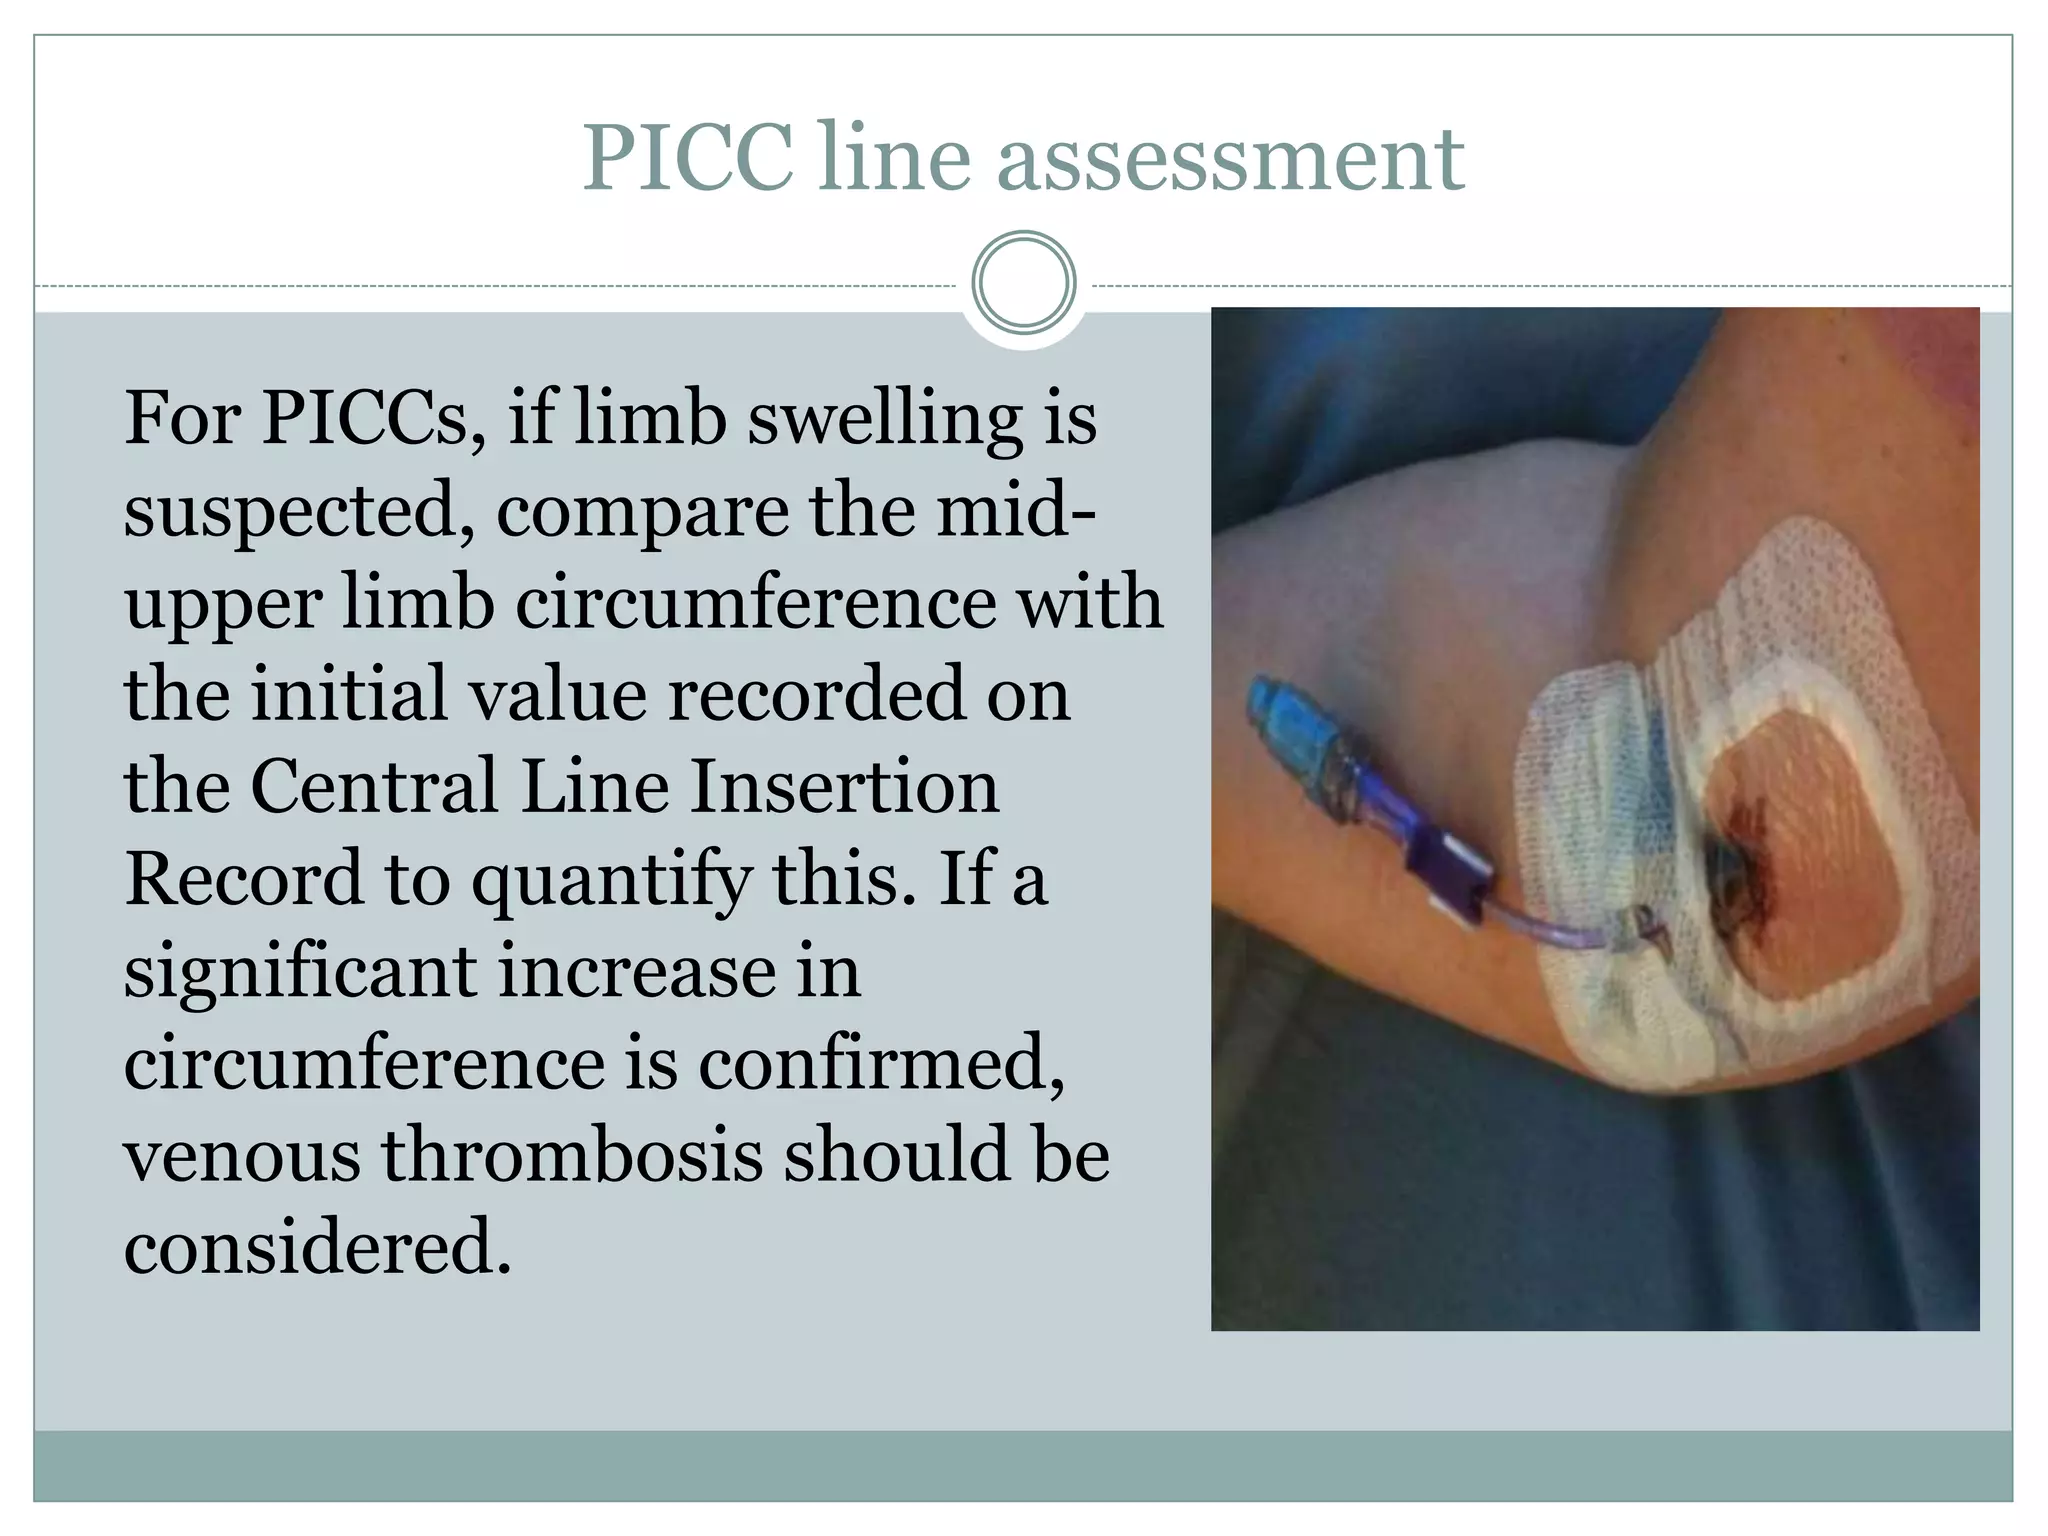
Here's something most orientation programs don't emphasize enough: assessing a PICC line isn't just about looking at the insertion site. You need to measure the external catheter length at the site and compare it to the baseline measurement documented during insertion. If the catheter has moved even a centimeter outward, that's significant. It could mean the line has slipped partially out of the SVC and into a smaller vein, which increases the risk of thrombosis and phlebitis. I made this mistake on a patient whose external length had increased by 2 cm over three days. We thought it was fine because the site looked clean. A stat X-ray confirmed the tip had migrated into the axillary vein. The line had to be repositioned. Another thing nobody really drills into you: knowing when to escalate. LPNs are often the ones spending the most time at the bedside with these lines. If something looks off — mild redness that's spreading, a patient complaining of shoulder pain on the affected side, unexplained low-grade fever — you report it. You don't wait to see if it resolves. PICC-related complications can progress fast. A small thrombus can become a full clot in a matter of hours. I've seen it happen on a night shift where a patient complained of vague arm discomfort and I documented it as "patient reports mild ache, no other concerns." By morning, the arm was frankly edematous and cyanotic. The attending was not pleased. That was the night I stopped documenting and started calling the resident immediately for any vascular concern. There's also the question of what happens when your scope doesn't cover something and the RN isn't available. This comes up on nights and weekends. The honest answer is: you do what your scope allows and you escalate what you can't handle. Don't attempt a procedure you're not credentialed for just because there's nobody else around. Document your assessment, document your limitations, and get the appropriate person involved. I've seen LPNs press charges through PICC lines they weren't trained to use because "the RN was in a code." That's not a situation you solve alone. Call the on-call RN. Call the physician. Don't improvise.
When You Should Push Back
Your license is yours. If a provider writes an order for something outside your scope — and this does happen — you have the responsibility to clarify before you carry it out. I had a hospitalist order aPICC line insertion for an LPN on a unit that didn't have LPN PICC privileges. I brought the order to the nurse manager, we reviewed the state board guidelines together, and the order was rewritten to an RN. That's the correct process. It's uncomfortable in the moment but far better than answering to the board later. The scope also changes based on patient acuity. Managing a stable PICC line on a chronic wound patient is very different from managing one on a post-op patient who's actively receiving vancomycin and vasopressors. The latter requires closer monitoring and more frequent assessment, and some facilities restrict LPN involvement in those cases entirely. Know your facility's policy documents. They're usually buried in the nursing manual or on the intranet somewhere, and reading them takes about twenty minutes that could save you from a major headache.