How to Build PICO Questions for Physical Therapy Practice
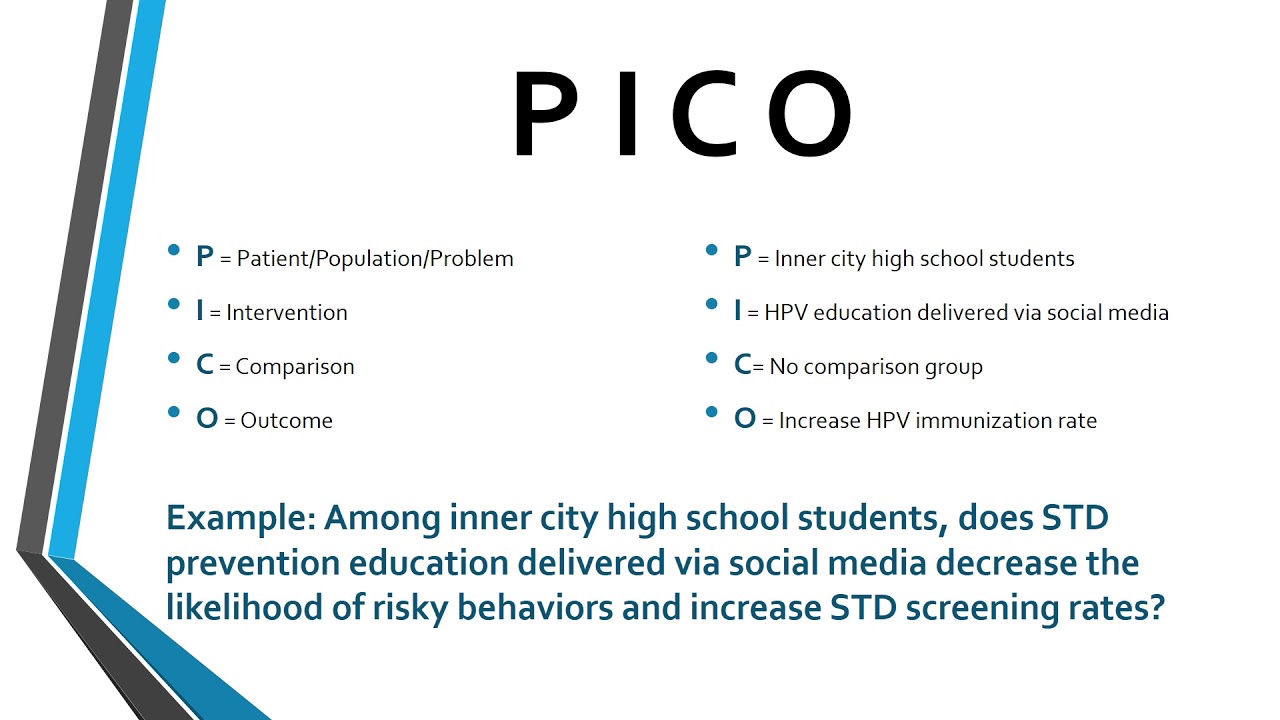
The PICO framework is your standard tool for turning a clinical curiosity into something searchable. In physical therapy, this usually means you start with a patient scenario and try to make it specific enough that PubMed or CINAHL will actually give you a useful result. I have spent years watching PTs write questions so vague that they get hundreds of irrelevant hits, then claim the evidence base is empty. P stands for Patient or Population. This is where you define the who. In physical therapy, that could be "adults with lateral hip pain" or "posterior cruciate ligament reconstruction patients at 6 weeks post-op." Being precise here matters because if you just write "knee pain," you are going to drown in results that include osteoarthritis, meniscal tears, and patellofemoral syndrome, none of which are interchangeable when you are trying to answer a treatment question. I stands for Intervention. This is the therapy or treatment you are evaluating. It could be something like "neuromuscular electrical stimulation," "hip strengthening program," or "manual therapy plus exercise." The trick here is being specific enough about dosage, frequency, and duration that the studies you pull back actually match what you are doing clinically.
C stands for Comparison. This is what you are measuring against. It could be sham treatment, a different exercise modality, standard care, or nothing at all. Some people skip this entirely, but leaving it out makes it harder to interpret whether any observed effect is real or just the natural history of the condition. O stands for Outcome. This is what you actually care about measuring. Pain scores, functional mobility, return to sport timelines, re-injury rates. Pick one or two primary outcomes. If you pick everything, you end up with a paper that is impossible to synthesize.
Pico Question Examples Physical Therapy in Practice
Here is a concrete example that works well in a clinic setting. A patient presents with chronic non-specific low back pain who has been sitting for work all day. Your clinical question becomes: In adults with chronic non-specific low back pain (P), does a progressive lumbar stabilization program (I) compared to general stretching exercises (C) improve functional disability as measured by the ODI (O)? That is searchable. That will pull back relevant studies within a reasonable time frame. Another one: In post-ACL reconstruction patients at 8 weeks post-op (P), does blood flow restriction training (I) compared to standard isolated quad strengthening (C) improve quadriceps strength and knee laxity measures (O)? Again, specific population, specific intervention with a clear mechanism, and outcomes you can actually measure in a clinic. And a third that trips people up less than you would think: In elderly patients with fall history (P), does a multicomponent balance training program (I) compared to usual care (C) reduce fall incidence over a 12-month period (O)? This one works because the population is well-defined, the intervention type is broad but recognizable in the literature, and the outcome is a hard clinical endpoint.
Get the Full Details

The Part Nobody Tells You About Formatting These Questions
The biggest mistake I see is making the population too narrow. You will spend twenty minutes refining "adults aged 45 to 62 with stage II diabetic peripheral neuropathy who walk more than 0.8 meters per second" and then find exactly zero studies that match that exactly. The search comes back empty and you conclude there is no evidence. There probably is evidence. It is just in a broader population bucket. My workaround for this is to build the PICO question in layers. Start with a slightly broader population, run the search, and then filter down manually using inclusion and exclusion criteria. I usually broaden the age range by ten years on each side, drop the functional threshold entirely for the initial sweep, and let the study selection do the rest of the narrowing. This approach turned a completely empty search into about eight relevant papers in under ten minutes for a patient presentation I had with moderate severe peripheral neuropathy and gait instability. Another thing that catches people off guard is the intervention specificity trap. You might write "manual therapy" as your intervention and get thousands of results, most of which are completely irrelevant to what you actually do. In physical therapy, manual therapy ranges from high-velocity low-amplitude thrusts to gentle soft tissue mobilization to joint play techniques, and the evidence for each is wildly different. I started specifying the technique, the body region, and the intended physiological mechanism when I realized my search results were a mess. "High-velocity low-amplitude thrust manipulation of the lumbar spine" pulled back a completely different and much more usable set of studies than just "lumbar manual therapy" ever did.
When PICO Falls Short in Physical Therapy
The framework works best for treatment and prognosis questions. It struggles with quality improvement questions, diagnostic accuracy questions, and patient experience questions. If you are trying to ask something like "what barriers do patients with hip osteoarthritis report when adhering to a home exercise program," PICO is not the right tool. That is a qualitative question and you need a different framework, like SPIDER or PICo with a lowercase c for context. It also falls apart when the intervention is highly individualized or protocol-driven in a way that does not translate to a researchable format. Clinical Pilates, for example, is something many physical therapists use, but the literature treats it inconsistently at best. Some studies call it "core stabilization," others call it "pilates-based exercise," and the intervention description varies so much across papers that even a well-formed PICO question can struggle to pull back coherent results. Cost-effectiveness questions are another weak point. PICO does not naturally accommodate economic outcomes in a way that produces clean searches. If you are asking whether a certain physical therapy intervention reduces total healthcare costs over two years, you are better off looking at systematic reviews that have already done the economic synthesis rather than building your own PICO from scratch.
Practical Steps to Using This Framework Daily
Start with the patient. Keep the clinical question front of mind while you are assessing, not after you have finished documentation. This prevents the question from becoming overly broad because you forgot the specific details of the case. Write the PICO components on paper or in a notes app before you open a database. This forces you to confront the vagueness in your own thinking before it becomes a vague search string. I noticed this made a real difference after I stopped typing directly into PubMed and started drafting the components separately first. The searches became faster and the results more relevant, mostly because I had already decided what mattered. Use MeSH terms and CINAHL subject headings once you have your PICO drafted. The natural language terms you write into the question do not always map cleanly onto database indexing. Adding the controlled vocabulary terms alongside your keywords usually doubles your yield without adding noise. This took me from finding three relevant studies on one topic to finding eleven in a single afternoon, which changed the entire direction of my treatment plan for a patient with shoulder impingement who was not responding to standard rehabilitation.

Don't treat PICO as the final word on clinical reasoning. It is a search tool, not a decision-making tool. The question it helps you answer is "what does the evidence say about this specific clinical scenario?" It does not tell you whether the evidence applies to your patient, whether the study quality is adequate, or whether the outcome matters to the person sitting on your treatment table. Those are separate judgments that require clinical experience, not a framework.