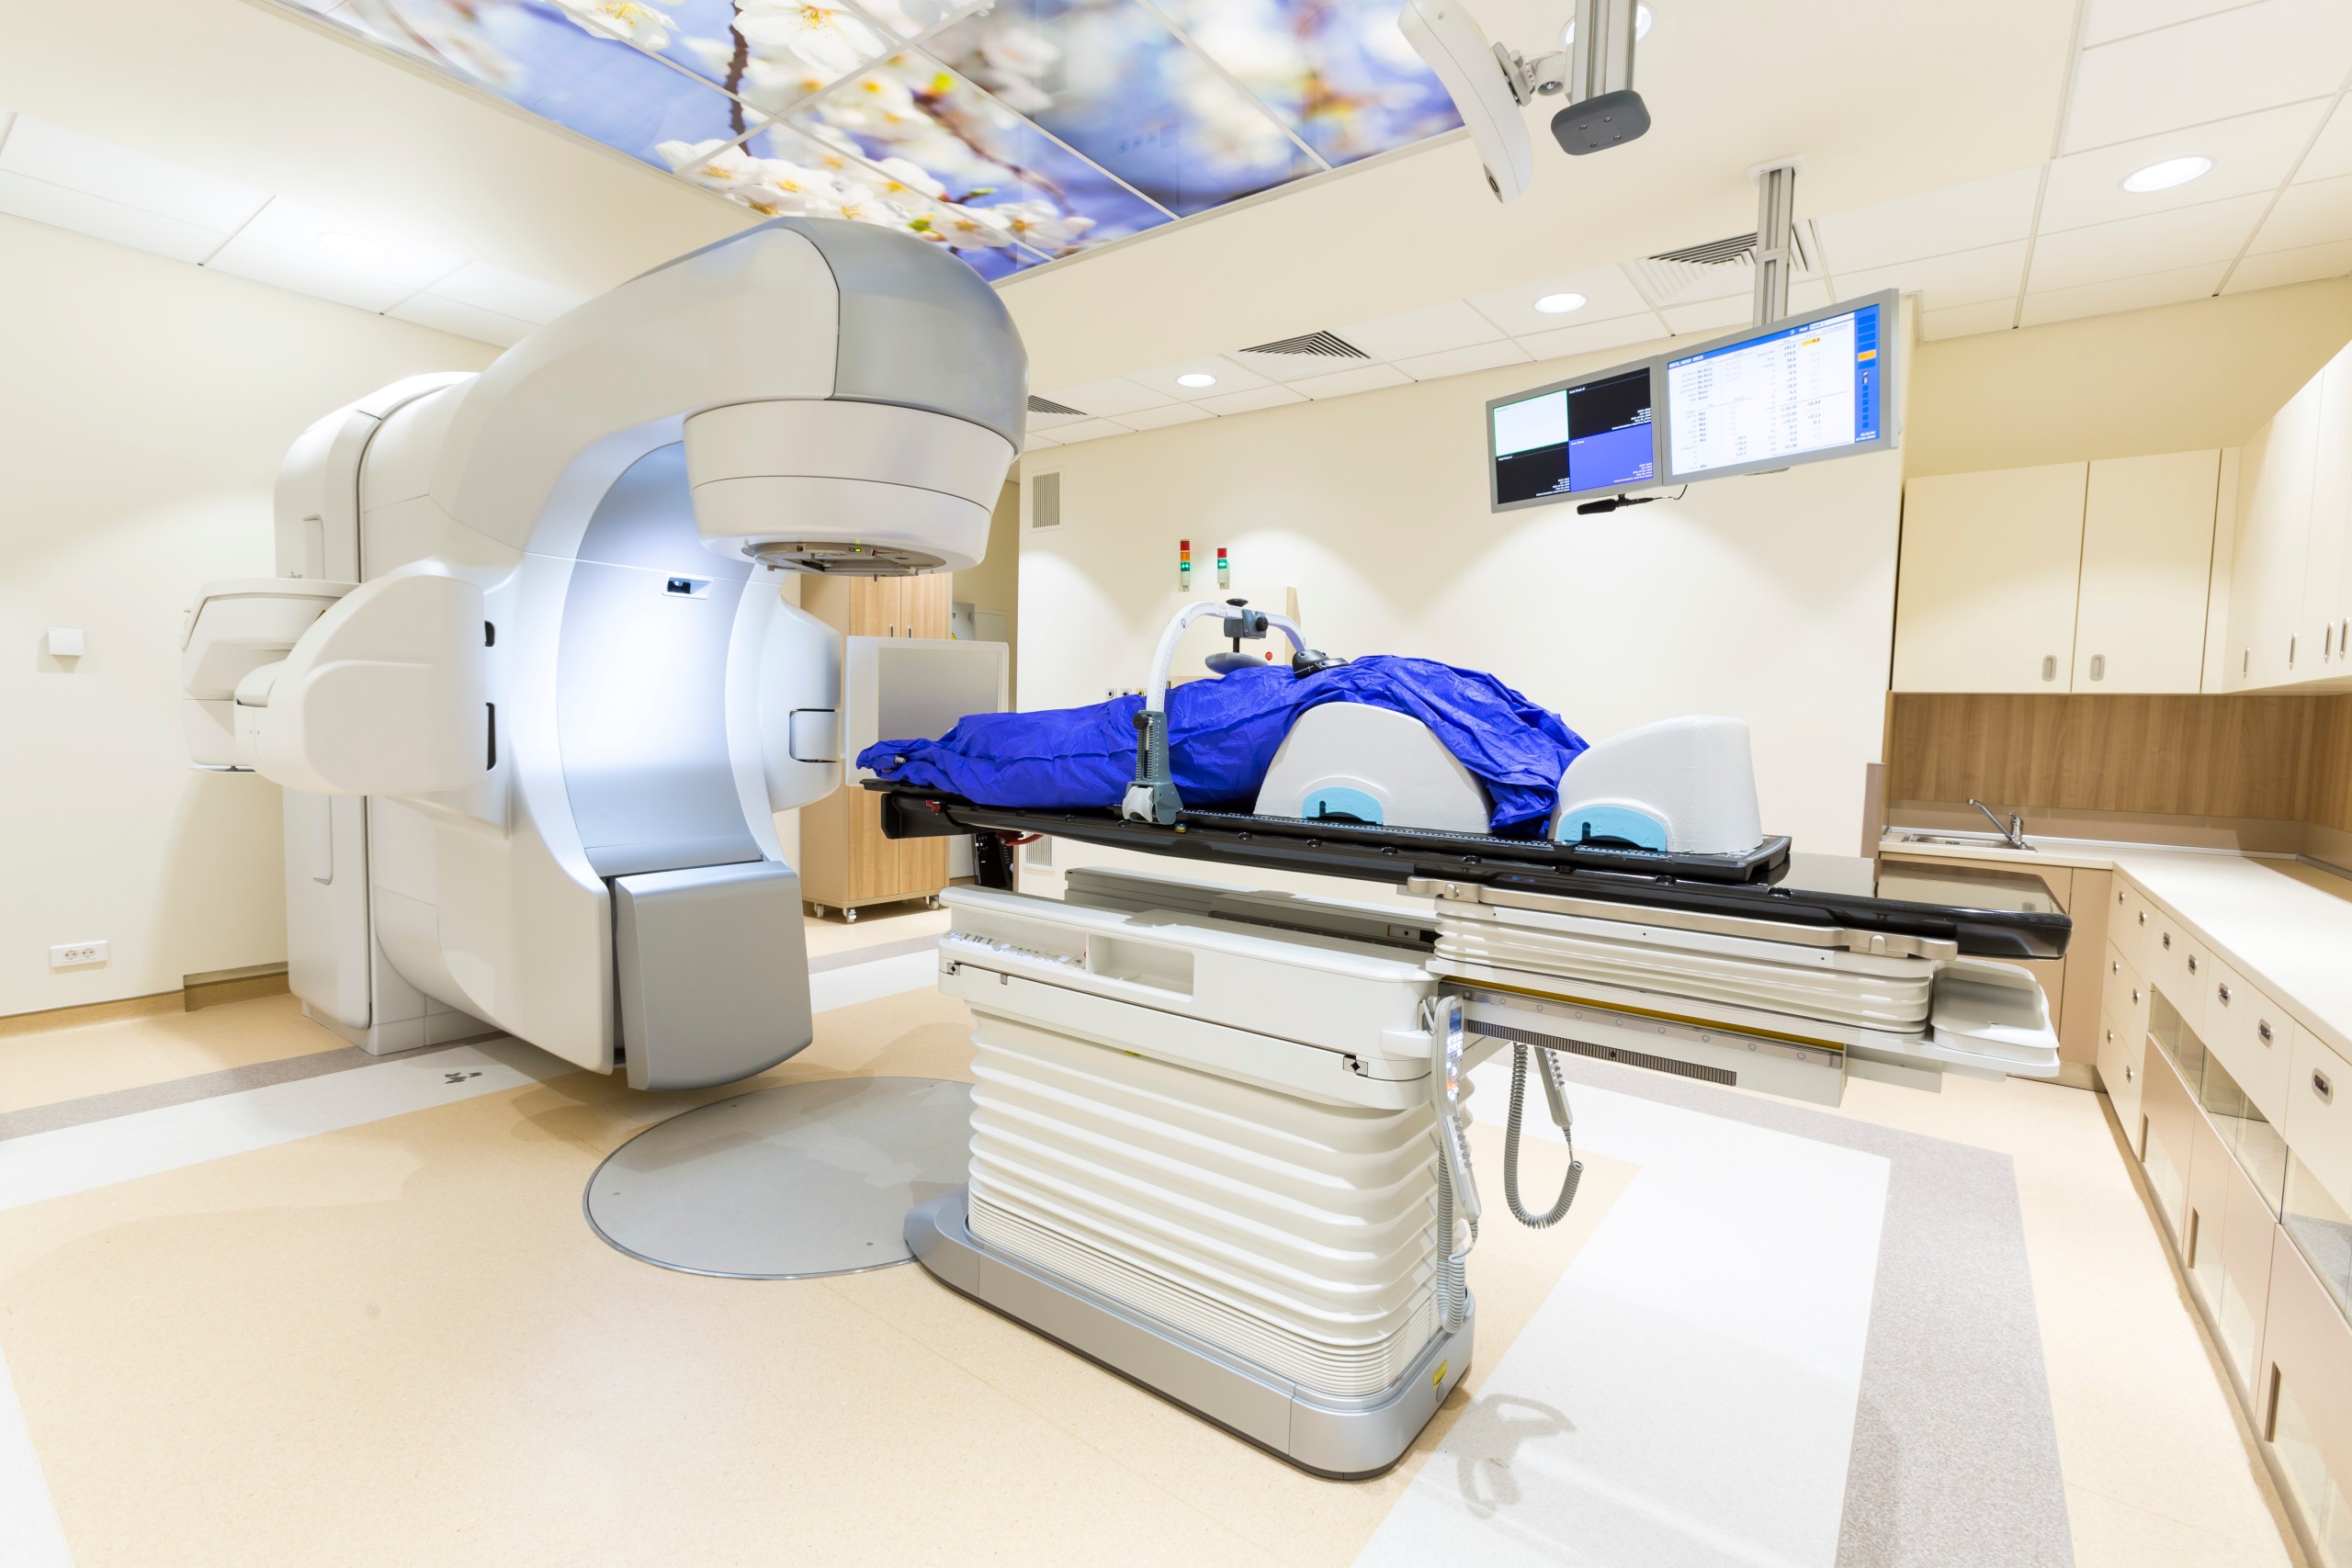
Working with Medical Imaging in Radiation Oncology
Radiation therapy relies heavily on accurate imaging to plan and deliver treatment. When you hear people talking about Pictures Of Radiation Therapy, they are usually referring to the diagnostic images used during the entire treatment pathway — simulation CTs, MRI fusion images, cone-beam CTs taken on the treatment machine, and the portal or orthogonal images checked before each fraction. It is not one single thing. It is a whole chain of imaging studies that feed into each other. The primary source is the simulation CT scan. This is a high-resolution CT performed on a dedicated simulation scanner while the patient is positioned exactly as they will be for treatment. Sometimes additional imaging like MRI or PET is fused on top of the CT to better define tumor boundaries. The radiation oncologist uses these to draw target volumes, and the medical physicist verifies that the imaging geometry matches what the treatment machine expects. After the plan is created, the first treatment day includes baseline portal images or electronic portal imaging device (EPID) images to confirm the patient was set up correctly. Throughout the course, daily cone-beam CT scans or orthogonal X-rays are acquired to check for positional changes.
The Practical Workflow
In my experience, the most common workflow starts with the simulation CT. The patient arrives at the simulation suite, gets immobilized with their positioning device, and the CT is scanned from skull base to mid-thigh or through the relevant region. The images are sent to the treatment planning system where the dosimetrist or physicist constructs the plan. Before the plan goes to the physician for approval, the medical physicist performs an image-based quality check — verifying that the isocenter coordinates, field shapes, and imaging landmarks all align between the planning CT and the treatment delivery system. On treatment days, the daily imaging check is routine. The patient lies on the treatment couch, the cone-beam CT is acquired, and the image is automatically or manually registered to the planning CT. If the shift exceeds the agreed tolerance — typically three millimeters for most sites — the team decides whether to correct it or flag it for further review.
A Problem I Have Actually Dealt With
During a stereotactic body radiation therapy (SBRT) lung case, I noticed that the daily cone-beam CT registration kept drifting by about four to five millimeters in the superior-inferior direction despite the patient being properly positioned. The planning CT had been acquired with a breath-hold protocol, but the CBCT was a free-breathing scan. The soft-tissue match looked fine on the CBCT, but when we overlay-planned it back onto the planning CT, the target seemed shifted. The issue was respiratory motion mismatch between the two imaging modalities. The workaround was straightforward but required coordination. We switched to a 4D-CT simulation so the internal target volume accounted for the breathing range, and then we used internal landmark-based registration on the CBCT rather than relying on the surface anatomy that moved with respiration. That reduced the apparent drift to under two millimeters. One of the most common errors is assuming that a good-looking image match on the CBCT means the treatment is correctly targeted. It does not. The CBCT has lower spatial resolution than the planning CT, and the soft-tissue contrast can be misleading at field edges. Always cross-check with the orthogonal portal images if available, and verify the bony anatomy independently from the soft-tissue registration. Another pitfall involves ignoring the imaging time delay. Between the simulation CT and the actual treatment, tissue changes can occur — tumor shrinkage, weight loss, fluid shifts. A patient who lost fifteen pounds between simulation and week three of treatment may have significant geometric changes that a simple rigid registration will not capture. In those cases, adaptive replanning is necessary, and the images need to be re-evaluated for target volume recalculation.
Get the Full Details

Limitations You Need to Accept
Imaging in radiation therapy is not perfect. Cone-beam CT has limited soft-tissue contrast compared to MRI. Portal images are two-dimensional projections of a three-dimensional setup, so overlap structures can hide setup errors. Fluoroscopic imaging introduces motion blur. And dose from imaging itself, while small per fraction, accumulates over a typical twenty-five-fraction course. For certain sites — particularly pancreatic and liver tumors — the imaging challenge is severe. Respiratory motion, low contrast between tumor and surrounding tissue, and interfraction organ displacement make image-guided accuracy extremely difficult. In those situations, some centers use fiducial markers or internal gold seeds to improve tracking, though placing fiducials carries its own risks and is not appropriate for every patient. For upper abdominal tumors, the most reliable approach I have seen is combining 4D-CT simulation with respiratory-gated treatment delivery, accepting the tradeoff in workflow complexity and longer treatment times.
Documents and Reference Images
If you are looking for reference Pictures Of Radiation Therapy to study the standard workflows, the most useful sources are the medical physics textbooks and professional society guidelines. The AAPM (American Association of Physicists in Medicine) has published extensive task group reports on image guidance for radiation therapy. The ICRU reports, particularly ICRU Report 62 for target definition and ICRU Report 83 for prescription and reporting, contain standardized image-based terminology that is used across clinics. Online resources like the Radiopaedia database also have annotated imaging cases that show typical simulation CTs, contouring conventions, and portal image examples for different treatment sites. The practical value of these images is not in memorizing them but in understanding how each modality fits into the verification chain. A simulation CT tells you where the anatomy was on planning day. A CBCT tells you where it is today. Portal images tell you whether the beams themselves are aligned. When those three agree, you have confidence in the setup. When they do not, you investigate before delivering the next fraction.