What The Photos Actually Show
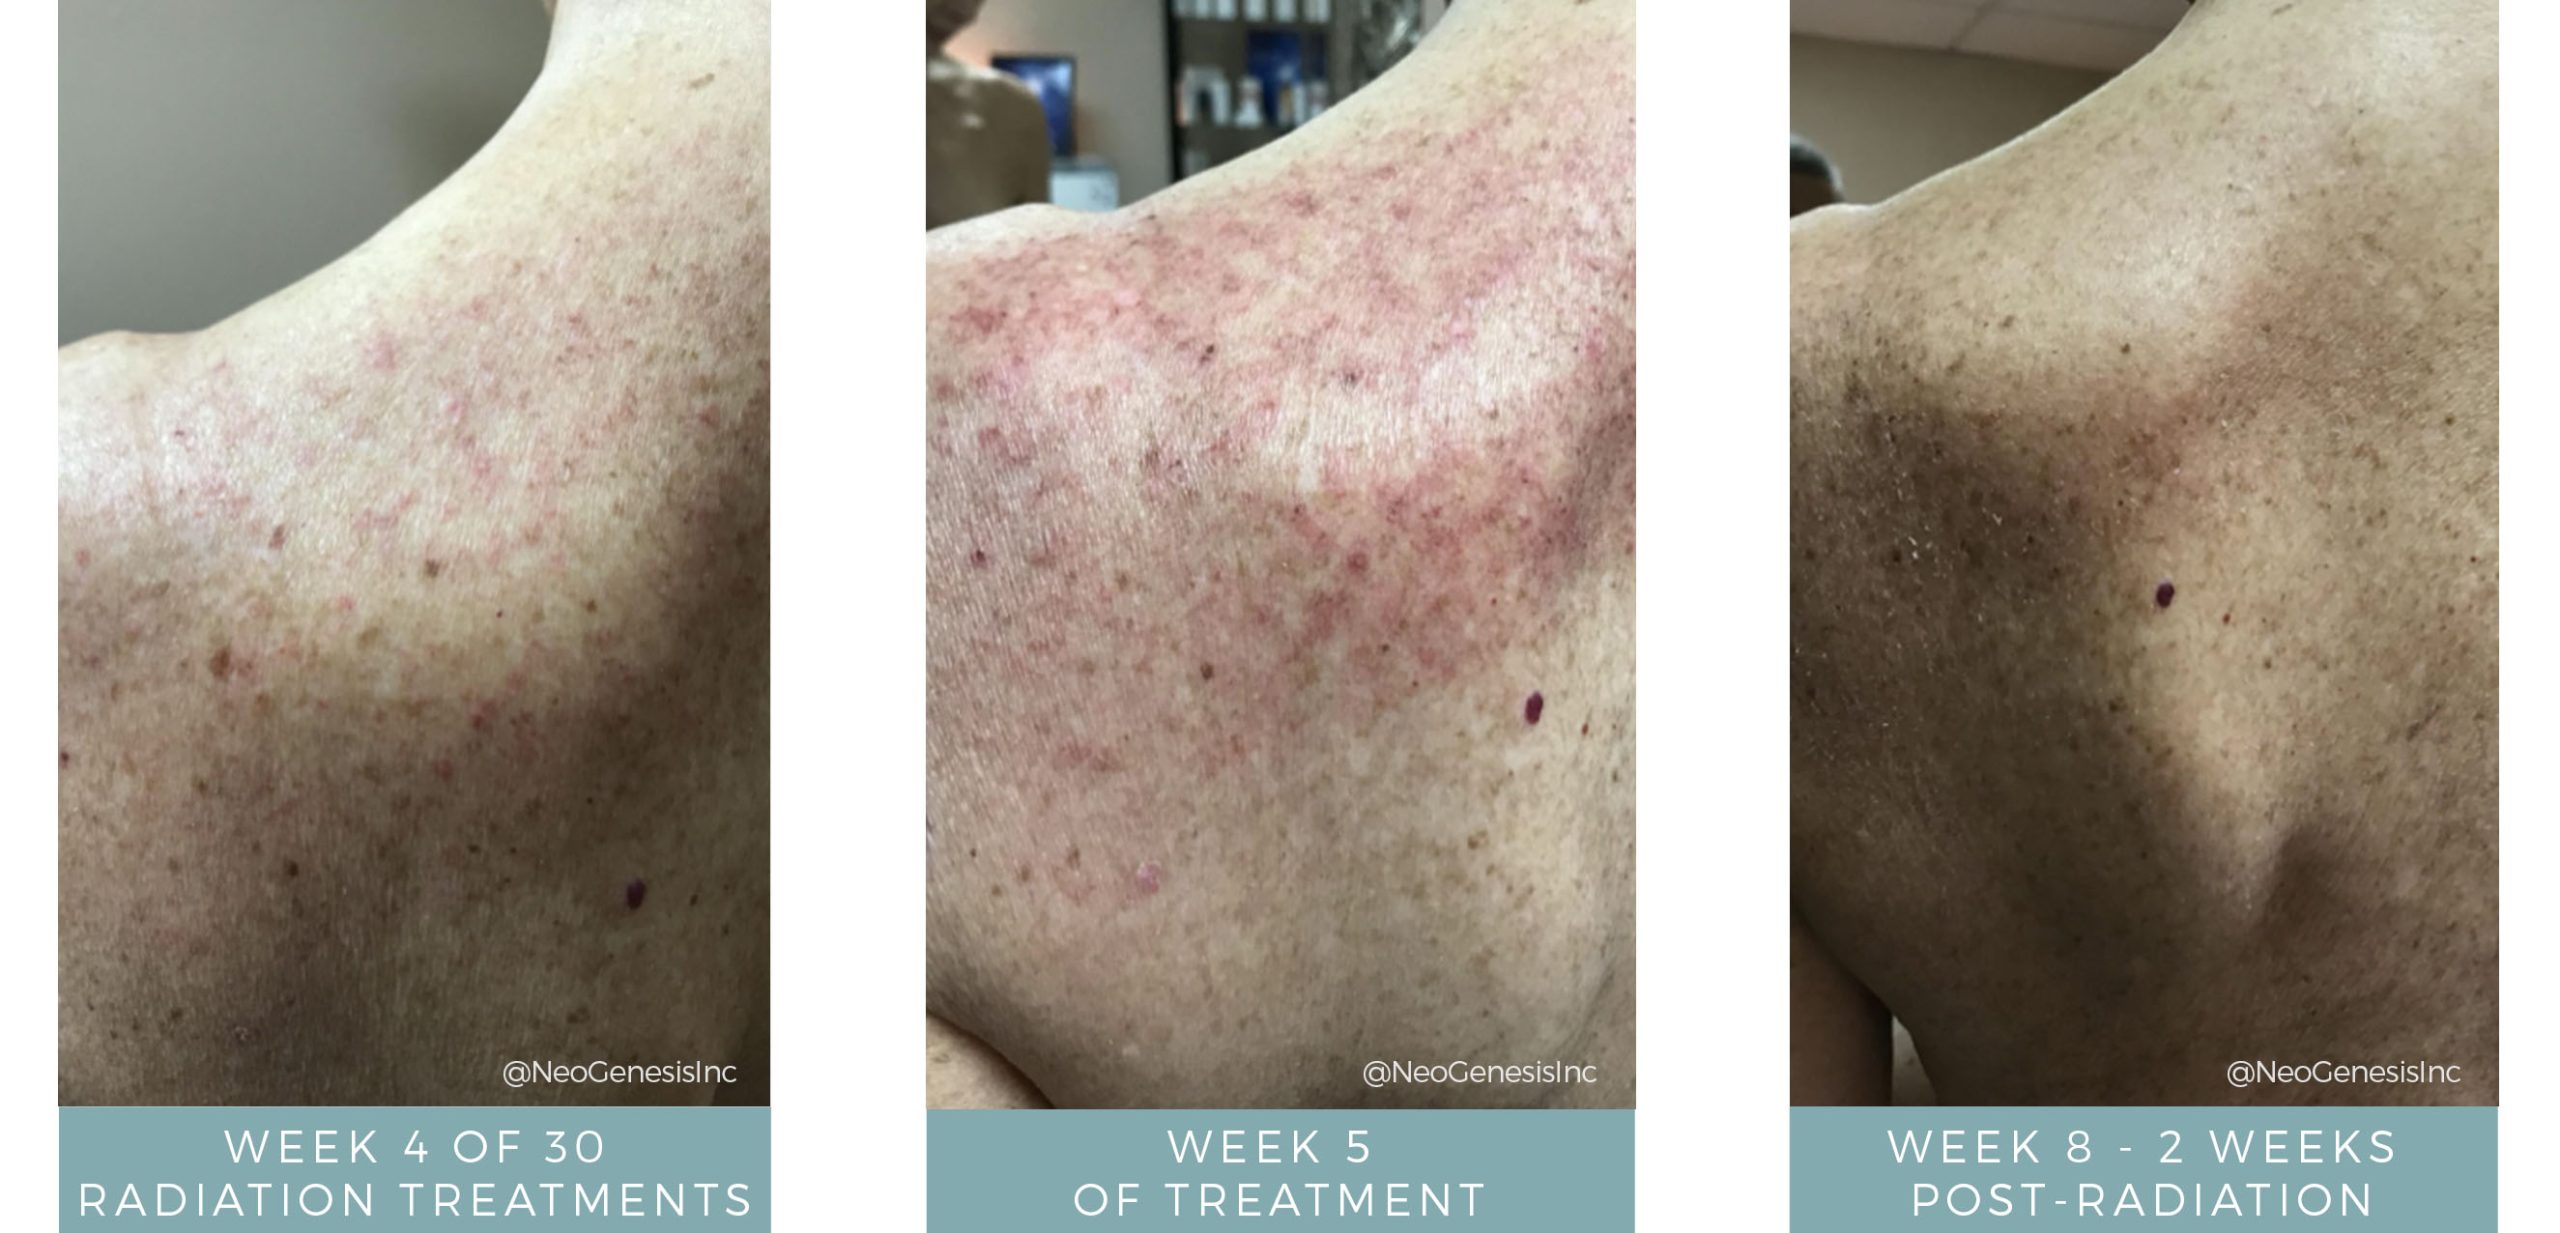
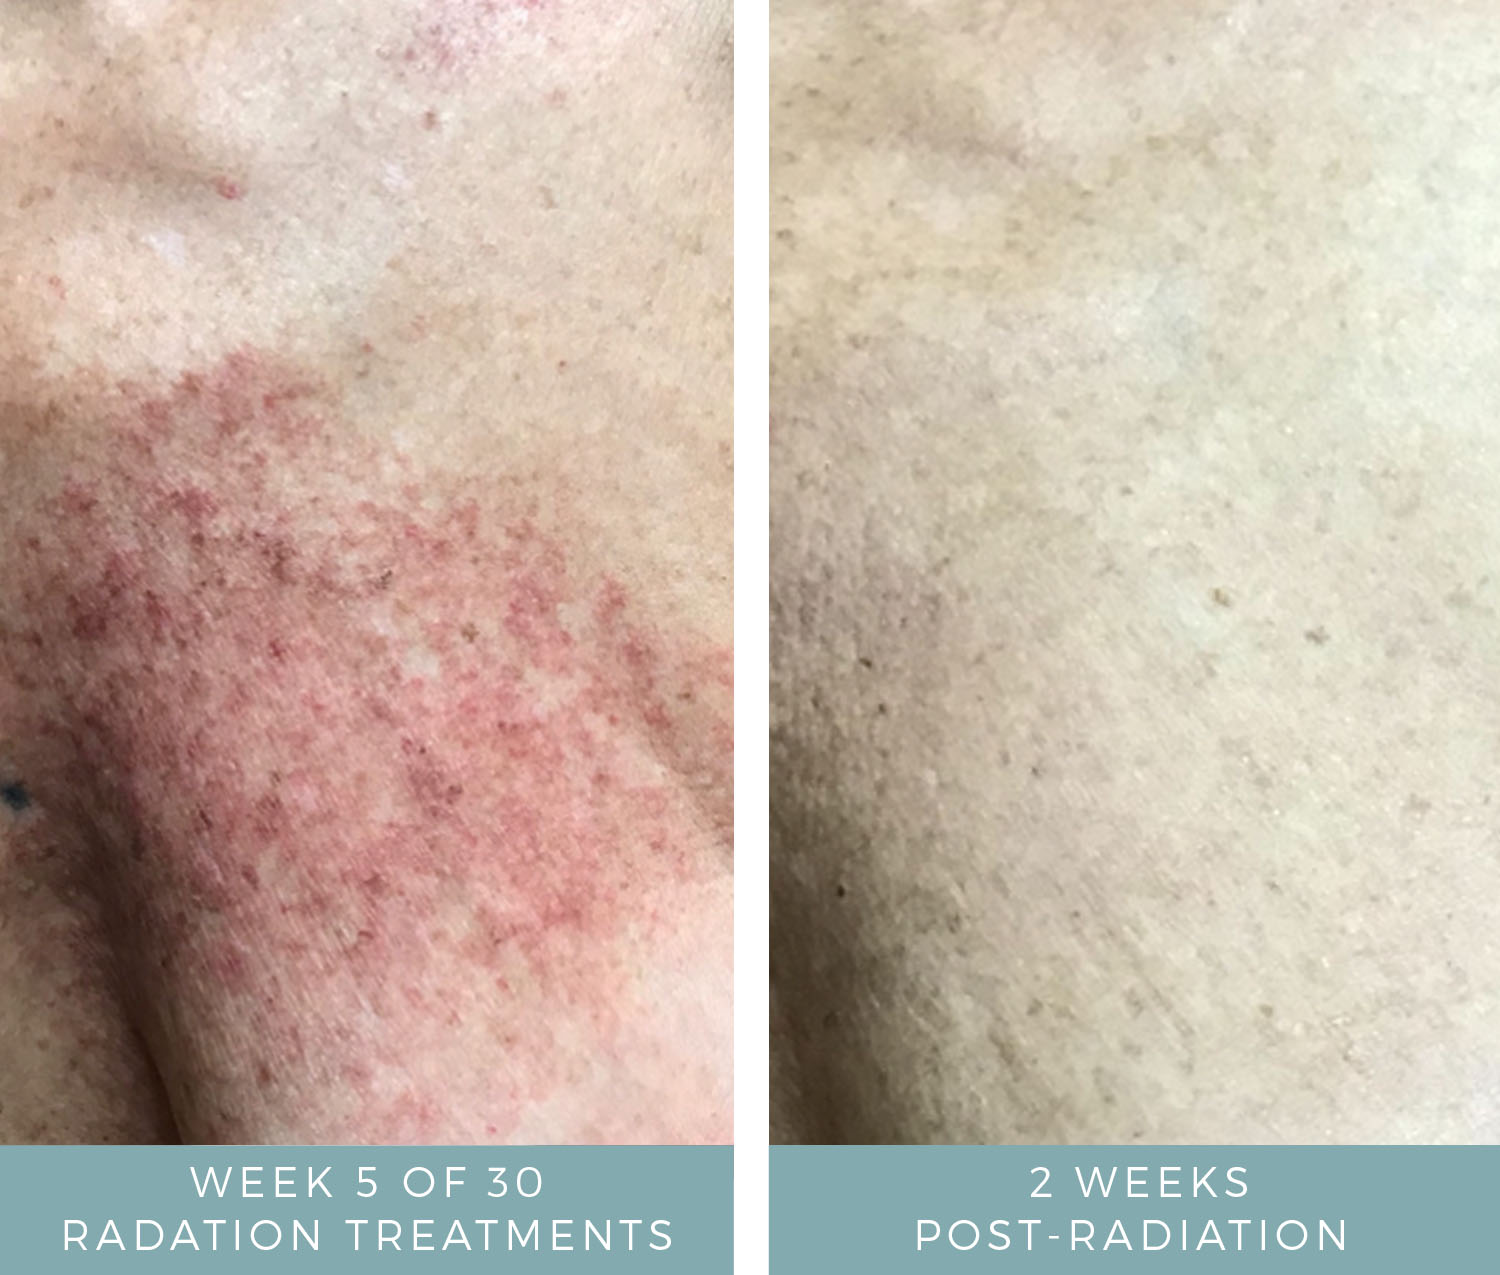
Radiation dermatitis is a spectrum, not a single condition. When I look at pictures of skin after radiation therapy, the first thing I check is the grade. Grade 1 is faint erythema, barely noticeable. Grade 2 is moderate to bright redness with patchy moist desquamation, usually in the skin folds. Grade 3 is confluent moist desquamation covering most of the field. Grade 4 is ulceration or necrosis, which is rare but real. A patient in breast radiation often presents with Grade 2 around the inframammary fold where moisture gets trapped. That looks dramatically different from dry desquamation on the scalp, which peels in thin sheets and never truly wets out. Documenting these changes matters more than people realize. When I first started working through oncology imaging and dermatology workflows, I noticed that photos taken at the same time of day, with consistent lighting, made it significantly easier to track progression week to week. Flash completely distorts the color grade. I switched to natural window light and a white balance card and the improvement in consistency was immediately visible. This helped my radiation oncologist calibrate whether a patient needed a treatment break or could continue through. Start by setting up a dedicated space. A corner near a north-facing window eliminates direct sunlight, which shifts colors unpredictably throughout the day. You need a simple backdrop. A plain white sheet or poster board works fine. Place it flat behind the area you are photographing. Remove jewelry and clothing that might frame the shot inconsistently.
Turn off your phone flash entirely. Use the rear camera, not the front-facing one. The rear sensor on most modern phones captures significantly more detail and color accuracy. Set the exposure manually if your camera app allows it. Tap on the skin area and slide the brightness indicator down slightly. Radiation dermatitis often looks worse in automatically exposed photos because the camera tries to compensate for lighter patches of desquamation. Add a scale reference in every image. A ruler, a coin, or even a standard credit card placed at the edge of the field gives clinical context. Without scale, a picture of erythema on an arm looks nearly identical to the same rash on a torso, but the surface area differences are clinically relevant. I once reviewed a set of photos from a head and neck patient where the team couldn't tell if the reaction was progressing or stabilizing because the distance from the camera kept changing between sessions. We standardized at two feet from the skin surface and used a tape measure on the lens to confirm positioning. Take the photos at consistent intervals. Weekly is standard during curative radiation. For patients on hypofractionated regimens, twice weekly may be necessary. Same time of day matters because skin blood flow changes with circadian rhythm and activity level. A patient who just showered will have more erythema than the same patient three hours later. I recommend photographing in the late morning before any significant physical activity, and always after the patient has been sitting quietly for at least ten minutes.
Common Presentation Patterns By Treatment Site
Breast and chest wall radiation produces a characteristic pattern. The skin becomes uniformly erythematous within the port boundaries. Moist desquamation appears most frequently in the inframammary crease because friction and occlusion create a microenvironment that accelerates breakdown. I had a patient whose reaction stayed mild on the anterior breast but developed severe Grade 3 dermatitis exclusively in the fold. We switched her from a standard aqueous cream to a hydrocolloid dressing placed only in the crease, and the reaction stabilized within four days. The rest of the field continued with regular moisturizer alone. Head and neck treatments produce a very different visual profile. The skin tends to become dry and hyperpigmented rather than moist. You will see bronzing and flaking across the treatment field. Ulceration is uncommon unless the mucosal surfaces are involved. These patients often complain about the cosmetic appearance more than discomfort, and rightfully so. The discoloration can persist for months after treatment ends. Skin fold areas throughout the body respond similarly due to the same mechanical factors. Axilla, groin, and perineal radiation fields all share the risk of intertriginous breakdown. The solution is always the same in principle: reduce moisture, reduce friction, and protect the barrier. I use a combination of silicone barrier film applied to intact skin surrounding the field and soft foam dressings placed directly in the fold where the skin contacts skin.
Get the Full Details

Extremity radiation, particularly for lymphoma or sarcoma cases, shows prominent telangiectasia in follow-up images. These fine red lines appear weeks to months after treatment completes and represent permanent vascular changes. They do not indicate active dermatitis. Patients sometimes photograph them thinking something new is developing. Understanding that this is a late effect rather than an acute flare prevents unnecessary anxiety and clinic visits.
Technical Details Most People Miss
Color calibration is the single most important technical factor and the one most photography guides skip entirely. A white balance reference card costs about five dollars and changes everything. Place it in the frame for the first photo of each session. You can adjust the color grading in any free editing tool afterward and correct the entire set to a neutral baseline. Without this, photos taken on different days or with different devices will show inconsistent color rendering, making grade assessment unreliable. Resolution matters less than you might think for clinical documentation. A 4-megapixel image stored as a JPEG is perfectly adequate for tracking dermatitis progression. Larger files create storage and sharing problems without adding diagnostic value. The critical factor is consistency, not megapixels. I stopped carrying a dedicated camera years ago. My phone handles everything now, and the quality difference is irrelevant for this purpose. Lighting direction should be consistent. Side lighting reveals texture changes like desquamation and induration better than frontal lighting. However, frontal diffused light is better for color assessment. I take both: one straight-on for color grading and one at a forty-five degree angle to capture surface texture. Two photos per session takes thirty seconds and provides substantially more information.
Limitations And What Photos Cannot Show
Pictures of skin after radiation therapy capture only the epidermal and superficial dermal changes. They cannot show subcutaneous fibrosis, which develops over months and affects tissue compliance. They cannot reveal mucosal involvement in head and neck patients. They cannot assess pain levels, sensation changes, or nerve damage. A photo of relatively mild erythema might belong to a patient with severe pain, while a dramatically red field might be barely uncomfortable. Clinical correlation is always necessary. Some patients develop radiation recall dermatitis triggered by chemotherapy drugs weeks or months after radiation completes. The visual appearance can be identical to acute radiation dermatitis, but the mechanism and management differ. Photos alone cannot distinguish these. A detailed medication history is required. Differential diagnosis is another blind spot. Erysipelas, cellulitis, contact dermatitis from topical agents, and fungal superinfection can all mimic radiation dermatitis on photos. I once spent two weeks managing what I thought was worsening radiation reaction in a breast patient until a culture grew out a staphylococcal infection. The skin looked identical. Swabbing a weeping area and sending it for culture is cheap and fast. It should be routine when the visual presentation does not match the expected trajectory.
Practical Tips That Come From Doing This Regularly
Teach patients to take their own photos before they leave the clinic. Provide a printed instruction card with exact specifications: no flash, natural light, ruler in frame, same time of day. Most patients will follow written instructions better than verbal ones. I laminate a small card and give it to every patient starting Grade 2 or higher reactions. Organize images chronologically on a single screen. Most phone gallery apps sort by date automatically. Reviewing a week-by-week sequence in rapid succession reveals patterns that individual photos obscure. A gradual deepening of redness is different from a sudden onset of patchy involvement. The former tracks with expected progression. The latter suggests a new variable entering the equation. Backup the photos immediately. Cloud storage is sufficient. Local storage fails. I have lost patient records to corrupted hard drives and failed phone upgrades. An automatic cloud backup running in the background costs nothing and prevents catastrophic data loss.
Share images securely with the oncology team. Standard text messages and consumer email platforms are not compliant with patient privacy regulations in most jurisdictions. Use the patient portal or a secure medical imaging platform. The extra thirty seconds of setup prevents serious compliance issues and ensures the treating physician sees the same images you do.